A Seizure on a Normal Drug Level
Why the parent drug reassures you and the metabolite does the damage
Visual reference
Open the visual review after completing the case
Browse the visual reference library · Download lesson Markdown
Presentation
A 47-year-old man on maintenance hemodialysis for diabetic nephropathy has been trying to quit smoking. Three weeks ago his primary care physician started bupropion sustained-release 150 mg daily. He is also on carvedilol 12.5 mg twice daily, insulin, and sevelamer.
He is brought in after a witnessed generalized tonic-clonic seizure at home. He has no seizure history, no alcohol use, and no head trauma. Glucose was 118 at the scene.
Workup
Sodium 138 · calcium and magnesium normal · non-contrast head CT unremarkable. He had dialysed the previous day with a normal run. A send-out bupropion level returns within the usual therapeutic range. BP is 168/96, up from his usual 140s.
Questions
The bupropion level is 'normal.' Why does that not exclude bupropion toxicity in this patient?
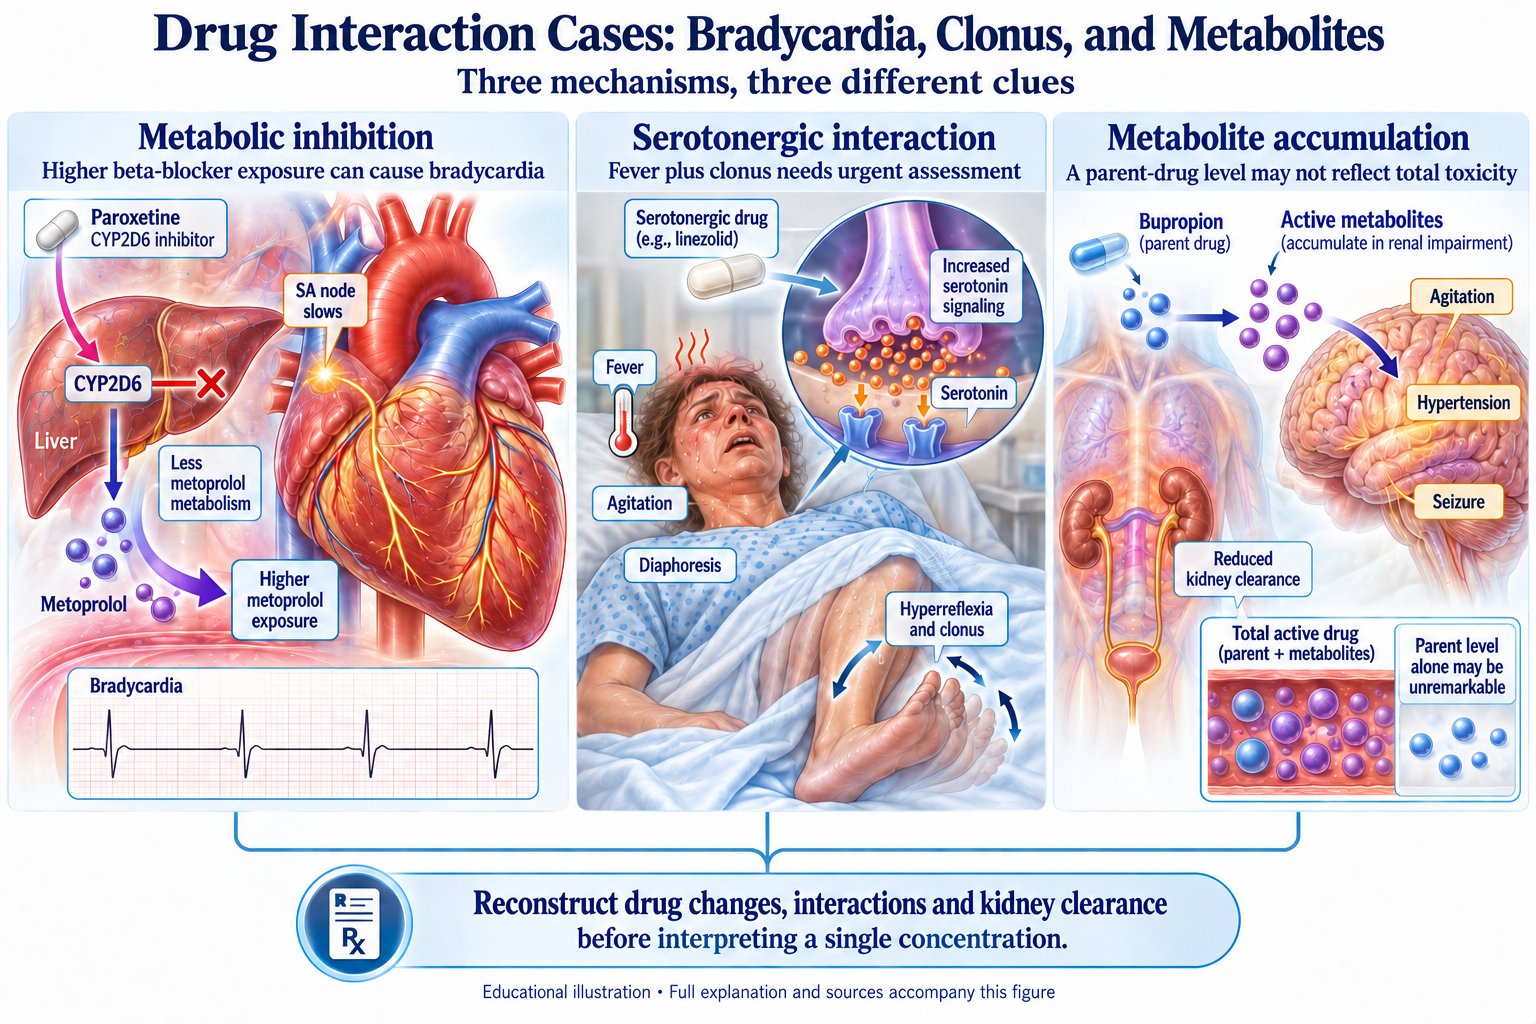
Learning Point: In the only dedicated hemodialysis study, parent bupropion pharmacokinetics resembled normal renal function, but the metabolites hydroxybupropion and threohydrobupropion showed increased AUC, indicating accumulation. Hydroxybupropion is pharmacologically active, and bupropion's dose-dependent toxicities — seizure-threshold reduction, agitation, blood-pressure elevation — track total exposure. Measuring only the parent drug is falsely reassuring.
📚 Reference: Clinical Mastery: Psychotropic and ADHD Medications in Hypertension and CKD — Section 3
Which regimen did the small single-dose hemodialysis study propose for further evaluation?
Learning Point: The small single-dose pharmacokinetic study proposed 150 mg every 3 days; this answer identifies the authors’ proposal, not a validated universal dialysis prescription. It does not prove daily dosing gives three times the appropriate exposure. Product labeling recommends considering lower dose and/or frequency in renal impairment and monitoring adverse effects. Metabolite accumulation and limited dialysis clearance warrant specialist/pharmacist review; do not assume an after-dialysis schedule solves the problem.
📚 Reference: Student Handout — Section 7
His blood pressure has also risen from the 140s to 168/96. Which TWO bupropion properties could contribute?
Learning Point: Bupropion raises blood pressure through norepinephrine reuptake inhibition — the same NET mechanism that governs the whole drug family — and the effect is dose- and exposure-related, so metabolite accumulation amplifies it. Option A names a real interaction in the wrong direction: bupropion inhibiting CYP2D6 would raise carvedilol levels, which would tend to lower blood pressure and heart rate, not raise them. Bupropion has no meaningful serotonergic activity.
📚 Reference: Lecture: Psychiatric & ADHD Medications and Blood Pressure
Independent of the seizure, what interaction should have been flagged when bupropion was started in this patient?
Learning Point: Bupropion is a potent CYP2D6 inhibitor, and carvedilol is a CYP2D6 substrate — the same interaction class as paroxetine with metoprolol. This is the most commonly missed feature of bupropion's profile, precisely because it is often prescribed for smoking cessation by a clinician who is not managing the cardiac medications.
📚 Reference: Clinical Mastery: Psychotropic and ADHD Medications in Hypertension and CKD — Section 6.2
Take-Home
A normal level is not a safe level
When a drug has active metabolites cleared by the kidney, measuring the parent compound tells you very little in renal failure. Bupropion is the clean example, but the principle generalizes — think of it whenever an assay reassures you and the patient does not.
Honest limitation: the dialysis pharmacokinetic study had only 8 patients and used a single dose, and the authors explicitly called for a multi-dose study. It is thin evidence. It is also the only direct evidence there is, and it points one direction — which is exactly the situation in which you should say so out loud rather than quote the number as if it were settled.
Andrew Bland, MD, FACP, FAAP
Medical Associates Department of Nephrology · University of Illinois College of Medicine at Peoria · University of Dubuque PA & DPT Programs · Butler College of Osteopathic Medicine
Interactive teaching case · Psychotropic & ADHD Medications and Blood Pressure
© 2026 · urinenephrology.org