Visual reference
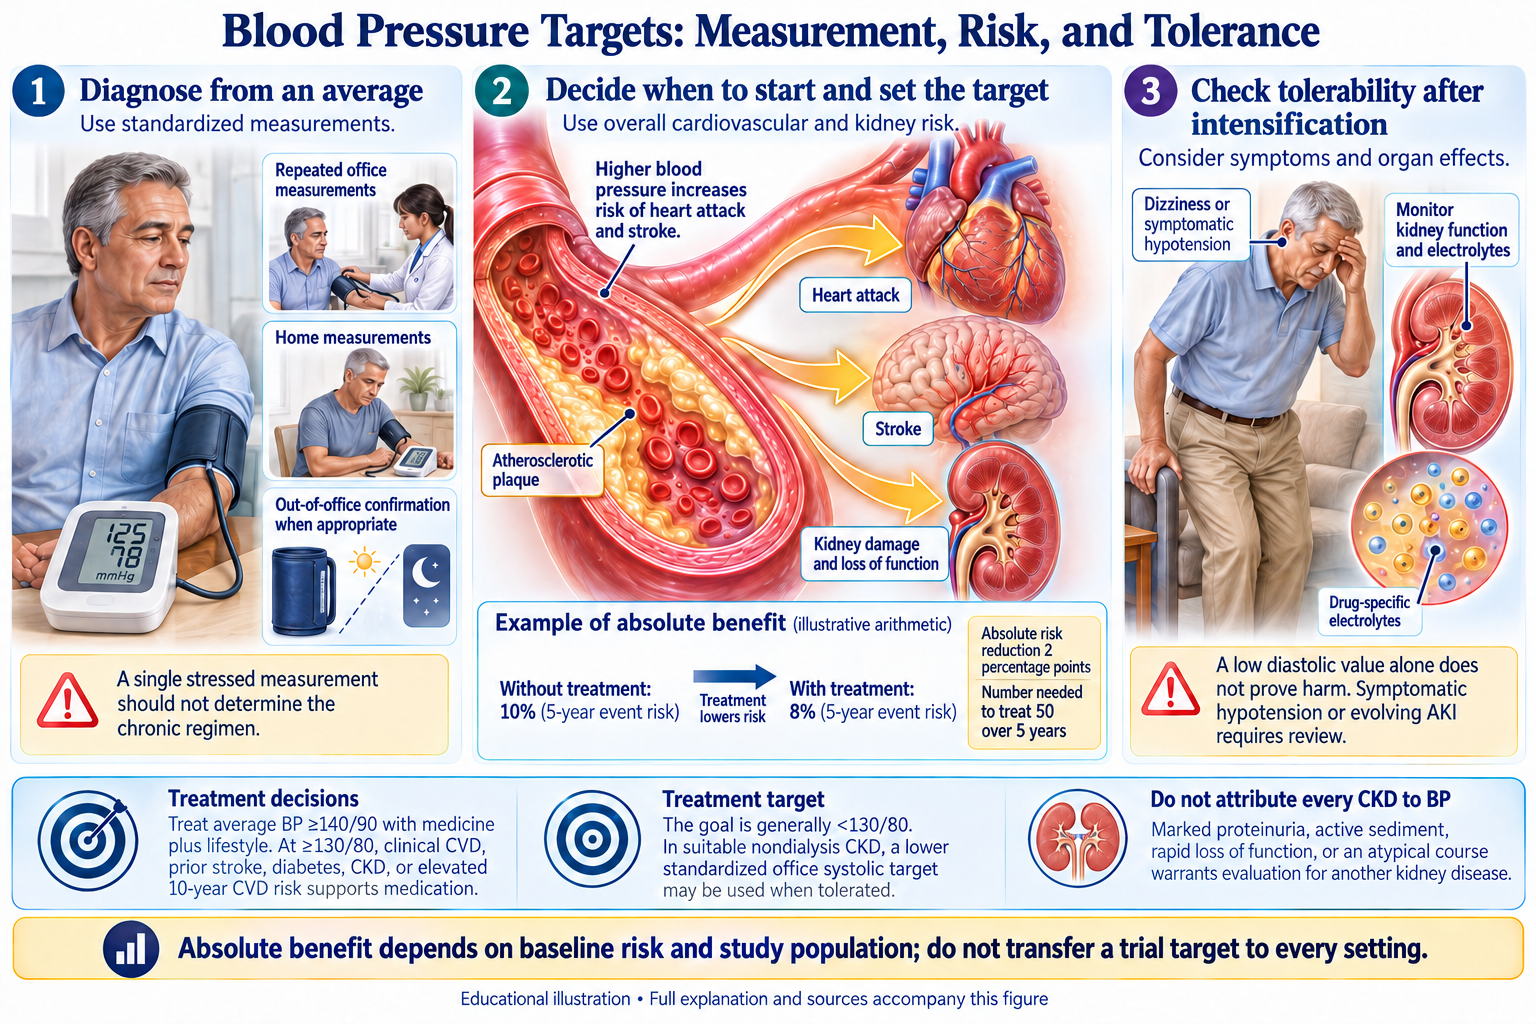
Browse the visual reference library · Download lesson Markdown
🎯 Key Target Principles
📊 Cardiovascular Risk Reduction by BP Level
| Per 10 mmHg SBP Reduction | Outcome | Relative Risk Reduction | Hazard Ratio | Source |
|---|---|---|---|---|
| 10 mmHg ↓ SBP | Major CV events (composite) | 20% | HR 0.80 (95% CI 0.77-0.83) | Ettehad 2016 PMID 26724178 |
| Coronary heart disease | 17% | HR 0.83 (95% CI 0.78-0.88) | Ettehad 2016 | |
| Stroke | 27% | HR 0.73 (95% CI 0.68-0.77) | Ettehad 2016 | |
| Heart failure | 28% | HR 0.72 (95% CI 0.67-0.78) | Ettehad 2016 | |
| BPLTTC 2021 (Rahimi et al., Lancet 397:1625-1636, PMID 33933205) — individual-patient meta-analysis (n=344,716, 48 trials): per 5 mmHg SBP reduction, major CV event HR 0.91 (95% CI 0.89-0.94) in primary prevention and 0.89 (0.86-0.92) in secondary prevention — approximately 10% RRR per 5 mmHg, with relative effect consistent across baseline SBP strata from <120 to ≥170 mmHg. Companion age-stratified analysis (Lancet 2021;398:1053-1064, PMID 34461040) extended this finding to age groups: HR 0.82 (<55y), 0.91 (55-84y), 0.99 (≥85y). Together these confirm the constant-RRR pattern of Ettehad 2016 across baseline BP, baseline CV history, and age (with attenuation only in the ≥85y subgroup). | ||||
Implication for absolute risk: a patient with starting SBP 180 and 10-year CV risk 30% gets larger absolute benefit from 10 mmHg reduction (ARR approximately 6 percentage points per decade) than a patient with starting SBP 140 and 10-year CV risk 5% (ARR approximately 1 percentage point per decade) — even though RRR is the same approximately 20%. The "diminishing returns" pedagogy is correct at the absolute-benefit level but does not reflect a true falloff in relative effect. Tailor target-intensity decisions to baseline absolute risk, not relative effect estimates.
🔬 Major Trial Evidence
💪 SPRINT Trial - Intensive vs Standard
- Population: High-risk non-diabetic patients (N=9,361)
- Targets: <120 mmHg vs <140 mmHg systolic
- Primary Outcome: 25% relative risk reduction
- Absolute Benefit: 1.6% over 3.26 years (2.5% over 5 years)
- NNT: 61 to prevent one primary outcome event
- Mortality Benefit: 27% relative reduction, 1.2% absolute
👴 STEP Trial - Elderly Patients
- Population: Chinese adults age 60-80 years (N=8,511)
- Targets: SBP 110-130 mmHg vs 130-150 mmHg
- Primary Outcome: HR 0.74 (26% relative risk reduction)
- Absolute Benefit: ARR approximately 1.1% over 3.34 years (event rate 3.5% intensive vs 4.6% standard); NNT 91
- Key Finding: Confirmed benefit of intensive BP control extends to elderly Chinese population
- Source: Zhang W et al. NEJM 2021;385(14):1268-1279, PMID 34491661
🧠 SPRINT-MIND - Cognitive Outcomes
- Cognitive Focus: Mild cognitive impairment prevention
- Result: 19% reduction in mild cognitive impairment
- Brain Health: Intensive BP control preserves cognition
- Dementia: Trend toward reduced dementia risk
- Implications: Brain protection beyond cardiovascular benefits
- Age Consideration: Midlife hypertension particularly harmful
⚖️ Intensive Targets: Benefits vs Risks
✅ Benefits of <120 mmHg Target
SPRINT Trial as published (3.26-year follow-up; SPRINT primary paper Wright NEJM 2015, PMID 26551272)
- All-cause mortality: HR 0.73, ARR 1.2% (NNT 83)
- Primary CV composite: HR 0.75, ARR 1.6% (NNT 61)
- Heart failure: HR 0.62 (38% RRR)
- Cognitive protection (SPRINT-MIND): HR 0.81 for MCI (19% RRR)
- Renal outcomes: Slower eGFR decline in non-CKD subset; mixed in baseline CKD
⚠️ Risks of <120 mmHg Target
SPRINT Trial Adverse Events as published (3.26-year follow-up)
- Hypotension/syncope/AKI/electrolyte SAEs: HR approximately 1.33–1.67 in intensive arm (statistically significant)
- Falls with injury: HR 1.00 — NO increase, including in SPRINT-Senior subgroup ≥75y
- Acceptable safety profile for the absolute risk magnitudes given the cardiovascular benefit
👥 Population-Specific Target Recommendations
🌟 High-Risk Patients
Target: <130/80 mmHg (Class 1 Recommendation)
- Established CVD: CAD, stroke, PAD, heart failure
- Diabetes Mellitus: Type 1 or 2 with any complications
- CKD with Albuminuria: ≥30 mg/g albumin/creatinine ratio
- 10-Year CVD Risk ≥10%: Based on PREVENT calculator
- Evidence: Consistent benefit across multiple trials
- Monitoring: More frequent follow-up required
👴 Elderly Patients (>80 years)
Target: Individualized, Often 140-150 mmHg Systolic
- Frailty Assessment: Consider functional status and life expectancy
- Comorbidity Burden: Multiple conditions may limit benefit
- Fall Risk: Orthostatic hypotension prevention priority
- Cognitive Function: Severe dementia may preclude intensive targets
- Goals of Care: Quality of life vs longevity considerations
- Gradual Approach: Slow titration to avoid complications
🫀 Special Cardiac Conditions
Target: Condition-Specific Considerations
- CAD with Wide PP: Avoid diastolic <70 mmHg
- Heart Failure: <130/80 mmHg if tolerated
- Aortic Stenosis: Careful reduction to maintain perfusion
- Hypertrophic Cardiomyopathy: Avoid excessive reduction
- Post-MI: <130/80 mmHg for secondary prevention
- Atrial Fibrillation: Consider stroke risk in target selection
🫘 Chronic Kidney Disease
Target: <130/80 mmHg Across All CKD Stages
- Unified Approach: Same target regardless of CKD stage
- Albuminuria: RAAS inhibition mandatory if present
- eGFR Monitoring: 30% increase acceptable with RAAS inhibitors
- Progression Prevention: BP control slows CKD advancement
- CVD Protection: Reduced cardiovascular events
- Dialysis Patients: Individualized based on fluid status
🌡️ Diastolic Blood Pressure Considerations
📈 Age-Related Changes
- Young Adults (<50): Diastolic BP equally important predictor
- Middle Age (50-59): Systolic becomes predominant
- Elderly (≥60): Only systolic BP remains significant predictor
- Mechanism: Arterial stiffening with aging
- Pulse Pressure: Widens progressively with age
- Clinical Focus: Shift emphasis to systolic in elderly
⚠️ Wide Pulse Pressure Risks
- Definition: Pulse pressure ≥60 mmHg (some use ≥70 mmHg)
- Prevalence: 42% in patients ≥65 years with hypertension
- J-Curve Risk: Diastolic <70 mmHg with CAD increases events
- Coronary Perfusion: Occurs primarily during diastole
- High-Risk Groups: CAD, diabetes, age >75 years
- Management: Target systolic while avoiding low diastolic
🧮 Blood Pressure Target Calculator
Determine appropriate BP target based on patient characteristics
🎯 Practical Implementation Strategies
📈 Stepwise Approach to Target Achievement
- Initial Goal: <140/90 mmHg for all patients
- Secondary Goal: <130/80 mmHg if tolerated
- Intensive Goal: <120 mmHg systolic in selected patients
- Monitoring Frequency: Every 2-4 weeks during titration
- Medication Adjustment: Add/increase every 2-4 weeks
- Plateau Phase: Monthly monitoring once stable
🏥 Clinical Monitoring Guidelines
- Home BP Monitoring: Essential for accurate assessment
- Laboratory Monitoring: Electrolytes, creatinine every 2-4 weeks
- Symptom Assessment: Dizziness, fatigue, syncope
- Adherence Evaluation: Pill counts, pharmacy records
- Lifestyle Reinforcement: Diet, exercise, weight management
- Complication Screening: Target organ damage assessment
🚫 When to Avoid Intensive Targets
⚠️ Absolute Contraindications
- Symptomatic Hypotension: Dizziness, falls, syncope
- Severe Orthostatic Hypotension: >20/10 mmHg drop
- Limited Life Expectancy: <2-3 years prognosis
- Severe Frailty: High fall risk, cognitive impairment
- Medication Intolerance: Multiple drug allergies/intolerances
- Patient Preference: Informed refusal of intensive therapy
🤔 Relative Contraindications
- Advanced Age: >85 years without clear benefit
- Multiple Comorbidities: Complex medical conditions
- Polypharmacy: >10 medications with interaction risk
- Cognitive Impairment: Moderate-severe dementia
- Recent Stroke: Within 3 months, individualize
- Social Factors: Poor follow-up, medication access issues
📋 Evidence-Based Target Selection Algorithm
🎯 Systematic Approach to BP Target Selection
📚 Sources
- Ettehad D, Emdin CA, Kiran A, et al. Blood pressure lowering for prevention of cardiovascular disease and death: a systematic review and meta-analysis. Lancet. 2016;387(10022):957-967. PMID: 26724178. [Source for: per-10-mmHg constant RRR — major CV events HR 0.80, CHD HR 0.83, stroke HR 0.73, heart failure HR 0.72; n=613,815, 123 trials.]
- Rahimi K, et al; Blood Pressure Lowering Treatment Trialists' Collaboration. Pharmacological blood pressure lowering for primary and secondary prevention of cardiovascular disease across different levels of blood pressure: an individual participant-level data meta-analysis. Lancet. 2021;397(10285):1625-1636. PMID: 33933205. [Source for: constant-RRR finding across baseline SBP strata; primary vs secondary prevention HR 0.91 vs 0.89 per 5 mmHg; n=344,716, 48 trials.]
- Rahimi K, et al; Blood Pressure Lowering Treatment Trialists' Collaboration. Age-stratified and blood-pressure-stratified effects of blood-pressure-lowering pharmacotherapy for the prevention of cardiovascular disease and death: an individual participant-level data meta-analysis. Lancet. 2021;398(10305):1053-1064. PMID: 34461040. [Source for: age-stratified effects — HR 0.82 (<55y) to 0.99 (≥85y); n=358,707, 51 trials.]
- SPRINT Research Group; Wright JT Jr, Williamson JD, Whelton PK, et al. A Randomized Trial of Intensive versus Standard Blood-Pressure Control. N Engl J Med. 2015;373(22):2103-2116. PMID: 26551272. [Source for: SPRINT primary outcome HR 0.75 (25% RRR), all-cause mortality HR 0.73 (27% RRR), heart failure HR 0.62, NNT 61 over 3.26 years; N=9,361.]
- Zhang W, Zhang S, Deng Y, et al. Trial of Intensive Blood-Pressure Control in Older Patients with Hypertension (STEP). N Engl J Med. 2021;385(14):1268-1279. PMID: 34491661. [Source for: STEP primary composite HR 0.74 (26% RRR); event rate 3.5% intensive vs 4.6% standard over 3.34 years → ARR approximately 1.1%, NNT approximately 91; N=8,511 Chinese adults age 60-80.]
- Williamson JD, Pajewski NM, Auchus AP, et al; SPRINT MIND Investigators. Effect of Intensive vs Standard Blood Pressure Control on Probable Dementia: SPRINT MIND. JAMA. 2019;321(6):553-561. PMID: 30688979. [Source for: SPRINT-MIND mild cognitive impairment HR 0.81 (19% RRR); dementia trend non-significant.]
- Whelton PK, Carey RM, Aronow WS, et al. 2017 ACC/AHA Guideline for the Prevention, Detection, Evaluation, and Management of High Blood Pressure in Adults. Hypertension. 2018;71(6):e13-e115. PMID: 29133356. [Source for: Class 1 <130/80 target for high-risk patients, intensive <120 target indications.]
- Cameron NA, Jones DW, Khan SS, Lloyd-Jones DM. Case-Based Applications of the 2025 AHA/ACC/Multispecialty High Blood Pressure Guideline. Hypertension. 2025;82(12):2055-2063. PMID: 41204807. [Source for: 2025 AHA/ACC update reaffirms targets and risk-based approach; PREVENT calculator replaces pooled cohort equations.]