Systemic AL Amyloidosis with Cardiac and Renal Involvement
Inpatient Case Report and Clinical Decision Framework
Medical Associates Department of Nephrology | University of Illinois College of Medicine at Peoria | Butler College of Osteopathic Medicine
Andrew Bland, MD, FACP, FAAP
Visual reference
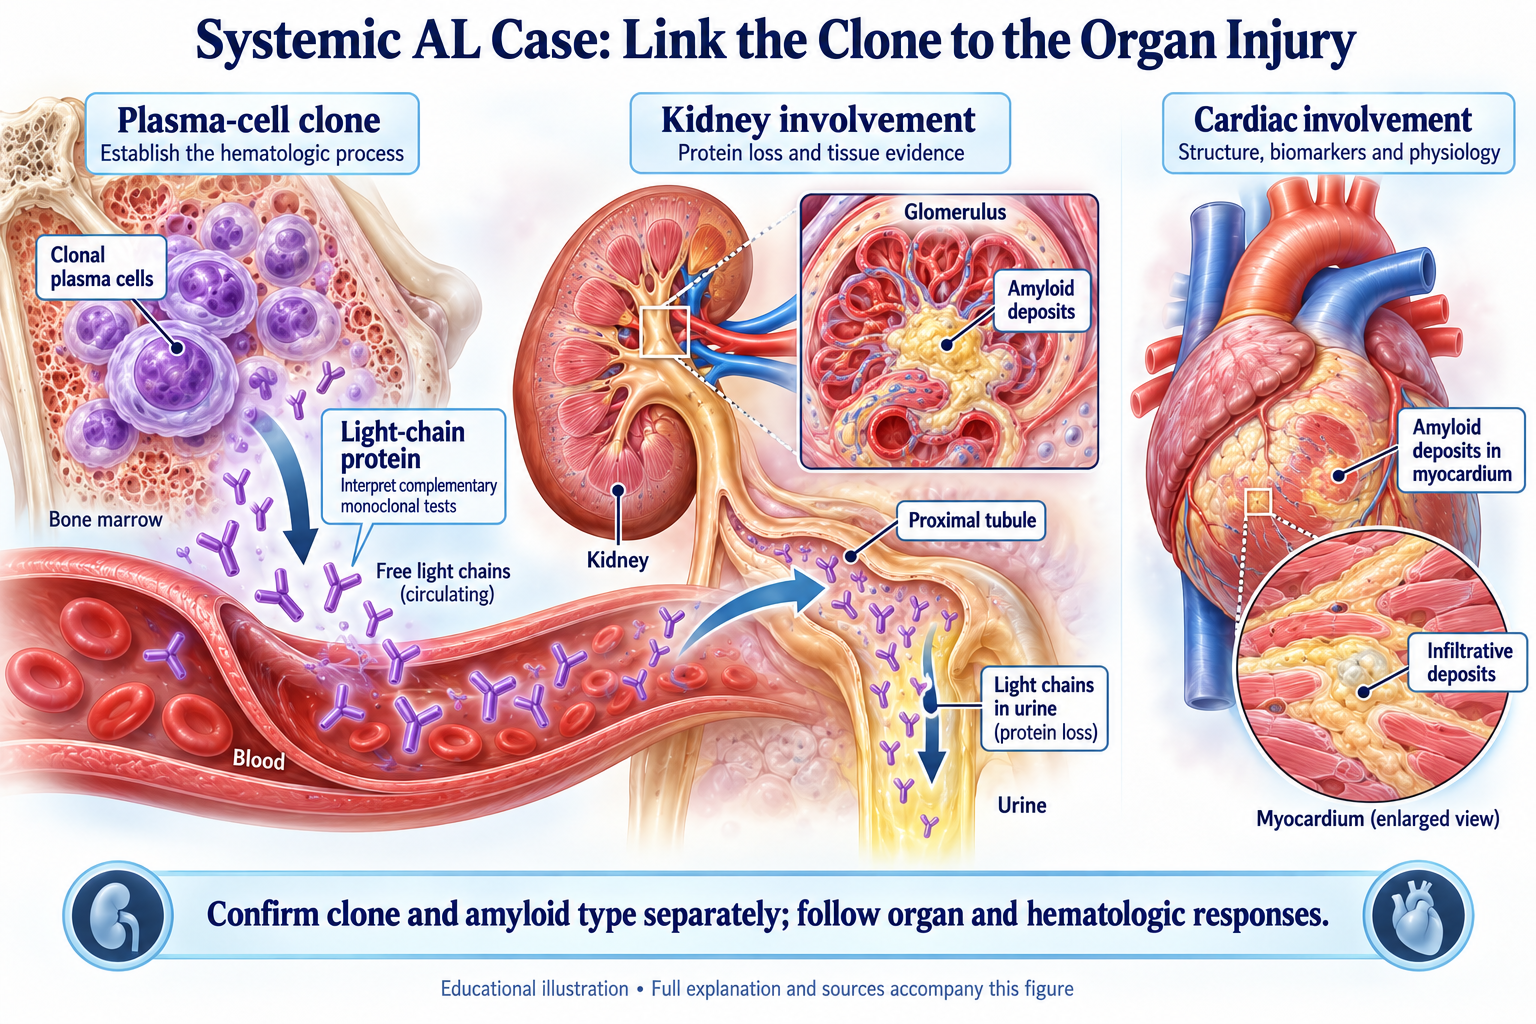
Browse the visual reference library · Download lesson Markdown
Executive Summary
Key Points - A patient presenting with massive albuminuria (protein/Cr 7.9), hypoalbuminemia, 3+ edema, and worsening renal function should prompt immediate evaluation for plasma cell dyscrasia regardless of the absence of CRAB features. - Free light chains reported as kappa 17.4 / lambda 3.24 / ratio 5.37 in mg/dL correspond to kappa 174 mg/L and lambda 32.4 mg/L in standard units — both the ratio and the absolute kappa are elevated above the renal-adjusted reference range, raising concern for a clonal kappa-dominant process that requires immunofixation and tissue correlation (1,2). - BNP 4,598 pg/mL and troponin I 59 ng/L with echocardiographic LVH, impaired relaxation, and EF 45% meet criteria for advanced cardiac involvement. This is an oncologic and cardiorenal emergency (3). - The differential diagnosis in a kappa-dominant FLC pattern with nephrotic-range albuminuria is led by Light Chain Deposition Disease (LCDD), followed by kappa AL amyloidosis; kidney biopsy is the only test that resolves this distinction (4). - Daratumumab, bortezomib, cyclophosphamide, and dexamethasone (Dara-VCd) is the FDA-approved standard of care for newly diagnosed AL amyloidosis, established in the phase 3 ANDROMEDA trial (5). - Multi-disciplinary care involving nephrology, cardiology, and hematology/oncology with amyloid expertise is required within 24 hours of biomarker confirmation.
1. Case Presentation
1.1 Presenting Clinical Data
The patient presented with a clinical syndrome characterized by progressive renal insufficiency and volume overload in the setting of prior evaluation by an outside oncologist for severe anemia. The following data were collected at the time of nephrology involvement:
Admission data: - Creatinine: 2.5 mg/dL (rising to 4.0 with aggressive diuresis) - Bicarbonate: 21 mEq/L (mild metabolic acidosis) - Albumin: 3.1 g/dL - Hemoglobin: 8.2 g/dL (prior range 7–9 g/dL, worked up by outside oncology) - Platelets: 192 × 10³/µL (normal) - Calcium: 8.8 mg/dL (normal) - Edema: 3+ bilateral - Urine albumin-to-creatinine ratio: >4 - Urine protein-to-creatinine ratio: 7.9 - Volume response: Minimal fluid removed with aggressive loop diuretic therapy; creatinine worsened
Subsequent evaluation: - Free light chain kappa: 17.4 mg/dL (= 174 mg/L) - Free light chain lambda: 3.24 mg/dL (= 32.4 mg/L) - κ/λ ratio: 5.37 - Echocardiogram: EF 45%, LVH, impaired relaxation (Grade I–II diastolic dysfunction) - BNP: 4,598 pg/mL - Troponin I: 59 ng/L - Monoclonal evaluation: Pending at time of nephrology consultation (no prior SPEP, immunofixation, or FLC had been obtained)
1.2 Initial Clinical Impression
The combination of massive albuminuria, hypoalbuminemia, preserved platelet count, normal calcium, and absent bone pain placed this patient outside the classical CRAB (hypercalcemia, renal failure, anemia, bone lesions) framework of symptomatic multiple myeloma. The outside oncologic workup had not specifically addressed plasma cell dyscrasia with renal-organ manifestation. Nephrology involvement reframed the presentation from “anemia workup with CKD” to a potential monoclonal gammopathy of renal significance (MGRS) or systemic AL amyloidosis.
2. Proteinuria Phenotyping — Glomerular Disease, Not Cast Nephropathy
The urine protein/Cr of 7.9 with albumin/Cr >4 establishes that the proteinuria is albumin-predominant and glomerular in origin. This is the first and most diagnostically decisive point in the case.
Differential by proteinuria phenotype:
| Feature | Cast Nephropathy (Myeloma Kidney) | Glomerular Amyloid / LCDD |
|---|---|---|
| Primary pathology | Distal tubular casts | Mesangial/GBM fibril or non-fibrillar deposits |
| Proteinuria type | Bence Jones (light chains) | Albumin-dominant |
| Urine dipstick | Trace or negative (misses light chains) | 3-4+ positive |
| Serum albumin | Usually preserved | Low — hypoalbuminemia |
| FLC threshold | Typically >500–1,500 mg/L | Often lower (<500 mg/L) |
| Volume physiology | Variable | Oncotic-driven underfilling |
Cast nephropathy presents with predominantly tubular proteinuria and low albumin excretion, often with a trace-positive or negative dipstick despite elevated total protein, because standard urine dipstick detects albumin rather than immunoglobulin light chains. This patient’s pattern — heavy dipstick-positive, albumin-rich proteinuria with hypoalbuminemia and massive edema — is the inverse of that phenotype and confirms glomerular rather than tubular injury as the primary lesion (6).
Clinical Pearl: When a patient with a suspected plasma cell dyscrasia has 3-4+ dipstick proteinuria with hypoalbuminemia and edema, the lesion is glomerular (amyloid, LCDD, or membranoproliferative pattern), not tubular cast nephropathy. Aggressive loop diuresis without this distinction risks AKI from intravascular depletion in a patient who cannot refill from the interstitium due to insufficient oncotic pressure.
3. Free Light Chain Interpretation in Renal Failure
3.1 Unit Conversion — A Critical Potential Error Source
Serum free light chains are measured and reported in mg/L at most reference laboratories, including Mayo Clinic. When values are reported in mg/dL (as in this case), conversion is mandatory before clinical interpretation:
1 mg/dL = 10 mg/L
| Analyte | Reported (mg/dL) | Converted (mg/L) | Standard Reference (mg/L) |
|---|---|---|---|
| Kappa (κ) | 17.4 | 174 | 3.3–19.4 |
| Lambda (λ) | 3.24 | 32.4 | 5.7–26.3 |
| κ/λ Ratio | 5.37 | 5.37 | 0.26–1.65 |
The kappa of 174 mg/L is approximately 9× the upper limit of normal. The lambda of 32.4 mg/L is only mildly above the standard reference upper limit, and this mild elevation is entirely attributable to reduced renal clearance (kappa clears faster than lambda in normal renal function; impaired GFR raises both proportionally, but the smaller monomer kappa typically rises more in CKD as a non-clonal artifact).
3.2 Renal-Adjusted Reference Range
The standard κ/λ FLC reference range (0.26–1.65) was established in patients with normal renal function. In CKD, differential renal clearance of κ vs. λ light chains alters the ratio independent of clonality. The extended reference range for renal impairment is approximately 0.37–3.1. This patient’s ratio of 5.37 exceeds the renal-adjusted upper limit of 3.1, confirming a true clonal process rather than a CKD artifact (1,2).
3.3 Delta FLC (dFLC) Calculation
The dFLC (involved minus uninvolved FLC) = 174 − 32.4 = 141.6 mg/L
The measured dFLC is 174 − 32.4 = 141.6 mg/L, below the Mayo 2012 dFLC threshold of 180 mg/L. Heavy total proteinuria does not quantify urinary light-chain loss and cannot justify increasing the measured dFLC or treating it as an underestimated floor. Stage with the actual required biomarkers and assay definitions.
⚠️ Warning: In patients with heavy nephrotic-range proteinuria, serum FLC levels are spuriously lowered by urinary losses. The degree of clonal disease burden is likely greater than the serum FLC values imply. Do not use the dFLC alone to assess clone burden in this setting.
4. Differential Diagnosis — Kappa-Dominant FLC Pattern
The kappa-dominant FLC pattern changes the differential hierarchy compared to a lambda-dominant presentation. Lambda accounts for approximately 70–75% of AL amyloidosis cases, while kappa predominates in multiple myeloma (approximately 60–65%). A kappa-dominant low-burden clonal process with nephrotic-range albuminuria and absent CRAB features raises the following diagnoses in order of probability:
1. Light Chain Deposition Disease (LCDD) — Leading Diagnosis LCDD most commonly involves kappa light chains (approximately 60–70% of LCDD cases), producing a non-fibrillar, Congo red–negative glomerular deposit along the GBM and mesangium. Presentation is nephrotic-range albuminuria with preserved or mildly reduced GFR and absent CRAB features — precisely this patient’s profile at baseline presentation. The Vκ4 and Vλ6 germline gene subsets are overrepresented in LCDD. LCDD deposits are non-fibrillar and will be Congo red negative on biopsy, differentiating LCDD from AL amyloidosis.
2. Kappa AL Amyloidosis — Close Second Kappa AL amyloidosis accounts for approximately 25–30% of AL cases. Kappa AL tends to have more hepatic involvement compared to lambda AL (which is more associated with cardiac and renal organ tropism), though renal amyloid deposition does occur. Congo red staining of kidney biopsy will be positive with apple-green birefringence under polarized light if this is the diagnosis.
3. MGRS-class disease — Broadest Category Either of the above may represent a Monoclonal Gammopathy of Renal Significance (MGRS) — renal disease caused by a clonal immunoglobulin that does not meet criteria for overt myeloma. A nephrologist who identifies a monoclonal protein in the setting of unexplained renal disease should not assume the paraprotein is an innocent MGUS simply because the M-protein is small and the marrow involvement is <10%. Renal biopsy is essential to determine whether the monoclonal protein is directly causing renal injury (7).
SLiM Myeloma-Defining Criteria Assessment:
The involved/uninvolved FLC ratio criterion for a myeloma-defining biomarker event requires ≥100 (kappa direction). This patient’s ratio of 5.37 does not meet that threshold. This does not diminish the urgency of evaluation; MGRS-class disease causes dialysis-driving renal failure from clones that by definition do not qualify as myeloma.
Do not wait for overt myeloma criteria before investigating possible monoclonal organ injury. Abnormal free light chains with heavy proteinuria raise concern but do not prove the clone caused the renal lesion. Confirm with immunofixation and appropriate tissue examination, including reliable amyloid typing when amyloid is found; disease-directed treatment follows the established lesion.
5. Cardiac Evaluation — Confirmed Advanced Involvement
5.1 Biomarker Staging
| Measured finding | Value | Interpretation |
|---|---|---|
| BNP | 4,598 pg/mL | Markedly elevated; not interchangeable with NT-proBNP |
| High-sensitivity troponin I | 59 ng/L | Requires assay-specific interpretation |
| Formal cardiac stage | Not established here | Confirm amyloid diagnosis and required biomarkers |
The reported BNP and high-sensitivity troponin I indicate a concerning cardiac phenotype but are not interchangeable with the NT-proBNP and specified troponin assays of another staging system. Confirm amyloid diagnosis and apply a validated assay-specific scheme before assigning a stage or stage-based prognosis. CKD also affects biomarker interpretation.
An important caveat: this patient has a creatinine of 4.0 mg/dL. Natriuretic peptides are renally cleared, and NT-proBNP in particular rises as a function of reduced GFR. However, a BNP of 4,598 pg/mL far exceeds what renal failure alone produces. Published data suggest that in impaired renal function (CKD Stage III+), BNP thresholds for cardiac amyloid involvement shift to approximately 427 pg/mL — still orders of magnitude below this patient’s value. The biomarker elevation is cardiac, not purely renal (8).
5.2 Echocardiographic Reinterpretation
The echocardiogram showing EF 45%, LVH, and impaired relaxation was initially framed as hypertensive heart disease. The biomarker and hemodynamic findings warrant reassessment for infiltrative and other causes; a formal stage remains unconfirmed:
- EF 45% in cardiac amyloidosis does not represent mild systolic dysfunction — it represents the transition point where systolic reserve is becoming exhausted. Early cardiac amyloidosis presents with preserved EF; declining EF below 50% reflects progression into the systolic failure phase.
- “LVH” in amyloidosis is infiltrative pseudohypertrophy — amyloid fibrils depositing in the myocardial interstitium — not true myocyte hypertrophy driven by pressure overload. These walls appear thick but are physiologically hostile: stiff, non-compliant, and dependent on elevated filling pressures to maintain stroke volume.
- The echocardiogram should be re-read with a dedicated amyloid protocol including: posterior wall + septal thickness, mitral annular velocity (e’), E/e’ ratio, and most importantly global longitudinal strain (GLS) with apical sparing pattern. The relative apical sparing pattern on strain imaging (Bull’s-eye map) is highly specific for cardiac amyloidosis (sensitivity and specificity both exceeding 80%).
⚠️ Warning: A patient with suspected cardiac amyloidosis and EF 45% has already lost significant systolic reserve. Standard heart failure medications that reduce preload (aggressive diuretics), afterload (ACE-inhibitors, ARBs), or heart rate (beta-blockers, non-dihydropyridine calcium channel blockers) may be poorly tolerated or harmful. Cardiology co-management with amyloid expertise is required before titrating any cardiac medications.
5.3 The European IIIB Substage
The European modification of the Mayo staging system subdivides Stage III into IIIA (NT-proBNP 332–8,500 ng/L or BNP equivalent) and IIIB (NT-proBNP >8,500 ng/L). BNP and NT-proBNP are different molecules and not interchangeable by simple ratio, but a BNP of 4,598 pg/mL corresponds to a very high-risk profile. Whether this patient meets IIIB criteria requires NT-proBNP confirmation. Stage IIIB disease carries a median survival of approximately 5 months — the extreme high-risk category where speed of hematologic response is the dominant modifiable outcome predictor.
6. Renal Staging (Palladini 2014 System)
The Palladini renal staging system stratifies risk of progression to dialysis using two thresholds: eGFR <50 mL/min/1.73m² and 24-hour proteinuria >5 g/day (9).
| Risk Factor | Patient Status |
|---|---|
| eGFR <50 mL/min/1.73m² | YES — Cr 4.0, eGFR estimated 15–20 mL/min |
| Proteinuria >5 g/day | YES — Protein/Cr 7.9, consistent with >15–20 g/day |
| Renal Stage | Stage III (both adverse criteria present) |
Patients with Palladini Renal Stage III have a 60–85% probability of requiring dialysis within 3 years at diagnosis; this patient is presenting at Palladini Stage III with an acutely rising creatinine (9). If AL amyloidosis is confirmed, cardiac and renal risk must be staged separately using each system’s required measurements.
Clinical Pearl: The 5-year cumulative incidence of renal replacement therapy for Stage III patients in revised staging models approaches 51%. This does not mean dialysis is inevitable — rapid and deep hematologic response to Dara-VCd can halt amyloid production and allow gradual clearance of fibril deposits. However, the window for meaningful renal recovery is time-dependent and narrows with further injury.
7. The Diuresis Problem — Cardiorenal Physiology of Amyloidosis
7.1 Why Diuresis Failed
Creatinine rising from 2.5 to 4.0 during aggressive loop diuretic therapy with minimal fluid removal is the pathognomonic hemodynamic signature of advanced cardiorenal amyloidosis:
- Oncotic failure: With albumin at 3.1 g/dL, plasma oncotic pressure is insufficient to draw interstitial edema fluid back into the intravascular compartment. Diuresis removes intravascular volume faster than it can be refilled.
- Stiff ventricle dependence on preload: The amyloid-infiltrated left ventricle requires elevated filling pressures to maintain stroke volume. Reduction of preload through diuresis drops cardiac output, reducing renal perfusion.
- Tubular light chain toxicity: Loop diuretics concentrate tubular fluid, potentially increasing tubular light chain concentration and promoting Tamm-Horsfall protein binding — the same mechanism driving cast nephropathy. In a patient with heavy kappa light chain burden, aggressive furosemide may simultaneously worsen tubular injury.
7.2 Right Heart Catheterization — The Case For and Against
The diagnostic question (is this cardiac amyloidosis?) is answered. RHC is not needed to establish the diagnosis.
The management question (how do we safely manage volume?) remains open. RHC is justified to define: - Cardiac output and index (CI <2.0 L/min/m² confirms low-output state driving pre-renal AKI) - Right atrial pressure and PCWP (defining safe operating filling pressures) - Pulmonary vascular resistance (relevant if cardiac transplant consideration arises later)
If CI is markedly reduced, the appropriate response is not diuretic escalation but rather a shift to slow ultrafiltration or continuous renal replacement therapy with carefully defined net negative fluid removal rates that the ventricle can tolerate.
⚠️ Warning: Screen for Factor X deficiency before any invasive procedure. Systemic AL amyloid fibrils adsorb and sequester clotting Factor X, producing an acquired Factor X deficiency in up to 14% of AL amyloidosis patients. This causes procedure-related hemorrhage risk independent of platelet count and INR. A Factor X activity level should be sent before kidney biopsy or RHC.
8. Tissue Diagnosis — Required, Not Optional
Kidney biopsy is necessary to differentiate between the entities with identical laboratory profiles but distinct pathology and treatment nuance:
| Finding | AL Amyloidosis | LCDD |
|---|---|---|
| Congo red stain | Positive — apple-green birefringence under polarized light | Negative |
| Electron microscopy | Fibrils 8–12 nm, randomly arranged | Non-fibrillar, organized, granular deposits |
| Immunofluorescence | Restricted light chain (Congo red confirms fibril) | Linear kappa or lambda staining along GBM |
| Mass spectrometry amyloid typing | Required — confirms AL vs. AA vs. ATTR | N/A |
| Treatment implication | Dara-VCd | Clone-directed therapy (similar but biopsy defines urgency) |
Abdominal fat pad biopsy is a less invasive alternative with approximately 60–80% sensitivity for systemic AL amyloidosis. It can be performed bedside and may yield a positive result while awaiting definitive kidney biopsy, or if kidney biopsy is deferred due to coagulopathy concerns.
Bone marrow biopsy is required for clone characterization, cytogenetics, and assessment of plasma cell percentage — all of which define transplant eligibility and inform chemotherapy selection.
9. Treatment Framework
9.1 Standard of Care: Dara-VCd
The ANDROMEDA phase 3 randomized controlled trial established daratumumab, bortezomib, cyclophosphamide, and dexamethasone (Dara-VCd) as the first FDA-approved therapy for newly diagnosed AL amyloidosis (January 2021). In 388 patients, the addition of subcutaneous daratumumab to VCd resulted in a hematologic complete response rate of 53.3% versus 18.1% in the VCd-alone arm, with significantly superior survival free from major organ deterioration or hematologic progression (5).
Key ANDROMEDA eligibility nuances relevant to this patient: - Patients with cardiac Stage IIIB (NT-proBNP >8,500 ng/L) were excluded from ANDROMEDA — this patient’s NT-proBNP equivalent needs verification - eGFR ≥20 mL/min was required — this patient’s current eGFR is borderline - Symptomatic multiple myeloma (meeting CRAB criteria) was an exclusion
These nuances underscore why a hematologist with specific AL amyloidosis expertise — not general oncology — is required for treatment planning. The dosing of bortezomib and cyclophosphamide, the management of fluid overload from IV infusions, and the decision-making around early mortality risk all require specialized experience.
9.2 Three Pillars of Outcome Improvement
Three pillars have been identified for improving AL amyloidosis outcomes: 1. Early disease recognition before advanced organ damage — partially failed here (delayed diagnosis with Cr already 4.0 and concerning cardiac involvement) 2. Rapid and deep hematologic response — the dominant modifiable variable going forward 3. Comprehensive multi-specialty supportive care — cardiology, nephrology, hematology working in parallel, not sequentially
9.3 Supportive Care Considerations
- Diuresis: Hold or dramatically reduce; if volume management is mandatory, consider ultrafiltration after RHC-guided hemodynamic assessment.
- Albumin infusions: Physiologically intuitive but not proven to improve outcomes; may precipitate pulmonary edema if cardiac function is compromised — use with caution and only with cardiac monitoring.
- Avoid: ACE inhibitors, ARBs, beta-blockers, non-dihydropyridine calcium channel blockers (poorly tolerated with amyloid cardiomyopathy).
- Coagulopathy surveillance: Factor X level, CBC, INR before procedures.
- Renal support: If creatinine continues to rise and the patient cannot tolerate adequate fluid removal for pulmonary protection, early renal replacement therapy planning should begin.
10. Priority Diagnostic and Management Checklist
Immediate (within 24 hours): - [ ] Hematology/oncology consultation — amyloid-experienced center preferred - [ ] Cardiology consultation with dedicated amyloid echo re-read (GLS, strain imaging) - [ ] NT-proBNP to complement BNP (define IIIA vs. IIIB status) - [ ] Factor X activity level (pre-procedure coagulopathy screen) - [ ] Serum immunofixation + urine immunofixation (characterize M-protein isotype) - [ ] 24-hour urine protein (formal Palladini renal staging) - [ ] Alkaline phosphatase (hepatic amyloid screening)
Within 48–72 hours: - [ ] Bone marrow biopsy (clone characterization, cytogenetics, plasma cell percentage) - [ ] Kidney biopsy (or fat pad biopsy as interim) - [ ] RHC consideration (hemodynamic-guided volume management) - [ ] Echocardiogram with dedicated amyloid protocol including GLS - [ ] Nerve conduction study if neuropathic symptoms present - [ ] Consider cardiac MRI if echocardiogram is technically limited
Pending test to follow specifically: - [ ] Serum and urine immunofixation — characterize heavy/light chain of M-protein - [ ] MASS-FIX (if accessible via Mayo) for superior sensitivity to conventional SPEP
11. Summary
This case represents systemic AL amyloidosis (or LCDD — tissue biopsy will distinguish) with confirmed multi-organ involvement. The key diagnostic milestones and their clinical implications are:
The albumin-rich proteinuria, abnormal free-light-chain ratio, kidney decline, and severe cardiac findings warrant urgent coordinated evaluation. They do not by themselves establish amyloid type or a validated Mayo cardiac stage. Complete serum/urine immunofixation, tissue diagnosis and typing when indicated, and the exact biomarkers required for the selected staging system. Manage congestion and perfusion while hematology, cardiology, and nephrology clarify the cause.
References
Dispenzieri A, Kyle RA, Katzmann JA, et al. Immunoglobulin free light chain ratio is an independent risk factor for progression of smoldering (asymptomatic) multiple myeloma. Blood. 2008;111(2):785-789. doi:10.1182/blood-2007-08-108357. PMID: 17942755
Hutchison CA, Plant T, Drayson M, et al. Serum free light chain measurement aids the diagnosis of myeloma in patients with severe renal failure. BMC Nephrol. 2008;9:11. doi:10.1186/1471-2369-9-11. PMID: 18808676
Dispenzieri A, Gertz MA, Kyle RA, et al. Serum cardiac troponins and N-terminal pro-brain natriuretic peptide: a staging system for primary systemic amyloidosis. J Clin Oncol. 2004;22(18):3751-3757. doi:10.1200/JCO.2004.03.029. PMID: 15365071
Palladini G, Hegenbart U, Milani P, et al. A staging system for renal outcome and early markers of renal response to chemotherapy in AL amyloidosis. Blood. 2014;124(15):2325-2332. doi:10.1182/blood-2014-04-570010. PMID: 25115890
Kastritis E, Palladini G, Minnema MC, et al. Daratumumab-based treatment for immunoglobulin light-chain amyloidosis. N Engl J Med. 2021;385(1):46-58. doi:10.1056/NEJMoa2028631. PMID: 34192431
Leung N, Bridoux F, Batuman V, et al. The evaluation of monoclonal gammopathy of renal significance: a consensus report of the International Kidney and Monoclonal Gammopathy Research Group. Nat Rev Nephrol. 2019;15(1):45-59. doi:10.1038/s41581-018-0077-4. PMID: 30510265
Rajkumar SV, Dimopoulos MA, Palumbo A, et al. International Myeloma Working Group updated criteria for the diagnosis of multiple myeloma. Lancet Oncol. 2014;15(12):e538-e548. doi:10.1016/S1470-2045(14)70442-5. PMID: 25439696
Lilleness B, Ruberg FL, Mussinelli R, Doros G, Sanchorawala V. Development and validation of a survival staging system incorporating BNP in patients with light chain amyloidosis. Blood. 2019;133(3):215-223. PMID: 30333122
Kumar S, Dispenzieri A, Lacy MQ, et al. Revised prognostic staging system for light chain amyloidosis incorporating cardiac biomarkers and serum free light chain measurements. J Clin Oncol. 2012;30(9):989-995. doi:10.1200/JCO.2011.38.5724. PMID: 22331953
Merlini G, Dispenzieri A, Sanchorawala V, et al. Systemic immunoglobulin light chain amyloidosis. Nat Rev Dis Primers. 2018;4(1):38. doi:10.1038/s41572-018-0034-3. PMID: 30361521
Also on this topic
The same subject at other levels of depth.
- Clinical Mastery deep dive: Systemic AL Amyloidosis with Cardiac and Renal Involvement