Visual reference
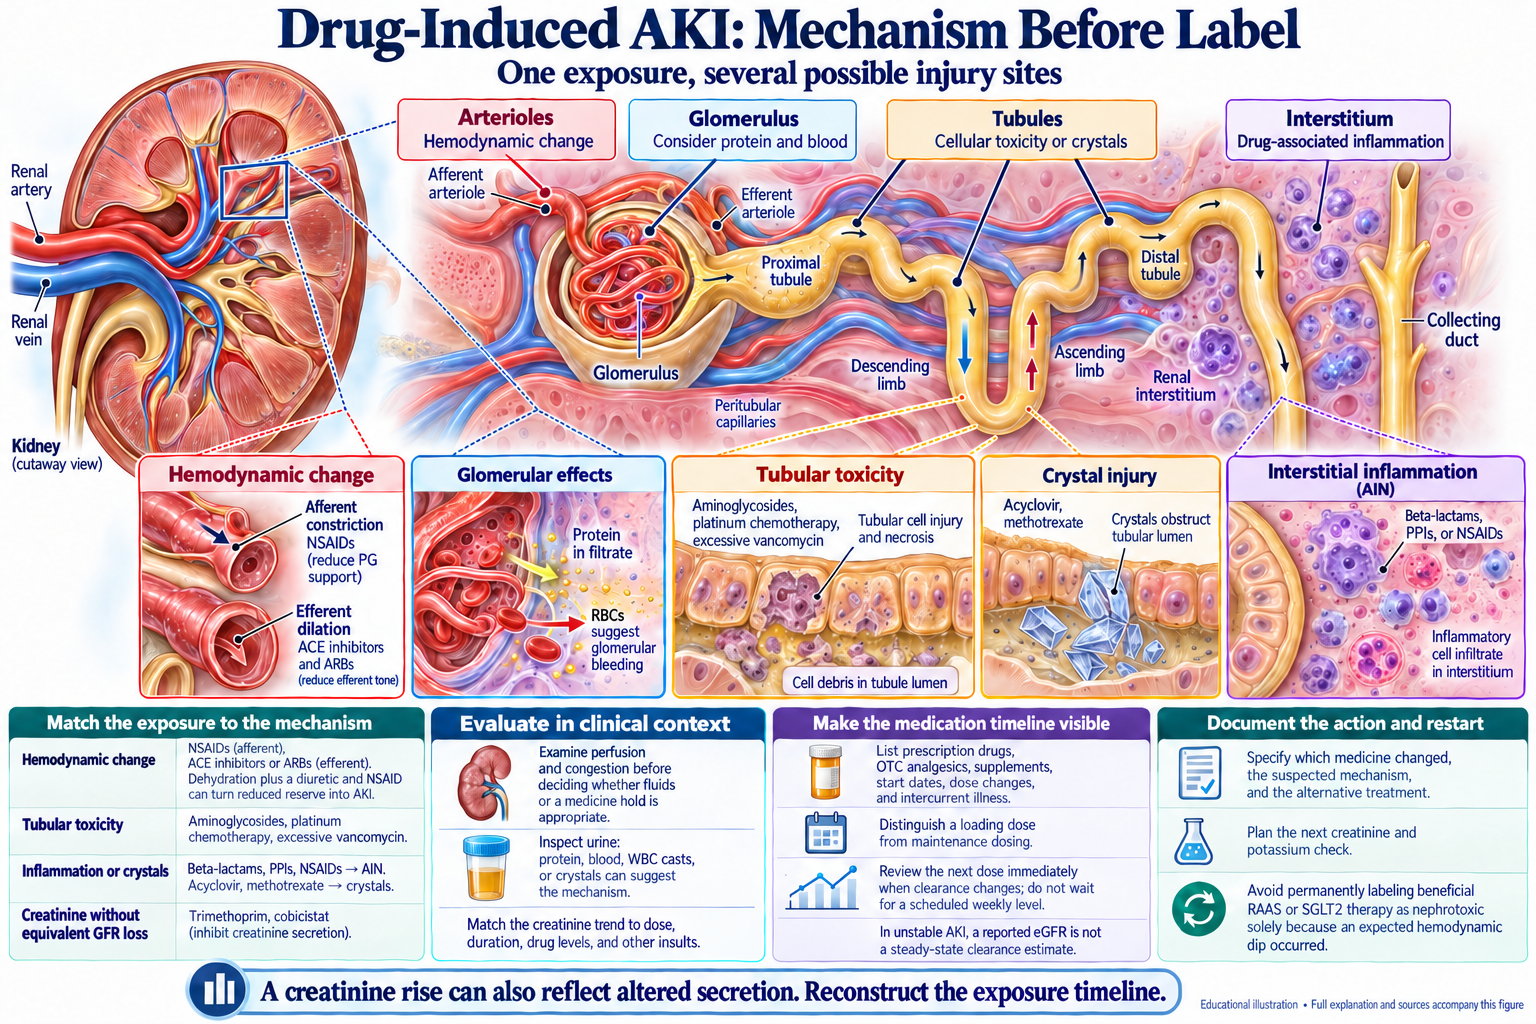
Browse the visual reference library · Download lesson Markdown
A clinical framework
Antimicrobials can cause kidney injury, alter electrolyte handling, or raise serum creatinine without reducing filtration. These are different problems. A patient receiving an antibiotic may also have sepsis, hypotension, obstruction, congestion, or another nephrotoxic exposure. Establish the clinical pattern before attributing every creatinine increase to the drug.
Three patterns are especially useful: tubular injury after a nephrotoxic exposure; immune-mediated acute interstitial nephritis (AIN); and intratubular precipitation or crystal injury. Drug interactions and altered creatinine secretion add further complexity. More than one mechanism can occur in the same patient. Urine microscopy, potassium and bicarbonate trends, drug levels when indicated, and the exposure timeline help narrow the differential.
Effective infection treatment remains essential. The practical goal is to use an active antibiotic at an appropriate exposure, remove avoidable toxicity, and reassess as cultures and kidney function change. An alternative with inadequate antimicrobial activity can be more dangerous than a monitored nephrotoxic agent. Decisions about substitution, biopsy, or kidney replacement therapy require the entire clinical picture.
Sources: Perazella, 2022 · Morales-Alvarez, 2020.
Aminoglycosides
Gentamicin, tobramycin, and amikacin can accumulate in proximal tubular cells and cause tubular injury. Risk depends on exposure, treatment duration, baseline kidney function, critical illness, and other nephrotoxic drugs. A rise in creatinine may occur after several days of treatment, but a fixed onset day is not a reliable diagnostic rule. Injury may be nonoliguric, so preserved urine output does not establish safety.
Granular casts or tubular epithelial cells support tubular injury when present; their absence does not exclude it. Electrolyte wasting may accompany tubular dysfunction. Consider sepsis-related injury and hemodynamic factors in parallel. Published ICU cohorts describe associations with toxicity in selected populations; their incidence estimates should not be treated as universal risks for every course of therapy.
Use a regimen appropriate to the infection and patient, with pharmacokinetic monitoring where indicated. Extended-interval dosing is suitable for some indications and populations, but it is not a universal replacement for every conventional regimen. Reassess dosing promptly when kidney function changes, limit unnecessary duration, and avoid additional nephrotoxins when feasible. Stop or replace the agent if toxicity outweighs its antimicrobial benefit.
Sources: Morales-Alvarez, 2020 · Oliveira, 2009.
Glycopeptides and vancomycin
Vancomycin-associated kidney injury may involve tubular oxidative stress and apoptosis, interstitial nephritis, and drug-associated casts. Experimental mechanisms help explain injury but do not establish that a particular antioxidant or pathway inhibitor prevents clinical AKI. The likelihood of injury rises with excessive exposure and may be affected by illness severity, duration, and concurrent nephrotoxins.
For serious MRSA infection, the 2020 consensus recommends targeting a vancomycin AUC/MIC of 400–600, assuming an MIC of 1 mg/L by broth microdilution. AUC-guided dosing is preferred to using a trough of 15–20 mg/L as the sole exposure target in that setting. These recommendations should not be generalized automatically to every organism or mild infection. Pharmacy-supported estimation is particularly useful when kidney function is unstable.
Check the dose and sampling history before interpreting a concentration. A high level can contribute to injury, but declining clearance can also raise the level. Follow both exposure and kidney function, reassess the need for vancomycin, and select an effective alternative when warranted. Other glycopeptides have different pharmacokinetics and adverse-effect profiles; a single class-wide risk percentage is misleading.
Sources: Pais, 2020 · Rybak, 2020.
Beta-lactams and interstitial nephritis
Penicillins and cephalosporins are important causes of drug-associated AIN. Fever, rash, and eosinophilia may occur, but the classic combination is often absent. Pyuria, hematuria, or modest proteinuria can be clues; none is diagnostic by itself. Urine eosinophils are not a dependable rule-in or rule-out test. Kidney biopsy may be needed when the diagnosis remains uncertain or would change treatment.
Withdrawal of the likely culprit is the first step when clinically feasible. Maintain effective infection coverage while avoiding unnecessary re-exposure. Whether and when to use corticosteroids depends on the probability of AIN, biopsy findings, infection control, and the balance of potential benefit and harm. Evidence should not be described as proving one universal steroid schedule or recovery percentage.
Beta-lactams can also cause problems beyond AIN. Certain high-exposure regimens can produce crystal-associated injury, and accumulation of renally cleared agents can cause nonrenal toxicity. Cefepime neurotoxicity is a relevant consideration when choosing an alternative in impaired kidney function. Renal dosing must be reassessed repeatedly during evolving AKI and recovery, rather than copied from a single admission estimate.
Sources: Perazella, 2022 · Raghavan, 2014.
Polymyxins
Colistin and polymyxin B can cause clinically important tubular toxicity. Their use generally reflects a need to treat resistant organisms, making both antimicrobial efficacy and toxicity central to the decision. They are not interchangeable drugs: formulations, pharmacokinetics, dose units, and the influence of kidney function differ. Colistimethate sodium is a prodrug, which adds particular complexity to prescribing and interpretation of exposure.
The international polymyxin consensus provides dosing and monitoring recommendations. It is a consensus guideline, not a randomized trial or a cohort proving a particular hazard ratio. Consult the appropriate formulation-specific guidance and involve infectious-disease and pharmacy specialists. When susceptibility and clinical circumstances permit, consider effective alternatives with a more favorable toxicity profile.
Monitor kidney function and avoid unnecessary nephrotoxic combinations. A creatinine rise warrants reassessment of exposure, hemodynamics, and other causes of AKI; it does not by itself identify a specific cellular death pathway. Preclinical findings about oxidative stress, mitochondria, or apoptosis should remain clearly distinguished from therapies shown to benefit patients.
Sources: Tsuji, 2019 · Morales-Alvarez, 2020.
Fluoroquinolones
Fluoroquinolone-associated kidney injury is less predictable than a simple dose-toxicity relationship. Reported patterns include interstitial nephritis and crystal-related injury. Observational research has found an association between oral fluoroquinolone exposure and AKI in the studied population. Such an association supports vigilance but cannot determine the cause of an individual patient's AKI or establish identical risk across all agents.
Assess the timing of treatment, volume status, other medications, urine findings, and alternative explanations. Adjust dosing when required by the selected agent and kidney function. Avoid assuming that a normal initial creatinine eliminates later risk. Conversely, do not diagnose AIN solely because an antibiotic was started before the creatinine rose.
If injury is suspected, review whether the drug is still needed and whether a suitable alternative exists. Improvement after withdrawal supports a drug contribution but is not definitive proof, especially when sepsis or dehydration is also resolving. Persistent or severe kidney dysfunction should prompt a broader evaluation rather than repeated empirical antibiotic substitutions.
Sources: Bird, 2013 · Morales-Alvarez, 2020.
Trimethoprim and sulfonamides
Trimethoprim can inhibit tubular creatinine secretion and increase serum creatinine without a corresponding fall in true GFR. This effect is distinct from structural kidney injury. An isolated creatinine change with a compatible timeline may reflect altered secretion, but oliguria, a concerning urine sediment, or other evidence of injury should not be dismissed as a laboratory artifact.
Trimethoprim also reduces distal potassium excretion through an amiloride-like effect. Hyperkalemia can occur even when the creatinine increase is largely due to altered secretion. Risk is greater with impaired kidney function and interacting medicines, including ACE inhibitors, ARBs, and potassium-sparing agents. Check potassium and kidney function according to the patient's risk and clinical course, particularly after initiation or dose changes.
The sulfamethoxazole component can contribute to AIN or crystal-associated injury. Thus, “trimethoprim raises creatinine” is not a complete explanation for every AKI during trimethoprim-sulfamethoxazole treatment. Review volume status, drug exposure, potassium, urinalysis, and other causes. Management depends on the mechanism and on whether the antimicrobial remains necessary.
Sources: Berglund, 1975 · Perazella, 2000 · Antoniou, 2010 · Perazella, 2022.
Tetracyclines
Tetracyclines differ in their elimination and adverse-effect profiles. Doxycycline is commonly useful when renal impairment limits other options, but that does not make every tetracycline interchangeable or every adverse event impossible. Use the specific drug's dosing information and consider hepatic function, infection site, interactions, and the patient's other risks.
Historical reports of tubular dysfunction with degraded tetracycline products should not be presented as the expected behavior of properly stored modern doxycycline. Rare drug-associated interstitial nephritis remains part of a broad medication differential. A proximal tubular pattern, when present, requires a search for the full range of possible causes rather than attribution to a class name alone.
During suspected toxicity, establish the actual product, dose, duration, and exposure history. Avoid unsupported comparative rankings that assign precise kidney-injury probabilities to doxycycline, minocycline, and older tetracyclines without comparable study populations. The general response remains recognition of injury, review of the medication, and maintenance of effective infection treatment.
Sources: Cunha, 1982 · Perazella, 2022.
Macrolides, ketolides, and interactions
For macrolides, a medication interaction may be more clinically important than direct tubular toxicity. Clarithromycin inhibits CYP3A4 and can increase exposure to susceptible co-medications. In an older-adult cohort receiving calcium-channel blockers, clarithromycin co-prescription was associated with more AKI than azithromycin co-prescription. This study concerns a defined interaction and population; it does not prove that all macrolides directly injure the kidney to the same extent.
In transplant recipients, review interactions with calcineurin inhibitors and other immunosuppressants. Elevated concentrations can contribute to toxicity, while unplanned dose reduction can compromise immunosuppression. Coordinate drug selection, concentration monitoring, and dose changes with the transplant team. Azithromycin has fewer CYP3A4 effects than clarithromycin, but an interaction review is still appropriate.
Assess blood pressure and volume status if kidney function worsens after adding an interacting antibiotic. Other causes, including infection and obstruction, remain possible. Ketolides should be evaluated individually using their own safety and prescribing information rather than being assigned the risk profile of a different macrolide.
Sources: Gandhi, 2013 · Jeong, 2019.
Other antimicrobial agents
Antifungals: Amphotericin B can impair renal blood flow and injure tubules, producing AKI and potassium or magnesium losses. Formulation matters: lipid formulations generally have a more favorable renal safety profile than conventional amphotericin B, but they can still cause toxicity. Monitor kidney function and electrolytes, address volume deficits appropriately, and choose the formulation and regimen in the context of the infection.
Antivirals: The mechanism varies by drug. Acyclovir can produce crystal-associated injury, particularly with excessive exposure or unfavorable administration conditions. Other antivirals can affect proximal tubular function. Prevention depends on correct dosing, appropriate administration, and attention to kidney function and hydration. A single toxicity percentage for “antivirals” is not meaningful.
Antimycobacterial and other agents: Rifampin can be associated with immune-mediated kidney injury, and additional antibiotics have uncommon renal adverse effects. The exposure and re-exposure history can be important. Also distinguish intrinsic nephrotoxicity from accumulation of a drug that is normally cleared by the kidney: AKI may increase the risk of neurological, hematologic, or other toxicity even when that drug did not cause the original injury.
Sources: Deray, 2002 · Morales-Alvarez, 2020 · Perazella, 2022.
Comparing patterns, not incompatible percentages
Comparisons across studies require caution. A creatinine-based AKI definition, a need-for-dialysis outcome, and biopsy-proven AIN measure different events. ICU cohorts, ambulatory treatment courses, and transplant populations have different baseline risks. Treatment duration and concurrent medications further limit direct comparison.
Aminoglycosides, vancomycin, polymyxins, and amphotericin B deserve attention for tubular toxicity. Beta-lactams and several other classes may trigger AIN. Trimethoprim adds the distinctive combination of inhibited creatinine secretion and impaired potassium excretion. Some drugs can precipitate in tubules or cause kidney injury through interactions. These patterns guide investigation; they are not mutually exclusive categories.
Time course is supportive rather than diagnostic. Prior sensitization, cumulative exposure, changing clearance, and the underlying illness can alter onset and recovery. Avoid rigid day-by-day stages or predictions of complete recovery based only on the antibiotic class. Follow the individual trajectory after treatment changes.
Sources: Morales-Alvarez, 2020 · Khalili, 2013.
Prevention and response to AKI
Before treatment, identify the infection, anticipated duration, baseline kidney function, and interacting drugs. Correct clinically important volume deficits without causing fluid overload. Select the narrowest effective regimen once microbiology allows. Use therapeutic drug monitoring for agents and situations in which it is established, and reassess dosing during both deterioration and recovery.
When AKI develops, evaluate hemodynamics, urine output, sediment, electrolytes, and the exposure timeline. Check for obstruction when appropriate. Stop avoidable nephrotoxins and reconsider the suspected culprit while preserving adequate infection treatment. Consult nephrology for severe or unexplained injury, difficult fluid or electrolyte problems, or a possible indication for biopsy.
Treat complications according to their severity. Kidney replacement therapy is considered for the usual clinical indications, including refractory electrolyte, acid-base, or volume problems and uremic complications; no antibiotic-specific creatinine threshold replaces that assessment. Corticosteroids are a selected AIN decision, not a general treatment for all antibiotic-associated AKI. Arrange follow-up of kidney function and medication safety after discharge.
Sources: Perazella, 2022 · Rybak, 2020 · Raghavan, 2014.
Combinations: association and causation
Observational studies and meta-analyses have associated vancomycin plus piperacillin-tazobactam with more creatinine-defined AKI than some comparator regimens. These data justify attention to exposure and patient risk, but residual confounding and differences in creatinine handling complicate interpretation.
In a prospective cohort, Miano and colleagues observed a creatinine signal without corresponding changes in cystatin C or evidence of higher dialysis or mortality risk. This supports the possibility that altered creatinine secretion explains part of the association, not a conclusion that every creatinine rise is harmless. In the ACORN randomized trial, piperacillin-tazobactam did not increase the primary AKI-or-death outcome compared with cefepime; cefepime was associated with more neurological dysfunction. Many participants were also receiving vancomycin. Trial setting and exposure duration matter when applying the findings.
For vancomycin-aminoglycoside, polymyxin-vancomycin, or other combinations, avoid assuming that a mechanistic concern proves a specific synergistic hazard ratio. Use combinations only when their antimicrobial benefit warrants them, monitor appropriately, and remove unnecessary components. The best alternative depends on pathogen coverage, kidney function, drug exposure, and competing adverse effects.
Sources: Luther, 2018 · Miano, 2022 · Qian, 2023.
Clinical takeaways
Recognize the pattern of injury, examine the exposure and interaction history, and keep other causes of AKI in view. Creatinine alone cannot distinguish tubular injury, AIN, altered secretion, and hemodynamic disease. Potassium changes, urine findings, drug levels, and the clinical course supply complementary information.
Use the evidence at its actual level: a cohort describes associations, a trial answers a defined comparison, a guideline synthesizes recommendations, and a laboratory experiment proposes mechanisms. None supplies a universal risk estimate for every patient. Effective antimicrobial treatment, thoughtful exposure control, and timely reassessment are the foundations of safer care.
Sources: Perazella, 2022 · Morales-Alvarez, 2020.
References
- Perazella MA, Rosner MH. Drug-Induced Acute Kidney Injury. Clin J Am Soc Nephrol. 2022;17(8):1220-1233. PubMed
- Morales-Alvarez MC. Nephrotoxicity of Antimicrobials and Antibiotics. Adv Chronic Kidney Dis. 2020;27(1):31-37. PubMed
- Oliveira JF, Silva CA, Barbieri CD, et al. Prevalence and risk factors for aminoglycoside nephrotoxicity in intensive care units. Antimicrob Agents Chemother. 2009;53(7):2887-2891. PubMed
- Pais GM, Liu J, Zepcan S, et al. Vancomycin-Induced Kidney Injury: Animal Models of Toxicodynamics, Mechanisms of Injury, Human Translation, and Potential Strategies for Prevention. Pharmacotherapy. 2020;40(5):438-454. PubMed
- Rybak MJ, Le J, Lodise TP, et al. Therapeutic monitoring of vancomycin for serious methicillin-resistant Staphylococcus aureus infections: A revised consensus guideline and review by the American Society of Health-System Pharmacists, the Infectious Diseases Society of America, the Pediatric Infectious Diseases Society, and the Society of Infectious Diseases Pharmacists. Am J Health Syst Pharm. 2020;77(11):835-864. PubMed
- Raghavan R, Eknoyan G. Acute interstitial nephritis - a reappraisal and update. Clin Nephrol. 2014;82(3):149-162. PubMed
- Tsuji BT, Pogue JM, Zavascki AP, et al. International Consensus Guidelines for the Optimal Use of the Polymyxins: Endorsed by the American College of Clinical Pharmacy (ACCP), European Society of Clinical Microbiology and Infectious Diseases (ESCMID), Infectious Diseases Society of America (IDSA), International Society for Anti-infective Pharmacology (ISAP), Society of Critical Care Medicine (SCCM), and Society of Infectious Diseases Pharmacists (SIDP). Pharmacotherapy. 2019;39(1):10-39. PubMed
- Bird ST, Etminan M, Brophy JM, et al. Risk of acute kidney injury associated with the use of fluoroquinolones. CMAJ. 2013;185(10):E475-E482. PubMed
- Berglund F, Killander J, Pompeius R. Effect of trimethoprim-sulfamethoxazole on the renal excretion of creatinine in man. J Urol. 1975;114(6):802-808. PubMed
- Perazella MA. Trimethoprim-induced hyperkalaemia: clinical data, mechanism, prevention and management. Drug Saf. 2000;22(3):227-236. PubMed
- Antoniou T, Gomes T, Juurlink DN, et al. Trimethoprim-sulfamethoxazole-induced hyperkalemia in patients receiving inhibitors of the renin-angiotensin system: a population-based study. Arch Intern Med. 2010;170(12):1045-1049. PubMed
- Cunha BA, Sibley CM, Ristuccia AM. Doxycycline. Ther Drug Monit. 1982;4(2):115-135. PubMed
- Gandhi S, Fleet JL, Bailey DG, et al. Calcium-channel blocker-clarithromycin drug interactions and acute kidney injury. JAMA. 2013;310(23):2544-2553. PubMed
- Jeong R, Quinn RR, Lentine KL, et al. Outcomes Following Macrolide Use in Kidney Transplant Recipients. Can J Kidney Health Dis. 2019;6:2054358119830706. PubMed
- Deray G. Amphotericin B nephrotoxicity. J Antimicrob Chemother. 2002;49 Suppl 1:37-41. PubMed
- Khalili H, Bairami S, Kargar M. Antibiotics induced acute kidney injury: incidence, risk factors, onset time and outcome. Acta Med Iran. 2013;51(12):871-878. PubMed
- Luther MK, Timbrook TT, Caffrey AR, et al. Vancomycin Plus Piperacillin-Tazobactam and Acute Kidney Injury in Adults: A Systematic Review and Meta-Analysis. Crit Care Med. 2018;46(1):12-20. PubMed
- Miano TA, Hennessy S, Yang W, et al. Association of vancomycin plus piperacillin-tazobactam with early changes in creatinine versus cystatin C in critically ill adults: a prospective cohort study. Intensive Care Med. 2022;48(9):1144-1155. PubMed
- Qian ET, Casey JD, Wright A, et al. Cefepime vs Piperacillin-Tazobactam in Adults Hospitalized With Acute Infection: The ACORN Randomized Clinical Trial. JAMA. 2023;330(16):1557-1567. PubMed
Reading the evidence
Evidence from clinical cohorts, randomized trials, pharmacokinetic studies, and experimental models answers different questions. Apply a source to the population, treatment, and outcome it actually studied.