Loop Diuretics in Acute Tubular Necrosis: A Comprehensive Review of Treatment, Prevention, and Diagnostic Applications
Visual reference
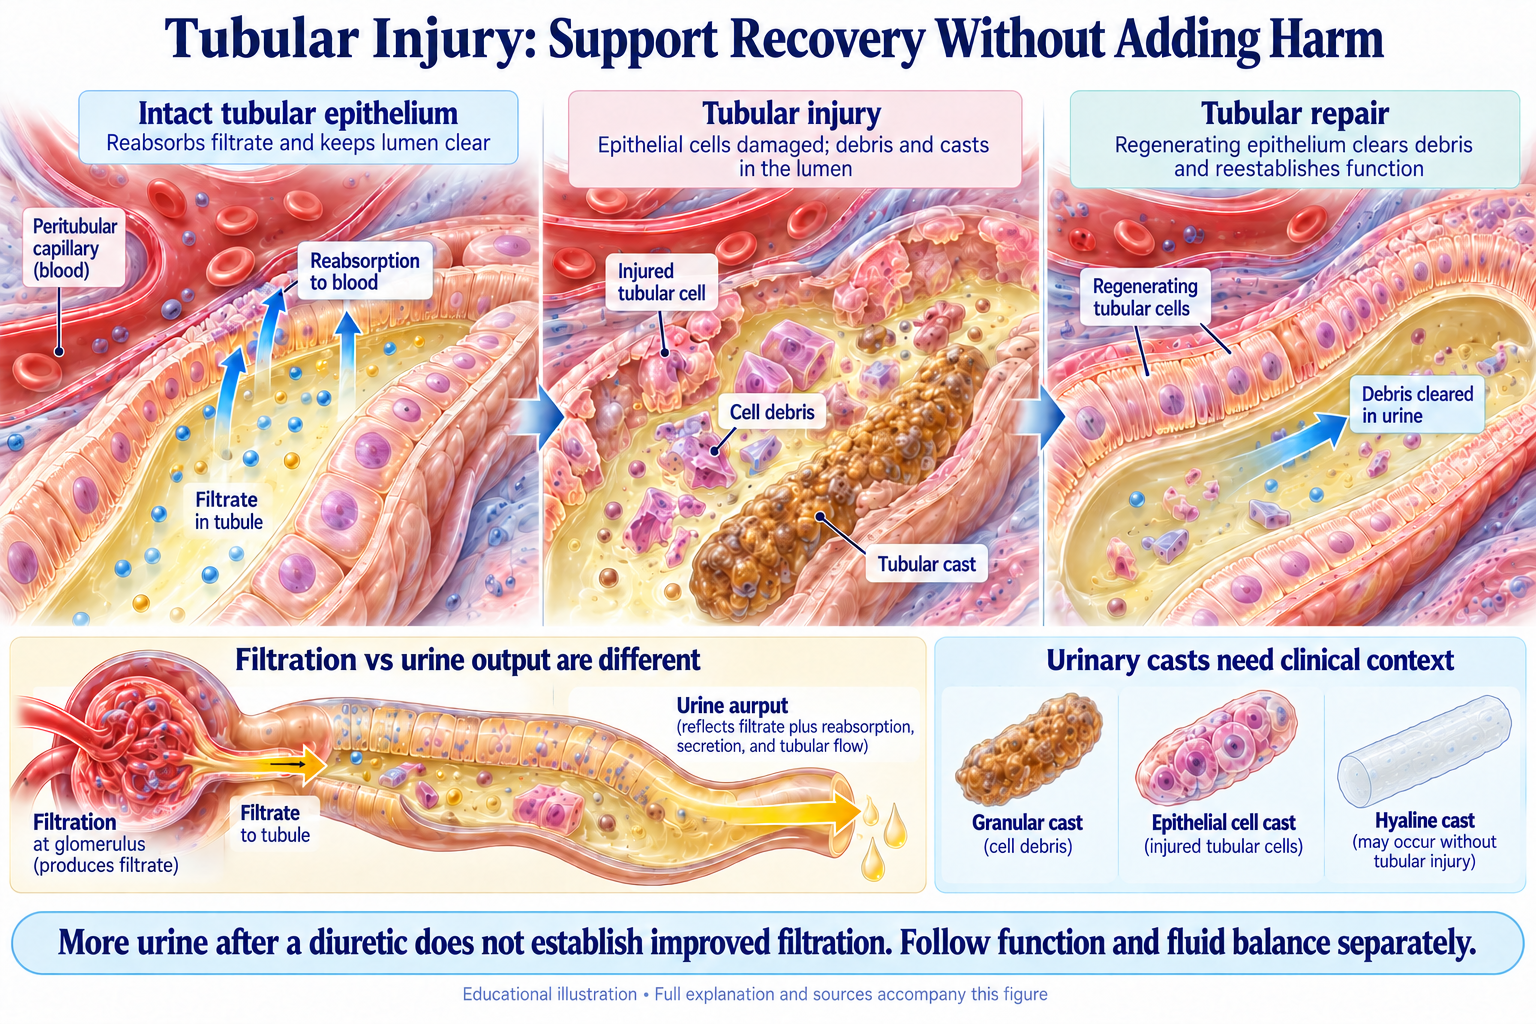
Browse the visual reference library · Download lesson Markdown
Executive Summary
🔗 Related Topics: AKI Workup, AKI Biomarkers, Heart Failure, Hyponatremia, Antibiotic-Induced AKI
Loop diuretics, particularly furosemide, have been extensively studied in the context of acute tubular necrosis (ATN) for both therapeutic and preventive applications. ATN represents a major component of acute kidney injury workup and frequently complicates heart failure management. While these agents possess theoretical mechanisms that could provide renal protection through energy conservation and tubular function optimization, clinical evidence demonstrates limited therapeutic benefit in established ATN. The evidence consistently shows that loop diuretics do not reduce mortality, accelerate renal recovery, or decrease dialysis requirements in patients with established ATN. However, emerging applications include the furosemide stress test as a validated diagnostic tool for risk stratification and the RenalGuard system for procedural nephroprotection. Current clinical practice should restrict loop diuretic use to volume management while recognizing their diagnostic utility in acute kidney injury assessment.
Introduction
Acute tubular necrosis represents the most common cause of intrinsic acute kidney injury in hospitalized patients and is associated with significant morbidity and mortality. The pathophysiology involves tubular cell damage and death resulting from ischemic or toxic events, leading to impaired renal function through multiple mechanisms including renal vasoconstriction, reduced glomerular capillary permeability, tubular obstruction, and transepithelial back-leak of filtrate. Loop diuretics have been employed in this clinical setting based on theoretical benefits derived from their mechanism of action, which includes inhibition of the sodium-potassium-chloride cotransporter in the thick ascending limb of Henle, resulting in reduced cellular energy demands and increased tubular flow.
The clinical application of loop diuretics in ATN encompasses three primary domains: treatment of established ATN, prevention in high-risk scenarios, and diagnostic risk stratification through functional testing. Each application requires distinct consideration of the available evidence, optimal protocols, and appropriate patient selection criteria.
Theoretical Foundation and Mechanisms of Action
Cytoprotective Mechanisms
Loop diuretics theoretically provide renal protection through several interconnected mechanisms. These agents decrease the metabolic demand of renal tubular cells by reducing their oxygen requirement, potentially increasing resistance to ischemia and other toxic insults¹. The inhibition of active sodium transport in the thick ascending limb of Henle reduces adenosine triphosphate utilization, thereby decreasing the net oxygen consumption of the kidney².
Reducing tubular transport may decrease oxygen demand, but biological plausibility does not establish a clinical kidney-protection effect or a known therapeutic time window for patients. Increased urine output does not show reversal of injury¹,².
Hemodynamic and Tubular Flow Effects
Enhanced tubular flow represents another theoretical benefit of loop diuretic administration. Greater urine flow may reduce the incidence of tubular obstruction, and higher hydraulic pressures may reduce the back-leak of glomerular filtrate¹. These effects could theoretically address multiple pathophysiologic factors contributing to ATN, including tubular obstruction from cellular debris and the loss of tubular integrity.
Loop diuretics may also improve renal blood flow through vasodilatory effects, potentially enhancing oxygen delivery to vulnerable renal tissue³. The diuretic effect increases tubular flow and hydraulic pressure, potentially dislodging material that causes tubular obstruction and improving venous outflow from the medulla⁴.
Clinical Evidence for Treatment of Established ATN
Systematic Reviews and Meta-Analyses
Comprehensive systematic reviews have consistently demonstrated the lack of clinical benefit from loop diuretics in established ATN. A major meta-analysis of 20 studies involving 2,608 patients found that furosemide had no impact on mortality (OR = 1.015; 95% CI 0.825–1.339) or the need for renal replacement therapy (OR = 0.947; 95% CI 0.521–1.721)⁵. The trials included prevention and treatment settings; interpret those populations separately.
The evidence regarding conversion of oliguric to non-oliguric ATN demonstrates that while diuretic treatment may increase urine output, that does not demonstrate reversal of injury. Reviews of established AKI have not established improved mortality or avoidance of kidney replacement from routine diuretic treatment¹,⁵.
Randomized Controlled Trials
SPARK was a multicenter, blinded pilot trial by Bagshaw and colleagues (2017), terminated after 73 participants. It found no significant difference in worsening AKI, recovery, or RRT, while electrolyte adverse events were more frequent with furosemide. Its small size limits conclusions about patient-centered outcomes⁸.
The Davis and Gooch article is an evidence review, not a trial of more than 2000 patients⁹. Bove and colleagues pooled 28 randomized trials with 3228 participants across prevention and treatment settings and found no overall mortality difference¹⁰. Absence of a demonstrated benefit should not be rephrased as proof that every use of diuretics is harmful.
Safety Considerations
The administration of loop diuretics in ATN carries significant risks that must be balanced against limited benefits. Adverse events include electrolyte abnormalities, particularly hypokalemia and hyponatremia, volume depletion, and potential ototoxicity with high-dose administration⁸. Dose and administration rate require attention to the product instructions and clinical context, particularly at high intravenous exposure¹,²⁰.
A fundamental concern involves the dual effect of loop diuretics on renal perfusion. The same diuretic that might improve renal function in fluid-overloaded patients may have detrimental effects on kidney perfusion if a patient becomes volume-depleted¹⁰. This dual effect explains the controversial results obtained in studies investigating the role of diuretics in ATN treatment.
The Furosemide Stress Test as a Diagnostic Tool
KDIGO 2026 public-review draft, proposed Recommendation 2.3.1: suggests FST for progression-risk assessment in euvolemic or hypervolemic patients with stage 1–2 AKI (adults 2C; children 2B). This is a draft proposal, not a final recommendation or a standalone indication for dialysis.
Development and Standardization
The furosemide stress test (FST) has emerged as a validated functional assessment tool for predicting acute kidney injury progression, complementing traditional AKI biomarkers in risk stratification. The test was developed based on the principle that furosemide response reflects tubular secretory capacity and integrity, as the drug is actively secreted through kidney tubules via the human organic anion transporter system¹¹.
The standardized protocol involves administration of 1.0 mg/kg furosemide for loop diuretic-naive patients and 1.5 mg/kg for patients previously exposed to loop diuretics within seven days, delivered as an intravenous bolus¹². Urine output is then measured hourly for six hours, with particular attention to the first two hours post-administration.
Diagnostic Performance
The diagnostic accuracy of the FST has been rigorously validated through multiple studies. A systematic review of eleven studies enrolling 1,366 patients demonstrated pooled sensitivity and specificity results for AKI progression prediction of 0.81 (95% CI 0.74–0.87) and 0.88 (95% CI 0.82–0.92), respectively¹³.
The most clinically relevant interpretation focuses on the two-hour urine output threshold. Patients producing less than 200 mL of urine in the first two hours following FST administration have significantly increased risk of progression to stage III AKI, with sensitivity of 73.9% and specificity of 90.0%¹⁴. Performance depends on the selected population and protocol. The Rewa study was prospective and observational, with 92 critically ill patients, not a randomized treatment trial.
Clinical Applications
In the pilot FST trial, 118 nonresponders were randomized to early or standard RRT; most patients assigned early RRT received it because of that protocol. The study showed feasibility of selecting a higher-risk trial population and did not demonstrate improved 28-day mortality from an FST-based early strategy³⁰.
FST may support monitoring, counseling, and preparation. A poor response does not itself mandate RRT; urgent clinical indications must not be delayed to perform a test. Xu and colleagues' 55-patient prospective single-center study associated post-CRRT FST response with successful discontinuation, but it does not establish a universal stopping threshold¹⁵.
Implementation Considerations
Use FST only in appropriately selected patients after assessing volume status, perfusion, obstruction, and contraindications. Published protocols concern monitored patients with early AKI who are adequately resuscitated; they should not be applied indiscriminately in hypovolemia.
Monitor urine output, circulation, and electrolytes and use a protocol-specific fluid plan to avoid depletion. Fluid replacement is individualized rather than mandatory additional fluid for every patient. The assessment is prognostic, not a treatment proven to repair tubules¹¹,¹⁴.
Early Intervention and Prevention Protocols
Theoretical Foundation for Early Use
Experimental mechanisms make early intervention a research question, but they do not establish a clinical window in which routine furosemide prevents ATN. Prevention trials often involve selected procedures and combined hydration strategies rather than treatment of unselected established AKI²,³².
Do not infer that a prevention signal proves direct cytoprotection or that a negative treatment trial occurred “too late” to work. These explanations require prospective testing.
Clinical Evidence in High-Risk Procedures
Cardiac Surgery Applications
Small cardiac-surgery trials differ in populations, protocols, and endpoints. Fakhari and colleagues randomized 81 patients: AKI incidence was similar, while the study's more severe renal-dysfunction endpoint favored infusion¹⁶. Bayat and colleagues' 123-patient trial concluded that intermittent furosemide did not provide benefit; changes in urea, sodium, or fluid balance should not be relabeled kidney protection¹⁷.
Mahesh and colleagues' 42-patient randomized trial found increased urine output but no reduction in postoperative renal dysfunction¹⁸. These trials do not support a universal prophylactic regimen.
Balanced Forced Diuresis Protocols
Luckraz and colleagues studied a combined matched-hydration and forced-diuresis strategy in 220 at-risk cardiac-surgery patients. AKI occurred in 10% of the device group versus 20.9% of controls¹⁹. This is evidence for the studied combined protocol, not for furosemide alone or routine treatment of established ATN.
Such strategies require careful selection, monitoring, and fluid matching. A favorable result in one procedure setting cannot be generalized to unstable or volume-depleted patients.
Limitations and Contraindications
Critical Timing Requirements
The practical limitation is uncertain patient selection and protocol-specific evidence, not a proven minutes-to-hours rescue window. Timing relative to an insult, hydration, dose, and procedure all vary across studies. Routine use during aortic surgery cannot be justified solely by theoretical cytoprotection.
Patient Selection Considerations
The natriuretic response to furosemide is significantly reduced in patients with chronic kidney disease, with only approximately 15-20% of the furosemide dose being delivered into tubular fluid in stage 5 CKD patients due to diminished tubular secretion²⁰. This reduced efficacy limits the applicability of prophylactic protocols in patients with pre-existing renal impairment.
The RenalGuard System: Technological Innovation
System Overview and Mechanism
RenalGuard couples diuretic-induced urine output with automated intravenous fluid replacement. MYTHOS used a specific hydration/diuretic protocol in patients with CKD undergoing coronary procedures²². This specialized combined intervention should not be treated as an interchangeable order set for every patient with AKI.
Proposed mechanisms include altered contrast concentration and tubular transit; these remain mechanistic explanations rather than proof of the cause of any clinical benefit. The REMEDIAL II rationale-and-design paper describes a study protocol, not its outcome results²³.
Clinical Applications and Evidence
Contrast-Induced Nephropathy Prevention
Meta-analysis data from three trials including 586 patients demonstrated that high-volume forced diuresis with matched hydration using the RenalGuard system decreased risk of contrast-induced nephropathy by 60%, major adverse clinical events by 59%, and the need for renal replacement therapy by 78% compared with standard care²⁴.
The MYTHOS trial involving 170 consecutive patients with chronic kidney disease undergoing coronary procedures showed significantly reduced risk of contrast-induced nephropathy in the furosemide with matched hydration group compared to standard intravenous isotonic saline hydration²².
Transcatheter Aortic Valve Replacement
The PROTECT-TAVI trial involving 112 consecutive patients undergoing transcatheter aortic valve replacement demonstrated that the acute kidney injury rate was significantly lower in the RenalGuard group than in the control group (5.4% versus 25.0%, respectively)²⁵. No cases of in-hospital renal failure requiring dialysis were reported, with no significant differences in mortality, cerebrovascular events, bleeding, and hospitalization for heart failure at 30 days.
Mixed Results in Recent Studies
However, more recent large-scale trials have shown mixed results. The STRENGTH study, a multicenter international randomized trial including 259 patients with moderate to severe chronic kidney disease, found that the primary endpoint of contrast-induced nephropathy incidence was similar between the RenalGuard group and control group (15.9% versus 13.9%, respectively)²⁶.
Safety Profile and Implementation
Wang and Guo's 2021 meta-analysis reported fewer pulmonary-edema events with matched hydration, but procedural groups and study results varied²⁷. Automated matching does not eliminate hemodynamic or electrolyte risk, and the negative STRENGTH trial limits claims of consistent benefit²⁶.
Use specialized protocols only with appropriate expertise and monitoring. Do not extrapolate selected procedural evidence to all forms of AKI or present the device as invariably safer than conventional care.
Current Guidelines and Recommendations
Professional Society Guidelines
The published KDIGO 2012 guideline advised against diuretics for AKI prevention and against using them to treat AKI except for managing volume overload²⁸. This does not imply that increasing urine output restores kidney function.
The 2026 public-review draft discusses newer evidence and proposes selected functional testing and a volume-removal approach. Distinguish that evolving proposal from the published 2012 recommendations and from independent trial evidence.
Clinical Practice Considerations
In clinical practice, the use of diuretics to convert oliguric AKI to non-oliguric AKI was sometimes recommended to help with fluid management. However, several meta-analyses have shown no reduction in mortality or the need for renal replacement therapy with this approach²⁸. The conversion to non-oliguric status may provide some clinical management advantages but does not improve fundamental outcomes.
Oliguria is associated with adverse outcomes but is not a direct measurement of tubular necrosis or the percentage of injured nephrons²⁹. However, converting oliguria pharmacologically does not address the underlying injury and may create additional risks through volume depletion.
KDIGO 2026 Diuretic Recommendations
The following is a summary of proposals in the March 2026 KDIGO AKI/AKD public-review draft. Recommendations may change before publication. Use the official draft and current clinical guidance for context.
Proposed Recommendations in the Public-Review Draft
Draft Recommendation 3.3.1 (2B): suggests diuretics for clinically significant volume overload in children and adults with or at risk of AKI/AKD.
Draft Recommendation 3.3.2 (1C): favors an initial diuretic approach over extracorporeal removal in overloaded adults when there is no other RRT indication.
Draft Practice Point 3.3.1: identifies intermittent boluses as an appropriate initial adult strategy. These proposals concern volume management; they do not prove renal regeneration or justify delaying urgent RRT.
Supporting Evidence
The 2025 Cochrane review included 53 prevention studies and 11 treatment studies. Prevention analyses suggested fewer AKI events (low certainty) and fewer KRT events and deaths (moderate certainty). Treatment analyses showed little or no difference in KRT or death, with hypotension and arrhythmia concerns³².
Populations, diuretics, co-interventions, and bias varied. Prevention findings do not establish that routine loop diuretics protect the tubules in every setting or that biomarker-positive patients benefit. Outcome-specific certainty is more useful than assigning a single confidence score to an entire article.
Adult Diuretic Escalation Example (KDIGO 2026 Draft, Table 22)
The public-review draft includes an adult escalation example in Table 22. The following illustrates the draft, not a finalized universal prescribing protocol. Individualize dosing and monitoring to the clinical setting:
| Step | Dose / Administration | Monitoring / Goal |
|---|---|---|
| Assessment | Furosemide 1.0 mg/kg IV bolus (1.5 mg/kg if prior diuretic exposure) | Goal: UOP >200 mL within 2 hours |
| Escalation | Double the dose (max bolus 200 mg) every 6-12 hours | Maximize bolus dose before switching to infusion |
| Synergism | Add thiazide (metolazone 5-10 mg PO or chlorothiazide 500 mg IV) 30-60 min before the loop diuretic | Block distal sodium reabsorption |
| Intensify | Switch to continuous infusion, start at 5-10 mg/hr (up to 20 mg/hr) | More effective for maintaining steady-state natriuresis |
| Failure | Re-evaluate for RRT | If net negative balance not achieved despite max therapy, or if K+/pH deranged |
Reassess response and adverse effects at each step. Refractory pulmonary edema or other urgent indications may require RRT without completing every dose-escalation step. Monitor perfusion, net balance, and electrolytes; treatment must not be delayed by rigid adherence to a draft table.
Future Directions and Research Opportunities
Advanced Diagnostic Applications
Combining functional testing with injury biomarkers is a research direction, not an established diuretic-treatment indication. The FST trial assessed feasibility of enrichment for RRT-timing research; it did not establish a biomarker-guided cytoprotective strategy³⁰.
Alternative stress-test protocols and combined prediction models require validation in their intended populations before clinical adoption³¹.
Evidence Gap: Biomarker Timing and the Treatment Paradox
Creatinine may rise after structural injury begins, creating an opportunity to study earlier detection. However, the cited evidence does not support claiming that every treatment trial used the same enrollment criteria, that a biological treatment window had definitively closed, or that biomarker-positive patients have never been studied.
Prevention and treatment populations differ in more than timing. A favorable prevention meta-analysis does not prove that initiating furosemide at a biomarker-positive stage improves outcomes. Biomarker-guided use for a kidney-protection goal remains a hypothesis requiring prospective evaluation, separate from clinically indicated treatment of congestion.
Precision Medicine Approaches
Future protocols may integrate furosemide stress testing for risk stratification with targeted therapeutic interventions, allowing for more personalized medicine approaches in patients most likely to benefit while avoiding unnecessary exposure in lower-risk populations.
Development of better predictive models for renal injury timing may expand the clinical scenarios where prophylactic intervention can be effectively implemented within the critical therapeutic window. Machine learning approaches may enhance the predictive accuracy of functional testing protocols.
Technology Integration
The evolution of automated fluid management systems beyond the current RenalGuard platform may provide more sophisticated approaches to maintaining the delicate balance between adequate tubular flow and hemodynamic stability. Integration with electronic health record systems can facilitate automated calculation of risk scores and provide real-time clinical decision support.
Conclusion
Loop diuretics can relieve congestion in responsive patients. Increased urine output does not demonstrate repair of tubular injury, and routine treatment of established AKI has not shown improved survival or avoidance of KRT.
FST provides prognostic information in selected monitored patients. It can inform planning but does not independently mandate starting or stopping dialysis. Specialized matched-hydration prevention protocols have procedure-specific and mixed evidence.
Keep published guidance, the KDIGO 2026 public-review draft, and research hypotheses distinct. Clinical priorities remain appropriate perfusion, careful volume management, complication treatment, and timely RRT when indicated.
References
Bagshaw SM, Delaney A, Haase M, et al. Loop diuretics in the management of acute renal failure: a systematic review and meta-analysis. Crit Care Resusc. 2007;9(1):60-8. PubMed PMID 17352669
Patschan D, Patschan S, Buschmann I, et al. Loop Diuretics in Acute Kidney Injury Prevention, Therapy, and Risk Stratification. Kidney Blood Press Res. 2019;44(4):457-464. PubMed PMID 31362295
Lameire NH, De Vriese AS, Vanholder R. Prevention and nondialytic treatment of acute renal failure. Curr Opin Crit Care. 2003;9(6):481-90. PubMed PMID 14639067
Schetz M. Should we use diuretics in acute renal failure? Best Pract Res Clin Anaesthesiol. 2004;18(1):75-89. PubMed PMID 14760875
Krzych ŁJ, Czempik PF. Impact of furosemide on mortality and the requirement for renal replacement therapy in acute kidney injury: a systematic review and meta-analysis of randomised trials. Ann Intensive Care. 2019;9(1):85. PubMed PMID 31342205
Bagshaw SM, Gibney RTN, Kruger P, et al. The effect of low-dose furosemide in critically ill patients with early acute kidney injury: A pilot randomized blinded controlled trial (the SPARK study). J Crit Care. 2017;42:138-146. PubMed PMID 28732314
Davis A, Gooch I. Best evidence topic report. The use of loop diuretics in acute renal failure in critically ill patients to reduce mortality, maintain renal function, or avoid the requirements for renal support. Emerg Med J. 2006;23(7):569-70. PubMed PMID 16794108
Bove T, Belletti A, Putzu A, et al. Intermittent furosemide administration in patients with or at risk for acute kidney injury: Meta-analysis of randomized trials. PLoS One. 2018;13(4):e0196088. PubMed PMID 29689116
Chawla LS, Davison DL, Brasha-Mitchell E, et al. Development and standardization of a furosemide stress test to predict the severity of acute kidney injury. Crit Care. 2013;17(5):R207. PubMed PMID 24053972
Rajasekaran KK, Venkataraman R. Furosemide Stress Test in Predicting Acute Kidney Injury Outcomes. Indian J Crit Care Med. 2020;24(Suppl 3):S100-S101. PubMed PMID 32704213.
Chen JJ, Chang CH, Huang YT, et al. Furosemide stress test as a predictive marker of acute kidney injury progression or renal replacement therapy: a systemic review and meta-analysis. Crit Care. 2020;24(1):202. PubMed PMID 32381019
Rewa OG, Bagshaw SM, Wang X, et al. The furosemide stress test for prediction of worsening acute kidney injury in critically ill patients: A multicenter, prospective, observational study. J Crit Care. 2019;52:109-114. PubMed PMID 31035185
Xu L, Chen L, Jiang X, et al. The furosemide stress test predicts successful discontinuation of continuous renal replacement therapy in critically ill patients with acute kidney injury. J Crit Care. 2025;85:154929. PubMed PMID 39383593
Fakhari S, Bavil FM, Bilehjani E, et al. Prophylactic furosemide infusion decreasing early major postoperative renal dysfunction in on-pump adult cardiac surgery: a randomized clinical trial. Res Rep Urol. 2017;9:5-13. PubMed PMID 28176949
Bayat F, Faritous Z, Aghdaei N, et al. A study of the efficacy of furosemide as a prophylaxis of acute renal failure in coronary artery bypass grafting patients: A clinical trial. ARYA Atheroscler. 2015;11(3):173-8. PubMed PMID 26405449
Mahesh B, Yim B, Robson D, et al. Does furosemide prevent renal dysfunction in high-risk cardiac surgical patients? Results of a double-blinded prospective randomised trial. Eur J Cardiothorac Surg. 2008;33(3):370-6. PubMed PMID 18243724
Luckraz H, Giri R, Wrigley B, et al. Reduction in acute kidney injury post cardiac surgery using balanced forced diuresis: a randomized, controlled trial. Eur J Cardiothorac Surg. 2021;59(3):562-569. PubMed PMID 33236105
Oh SW, Han SY. Loop Diuretics in Clinical Practice. Electrolyte Blood Press. 2015;13(1):17-21. PubMed PMID 26240596
Shah R, Wood SJ, Khan SA, et al. High-volume forced diuresis with matched hydration using the RenalGuard System to prevent contrast-induced nephropathy: A meta-analysis of randomized trials. Clin Cardiol. 2017;40(12):1242-1246. PubMed PMID 29247527
Marenzi G, Ferrari C, Marana I, et al. Prevention of contrast nephropathy by furosemide with matched hydration: the MYTHOS (Induced Diuresis With Matched Hydration Compared to Standard Hydration for Contrast Induced Nephropathy Prevention) trial. JACC Cardiovasc Interv. 2012;5(1):90-7. PubMed PMID 22230154
Briguori C, Visconti G, Ricciardelli B, et al. Renal insufficiency following contrast media administration trial II (REMEDIAL II): RenalGuard system in high-risk patients for contrast-induced acute kidney injury: rationale and design. EuroIntervention. 2011;6(9):1117-22, 7. PubMed PMID 21518686
Shah R, Wood SJ, Khan SA, et al. High-volume forced diuresis with matched hydration using the RenalGuard System to prevent contrast-induced nephropathy: A meta-analysis of randomized trials. Clin Cardiol. 2017;40(12):1242-1246. PubMed PMID 29247527
Barbanti M, Gulino S, Capranzano P, et al. Acute Kidney Injury With the RenalGuard System in Patients Undergoing Transcatheter Aortic Valve Replacement: The PROTECT-TAVI Trial (PROphylactic effecT of furosEmide-induCed diuresis with matched isotonic intravenous hydraTion in Transcatheter Aortic Valve Implantation). JACC Cardiovasc Interv. 2015;8(12):1595-604. PubMed PMID 26386766
Mauler-Wittwer S, Sievert H, Ioppolo AM, et al. Study Evaluating the Use of RenalGuard to Protect Patients at High Risk of AKI. JACC Cardiovasc Interv. 2022;15(16):1639-1648. PubMed PMID 35981838
Wang Y, Guo Y. RenalGuard system and conventional hydration for preventing contrast-associated acute kidney injury in patients undergoing cardiac interventional procedures: A systematic review and meta-analysis. Int J Cardiol. 2021;333:83-89. PubMed PMID 33662483
Khwaja A. KDIGO clinical practice guidelines for acute kidney injury. Nephron Clin Pract. 2012;120(4):c179-84. PubMed PMID 22890468
This PubMed article is an overview of KDIGO 2012. Official guideline and current draft status.
Hanif MO, Rout P, Ramphul K. Acute Renal Tubular Necrosis. StatPearls [Internet]. Updated August 8, 2025. PubMed PMID 29939592.
Lumlertgul N, Peerapornratana S, Trakarnvanich T, et al. Early versus standard initiation of renal replacement therapy in furosemide stress test non-responsive acute kidney injury patients (the FST trial). Crit Care. 2018;22(1):101. PubMed PMID 29673370
McMahon BA, Chawla LS. The furosemide stress test: current use and future potential. Ren Fail. 2021;43(1):830-839. PubMed PMID 33971784
Hashimoto H, Yamada H, Murata M, et al. Diuretics for preventing and treating acute kidney injury. Cochrane Database Syst Rev. 2025;1(1):CD014937. PubMed PMID 39878152
Confidence Matrix of References
Study Design and Applicability
| Reference | Verified author/year | Study design | Interpretation limit |
|---|---|---|---|
| 1 | Bagshaw, 2007 | Systematic review; 5 RCTs, 555 participants | Authors described overall trial quality as low; limited ICU applicability. |
| 2–4 | Patschan 2019; Lameire 2003; Schetz 2004 | Narrative/review articles | Mechanisms and context; not randomized outcome evidence. |
| 5 | Krzych and Czempik, 2019 | Meta-analysis; 20 studies, 2608 participants | Mixed prevention/treatment populations. |
| 8 | Bagshaw, 2017 (SPARK) | Pilot randomized blinded trial; 73 participants | Small trial; protocol deviations and electrolyte adverse events. |
| 9 | Davis and Gooch, 2006 | Best-evidence review | Not a trial of 2000 patients. |
| 10 | Bove, 2018 | Meta-analysis; 28 RCTs, 3228 participants | Overall and prevention-subgroup estimates answer different questions. |
| 11 | Chawla, 2013 | Two cohorts; 77 participants | FST development, not a randomized efficacy trial. |
| 12 | Rajasekaran and Venkataraman, 2020 | Clinical review | Summarizes other investigations. |
| 13 | Chen and colleagues, 2020 | Prediction systematic review; 11 studies, 1366 participants | Predictive accuracy is not proof of treatment benefit. |
| 14 | Rewa, 2019 | Multicenter prospective observational study; 92 participants | Stage 1–2 AKI; excluded severe CKD. |
| 15 | Xu, 2025 | Prospective single-center study; 55 participants | CRRT-discontinuation prediction requires broader validation. |
| 16 | Fakhari, 2017 | Randomized trial; 81 participants | Selected cardiac-surgery population and study-specific endpoints. |
| 17 | Bayat, 2015 | Randomized trial; 123 participants | No demonstrated intermittent-furosemide benefit. |
| 18 | Mahesh, 2008 | Randomized blinded trial; 42 participants | Urine output improved without reduced renal dysfunction. |
| 19 | Luckraz, 2021 | Randomized trial; 220 participants | Combined matched-hydration protocol; not furosemide alone. |
| 20 | Oh and Han, 2015 | Clinical review | Pharmacology and practical context. |
| 21,24 | Shah, 2017 | Same meta-analysis; 3 RCTs, 586 participants | Duplicate citations do not represent independent evidence. |
| 22 | Marenzi, 2012 (MYTHOS) | Randomized trial; 170 participants | CKD patients undergoing coronary procedures. |
| 23 | Briguori, 2011 | REMEDIAL II rationale/design paper | A protocol cannot establish treatment effectiveness. |
| 25 | Barbanti, 2015 (PROTECT-TAVI) | Single-center open-label randomized study; 112 participants | Mostly mild AKI events; limited power for hard outcomes. |
| 26 | Mauler-Wittwer, 2022 (STRENGTH) | Multicenter randomized study; 259 enrolled | No significant primary-endpoint benefit. |
| 27 | Wang and Guo, 2021 | Systematic review and meta-analysis | Procedural subgroups and heterogeneity affect interpretation. |
| 28 | Khwaja, 2012 | Guideline overview | Distinguish from the full guideline and 2026 draft. |
| 29 | Hanif, Rout and Ramphul, updated 2025 | StatPearls clinical chapter | Background teaching, not a primary trial. |
| 30 | Lumlertgul, 2018 | Pilot trial; 118 FST nonresponders randomized | Feasibility/enrichment; no demonstrated mortality advantage. |
| 31 | McMahon and Chawla, 2021 | Clinical review | Current uses and research proposals. |
| 32 | Hashimoto, 2025 | Cochrane review; 64 studies, 9871 participants | Certainty varies by outcome and prevention versus treatment. |
Assessing Evidence Quality
Do not assign an invented 1–10 quality score based only on study design. Assess bias, precision, consistency, and applicability for the specific outcome. A randomized trial may still be small or biased; a prediction study does not answer a treatment-effect question.
Interpreting Confidence
Use published outcome-specific certainty assessments when available and explain their limits. Keep randomized treatment effects, observational associations, prediction accuracy, narrative interpretation, and draft guidance separate.
Overall Assessment
The evidence supports careful volume management and selected prognostic testing while leaving uncertainty about routine prevention strategies. It does not justify a single “high confidence” percentage for the bibliography or automatic dialysis decisions based on FST.
Educational Resources
- Student Guide: Daptomycin Aki Review — PA/medical student educational guide
- Student Guide: Well Water Contamination, Diarrhea And Aki — PA/medical student educational guide
- Student Guide: Appendix E Pain Management Deep Dive — PA/medical student educational guide
- Student Handout: Diuretics — PA/medical student educational guide
Also on this topic
The same subject at other levels of depth.
- Primer chapter: Chapter 9: ATN & Loop Diuretics