Hemodynamic AKI: Cardiorenal and Hepatorenal Syndromes
Visual reference
Browse the visual reference library · Download lesson Markdown
1. Similar Urine Indices, Different Treatments
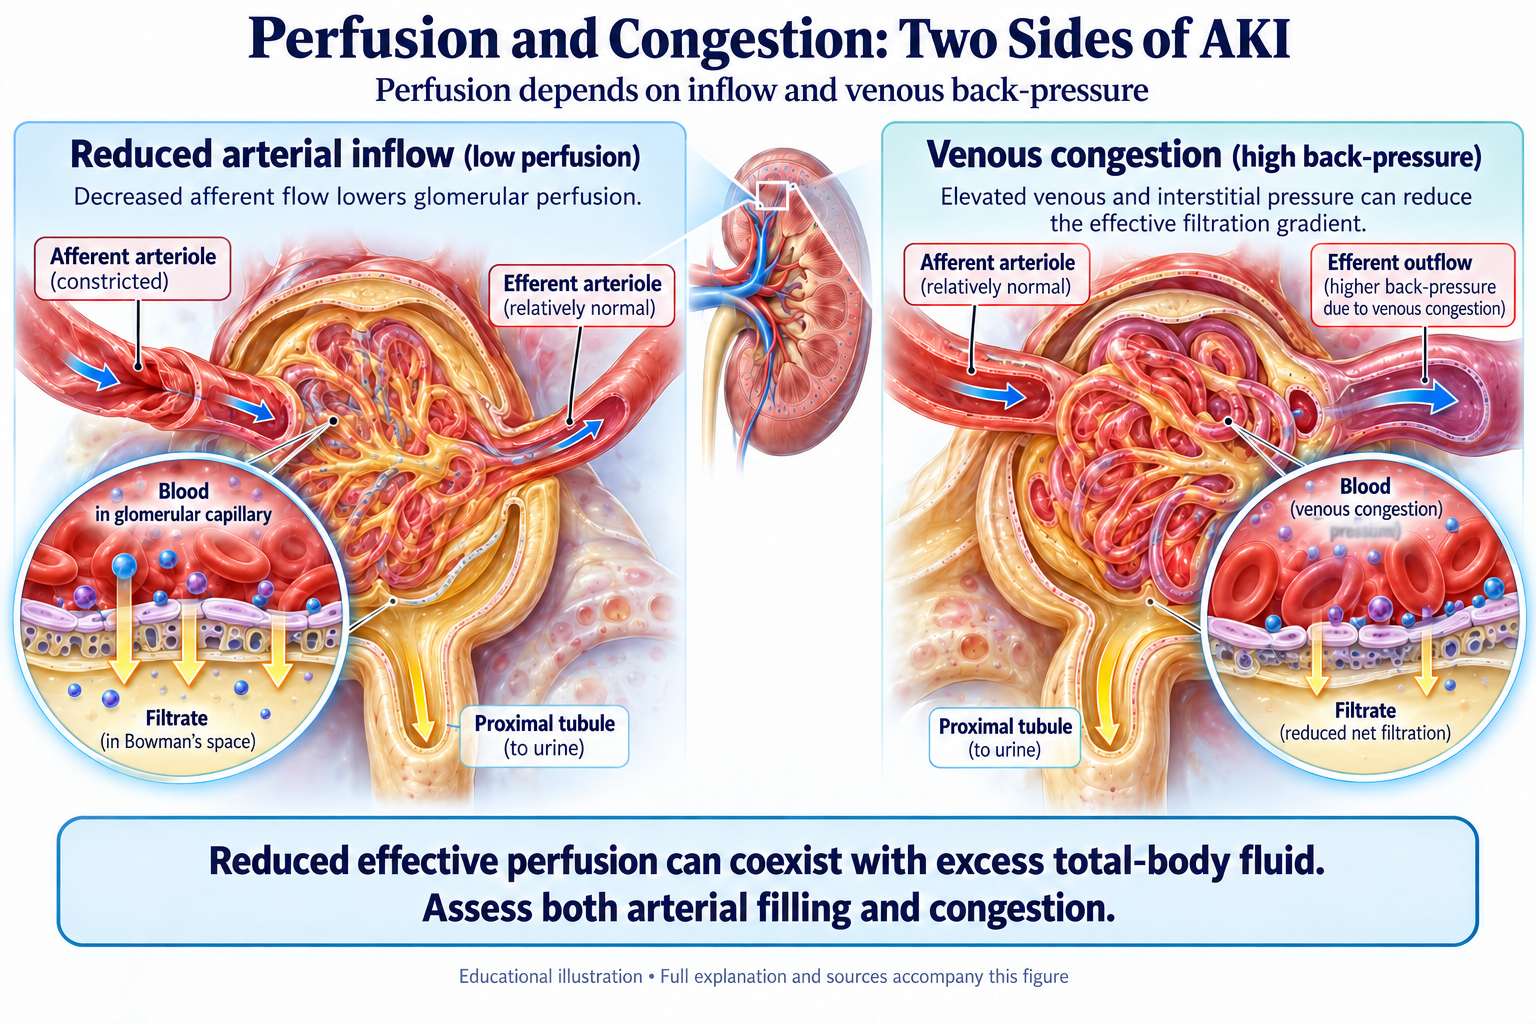
A fall in kidney perfusion can accompany true volume depletion, reduced forward flow, venous congestion, or cirrhosis-related circulatory dysfunction. More than one mechanism can coexist, and structural tubular injury may develop. A low urine sodium or fractional excretion of sodium does not identify which mechanism is present and does not automatically justify fluid administration.
Assess the history, perfusion, blood pressure, weight trend, urine output, congestion, medications, and creatinine trajectory. Urinalysis and sediment, protein quantification, and renal imaging help identify competing causes. Point-of-care ultrasound may add information but must be interpreted with the examination and the overall clinical picture.
Volume-depleted patients may benefit from appropriate resuscitation with reassessment. Congested patients may require decongestion despite an elevated creatinine. Shock requires urgent evaluation of its cause and restoration of adequate perfusion. Do not select among these treatments using one urine index or a fixed BUN-to-creatinine ratio. Rangaswami et al.
2. Cardiorenal Syndrome
Cardiac and kidney dysfunction can worsen each other through hemodynamic, neurohormonal, inflammatory, and treatment-related pathways. Venous congestion can impair kidney function even when cardiac output is not profoundly reduced. Conversely, true low output and hypotension can threaten perfusion. Clinical congestion and effective arterial perfusion therefore need separate assessment.
A creatinine rise during effective decongestion may reflect a functional change and does not invariably mean tubular injury. It also does not prove that further fluid removal is safe. Interpret the change alongside symptoms, blood pressure, perfusion, urine output, residual congestion, electrolytes, and the rate of change. Persistent congestion with adequate perfusion differs from progressive oliguria, hypotension, or new ischemic or toxic injury. Reassess the entire plan when these warning signs occur.
3. Decongestive Strategies
Loop diuretics are central to relief of acute congestion. Choose and adjust the dose using prior exposure, kidney function, delivery route, and observed response. Monitor urine output, weight, symptoms, blood pressure, electrolytes, and kidney function. Resistant congestion warrants a search for ongoing sodium intake, impaired absorption, drug interactions, and an inadequate initial prescription before adding more drugs.
Furosemide Stress Test: Prognostic Information
The standardized FST was studied in selected critically ill patients with early AKI using a one-time IV dose of 1.0 or 1.5 mg/kg according to prior loop exposure. In the original 77-patient study, two-hour urine output predicted progression to stage 3 AKI (AUC 0.87); a response below 200 mL identified higher risk. These estimates are cohort-dependent and do not establish a universal individual probability. Chawla et al.
The 2015 biomarker analysis used the same 77-patient cohort, rather than an independent 200-patient validation cohort. It compared the FST response with several biochemical biomarkers. The test should be considered only with attention to appropriate volume status, obstruction, monitoring, and local expertise. Koyner et al.
An FST response is neither a guarantee that continued diuresis is safe nor an indication by itself to start dialysis or ultrafiltration. It is not a treatment that has been shown to prevent AKI progression. Decisions about kidney replacement therapy depend on the evolving clinical indications.
Bolus or Infusion
DOSE randomized 308 patients with acute decompensated heart failure to bolus versus continuous administration and lower versus higher dosing. Symptoms and creatinine change were coprimary endpoints. Neither comparison significantly improved these coprimary endpoints. Higher dosing produced more diuresis and favorable changes in some secondary measures, with more transient worsening of kidney function. The trial does not establish that a continuous infusion protects the kidney or improves survival. Felker et al.
Combination Treatment
A thiazide-type diuretic or another selected agent may augment loop response when congestion persists. Sequential blockade can also produce substantial sodium, potassium, magnesium, acid–base, and volume disturbances. Use a defined reassessment plan; escalating treatment without checking response and perfusion can convert congestion management into depletion. SGLT2 inhibitors and other heart-failure therapies should be considered for their indication and eligibility, with attention to acute-illness precautions.
Ultrafiltration
Ultrafiltration can remove fluid but has not shown consistent superiority to an optimized pharmacologic strategy. In CARRESS-HF, patients with decompensated heart failure, worsening kidney function, and persistent congestion had a less favorable creatinine/weight endpoint and more adverse events with ultrafiltration. AVOID-HF stopped early and did not establish a statistically significant primary benefit. Consider the patient’s indication, hemodynamic tolerance, access, and response to medical treatment. Bart et al.; Costanzo et al.
Therapy After Stabilization
EMPULSE studied empagliflozin after clinical stabilization during hospitalization for acute heart failure. It favored empagliflozin on a hierarchical composite of death, heart-failure events, and symptoms at 90 days. That result should not be described as a proven isolated mortality benefit or generalized to patients in shock. Voors et al.
4. AKI in Cirrhosis and HRS-AKI
Cirrhosis does not make all AKI hepatorenal syndrome. Consider hypovolemia, infection and shock, nephrotoxic injury, obstruction, glomerular disease, and coexisting CKD. HRS-AKI is a phenotype associated with cirrhosis and ascites; circulatory dysfunction and inflammation contribute, and structural injury may coexist.
The 2024 ADQI–ICA consensus uses AKI criteria based on creatinine and/or urine output, lack of improvement within 24 hours after adequate resuscitation when clinically indicated, and no strong alternative primary explanation. It recommends against making a routine 48-hour albumin infusion mandatory for diagnosis. Volume assessment guides resuscitation, especially when overload is already present. Nadim et al.
Once HRS-AKI is established, the consensus recommends vasoconstrictor treatment with albumin, individualized to clinical status. Monitor oxygenation and volume, and adjust or stop albumin with overload. Norepinephrine is an alternative in an appropriately monitored setting when terlipressin cannot be used. Evidence for TIPS as treatment of HRS-AKI is limited; it is not a routine rescue recommendation. Liver-transplant assessment is central. Nadim et al.
Terlipressin: Benefit and Risk
CONFIRM found more verified HRS reversal with terlipressin than placebo in the trial population, both receiving albumin. Respiratory adverse events were an important concern. Follow the applicable product labeling and local protocol for eligibility, oxygenation assessment, dosing, response checks, and stopping rules. Do not infer a guaranteed survival benefit from an improvement in creatinine. Wong et al.
Kidney Replacement Therapy and Prognosis
Dialysis may treat otherwise unmanageable electrolyte, acid–base, volume, or uremic complications and may serve as a bridge to recovery or transplantation. Outcomes in advanced cirrhosis are often poor, but a single mortality percentage cannot guide every patient. Cohort data must be interpreted with transplant listing, illness severity, the reason for dialysis, and selection bias. Discuss expected benefits, burdens, patient goals, and whether a time-limited trial is appropriate. Allegretti et al.
5. A Reassessment-Based Approach
- Identify urgent threats: shock, pulmonary edema, severe electrolyte or acid–base disturbance, and uremic complications.
- Assess depletion, congestion, and perfusion separately using more than one finding.
- Search for competing causes of AKI and remove avoidable contributors.
- Select cause-directed treatment, then reassess the clinical and biochemical response.
- Escalate promptly when deterioration or refractory complications require intensive care, kidney replacement therapy, or specialist intervention.
Use the trajectory to revise the working diagnosis. Improvement in one laboratory value should not obscure worsening respiratory status, hypotension, or ongoing congestion.
6. Key Points
Low urine sodium can occur in both depletion and congestion. FST provides risk information, not a dialysis rule. A creatinine rise during decongestion requires context. HRS-AKI assessment must consider other causes and avoid indiscriminate albumin loading. Treatment and prognosis should be revisited as the patient’s condition changes.
References and Key Trials
- Rangaswami J, Bhalla V, Blair JEA, et al. Cardiorenal Syndrome: Classification, Pathophysiology, Diagnosis, and Treatment Strategies: A Scientific Statement From the American Heart Association. Circulation 2019. PubMed 30852913.
- Felker GM, Lee KL, Bull DA, et al. Diuretic strategies in patients with acute decompensated heart failure. N Engl J Med 2011. PubMed 21366472.
- Chawla LS, Davison DL, Brasha-Mitchell E, et al. Development and standardization of a furosemide stress test to predict the severity of acute kidney injury. Crit Care 2013. PubMed 24053972.
- Koyner JL, Davison DL, Brasha-Mitchell E, et al. Furosemide Stress Test and Biomarkers for the Prediction of AKI Severity. J Am Soc Nephrol 2015. PubMed 25655065.
- Bart BA, Goldsmith SR, Lee KL, et al. Ultrafiltration in decompensated heart failure with cardiorenal syndrome. N Engl J Med 2012. PubMed 23131078.
- Costanzo MR, Negoianu D, Jaski BE, et al. Aquapheresis Versus Intravenous Diuretics and Hospitalizations for Heart Failure. JACC Heart Fail 2016. PubMed 26519995.
- Voors AA, Angermann CE, Teerlink JR, et al. The SGLT2 inhibitor empagliflozin in patients hospitalized for acute heart failure: a multinational randomized trial. Nat Med 2022. PubMed 35228754.
- Nadim MK, Kellum JA, Forni L, et al. Acute kidney injury in patients with cirrhosis: Acute Disease Quality Initiative (ADQI) and International Club of Ascites (ICA) joint multidisciplinary consensus meeting. J Hepatol 2024. PubMed 38527522.
- Wong F, Pappas SC, Curry MP, et al. Terlipressin plus Albumin for the Treatment of Type 1 Hepatorenal Syndrome. N Engl J Med 2021. PubMed 33657294.
- Allegretti AS, Parada XV, Eneanya ND, et al. Prognosis of Patients with Cirrhosis and AKI Who Initiate RRT. Clin J Am Soc Nephrol 2018. PubMed 29122911.