Visual reference
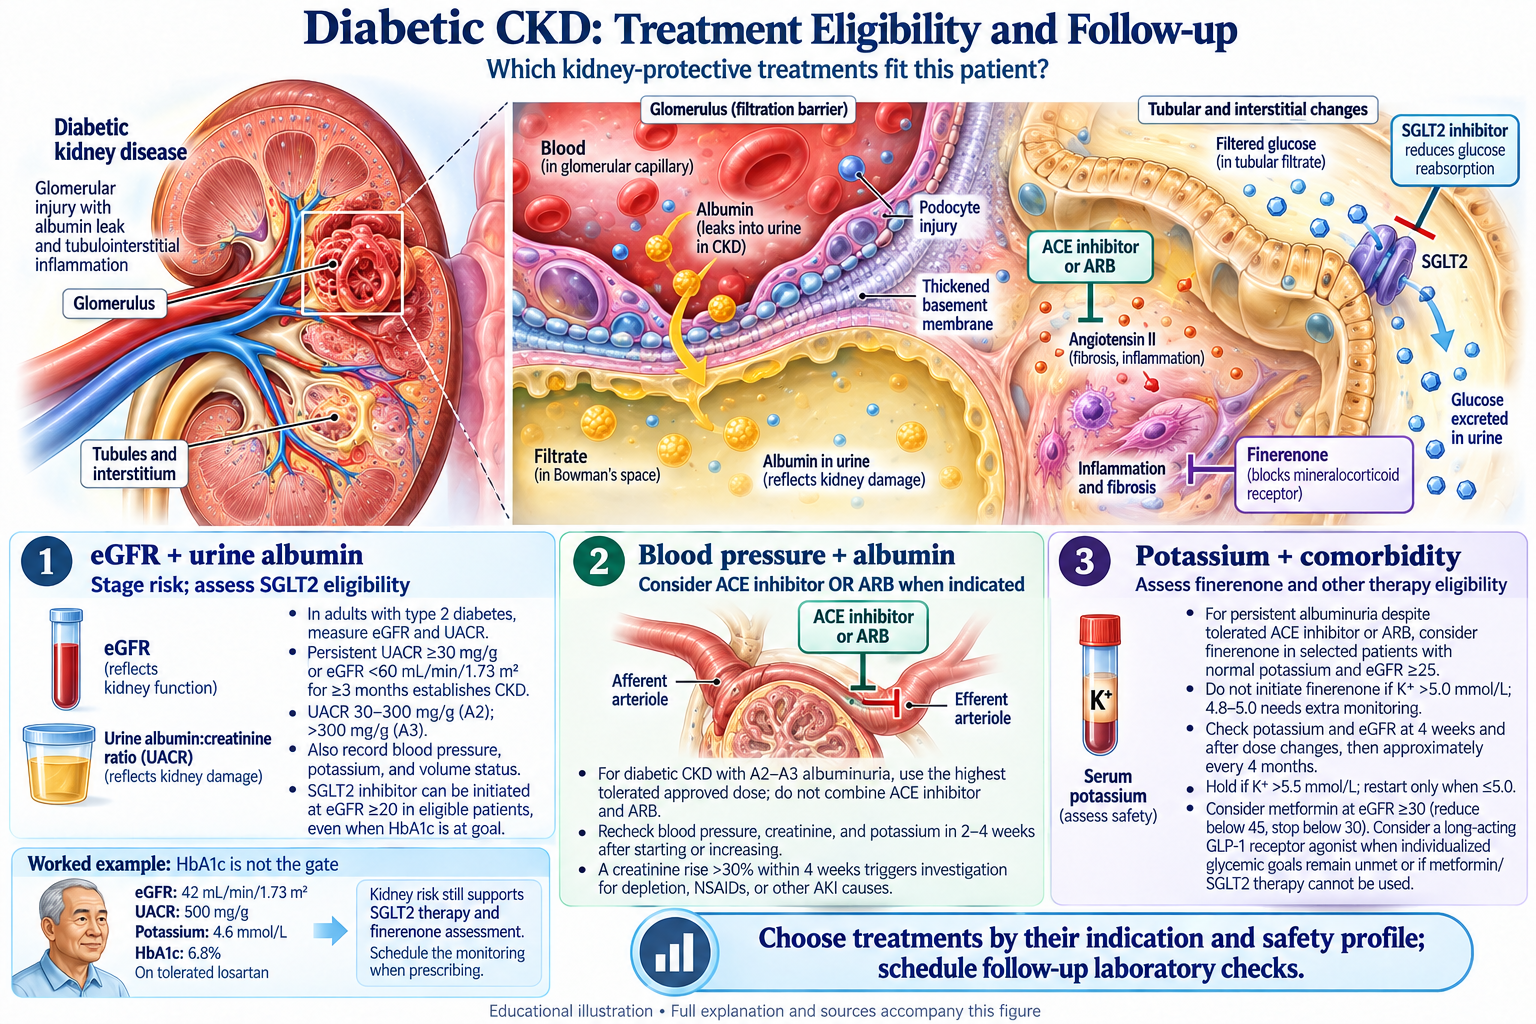
Browse the visual reference library · Download lesson Markdown
Executive Summary
Diabetic kidney disease (DKD) affects approximately 40% of individuals with diabetes and represents the leading cause of CKD globally. Modern management has evolved from single-agent RAAS blockade to a multi-targeted strategy incorporating four pillars of therapy.
SGLT2 inhibitors reduce kidney disease progression by 37% across multiple landmark trials regardless of diabetes status or baseline kidney function. Finerenone provides an additional 23% reduction in kidney failure risk. Semaglutide demonstrated a 24% reduction in major kidney disease events in FLOW. All four drug classes are cost-effective and reduce albuminuria by 25–40% individually; combined therapy can achieve >50% albuminuria reduction.
Comparative Effectiveness Overview
| Outcome | ACE-I/ARB | SGLT2-I | Finerenone | GLP-1 RA |
|---|---|---|---|---|
| Kidney failure reduction | 20–40% | 30–40% | 20–25% | 20–30% |
| CV death reduction | 0–10% | 15–20% | 10–15% | 20–30% |
| All-cause mortality | 0–10%* | 15–20% | 8–10% | 15–20% |
| UACR reduction | 25–35% | 30–40% | 30–35% | 30–40% |
| HbA1c reduction | None | 0.4–0.6% | None | 1.0–1.5% |
| Weight change | None | -2–3 kg | None | -5–6 kg |
| Monthly cost (USD) | $5–20 | $400–500 | $400–500 | $800–1000 |
*Mortality benefit seen only with maximally dosed ACE inhibitors
Pillar 1: RAAS Inhibitors
ACE Inhibitors vs ARBs
A comprehensive Cochrane review of 109 studies (28,341 adults) found ACE inhibitors demonstrated a 39% reduction in kidney failure (RR 0.61; NNT 67). ARBs showed a more modest 18% reduction (RR 0.82). When used at full doses, ACE inhibitors reduced all-cause mortality by 22% (RR 0.78)—a benefit not observed with ARBs.
| Parameter | ACE Inhibitors | ARBs |
|---|---|---|
| Kidney failure prevention | 39% reduction (RR 0.61) | 18% reduction (RR 0.82) |
| Doubling of SCr | 42% reduction | 21% reduction |
| Regression micro → normoalbuminuria | 3-fold increase | 1.4-fold increase |
| Cough incidence | 10–15% | <1% |
Clinical Pearl: Implementation Gap
Among 15,400 patients with incident CKD in T2DM not on RAAS blockade, only 17% initiated therapy within one year of CKD diagnosis. This represents a critical missed opportunity for kidney protection. Maximally tolerated doses are required for optimal benefit.
Pillar 2: SGLT2 Inhibitors
Major Trials
| Trial | Population | RRR | ARR | NNT |
|---|---|---|---|---|
| CREDENCE | T2DM + CKD, eGFR 30–90, UACR >300 | 30% (HR 0.70) | 4.4% | 23 |
| DAPA-CKD | CKD ± T2DM, eGFR 25–75 | 39% (HR 0.61) | 5.3% | 19 |
| EMPA-KIDNEY | CKD ± T2DM, eGFR 20–90 | 28% (HR 0.72) | 3.8% | 26 |
Mechanisms of Kidney Protection
- Reduction in intraglomerular pressure via tubuloglomerular feedback
- Decreased tubular workload and oxygen consumption
- Metabolic reprogramming favoring ketone utilization
- Anti-inflammatory and anti-fibrotic effects
- Reduction in albuminuria by 30–40%
Benefits emerge rapidly, with separation of event curves within 3–6 months of treatment initiation.
Pillar 3: Finerenone (Non-Steroidal MRA)
FIDELITY Pooled Analysis (n=13,026)
| Parameter | FIDELIO-DKD | FIGARO-DKD | FIDELITY (Pooled) |
|---|---|---|---|
| Kidney outcome reduction | 18% (HR 0.82) | 13% (HR 0.87) | 23% (HR 0.77) |
| CV outcome reduction | 14% (HR 0.86) | 13% (HR 0.87) | 14% (HR 0.86) |
| UACR reduction | 31% | 32% | 32% |
| Hyperkalemia ≥5.5 | 15.8% vs 7.8% | 10.8% vs 5.3% | 14% vs 6.9% |
Finerenone benefits were preserved in patients already receiving SGLT2 inhibitors (no interaction, p=0.63), supporting use of both agents as complementary therapies.
Pillar 4: GLP-1 Receptor Agonists (FLOW Trial)
The FLOW trial (n=3,533) randomized patients with T2DM and CKD (eGFR 25–75, UACR >300) to semaglutide 1.0 mg weekly vs placebo. The trial was stopped early after demonstrating a 24% reduction in the primary composite outcome.
| Outcome | HR (95% CI) | ARR | NNT |
|---|---|---|---|
| Primary composite (kidney failure, ≥50% eGFR decline, kidney/CV death) | 0.76 (0.66–0.88) | 4.5% | 22 |
| CV death | 0.71 (0.56–0.89) | 1.8% | 56 |
| All-cause mortality | 0.80 (0.67–0.95) | 2.0% | 50 |
| eGFR slope benefit | — | 1.16 mL/min/1.73m²/yr | — |
Benefits were preserved with concomitant SGLT2i use (no interaction, p=0.755). Rapid onset of benefit within 3–6 months.
Optimization: Sequencing and Combination Therapy
Step-by-Step Implementation Protocol
| Step | Action | Timing | Monitoring |
|---|---|---|---|
| 1. Diagnosis | Confirm DKD (2 eGFR/UACR); assess CV risk | Baseline | eGFR, UACR, K+, Cr, HbA1c, BP |
| 2. RAAS blockade | Start ACE-I (or ARB if cough); titrate to max tolerated | Weeks 0–4 | K+, Cr at 2 weeks; BP |
| 3. SGLT2 inhibitor | Add SGLT2-I if eGFR ≥20; educate on hygiene/sick days | Weeks 4–8 | Volume status; eGFR dip |
| 4. MRA consideration | If UACR >30 despite above, add finerenone 10–20 mg | Weeks 12–16 | K+ at 4 weeks; then q3–4 months |
| 5. GLP-1 RA | If HbA1c >7% or high CV risk; start semaglutide 0.25 mg weekly | Weeks 16–24 | GI tolerance; weight; glycemia |
| 6. Maintenance | Confirm all at target doses; reinforce adherence | Ongoing | Q3–6 month labs; annual UACR |
Clinical Pearl: Initial eGFR Dip
An early hemodynamic eGFR decrease can occur after selected kidney-protective drugs. A modest stable dip does not automatically require stopping treatment, but substantial or progressive decline, symptomatic hypotension, or hyperkalemia needs reassessment of volume, perfusion, interactions, and alternative injury. Follow the individual drug and guideline monitoring framework.
Safety Monitoring
| Drug Class | Key Concerns | Monitoring | Management |
|---|---|---|---|
| ACE-I/ARB | Hyperkalemia; AKI; angioedema (ACE-I) | K+, Cr at 2–4 wks, then q3–6 months | Accept ≤30% Cr rise; K+ <5.5: continue |
| SGLT2-I | Genital infections; volume depletion; euglycemic DKA (rare) | Initial education; symptom monitoring | Hygiene education; sick day rules; hold perioperatively |
| Finerenone | Hyperkalemia; hypotension | K+ at 1 month; then q3–4 months | Start 10 mg if eGFR <60; hold if K+ >5.5 |
| GLP-1 RA | GI symptoms; injection site reactions; pancreatitis (rare) | Symptom assessment; weight; HbA1c q3–6 months | Slow titration; dietary counseling |
Implementation Gaps
| Therapy | Eligible | Currently Receiving | Gap |
|---|---|---|---|
| ACE-I/ARB | ~90% | 40–70% | 20–50% |
| SGLT2 inhibitors | ~80% | 10–30% | 50–70% |
| Finerenone | ~60% | <5% | >90% |
| GLP-1 RA | ~70% | 5–15% | 55–65% |
References
- Natale P, Palmer SC, Navaneethan SD, et al. ACE inhibitors and ARBs for preventing DKD progression. Cochrane Database Syst Rev. 2024;4:CD006257. PubMed
- Tuttle KR, Wong L, St Peter W, et al. Moving from Evidence to Implementation of Breakthrough Therapies for Diabetic Kidney Disease. Clin J Am Soc Nephrol 2022. PubMed 35649722.
- SGLT2 Inhibitor Meta-Analysis Consortium. Impact of diabetes on SGLT2i kidney outcomes. Lancet. 2022;400(10365):1788-1801. PubMed
- Heerspink HJL, Stefánsson BV, Correa-Rotter R, et al. Dapagliflozin in patients with CKD. N Engl J Med. 2020;383(15):1436-1446. PubMed
- Agarwal R, Filippatos G, Pitt B, et al. CV and kidney outcomes with finerenone: the FIDELITY pooled analysis. Eur Heart J. 2022;43(6):474-484. PubMed
- Perkovic V, Tuttle KR, Rossing P, et al. Effects of semaglutide on CKD in patients with T2D. N Engl J Med. 2024;391(2):109-121. PubMed
- Perkovic V, Jardine MJ, Neal B, et al. Canagliflozin and renal outcomes in T2D and nephropathy. N Engl J Med. 2019;380(24):2295-2306. PubMed
- EMPA-KIDNEY Collaborative Group. Empagliflozin in patients with CKD. N Engl J Med. 2023;388(2):117-127. PubMed
- Bakris GL, Agarwal R, Anker SD, et al. Effect of finerenone on CKD outcomes in T2D. N Engl J Med. 2020;383(23):2219-2229. PubMed
- Kidney Disease: Improving Global Outcomes (KDIGO) Diabetes Work Group. KDIGO 2022 Clinical Practice Guideline for Diabetes Management in Chronic Kidney Disease. Kidney Int. 2022;102(5S):S1-S127. DOI | PubMed
Also on this topic
The same subject at other levels of depth.
- Student handout: Diabetic Kidney Disease: Comprehensive Management Overview