Phosphate Management in ESRD — A Review of Quality Metrics, Outcomes, Binders, and Tenapanor
A clinical review for the practicing nephrologist, dialysis medical director, and trainee. Built around an honest reading of the evidence: the observational case for phosphate control is strong, the interventional case is thin, and the question of whether aggressive phosphate lowering improves hard outcomes remains formally unresolved. This review pulls apart what we know, what we measure, and what works — across the full binder landscape and the new non-binder agent tenapanor.
Visual reference
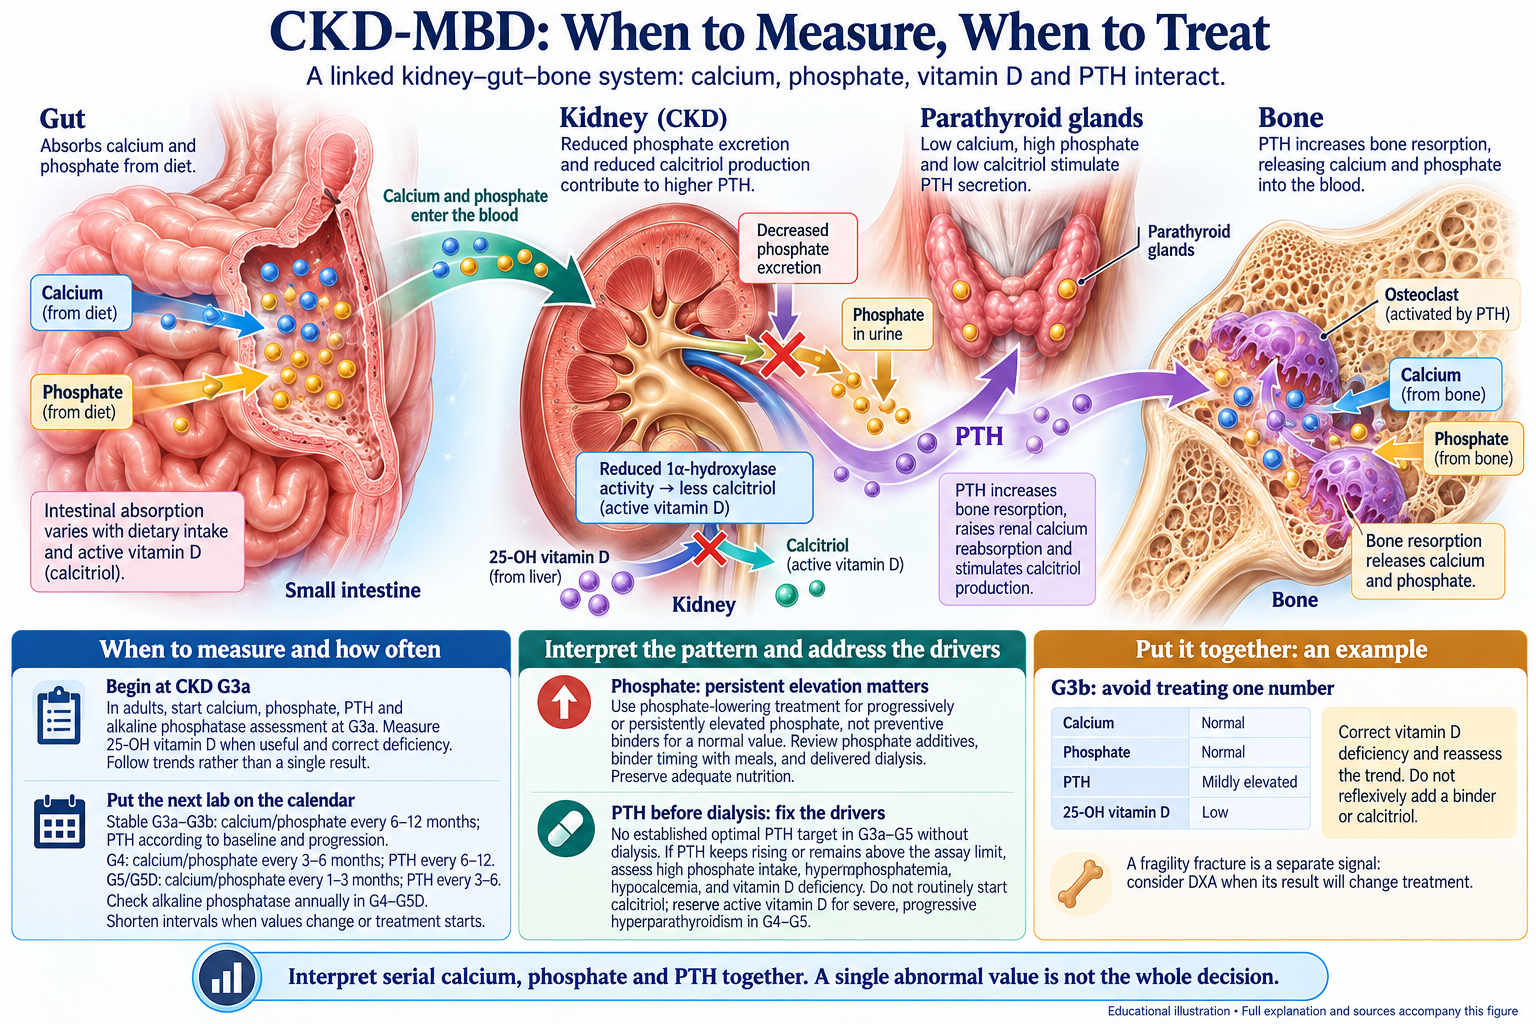
Browse the visual reference library · Download lesson Markdown
1. Why Phosphate, and Why Now
Hyperphosphatemia is the single most consistent biochemical abnormality of advanced CKD, and serum phosphate is the central biochemical metric in CKD-MBD. The KDIGO 2017 Update reframed the field’s stance: where the K/DOQI 2003 guidelines specified a strict 3.5–5.5 mg/dL target for dialysis patients, KDIGO 2017 recommends “lowering elevated phosphate toward the normal range” — a calibrated softening that reflects the absence of randomized evidence supporting any specific numerical target [1].
The shift matters operationally. ESRD QIP, KCQA, and CMS Five-Star metrics still carry phosphate-related performance measures [1], and dialysis units still ration binders, dietary counseling, and dialysis prescription decisions around the 5.5 mg/dL threshold. The clinical practice has not always caught up to the guideline ambiguity. The honest framing for trainees and practicing nephrologists is that phosphate management sits at the intersection of strong observational signal, weak interventional evidence, regulatory inertia, and a rapidly evolving therapeutic landscape that now includes a fundamentally different class of agent.
This review covers five domains: quality metrics and target evolution; observational outcome data; the central skeptical question of whether lowering phosphate improves hard outcomes; the comparative binder landscape; and the new non-binder agent tenapanor (Xphozah), including its regulatory and coverage trajectory.
2. Quality Metrics — KDIGO, KDOQI, ESRD QIP, and the Target Evolution
2.1 The KDIGO 2017 reframing
KDIGO 2003 / K/DOQI 2003 specified phosphate targets of 3.5–5.5 mg/dL in dialysis patients with calcium-phosphate product < 55 mg²/dL² [1]. These numerical targets drove a generation of dialysis quality programs and pay-for-performance metrics. The KDIGO 2017 CKD-MBD Update (Recommendation 4.1.1) deliberately moved away from strict numerical targets and toward a directional framework: “in patients with CKD G3a–G5D, we suggest lowering elevated serum phosphate levels toward the normal range” (level 2C, weak recommendation, low-quality evidence) [1].
The change was driven by an honest reading of the trial evidence — there was none demonstrating that hitting any specific phosphate number improved survival, cardiovascular events, or fracture. The framework retained the clinical priority (treat hyperphosphatemia) but abandoned the false precision of a hard cut-point.
Operationally, most dialysis units still treat 5.5 mg/dL as the actionable threshold, both because it remains the regulatory anchor (ESRD QIP performance scoring) and because the observational mortality signal does steepen above approximately 5.5 mg/dL [2,3].
2.2 ESRD QIP, KCQA, MIPS — what gets measured and why
ESRD QIP (CMS): Hypercalcemia (3-month rolling mean total serum calcium ≥ 10.2 mg/dL) is the directly-measured mineral metabolism quality metric in current ESRD QIP [1]. Hyperphosphatemia is not currently a direct performance measure but appears in clinical performance reporting through transparency mechanisms. The pragmatic effect: facility medical directors monitor phosphate-control percentages because they shape bundled-payment performance and Five-Star ratings even when the metric is not explicitly punitive.
KCQA (Kidney Care Quality Alliance): Has historically endorsed phosphate-related dialysis quality measures; the current KCQA core set continues to include mineral metabolism markers.
MIPS (Merit-Based Incentive Payment System): Nephrology MIPS measures touch CKD-MBD primarily through CKD progression and process measures (e.g., serum phosphorus monitored at appropriate intervals in CKD G4–G5). Outcome-based phosphate measures are not currently part of the MIPS nephrology specialty set.
2.3 Why the upper bound shifted
Three pieces of evidence converged. First, the observational mortality signal at the high end of phosphate distribution proved robust across multiple cohorts (Block 2004 [2], DOPPS [4], COSMOS [5]). Second, attempts to demonstrate that lowering phosphate with binders improves hard outcomes produced consistently null or marginal results (DCOR [6], INDEPENDENT [7], multiple meta-analyses). Third, the lower-bound concern — that very-low phosphate also tracks mortality (the U-shape) — undermined the case for aggressive lowering of mildly elevated values [8]. The combined effect: KDIGO acknowledged uncertainty, kept the directional priority, dropped the numerical target.
The 5.5 mg/dL threshold persists in clinical practice despite KDIGO 2017’s softening. Treat it as a clinical action threshold rather than a hard quality target — because that is exactly what KDIGO intends. The framework is “lower toward normal,” not “achieve 3.5 to 5.5.”
3. Outcomes Associated With Phosphate
3.1 The observational signal is large and consistent
Higher serum phosphate is associated with mortality in dialysis patients across virtually every cohort that has examined the question. The headline data:
- Block GA 2004 (J Am Soc Nephrol) — the foundational 40,538-patient analysis from the Fresenius database. Serum phosphate > 5.0 mg/dL was associated with progressively increased all-cause mortality; the relationship was monotonic and steep above 6.5 mg/dL [2].
- DOPPS — across multiple international cohort waves (12 countries, > 25,000 hemodialysis patients), serum phosphate > 5.5 mg/dL was consistently associated with increased all-cause and cardiovascular mortality. The DOPPS analyses also identified the U-shape — phosphate < 3.5 mg/dL carried similar or greater mortality risk than mid-range values, plausibly reflecting protein-energy wasting and inadequate intake rather than the phosphate level itself [4].
- Recent UpToDate-cited meta-analysis — 12 studies, 92,345 patients (approximately 97% on dialysis): per 1 mg/dL increase in serum phosphorus, mortality risk increased by 18% (95% CI 1.12–1.25) [9].
- Nondialysis CKD meta-analysis — 3 studies, approximately 5,000 patients with non-dialysis CKD: 35% increase in mortality per 1 mg/dL increase (95% CI 1.16–1.57) [9].
The biological framework is mechanistically coherent. Elevated phosphate drives FGF-23 elevation, secondary hyperparathyroidism, vascular smooth muscle calcification (via Pit-1 transporter and osteoblastic transdifferentiation), and accelerated arteriosclerosis. The cardiovascular burden of CKD-MBD is a real biology, not a statistical artifact.
3.2 The U-shape
Phosphate behaves like albumin and BMI in the dialysis population. Very-high values track mortality through the calcification-FGF23-cardiovascular-event pathway. Very-low values track mortality through protein-energy wasting, malnutrition, inflammation, and inadequate intake. The U-shape implies that aggressive lowering of mildly-elevated phosphate may not be benign — particularly if it requires aggressive dietary protein restriction in patients already at risk for malnutrition [8,10].
This nuance is missed by quality metrics that score “percent of patients with phosphate in target range” without distinguishing the direction of out-of-range. A patient with phosphate 3.0 mg/dL on a low-protein diet may carry worse prognosis than a patient with phosphate 6.0 mg/dL adequately nourished and on appropriate binder therapy. The metric does not capture this.
3.3 Hard outcomes beyond mortality
- Vascular and valvular calcification — mechanistic and observational data consistently link phosphate to accelerated coronary artery calcium progression and cardiac valve calcification. The Treat-to-Goal trial (Chertow 2002) used coronary and aortic calcification as the primary endpoint specifically because the imaging signal was clear [11].
- Fracture — disordered mineral metabolism is associated with fracture risk in dialysis, but the relationship to serum phosphate specifically is confounded by PTH, vitamin D status, bone turnover state, and adynamic bone disease.
- Hospitalization — DOPPS and US Renal Data System analyses associate hyperphosphatemia with increased hospitalization, with mineral metabolism abnormalities clustering with cardiovascular admissions.
3.4 Causal inference — the limit of observational data
The observational signal is consistent and biologically plausible. It is also confounded by everything that elevates phosphate in the first place: residual kidney function, dialysis adequacy, dietary intake, adherence to binders, GI absorption variability, and the unmeasured comorbidity burden that comes with poor phosphate control. The patients who maintain phosphate < 5.5 mg/dL are also the patients more adherent to therapy, more nutritionally stable, and more clinically engaged. Mortality may track phosphate because both track an underlying gestalt of disease severity.
Mendelian randomization analyses have been attempted but the genetic instruments for phosphate are weak. The clean answer would be a randomized trial of phosphate target. We did not have one until very recently.
Observational phosphate–mortality associations may reflect nutrition, inflammation, residual kidney function, and other confounding. Randomized target trials address a different question: whether changing phosphate targets improves patient-important outcomes.
4. Does Lowering Phosphate Actually Improve Hard Outcomes?
This is the central skeptical question for the practicing nephrologist. The honest answer, as of 2026, is probably not at the population level, and we still don’t have a definitive trial.
4.1 What we have
- DCOR (Suki 2007, Kidney Int) [6] — the largest randomized trial of phosphate-binder choice ever conducted. 2,103 incident hemodialysis patients randomized to sevelamer vs calcium-based binder, primary endpoint all-cause mortality. No overall mortality difference (HR 0.93, 95% CI 0.79–1.10). Subgroup analysis suggested benefit in patients age ≥ 65 (HR 0.77, p = 0.02), but the prespecified primary analysis was null.
- INDEPENDENT (Di Iorio 2012–2014) [7] — Italian incident-dialysis trial of sevelamer vs calcium carbonate. Reported a survival advantage for sevelamer, but trial size, attrition, and methodological concerns have limited its impact on guideline writing.
- Treat-to-Goal (Chertow 2002, Kidney Int) [11] — randomized 200 hemodialysis patients to sevelamer or calcium-based binder for 52 weeks. Primary endpoint: change in coronary artery calcium score and aortic calcification. Sevelamer arm showed less progression of coronary and aortic calcification. Surrogate endpoint, not mortality.
HiLo results were published in 2025. The trial enrolled 793 participants and stopped early because of insufficient enrollment and inadequate phosphate separation. Its primary hierarchical mortality/hospitalization outcome did not differ significantly between higher and lower targets. These limitations prevent a reliable conclusion about the clinical effects of the targets; the result does not establish equivalence or justify permissive hyperphosphatemia. Edmonston et al., 2025. Reference [13] describes the original design.
4.2 Surrogate vs patient-relevant outcomes
The binder-choice trials have consistently shown: - Surrogate improvement with non-calcium agents (less coronary artery calcium progression, lower FGF-23 levels, lower calcium burden) - No clear hard-outcome improvement in adequately-powered randomized comparisons
This is the central tension. Nephrology has spent two decades treating phosphate based on the assumption that the surrogate-outcome story would translate to hard outcomes. The trial evidence has not delivered. The pragmatic field response has been to keep treating phosphate (because the observational signal is real, the biology is plausible, and the regulatory and quality framework demands it) while acknowledging that the population-level mortality benefit of any specific intervention is unproven.
4.3 The honest assessment
Treat persistently elevated phosphate in the context of calcium, PTH, nutrition, dialysis delivery, and patient priorities. Discuss barriers before escalating treatment. Choose the binder or tenapanor strategy according to the clinical indication, safety, response, and current label; do not turn trial names into separate regulatory indications. Explain uncertainty about patient-important outcomes without dismissing biochemical management.
- Treat clearly elevated phosphate (e.g., > 6.5 mg/dL on serial measurements) — the observational signal is strong enough to act on
- Avoid the false precision of chasing a specific numerical target
- Recognize that pill burden, GI tolerability, adherence, and patient quality of life are real costs of binder therapy
- Be skeptical of any aggressive intervention that has not been shown to improve patient-relevant outcomes
Phosphate management in dialysis is one of the few areas where the gap between observational signal and randomized evidence is wide enough to warrant honest skepticism in patient counseling. When a patient struggles with binder pill burden or GI side effects, the clinical balance is genuinely closer than the quality metrics suggest.
5. Phosphate Binders — Comparative Landscape
Six binder classes are in current use. The decision matrix balances efficacy (mg of phosphate bound per gram of agent), safety (calcium load, accumulation, GI tolerability, pill burden), and cost. None has demonstrated unequivocal superiority on hard outcomes against any other.
5.1 Comparative table
| Binder class | Examples | PO4-binding potency | Pill burden (typical) | Major safety concerns | Outcome data |
|---|---|---|---|---|---|
| Calcium-based | Calcium carbonate (Tums, generic), calcium acetate (PhosLo) | Moderate | High (4–9 tablets/day) | Calcium load → vascular/valvular calcification; hypercalcemia | Treat-to-Goal: more CAC progression vs sevelamer [11]. DCOR: no mortality difference vs sevelamer overall [6] |
| Sevelamer (non-calcium polymer) | Sevelamer carbonate (Renvela), sevelamer HCl (Renagel) | Moderate | High (6–12 tablets/day typical) | GI intolerance, modest LDL reduction (pleiotropic) | Treat-to-Goal: less CAC progression [11]. DCOR: null overall mortality, signal in age ≥ 65 [6]. INDEPENDENT: survival advantage [7] |
| Lanthanum carbonate | Fosrenol | High (potent) | Low (1 tablet TID; chewable) | Long-term tissue accumulation (bone, liver — concerns more theoretical than clinical) | Less robust outcome data; effective surrogate-endpoint reduction |
| Iron-based: ferric citrate | Auryxia | High | Moderate (8–12 tablets/day) | Increased iron absorption (Hgb improvement, ferritin rise — can reduce IV iron and ESA need) | Lewis 2015 JASN pivotal trial: ferric citrate maintained PO4 control, increased iron stores, reduced IV iron and ESA requirements [14] |
| Iron-based: sucroferric oxyhydroxide | Velphoro | High | Low (3 tablets/day typical) | GI intolerance (discoloration of stool, mild diarrhea); minimal iron absorption | Floege phase 3 vs sevelamer: non-inferior PO4 control, lower pill burden [15] |
| Magnesium-containing | Calcium acetate + magnesium carbonate (OsvaRen, MagneBind) | Moderate (combination) | Moderate | Hypermagnesemia (mild); reduces calcium load when partially substituted | Limited outcome data; CALMAG trial showed non-inferior PO4 control vs sevelamer with lower calcium exposure [16] |
5.2 Calcium vs non-calcium — the mortality question
The COSMOS observational analysis and several systematic reviews have found higher mortality with calcium-based binders compared with non-calcium binders [5,17]. The clearest randomized signal comes from INDEPENDENT (Di Iorio) [7]. DCOR did not replicate this overall (only in age ≥ 65 subgroup) [6]. KDIGO 2017 reflects the uncertainty by recommending restricting calcium-based binder dose rather than declaring sevelamer or other non-calcium agents superior.
The pragmatic position: avoid calcium-based binders in patients with known vascular calcification, low PTH, adynamic bone disease, or hypercalcemia. Use them when cost and pill burden tip the balance — generic calcium acetate remains the cheapest and is reasonable in selected patients.
5.3 Iron-based binders — the dual benefit
Ferric citrate (Auryxia) and sucroferric oxyhydroxide (Velphoro) are both effective phosphate binders with very different iron-absorption profiles. Ferric citrate is absorbed substantially as elemental iron — the Lewis 2015 pivotal trial demonstrated meaningful increases in serum ferritin and TSAT, with a corresponding reduction in IV iron and ESA requirements [14]. This is a real bundled-payment economic argument when dialysis units are managing IV iron and ESA expense. Sucroferric oxyhydroxide is minimally absorbed, so it does not produce the iron-stores benefit but offers the lowest pill burden in the field (approximately 3 tablets/day) — a meaningful adherence advantage [15].
5.4 Pill burden, adherence, and the patient experience
The average dialysis patient on phosphate binders takes 8–12 tablets per day, often spread across all meals, alongside the rest of their dialysis pharmacopeia. Pill burden is a primary driver of non-adherence, and non-adherence is the most common reason for “refractory” hyperphosphatemia. Any honest binder discussion must include patient-experience and adherence reality, not just biochemistry.
When a patient is genuinely overwhelmed by pill burden and has reasonable adherence to dialysis, sucroferric oxyhydroxide (Velphoro) at 3 tablets per day is the cleanest single-intervention solution to consolidate binder therapy.
6. Tenapanor (Xphozah) — A Different Mechanism
Tenapanor is the first non-binder agent approved for hyperphosphatemia in dialysis. It is a fundamentally different therapeutic class, and its arrival changes the algorithm.
6.1 Mechanism
Tenapanor inhibits intestinal NHE3, reducing sodium absorption and phosphate permeability through the paracellular pathway. It does not bind phosphate. Reduced sodium absorption increases intestinal water content and can produce diarrhea. The phosphate effect and gastrointestinal effects require separate efficacy and tolerability assessment [18]. XPHOZAH prescribing information.
Tenapanor is taken before the morning and evening meals. The recommended dose is 30 mg twice daily, with phosphorus monitoring and dose adjustment for gastrointestinal tolerance. Do not take it immediately before hemodialysis; take it before the next meal after dialysis. Drug interactions remain possible, including reduced exposure to OATP2B1 substrates such as enalapril; non-binder action does not mean interaction-free treatment. XPHOZAH prescribing information.
6.2 The trial program — BLOCK, AMPLIFY, PHREEDOM
| Trial | Citation | Design | n | Result |
|---|---|---|---|---|
| BLOCK | Block GA et al. JASN 2019;30(4):641-652 [19] | Phase 3 randomized double-blind dose-finding (3, 10, 30 mg BID), 8-week treatment + 4-week withdrawal | 219 | All three doses produced significant phosphate reduction (1.00, 1.02, 1.19 mg/dL respectively); withdrawal phase: tenapanor +0.02 vs placebo +0.85 mg/dL |
| AMPLIFY | Pergola PE et al. JASN 2021;32(6):1465-1473 [20] | Phase 3 RCT of tenapanor 30 mg BID add-on to existing binder therapy vs placebo + binder, 4 weeks | 236 | Tenapanor + binder: −0.84 mg/dL vs placebo + binder: −0.19 mg/dL (p < 0.001). Diarrhea-related discontinuation: 3.4% tenapanor vs 1.7% placebo |
| PHREEDOM | Block GA et al. Kidney360 2021;2(10):1600-1610 [21] | 52-week phase 3, 3:1 randomization to tenapanor 30 mg BID (26 weeks) vs sevelamer carbonate (52 weeks safety control); then re-randomization to tenapanor or placebo for 12-week withdrawal | 564 | Efficacy analysis set (n=131): −1.4 mg/dL (p < 0.0001) [21]; ITT: −0.7 mg/dL (p = 0.002) [21]. Loosened stools: 53% [21] during randomized treatment period |
The phase 3 program demonstrated phosphate lowering in the studied withdrawal and add-on designs [19–21]. These results do not establish improved survival or one universally preferred regimen. XPHOZAH is indicated in adults with CKD on dialysis as add-on therapy when response to phosphate binders is inadequate or when any dose of binder therapy is not tolerated. The trials and indication should not be described as an initial general monotherapy approval followed by an add-on expansion. XPHOZAH prescribing information.
6.3 The diarrhea question — manageable but real
Diarrhea is a common adverse reaction and can be severe. Monitor symptoms, fluid status, and phosphorus; adjust the prescribed dose according to gastrointestinal tolerance. Discontinue tenapanor if severe diarrhea develops and assess dehydration and electrolytes promptly. Do not require a patient to wait through an adaptation period or continue until functional impairment occurs. XPHOZAH prescribing information.
6.4 Positioning — monotherapy, add-on, or binder replacement
The current operational positioning emerging from the trial data and post-marketing experience:
- Inadequate response to binders — AMPLIFY studied add-on treatment. The patient is on adequate binder therapy but cannot achieve target phosphate without further intervention. Tenapanor adds a different mechanism to the existing approach. This avoids the binder-replacement decision entirely.
- Binder intolerance — the label also addresses patients unable to tolerate any dose of binder therapy. Pill burden should inform the assessment but does not independently establish this indication.
- Longer follow-up — PHREEDOM assessed longer-term phosphate control and safety in its trial design; ongoing response and tolerability must still be reviewed [21].
Selection depends on inadequate binder response or intolerance, phosphate trajectory, treatment burden, gastrointestinal risks, interactions, and patient priorities. The available trials do not establish that one broad patient phenotype always benefits most.
Explain expected bowel changes and how to obtain advice before starting treatment. Diarrhea remains an adverse effect even when related to the mechanism. Severe diarrhea requires stopping treatment and prompt clinical assessment.
6.5 Cost and coverage — Part B vs Part D, TDAPA, the bundle debate
This is the active operational and policy question for 2025–2026 nephrology practice.
The CMS ESRD bundled prospective payment system (PPS) historically excluded oral-only ESRD-related drugs from the bundle, with separate billing under Medicare Part D. Tenapanor was approved in 2023 and entered Medicare coverage initially through Part D. CMS proposed inclusion of oral-only ESRD drugs (including tenapanor and oral phosphate binders) in the ESRD bundle, with TDAPA (Transitional Drug Add-on Payment Adjustment) status as a transition mechanism.
The current 2025–2026 status: - Tenapanor is currently in TDAPA status for two years following bundle inclusion (timeline subject to CMS rule changes) - Phosphate binders themselves were also targeted for bundle inclusion under the 2025 ESRD PPS Final Rule, with TDAPA support. This is the operational change with the largest impact: dialysis units now receive bundled payment for binders that were previously billed separately under Part D - Practical effect — dialysis units now have direct economic exposure to binder choice in a way they did not before. Selection toward lower-cost binders (calcium carbonate, generic calcium acetate) becomes economically rational at the unit level even when clinical considerations argue for non-calcium agents - Tenapanor pricing is driven by Ardelyx (the manufacturer); during TDAPA coverage, dialysis units can prescribe without absorbing the full agent cost, but at TDAPA expiration the bundle calculation must absorb the agent cost or the unit will lose money on tenapanor prescriptions
The implication for practice: the next 2–3 years will determine whether tenapanor remains broadly accessible or becomes a payer-formulary-restricted agent based on bundle economics. Nephrologists who want to use tenapanor for the right patient should document the indication and rationale clearly to support coverage decisions.
7. Practical Algorithm
flowchart TD
    A[Maintenance dialysis patient<br/>PO4 > 5.5 mg/dL on serial labs] --> B[Confirm dietary counseling<br/>Optimize dialysis prescription<br/>Reinforce binder timing]
    B --> C{PO4 still elevated<br/>after 4–6 weeks?}
    C -->|No| D[Continue current regimen,<br/>monitor monthly]
    C -->|Yes| E[Initiate or escalate binder]
    E --> F{Calcium load<br/>concerns?}
    F -->|Yes — vascular Ca, low PTH, hyperCa| G[Non-calcium binder:<br/>sevelamer, lanthanum,<br/>or iron-based]
    F -->|No — cost / pill burden tips| H[Calcium acetate or carbonate]
    G --> I{Adequate control<br/>with reasonable pill burden?}
    H --> I
    I -->|Yes| D
    I -->|No — refractory or pill burden problem| J[Add tenapanor 30 mg BID<br/>AMPLIFY indication]
    J --> K{Tolerated?}
    K -->|Yes| L[Continue tenapanor + binder<br/>combination]
    K -->|GI intolerance| M[Adjust per label for tolerability;<br/>stop for severe diarrhea;<br/>reassess treatment and volume status]
8. Refractory Hyperphosphatemia — The Honest Differential
When a patient stays above 6.5 mg/dL despite reasonable binder therapy, the differential is rarely “needs more medication.” It is almost always one of:
- Adherence — pill burden, side effects, schedule complexity, cost. The most common reason. Direct conversation, not biochemistry, is the diagnostic tool.
- Inadequate dialysis — short dialysis time, reduced frequency, missed sessions, suboptimal flux/clearance. Optimize the dialysis prescription before escalating drug therapy.
- Excess dietary intake — hidden phosphate additives in processed foods, dairy, cola, organ meats. Renal dietitian referral if not already engaged.
- GI absorption variability — small bowel transit, gut motility, concurrent medications affecting binder activity (PPI use, antibiotics).
- Hyperparathyroidism — uncontrolled secondary HPT mobilizes phosphate from bone. Address PTH (cinacalcet, etelcalcetide, vitamin D analogues) as a parallel intervention.
- Genuine binder resistance — the indication for tenapanor add-on (the AMPLIFY scenario).
“Refractory” hyperphosphatemia is almost always adherence, dialysis adequacy, dietary intake, or hyperparathyroidism — not pharmacologic failure. Confirm all four before escalating drug therapy.
9. Clinical Pearls and Warnings
A 667 mg calcium acetate tablet contains approximately 169 mg elemental calcium; 1334 mg (two such tablets) contains approximately 338 mg. Six 667 mg tablets supply about 1.014 g elemental calcium. Review total calcium exposure, calcium/PTH trends, and calcification risk. KDIGO 2017 recommends restricting calcium-based binder doses; it does not establish the claimed universal 1 g/day binder ceiling. Calcium acetate labeling.
Sucroferric oxyhydroxide (Velphoro) at 3 tablets per day is the lowest-pill-burden binder option in current use. For the patient overwhelmed by pill count, this is often the single-intervention solution.
Ferric citrate (Auryxia) increases iron stores and can reduce IV iron and ESA requirements. Useful in iron-deficient dialysis patients where the dual benefit makes economic and clinical sense.
Counsel before the first dose. Review tolerability during treatment; severe diarrhea requires discontinuation and assessment. Do not dismiss an adverse effect as proof that the medicine is working.
Phosphate < 3.5 mg/dL in a dialysis patient is not a quality success — it usually signals protein-energy wasting, inadequate intake, or aggressive over-binding. Investigate, do not celebrate.
The largest randomized binder-mortality trial (DCOR, Suki 2007) was null for the primary endpoint. The field acts on observational data and consensus, not on RCT evidence. Be honest with patients about the limits of what we know.
With phosphate binders now in the ESRD bundle (TDAPA transition), unit-level economics now influence binder selection in ways that did not exist 2 years ago. Document indication and rationale clearly when prescribing non-formulary or higher-cost binders.
10. Summary
Hyperphosphatemia remains a clinically important component of CKD-MBD. KDIGO 2017 recommends interpreting serial phosphate, calcium, and PTH together and lowering persistently elevated phosphate toward normal [1]. Binder trials and the underpowered HiLo target trial do not establish an optimal mortality-reducing target. Balance biochemical control with nutrition, calcium exposure, pill burden, tolerability, and patient priorities.
Binder selection should consider calcium exposure, phosphate response, iron status, gastrointestinal tolerance, pill burden, and access. Tenapanor supplies a non-binder mechanism for the label-defined inadequate-response or binder-intolerance setting [19–21]. Monitor phosphorus and tolerability; severe diarrhea requires discontinuation and assessment. Clinical outcome evidence and biochemical efficacy are distinct.
Treat persistently elevated phosphate in the context of calcium, PTH, nutrition, dialysis delivery, and patient priorities. Discuss barriers before escalating treatment. Choose the binder or tenapanor strategy according to the clinical indication, safety, response, and current label; do not turn trial names into separate regulatory indications. Explain uncertainty about patient-important outcomes without dismissing biochemical management.
References
Ketteler M, Block GA, Evenepoel P, et al. Executive summary of the 2017 KDIGO Chronic Kidney Disease-Mineral and Bone Disorder (CKD-MBD) Guideline Update: what’s changed and why it matters. Kidney Int. 2017;92(1):26-36. PMID: 28646995
Block GA, Klassen PS, Lazarus JM, Ofsthun N, Lowrie EG, Chertow GM. Mineral metabolism, mortality, and morbidity in maintenance hemodialysis. J Am Soc Nephrol. 2004;15(8):2208-18. PMID: 15284307
Block GA, Hulbert-Shearon TE, Levin NW, Port FK. Association of serum phosphorus and calcium x phosphate product with mortality risk in chronic hemodialysis patients: a national study. Am J Kidney Dis. 1998;31(4):607-17. PubMed: 9531176
Tentori F, Blayney MJ, Albert JM, et al. Mortality risk for dialysis patients with different levels of serum calcium, phosphorus, and PTH: the Dialysis Outcomes and Practice Patterns Study (DOPPS). Am J Kidney Dis. 2008;52(3):519-30. PubMed: 18514987
Fernández-Martín JL, Martínez-Camblor P, Dionisi MP, et al. Improvement of mineral and bone metabolism markers is associated with better survival in haemodialysis patients: the COSMOS study. Nephrol Dial Transplant. 2015;30(9):1542-51. PubMed: 25920921
Suki WN, Zabaneh R, Cangiano JL, et al. Effects of sevelamer and calcium-based phosphate binders on mortality in hemodialysis patients (DCOR). Kidney Int. 2007. PubMed: 17728707
Di Iorio B, Molony D, Bell C, et al. Sevelamer versus calcium carbonate in incident hemodialysis patients (INDEPENDENT): results of an open-label, randomized clinical trial. Am J Kidney Dis. 2013. PubMed: 23684755
Kalantar-Zadeh K, Kuwae N, Regidor DL, et al. Survival predictability of time-varying indicators of bone disease in maintenance hemodialysis patients. Kidney Int. 2006;70(4):771-80. PubMed: 16820797
Palmer SC, Hayen A, Macaskill P, Pellegrini F, Craig JC, Elder GJ, Strippoli GFM. Serum levels of phosphorus, parathyroid hormone, and calcium and risks of death and cardiovascular disease in individuals with chronic kidney disease: a systematic review and meta-analysis. JAMA. 2011;305(11):1119-27. PubMed: 21406649
Lopes AA, Tong L, Thumma J, et al. Phosphate binder use and mortality among hemodialysis patients in the Dialysis Outcomes and Practice Patterns Study (DOPPS): evaluation of possible confounding by nutritional status. Am J Kidney Dis. 2012;60(1):90-101. PubMed: 22385781
Chertow GM, Burke SK, Raggi P; Treat to Goal Working Group. Sevelamer attenuates the progression of coronary and aortic calcification in hemodialysis patients. Kidney Int. 2002. PubMed: 12081584
Wald R, Thorpe KE, Walsh MW. Leveraging pragmatic clinical trial design to advance phosphate management in end-stage renal disease. Curr Opin Nephrol Hypertens. 2019;28(1):34-39. PubMed: 30480640
Edmonston DL, Isakova T, Dember LM, et al. Design and Rationale of HiLo: A Pragmatic, Randomized Trial of Phosphate Management for Patients Receiving Maintenance Hemodialysis. Am J Kidney Dis. 2021;77(6):920-930. PubMed: 33279558
Lewis JB, Sika M, Koury MJ, et al. Ferric citrate controls phosphorus and delivers iron in patients on dialysis. J Am Soc Nephrol. 2015;26(2):493-503. PubMed: 25060056
Floege J, Covic AC, Ketteler M, et al. A phase III study of the efficacy and safety of a novel iron-based phosphate binder in dialysis patients (PA21 / sucroferric oxyhydroxide). Kidney Int. 2014;86(3):638-47. PubMed: 24646861
de Francisco AL, Leidig M, Covic AC, Ketteler M, et al. Evaluation of calcium acetate/magnesium carbonate as a phosphate binder compared with sevelamer hydrochloride in haemodialysis patients: a controlled randomized study (CALMAG study) assessing efficacy and tolerability. Nephrol Dial Transplant. 2010;25(11):3707-17. PubMed: 20530499
Jamal SA, Vandermeer B, Raggi P, et al. Effect of calcium-based versus non-calcium-based phosphate binders on mortality in patients with chronic kidney disease: an updated systematic review and meta-analysis. Lancet. 2013;382(9900):1268-77. PubMed: 23870817
Spencer AG, Labonte ED, Rosenbaum DP, et al. Intestinal inhibition of the Na+/H+ exchanger 3 prevents cardiorenal damage in rats and inhibits Na+ uptake in humans. Sci Transl Med. 2014;6(227):227ra36. PubMed: 24622516
Block GA, Rosenbaum DP, Yan A, Chertow GM. Efficacy and Safety of Tenapanor in Patients with Hyperphosphatemia Receiving Maintenance Hemodialysis: A Randomized Phase 3 Trial (BLOCK). J Am Soc Nephrol. 2019;30(4):641-652. PubMed: 30846557
Pergola PE, Rosenbaum DP, Yang Y, Chertow GM. A Randomized Trial of Tenapanor and Phosphate Binders as a Dual-Mechanism Treatment for Hyperphosphatemia in Patients on Maintenance Dialysis (AMPLIFY). J Am Soc Nephrol. 2021;32(6):1465-1473. PubMed: 33766811
Block GA, Bleyer AJ, Silva AL, et al. Safety and Efficacy of Tenapanor for Long-term Serum Phosphate Control in Maintenance Dialysis: A 52-Week Randomized Phase 3 Trial (PHREEDOM). Kidney360. 2021;2(10):1600-1610. PubMed: 35372979
Medical Associates Department of Nephrology | University of Illinois College of Medicine at Peoria | University of Dubuque PA Program | Butler College of Osteopathic Medicine