Enterococcal Endocarditis in Hemodialysis: Evidence, Dosing, and Access
Visual reference
Browse the visual reference library · Download lesson Markdown
Coordinate Infection Treatment and Kidney Care
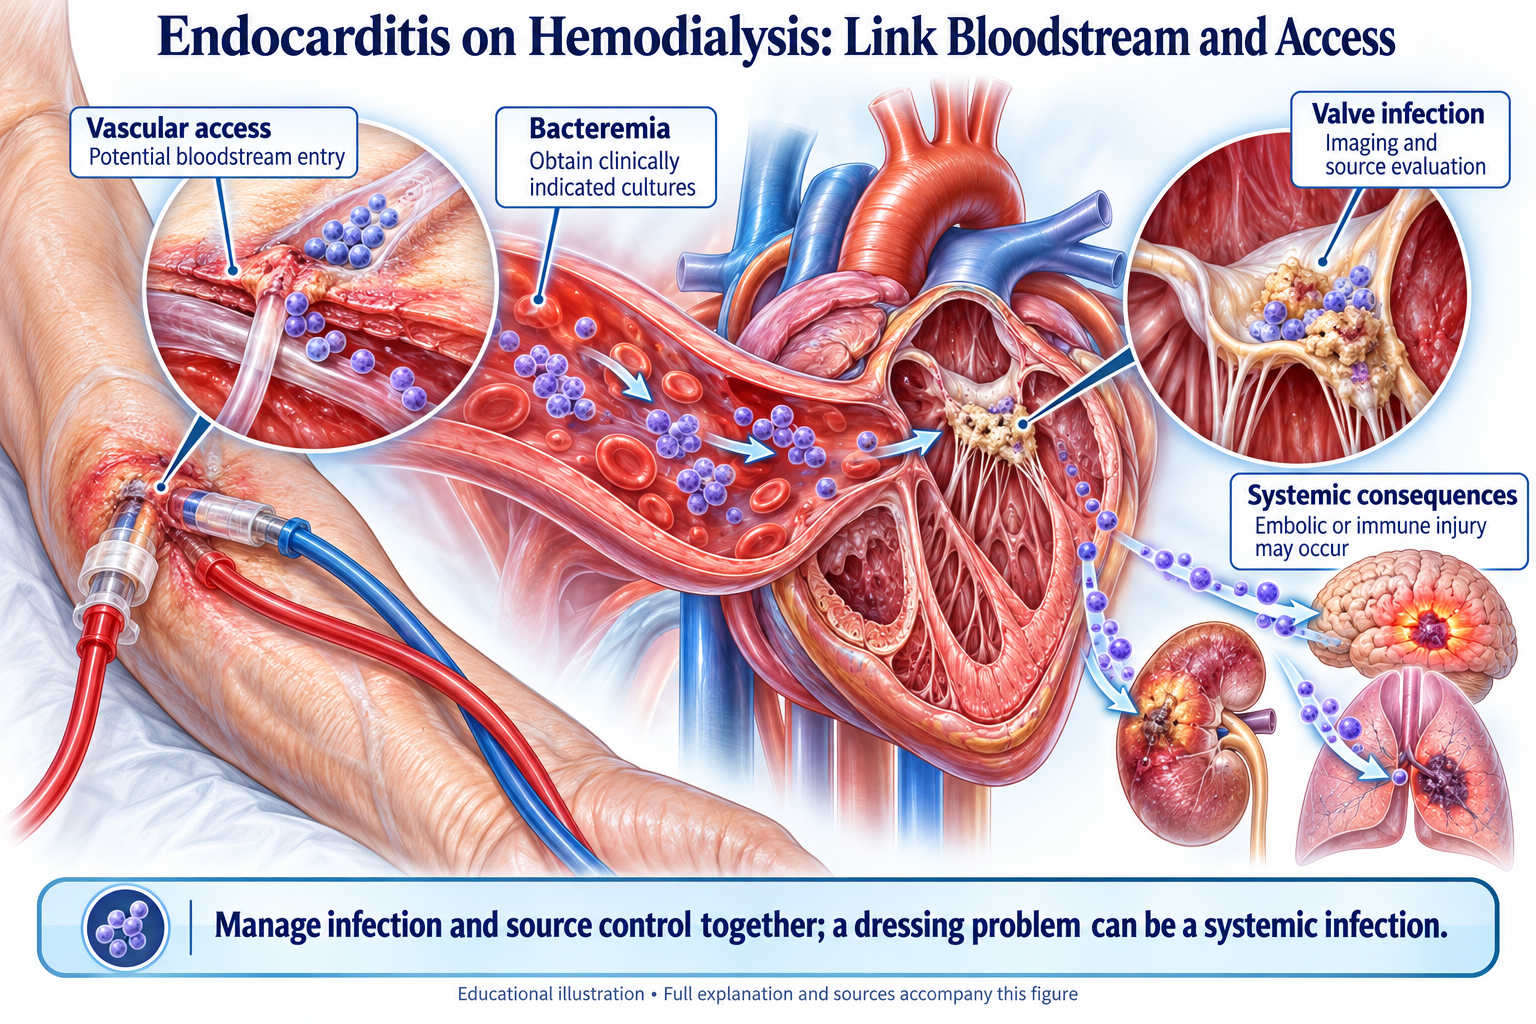
Enterococcal endocarditis in a patient receiving hemodialysis requires infectious-disease, cardiology, nephrology, and pharmacy coordination. Confirm the organism, susceptibility pattern, valve or device involvement, infection source, and complications. The dialysis schedule and vascular-access plan matter, but convenience cannot substitute for a regimen that provides adequate exposure for the infection.
Current endocarditis guidance supports a multidisciplinary team, appropriate imaging, microbiological diagnosis, assessment for surgery, and structured follow-up. A long antimicrobial half-life alone does not prove that a three-times-weekly regimen treats enterococcal endocarditis effectively. PubMed 37622656
Ampicillin–Ceftriaxone: What the Evidence Shows
For appropriate susceptible E. faecalis infections, ampicillin plus ceftriaxone is an established combination strategy. The foundational studies include a small nonrandomized clinical study and a larger observational comparison with ampicillin–gentamicin. The observational comparison found similar major outcomes and less treatment interruption from adverse effects with ampicillin–ceftriaxone. These are not randomized trials proving equivalence in every dialysis patient. PubMed 17438316; PubMed 23392394
A meta-analysis also found similar measured clinical outcomes and less nephrotoxicity with the dual beta-lactam approach, while inheriting limitations of the underlying studies. Dosing, interval, duration, and route still require adjustment to organism, renal function, dialysis modality, and infection characteristics. Do not copy the nondialysis dosing schedule from a trial into a dialysis prescription. PubMed 34751788
Dialysis Pharmacokinetics
Residual kidney function, protein binding, volume of distribution, dialyzer characteristics, session duration, and the timing of administration influence antibiotic exposure. Both the 48-hour and 72-hour interdialytic intervals need consideration. Acute illness may differ substantially from stable outpatient pharmacokinetic study populations.
Document the actual dialysis schedule, missed or shortened sessions, and medication timing. A post-dialysis regimen should be supported for the specific drug, organism, infection site, and target exposure. A regimen suitable for a susceptible uncomplicated infection may be inadequate for endocarditis. Pharmacy review is essential when extrapolating from small studies.
Daptomycin: Modeling Is Not a Cure-Rate Trial
A pharmacokinetic study in 12 adults receiving HD used modeling to compare exposure across interdialytic intervals. Its simulations addressed the longer weekend interval and sought to minimize high troughs associated with toxicity. The cited trough of 24.3 mg/L was a toxicity consideration, not a minimum therapeutic target to exceed. PubMed 21282429
A later pilot study examined high-dose daptomycin in HD patients with infected medical devices. Such studies inform specialist dosing; they do not establish that a fixed high-dose schedule plus intermittent ceftriaxone is clinically equivalent to standard E. faecalis endocarditis therapy. Drug choice and any combination require susceptibility data and specialist review. Monitor for myopathy and other adverse effects using current prescribing information. PubMed 28645706; PubMed 24259698
Ceftriaxone: Distinguish Its Roles
A 2023 population pharmacokinetic study evaluated three-times-weekly post-HD ceftriaxone in infected Indigenous Australian patients. It supports exposure assessment for selected susceptible bacterial infections in the studied setting. It did not test clinical equivalence of a dialysis-only enterococcal endocarditis combination. Enterococci are not being treated with ceftriaxone monotherapy merely because it has a prolonged half-life. PubMed 37367723
Consider protein binding, liver and kidney function, neurological symptoms, and interacting treatment. New confusion, myoclonus, or seizures during antibiotic treatment require prompt review; infection, metabolic disease, and drug toxicity all remain possible.
Resistant Organisms and Long-Acting Agents
Do not extrapolate E. faecalis treatment evidence to E. faecium or vancomycin-resistant isolates without checking susceptibility and the clinical literature. Resistance phenotype, source control, and combination rationale determine options.
Prolonged oritavancin use for vancomycin-resistant E. faecium prosthetic-valve endocarditis has been described in a case report. It is case-based salvage evidence, not proof of routine efficacy or an approved endocarditis regimen. Long-acting agents can be difficult to withdraw after toxicity and may interfere with some laboratory tests; follow current product guidance. PubMed 26677455
Teicoplanin continuation after initial standard therapy has observational data in selected E. faecalis endocarditis. Availability, susceptibility, therapeutic monitoring, and selection bias limit generalization. A favorable cohort does not validate every intermittent regimen. PubMed 30809761
Preserve Future Dialysis Access
PICC exposure is associated with worse subsequent dialysis-access outcomes. A case-control study and a larger observational study support taking vein preservation seriously. These associations do not mean every individual PICC causes access failure, nor do they establish a universal numerical risk for a specific patient. PubMed 22704142; PubMed 27340280
KDOQI frames vascular access within the individual ESKD Life-Plan. In advanced CKD or dialysis, discuss proposed PICC or other central access with the kidney and access teams. Consider existing access and suitable alternatives while accounting for infection source, required dosing, expected treatment duration, anatomy, and patient goals. Avoid categorical language that ignores exceptional clinical need. PubMed 32778223
Monitoring and Reassessment
Follow microbiological clearance, clinical course, drug toxicity, volume status, and dialysis delivery. Persistent bacteremia or deterioration should prompt reassessment of source control, complications, susceptibility, and antimicrobial exposure rather than simply lengthening treatment or increasing a dose.
The monitoring plan should specify responsible clinicians, laboratory frequency, symptom escalation, and what happens after missed dialysis. Depending on the regimen, blood counts, liver tests, creatine kinase, drug concentrations, and neurological assessment may be needed. Review concomitant medications and product-specific interactions. A universal trough target or laboratory stopping threshold is not appropriate across all agents.
Discharge and Follow-Up
Outpatient treatment is appropriate only after the endocarditis team confirms clinical stability, a supported regimen, reliable delivery, monitoring, and a plan for complications. Dialysis attendance alone does not ensure antibiotic adequacy. Communicate the full regimen and duration, culture results, surgery decisions, access plan, and follow-up responsibilities to the dialysis unit.
Assess success with infection control, adverse events, recurrence, access preservation, and patient experience. The percentage of patients receiving a convenient intermittent regimen is not itself a quality outcome.
Teaching Points
- Match the regimen to the organism and endocarditis evidence.
- Adjust for dialysis using pharmacology and specialist input.
- Separate pharmacokinetic modeling, observational studies, and isolated salvage cases.
- Preserve veins through an individualized access plan.
- Reassess cultures, source control, toxicity, and delivery throughout treatment.
References
- Delgado V, Ajmone Marsan N, de Waha S, et al. 2023 ESC Guidelines for the management of endocarditis. Eur Heart J 2023. PubMed 37622656.
- Gavaldà J, Len O, Miró JM, et al. Brief communication: treatment of Enterococcus faecalis endocarditis with ampicillin plus ceftriaxone. Ann Intern Med 2007. PubMed 17438316.
- Fernández-Hidalgo N, Almirante B, Gavaldà J, et al. Ampicillin plus ceftriaxone is as effective as ampicillin plus gentamicin for treating enterococcus faecalis infective endocarditis. Clin Infect Dis 2013. PubMed 23392394.
- Mirna M, Topf A, Schmutzler L, et al. Time to abandon ampicillin plus gentamicin in favour of ampicillin plus ceftriaxone in Enterococcus faecalis infective endocarditis? A meta-analysis of comparative trials. Clin Res Cardiol 2022. PubMed 34751788.
- Patel N, Cardone K, Grabe DW, et al. Use of pharmacokinetic and pharmacodynamic principles to determine optimal administration of daptomycin in patients receiving standardized thrice-weekly hemodialysis. Antimicrob Agents Chemother 2011. PubMed 21282429.
- Diolez J, Venisse N, Belmouaz S, et al. Pilot Pharmacokinetic Study of High-Dose Daptomycin in Hemodialysis Patients With Infected Medical Devices. Am J Kidney Dis 2017. PubMed 28645706.
- Haselden M, Leach M, Bohm N. Daptomycin dosing strategies in patients receiving thrice-weekly intermittent hemodialysis. Ann Pharmacother 2013. PubMed 24259698.
- Tsai D, Zam BB, Tongs C, et al. Validating a novel three-times-weekly post-hemodialysis ceftriaxone regimen in infected Indigenous Australian patients-a population pharmacokinetic study. J Antimicrob Chemother 2023. PubMed 37367723.
- Johnson JA, Feeney ER, Kubiak DW, et al. Prolonged Use of Oritavancin for Vancomycin-Resistant Enterococcus faecium Prosthetic Valve Endocarditis. Open Forum Infect Dis 2015. PubMed 26677455.
- De Nadaï T, François M, Sommet A, et al. Efficacy of teicoplanin monotherapy following initial standard therapy in Enterococcus faecalis infective endocarditis: a retrospective cohort study. Infection 2019. PubMed 30809761.
- El Ters M, Schears GJ, Taler SJ, et al. Association between prior peripherally inserted central catheters and lack of functioning arteriovenous fistulas: a case-control study in hemodialysis patients. Am J Kidney Dis 2012. PubMed 22704142.
- McGill RL, Ruthazer R, Meyer KB, et al. Peripherally Inserted Central Catheters and Hemodialysis Outcomes. Clin J Am Soc Nephrol 2016. PubMed 27340280.
- Lok CE, Huber TS, Lee T, et al. KDOQI Clinical Practice Guideline for Vascular Access: 2019 Update. Am J Kidney Dis 2020. PubMed 32778223.