Medication-Related Swelling: Mechanisms and Clinical Assessment
Visual reference
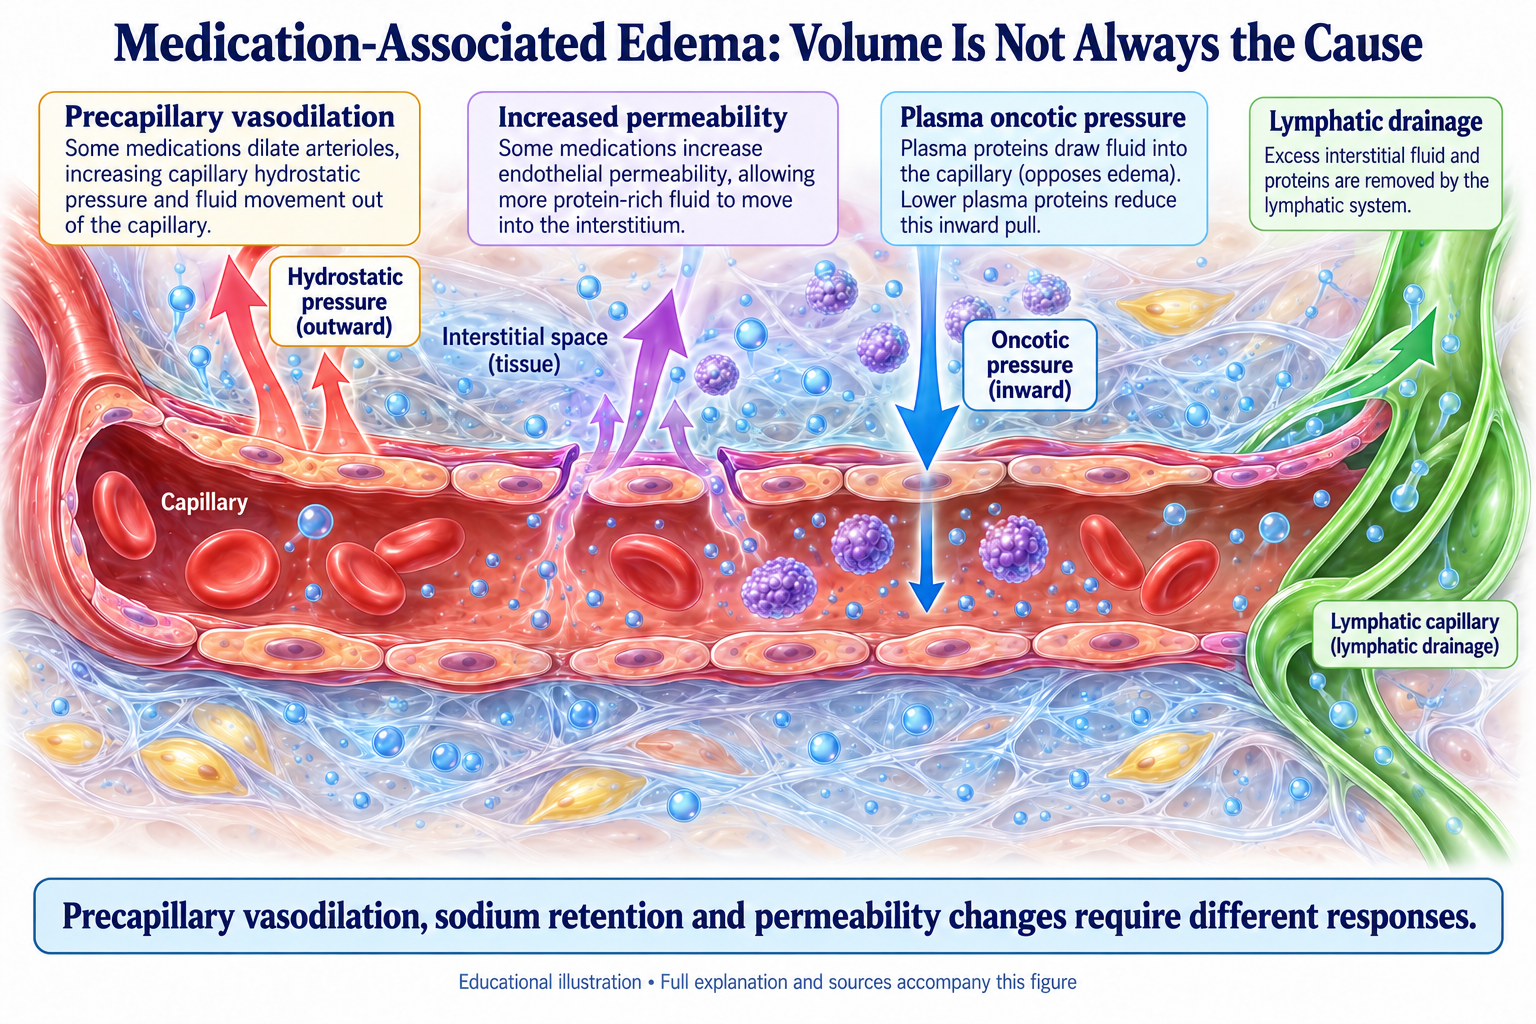
Browse the visual reference library · Download lesson Markdown
Overview
Medication-related edema is a clinical possibility when swelling begins after a new prescription or a dose change. It may coexist with heart failure, kidney disease, venous insufficiency, or lymphatic disease. Distinguishing sodium retention from altered capillary pressure or permeability helps avoid an ineffective prescribing cascade. Review both prescribed and over-the-counter products, including anti-inflammatory drugs.
Start with the Pattern
Record timing, distribution, weight change, symptoms, blood pressure, and recent kidney function. Bilateral ankle swelling after a vasodilator differs from rapidly progressive generalized edema with proteinuria or breathlessness. A temporal association supports suspicion but does not establish causality. Improvement after a supervised dose reduction or withdrawal can be informative.
Urgent evaluation takes priority for breathlessness, pulmonary edema, painful unilateral leg swelling, or facial, tongue, or throat swelling. Angioedema is distinct from dependent peripheral edema and may threaten the airway. Do not respond to every form of swelling by adding a loop diuretic. Largeau et al.; Sinnathamby et al.
NSAIDs
NSAIDs can reduce renal prostaglandin activity, promote sodium and water retention, raise blood pressure, and impair kidney perfusion in susceptible patients. Risk increases when kidney function or effective circulating volume is compromised. New edema with an NSAID should prompt review of creatinine, potassium, blood pressure, and other medications, including diuretics and renin–angiotensin system blockers. Consider an alternative analgesic strategy rather than simply escalating diuresis. Sinnathamby et al.
Calcium Channel Blockers
Dihydropyridines such as amlodipine can cause dose-related ankle edema through preferential precapillary arteriolar dilation. This raises capillary hydrostatic pressure and can occur without generalized volume overload. Diuretics may have limited benefit when this mechanism dominates.
Options include dose reduction, a different antihypertensive, or an appropriate combination regimen. Randomized-trial meta-analyses show that combining a calcium channel blocker with an ACE inhibitor or ARB can reduce edema compared with the blocker alone, although the effect varies across agents. Choose combinations for the whole clinical situation and monitor kidney function and potassium; do not add a drug solely to conceal an adverse effect. Liang et al.; Makani et al.
Corticosteroids
Systemic corticosteroids can contribute to salt and water retention, with effects depending on the specific agent, dose, duration, and patient. Assess blood pressure, weight, and competing explanations for edema. A taper or steroid-sparing strategy requires the treating team’s guidance; abrupt discontinuation after sustained exposure can be dangerous. The indication matters: corticosteroid premedication can reduce docetaxel-related fluid retention even though corticosteroids themselves may contribute to edema in other settings. Sinnathamby et al.; Piccart et al.
Thiazolidinediones
Pioglitazone and related PPAR-gamma agonists can expand extracellular volume and precipitate or worsen heart failure. Renal sodium retention and vascular effects contribute; the mechanism should not be reduced to one proven sodium channel. Weight gain with dyspnea or edema requires assessment for heart failure and review of continued treatment. Adding a diuretic without reconsidering the causative drug may leave the underlying problem unresolved. Bełtowski et al.
Gabapentin and Pregabalin
Both gabapentin and pregabalin can cause peripheral edema, including after dose escalation. A pharmacovigilance and experimental study supports altered vascular tone as one mechanism of noncardiogenic edema; spontaneous reports cannot provide a reliable population incidence. Reports also include heart failure, so breathlessness or congestion needs clinical evaluation.
Review the indication, dose, kidney function, recent titration, and concomitant sedatives. Consider supervised dose reduction, withdrawal, or an alternative when appropriate. Avoid treating the swelling indefinitely with another drug before assessing the original prescription. Largeau et al.
Hormonal Therapies
Ask about hormonal therapy as part of the medication history, but do not attribute new swelling to benign fluid retention without considering other causes. Painful unilateral swelling warrants assessment for venous thrombosis. The management of a suspected adverse effect depends on the preparation, indication, and individual risk; involve the prescribing clinician before changing a necessary therapy.
Cancer Therapies
Swelling during cancer treatment has several possible explanations: drug toxicity, venous obstruction or thrombosis, proteinuric kidney injury, cardiac dysfunction, low albumin, or progression of the malignancy. These possibilities have different treatments. Assess the timing relative to each drug, urine protein, kidney function, blood pressure, and cardiopulmonary findings. Coordinate changes with oncology rather than assuming that all treatment-related edema is mild or self-limited.
Selected Agents and Important Distinctions
The strength of evidence differs among medicines. Case reports can identify a signal but do not establish how often an adverse effect occurs or prove one mechanism. Review the product-specific evidence and the patient’s competing diagnoses.
Dopamine Agonists
Pramipexole-associated peripheral edema is documented in a retrospective case series. Swelling improved after withdrawal and recurred on rechallenge in reported patients; diuretics had limited effect. These observations support a possible drug effect but do not determine incidence across all treated populations. Discuss medication changes with the neurologic treatment team. Tan et al.
Psychotropic Medications
Include psychotropic drugs in a structured medication review. Do not assign an incidence, mechanism, or class-wide causal diagnosis from an isolated report. Weigh any proposed substitution against psychiatric stability and relevant withdrawal or interaction risks.
Biologic Therapies
When edema develops during biologic therapy, evaluate timing, infection, cardiac and renal disease, and all concurrent drugs. The name of the cytokine pathway alone does not establish a capillary-leak mechanism or predict response to a diuretic.
Pulmonary Hypertension Therapies
In a patient receiving treatment for pulmonary hypertension, peripheral edema may reflect right-sided heart failure or another comorbidity. Reassess the clinical state before labeling swelling a direct vasodilator adverse effect. Decisions about disease-specific treatment belong with the pulmonary hypertension team.
Anti-VEGF Therapy
Systemic VEGF inhibition can cause glomerular injury, including thrombotic microangiopathy, and associated proteinuria. Edema with new hypertension or proteinuria warrants kidney evaluation. Clinical observations and experimental work support a direct role for impaired glomerular VEGF signaling. Distinguish systemic oncology exposure from ophthalmic use; an anti-VEGF injection used to treat macular edema should not be presented as a common cause of that same condition. Eremina et al.
SGLT2 Inhibitors
SGLT2 inhibitors have demonstrated kidney and cardiovascular benefits in appropriate populations. For example, DAPA-CKD showed benefit with dapagliflozin in selected patients with albuminuric CKD. New peripheral edema should prompt assessment for heart failure, kidney disease, venous disease, and other medications rather than an assumption of a class-wide paradoxical fluid-retention mechanism. Heerspink et al.
Docetaxel
Docetaxel can cause cumulative fluid retention. A randomized trial found that corticosteroid premedication delayed its onset. Follow the oncology regimen’s premedication and monitoring instructions; do not independently omit the steroid because of a general concern about steroid-associated edema. New respiratory symptoms, substantial weight gain, or worsening swelling merit prompt assessment. Piccart et al.
A Practical Assessment
- Identify urgent features and alternative diagnoses before attributing swelling to a drug.
- Reconcile all medicines, start dates, dose changes, and over-the-counter products.
- Determine whether the pattern suggests systemic sodium retention, local capillary pressure, permeability, venous obstruction, or lymphatic dysfunction.
- Use targeted laboratory tests and imaging according to the clinical findings.
- Discuss a supervised dose change or substitution when the medication is a plausible cause.
- Reassess symptoms, weight, kidney function, and electrolytes after the intervention.
Takeaways
A medication may contribute to edema without being its only cause. Treatment works best when it addresses the dominant mechanism. Dose reduction or substitution may be more effective than adding a diuretic, while true systemic congestion requires cause-directed management. Preserve beneficial therapy when possible and make changes with the responsible clinical team.
References
- Largeau B, Cracowski JL, Lengellé C, et al. Drug-induced peripheral oedema: An aetiology-based review. Br J Clin Pharmacol 2021. PubMed 33506982.
- Liang L, Kung JY, Mitchelmore B, et al. Comparative peripheral edema for dihydropyridines calcium channel blockers treatment: A systematic review and network meta-analysis. J Clin Hypertens (Greenwich) 2022. PubMed 35234349.
- Makani H, Bangalore S, Romero J, et al. Effect of renin-angiotensin system blockade on calcium channel blocker-associated peripheral edema. Am J Med 2011. PubMed 21295192.
- Bełtowski J, Rachańczyk J, Włodarczyk M. Thiazolidinedione-induced fluid retention: recent insights into the molecular mechanisms. PPAR Res 2013. PubMed 23577024.
- Largeau B, Bordy R, Pasqualin C, et al. Gabapentinoid-induced peripheral edema and acute heart failure: A translational study combining pharmacovigilance data and in vitro animal experiments. Biomed Pharmacother 2022. PubMed 35303569.
- Sinnathamby ES, Urban BT, Clark RA, et al. Etiology of Drug-Induced Edema: A Review of Dihydropyridine, Thiazolidinedione, and Other Medications Causing Edema. Cureus 2024. PubMed 38435190.
- Tan EK, Ondo W. Clinical characteristics of pramipexole-induced peripheral edema. Arch Neurol 2000. PubMed 10815140.
- Eremina V, Jefferson JA, Kowalewska J, et al. VEGF inhibition and renal thrombotic microangiopathy. N Engl J Med 2008. PubMed 18337603.
- Piccart MJ, Klijn J, Paridaens R, et al. Corticosteroids significantly delay the onset of docetaxel-induced fluid retention: final results of a randomized study of the European Organization for Research and Treatment of Cancer Investigational Drug Branch for Breast Cancer. J Clin Oncol 1997. PubMed 9294478.
- Heerspink HJL, Stefánsson BV, Correa-Rotter R, et al. Dapagliflozin in Patients with Chronic Kidney Disease. N Engl J Med 2020. PubMed 32970396.