Hypokalemia: Cardiac Effects and Clinical Risk
Visual reference
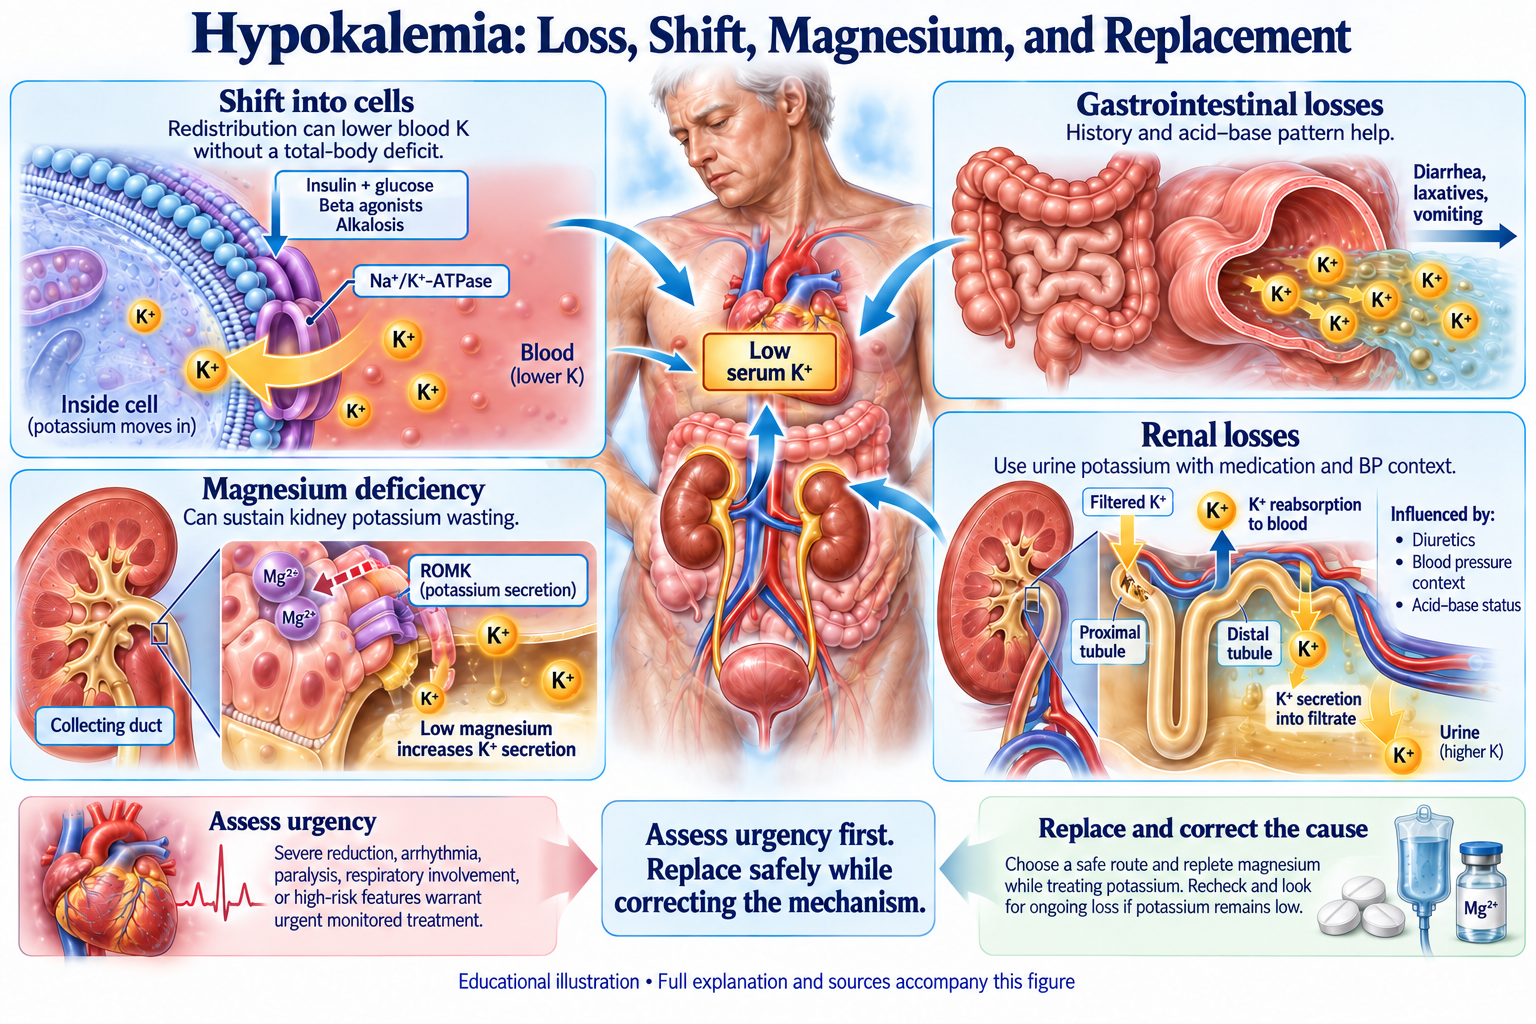
Browse the visual reference library · Download lesson Markdown
Executive Summary
Low serum potassium can impair neuromuscular function and promote dangerous cardiac arrhythmias. Urgency depends on the concentration, rate of change, symptoms, ECG, kidney function, ongoing losses, and the patient's cardiac substrate. A normal ECG does not exclude clinically important hypokalemia. Severe hypokalemia, arrhythmia, marked weakness, or an inability to take oral treatment requires urgent monitored assessment.
Population studies associate low potassium with worse outcomes, especially in heart failure and myocardial infarction. These associations are useful signals of risk; they do not provide a universal mortality percentage for an individual patient or prove that one replacement target improves survival in every setting.
Definition and Classification
Hypokalemia is usually defined as serum potassium below 3.5 mmol/L; for potassium, mmol/L and mEq/L are numerically equivalent. Values around 3.0–3.4 are commonly called mild, 2.5–2.9 moderate, and below 2.5 severe. These labels are guides, not boundaries between safe and dangerous. Symptoms or ECG changes at any concentration can raise urgency. A value of 2.5 or lower is an urgent feature in clinical reviews.
Serum potassium is a concentration in a small extracellular compartment. It is not a direct measurement of total body stores. Redistribution into cells can produce a low value without the same deficit as sustained gastrointestinal or renal loss. Confirm an unexpected result promptly while avoiding delays in treatment when clinical danger is evident. Kim et al.
Identify the Cause
Review vomiting, diarrhea, nasogastric losses, poor intake, loop or thiazide diuretics, insulin, beta agonists, laxatives, and recent medication changes. Multiple mechanisms often coexist. Reduced intake alone is less likely to produce a large deficit unless losses or other vulnerabilities are also present.
Assess magnesium, creatinine, acid–base status, blood pressure, and urine potassium when the cause is uncertain. Urine studies help distinguish renal losses from an appropriate kidney response, but must be interpreted with timing, replacement, diuretic exposure, and urine concentration. Hypertension with renal potassium wasting raises the possibility of mineralocorticoid excess. Hypomagnesemia can sustain renal potassium loss and make potassium replacement less effective.
Why Low Potassium Affects the Heart
Potassium gradients influence membrane voltage, repolarization, and conduction. Low extracellular potassium changes potassium currents and sodium–potassium pump activity. Experimental work links reduced pump activity to abnormal intracellular sodium and calcium handling, afterdepolarizations, and triggered arrhythmia. Ischemia, scar, ventricular dysfunction, and repolarization disorders can lower the threshold for an arrhythmia.
These mechanisms explain biological plausibility; they do not establish a fixed risk multiplier at each potassium value. The mechanistic literature includes cellular and animal experiments as well as human observations. Skogestad et al.
Cardiac Effects and ECG
Possible ECG findings include T-wave flattening or inversion, ST depression, prominent U waves, and apparent prolongation of the QT interval when the T and U waves merge. Severe disturbances can accompany atrial or ventricular ectopy, ventricular tachyarrhythmia, or conduction abnormalities. ECG manifestations vary, and there is no reliably predictable sequence tied to exact serum concentrations.
Obtain an ECG in clinically significant hypokalemia and use continuous monitoring for severe or symptomatic cases, arrhythmia, high-risk cardiac disease, or intravenous replacement requiring monitoring under the local protocol. Treat the patient and the evolving clinical picture rather than relying on a reassuring tracing alone.
Interpreting Mild Hypokalemia
An otherwise stable patient with a mildly low value differs from a patient with ischemia, ventricular dysfunction, digoxin exposure, or a rapidly falling potassium level. Review the trend, ongoing losses, magnesium, medication interactions, and the feasibility of follow-up. Mild hypokalemia should prompt a cause-directed plan rather than a declaration that the concentration is universally safe.
A retrospective emergency-department study found no hospital-mortality advantage associated with replacement in selected patients with potassium 3.0–3.4 mmol/L. It excluded acute coronary syndromes, major arrhythmias, diabetic ketoacidosis, and hyperosmolar states. Its findings therefore cannot justify withholding potassium from those higher-risk groups or establish a causal benefit or lack of benefit of treatment. Wongtanasarasin et al.
Cardiac Patients Need Individualized Targets
Heart failure, recent myocardial infarction, structural heart disease, congenital long-QT syndromes, and QT-prolonging medications can make a low potassium level more consequential. Diuretics may cause continuing losses, while renin–angiotensin system inhibitors and mineralocorticoid receptor antagonists can raise potassium. Kidney function can change during decongestion, altering both replacement needs and the risk of overshoot.
Hypokalemia increases susceptibility to digoxin toxicity. Assess digoxin exposure and clinical toxicity when relevant; do not assume that a drug concentration alone excludes danger. Magnesium depletion and interacting medications deserve attention alongside potassium. No single concentration can be used to rank all patients with HFrEF, HFpEF, ischemia, or inherited arrhythmia syndromes.
Risk Assessment at the Bedside
| Finding | Clinical implication |
|---|---|
| Stable mild reduction, no dangerous symptoms | Confirm the cause, consider oral replacement, address losses, and arrange repeat measurement. |
| Low value with ischemia, digoxin, QT risk, or falling trend | Increase urgency and monitoring; individualize replacement and cardiac evaluation. |
| Potassium 2.5 mmol/L or lower, severe weakness, arrhythmia, or significant ECG changes | Urgent monitored treatment and reassessment; intravenous replacement may be required. |
| AKI, advanced CKD, oliguria, or potassium-raising therapy | Use cautious replacement with frequent reassessment because accumulation and hyperkalemia can occur. |
What Mortality Studies Can Tell Us
Observational studies commonly show a U-shaped relationship between potassium and adverse outcomes. In an acute myocardial infarction cohort, the lowest observed mortality was associated with potassium approximately 3.5 to below 4.5 mmol/L. This was an association, not a randomized comparison of replacement targets. It should not be turned into a universal safe interval or an instruction to lower potassium routinely. Goyal et al.
In heart failure, low potassium often tracks diuretic exposure, neurohormonal activation, comorbidity, and illness severity. A review highlights rising risk below approximately 4.0 mmol/L, especially below 3.5; the treatment plan must also avoid hyperkalemia and preserve beneficial heart-failure therapy when possible. Ferreira et al.
Serial values add information. A registry analysis found that persistent hypokalemia during acute-heart-failure hospitalization was associated with worse subsequent survival. Observational associations remain susceptible to confounding and cannot prove that replacing to a specified number alone prevents death. Caravaca et al.
Replacement and Monitoring
Address the cause as well as the concentration. Reassess the need and dose of potassium-losing medication, correct magnesium deficiency, and treat gastrointestinal losses. Oral potassium is generally preferred when the patient can absorb it, the value is above 2.5 mmol/L, and no urgent symptoms or ECG findings require intravenous therapy. Potassium chloride is commonly appropriate, particularly when chloride depletion or metabolic alkalosis accompanies the deficit.
Intravenous potassium requires an infusion pump and a monitored protocol appropriate to the access, concentration, infusion rate, cardiac risk, and kidney function. Never administer potassium as an intravenous push. Severe or unstable presentations warrant repeated potassium measurements during correction and continuous cardiac monitoring when indicated. Use local pharmacy and institutional protocols for dosing and infusion limits.
Do not estimate the entire required dose from one serum value or assume that a fixed amount produces the same concentration change in everyone. Ongoing losses, cell shifts, magnesium deficiency, body size, and excretion change the response. Avoid stacking replacement orders without checking what has already been administered. After stabilization, provide a clear plan for medication changes, repeat testing, and escalation for symptoms. Kim et al.
Losses still running? When urine or GI losses continue, standard dosing may never catch up. See Correcting Severe Hypokalemia When Losses Continue for how to measure ongoing losses, what the FDA labels say about the 40 mEq oral dose ceiling, and the evidence on split immediate- and extended-release dosing.
Practical Takeaways
Recognize urgent symptoms and ECG findings, identify the mechanism, and account for the patient's cardiac and renal context. Correct hypomagnesemia and ongoing losses. Prefer oral treatment when appropriate and use monitored protocols when intravenous replacement is needed. Follow the trend and avoid overcorrection. Clinical risk is not captured by a single potassium threshold or a generic mortality chart.
References
- Kim MJ, Valerio C, Knobloch GK. Potassium Disorders: Hypokalemia and Hyperkalemia. Am Fam Physician 2023. PubMed 36689973.
- Skogestad J, Aronsen JM. Hypokalemia-Induced Arrhythmias and Heart Failure: New Insights and Implications for Therapy. Front Physiol 2018. PubMed 30464746.
- Ferreira JP, Butler J, Rossignol P, et al. Abnormalities of Potassium in Heart Failure: JACC State-of-the-Art Review. J Am Coll Cardiol 2020. PubMed 32498812.
- Goyal A, Spertus JA, Gosch K, et al. Serum potassium levels and mortality in acute myocardial infarction. JAMA 2012. PubMed 22235086.
- Caravaca Perez P, González-Juanatey JR, Nuche J, et al. Serum potassium dynamics during acute heart failure hospitalization. Clin Res Cardiol 2022. PubMed 33070219.
- Wongtanasarasin W, Meelarp N. Replacing Potassium in the Emergency Department May Not Decrease the Hospital Mortality in Mild Hypokalemia: A Propensity Score Matching Analysis. Medicina (Kaunas) 2023. PubMed 38003961.