Visual reference
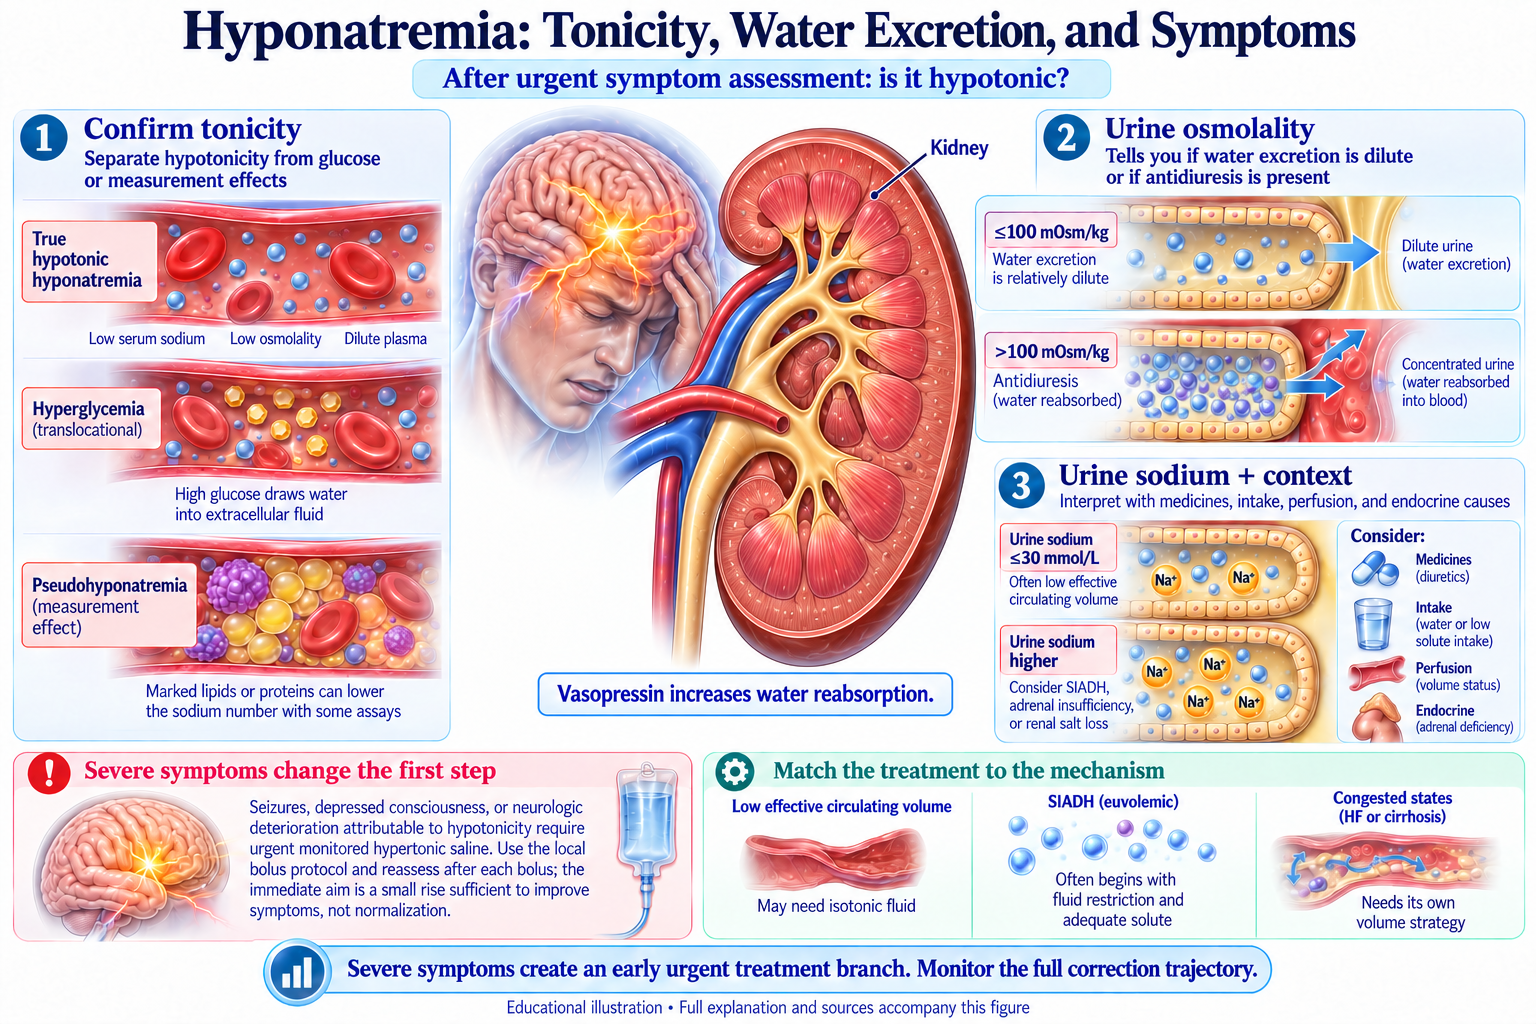
Browse the visual reference library · Download lesson Markdown
Preface: Understanding the Complexity of Hyponatremia
Hyponatremia represents one of the most challenging electrolyte disorders encountered in clinical practice, demanding a sophisticated understanding that extends far beyond simple sodium replacement. Successful hyponatremia management requires mastery of multiple interconnected concepts: the delicate balance between water and sodium homeostasis, the recognition of distinct pathophysiological mechanisms, the appreciation of correction rate optimization, and the integration of emerging therapeutic modalities.
Hyponatremia affects approximately 15–30% of hospitalized patients and serves as an independent predictor of poor outcomes across diverse medical conditions, from heart failure to neurological disorders. The evolution of our understanding, particularly with the landmark 2024 treatment standards, has fundamentally reshaped therapeutic approaches while reinforcing the paramount importance of preventing osmotic demyelination syndrome.
Chapter 1: Foundational Physiology — The Dual Hormonal Control System
Two Separate But Interconnected Systems
Your body uses two distinct hormonal systems to control fluid balance. Think of them as two different thermostats: one controls water balance (ADH), the other controls sodium balance (aldosterone). They work independently but can influence each other.
The ADH (Antidiuretic Hormone) System: The Water Controller
ADH (vasopressin) is released from the posterior pituitary in response to increased plasma osmolality or decreased effective blood volume. It acts on collecting ducts through aquaporin-2 water channels. When ADH is high, the kidney retains water, concentrating urine and diluting blood. When ADH is low, the kidney excretes dilute urine.
Under normal circumstances, when blood osmolality rises above 280–290 mOsm/kg, osmoreceptor cells in the hypothalamus trigger ADH release. The kidney can concentrate urine to osmolalities exceeding 1000 mOsm/kg.
The Aldosterone System: The Sodium Controller
The RAAS responds primarily to changes in effective blood volume. Aldosterone acts on the distal tubule and collecting duct to increase sodium reabsorption and potassium excretion.
Water Homeostasis: The Osmotic Regulation System
Plasma osmolality is maintained within the narrow range of 275–290 mOsm/kg. Specialized osmoreceptor cells in the OVLT and subfornical organ detect changes as small as 1–2 mOsm/kg. These are exquisitely sensitive to NaCl but less responsive to urea and glucose, explaining why rapid glucose changes can create translocational hyponatremia without triggering ADH suppression.
Thirst is activated at slightly higher osmolality thresholds than ADH release (~295 vs ~285 mOsm/kg). In the absence of ADH, urine osmolality can be as low as 50–100 mOsm/kg. With maximal ADH, urine can reach ~1200 mOsm/kg.
Chapter 2: Classification and Diagnostic Framework
Classification by Serum Osmolality
| Type | Osmolality | Description |
|---|---|---|
| Hypotonic | <275 mOsm/kg | True hyponatremia — excess water relative to sodium. Vast majority of clinically significant cases. |
| Isotonic (Pseudo) | 275–290 mOsm/kg | Laboratory artifact from extreme hyperlipidemia or hyperproteinemia. Rare with modern ion-selective electrodes. |
| Hypertonic | >290 mOsm/kg | Osmotically active substances (e.g., hyperglycemia) draw water into ECF. Each 100 mg/dL glucose rise above normal decreases Na by ~1.6–2.4 mEq/L. |
Classification by Volume Status
| Category | Total Body Na | Total Body Water | Common Causes | Clinical Findings |
|---|---|---|---|---|
| Hypovolemic | Decreased | Decreased (Na loss > H2O loss) | GI losses, diuretics, salt-wasting nephropathy, third-spacing | Orthostatic hypotension, tachycardia, dry mucous membranes |
| Euvolemic | Normal | Increased | SIADH, hypothyroidism, adrenal insufficiency | Clinically euvolemic, subtle fluid retention |
| Hypervolemic | Increased | Increased (H2O > Na) | Heart failure, cirrhosis, nephrotic syndrome | Edema, ascites, elevated JVP |
Classification by Severity
| Severity | Sodium (mEq/L) | Typical Symptoms |
|---|---|---|
| Mild | 130–134 | May be asymptomatic; subtle cognitive impairment, increased fall risk in elderly |
| Moderate | 125–129 | Headache, nausea, confusion, muscle weakness |
| Severe | <125 | Seizures, coma, respiratory arrest — medical emergency |
Physical Examination: Assessing Volume Status
Physical examination focuses on volume status assessment, which reflects aldosterone system activity (not ADH). Orthostatic vital signs: drop in SBP >20 mmHg or increase in HR >20 bpm suggests volume depletion. Assess mucous membranes, skin turgor, JVP, and peripheral edema.
Medication History: The Detective Work
- Thiazide diuretics: Most common medication cause. Impaired urinary dilution + volume depletion stimulating ADH. Typically develops within days to weeks but can occur after years of stable use.
- SSRIs: Enhanced serotonergic neurotransmission stimulates ADH secretion. Classic SIADH pattern. Risk highest in elderly, women, low body weight. Usually within first month.
- Other: Antipsychotics (haloperidol, fluphenazine), anticonvulsants (carbamazepine, oxcarbazepine), PPIs, antineoplastics.
Chapter 3: Laboratory Evaluation — Solving the Diagnostic Puzzle
Essential Serum Measurements
- Comprehensive metabolic panel (Na, K, Cl, HCO3, BUN, Cr, glucose)
- Serum osmolality (measured > calculated). Calculated: 2(Na) + glucose/18 + BUN/2.8
- Osmolal gap (measured − calculated; normal <10 mOsm/kg) — elevated suggests toxic alcohols
- TSH, cortisol as clinically indicated
Serum Uric Acid: The Diagnostic Helper
In SIADH, persistent volume expansion leads to increased uric acid clearance → hypouricemia (typically <4 mg/dL). Sensitivity 70–80%, specificity 80–90% for SIADH diagnosis. Approximately 5–7% of patients initially diagnosed with “idiopathic SIADH” may have underlying monoclonal gammopathies.
Urine Osmolality: The Master Parameter
| Urine Osmolality | Interpretation | Likely Diagnosis |
|---|---|---|
| <100 mOsm/kg | Maximally dilute — ADH appropriately suppressed | Primary polydipsia, beer potomania, tea-and-toast syndrome |
| 100–300 mOsm/kg | “Mixed picture” — partial ADH effect, reset osmostat, transitional states | Requires clinical correlation |
| >300 mOsm/kg | Concentrated — significant ADH effect | SIADH if euvolemic; appropriate ADH if hypo/hypervolemic |
| >500 mOsm/kg | Highly concentrated | Strongly suggests SIADH when coupled with euvolemia |
Urine Sodium: Understanding Aldosterone Activity
| Urine Na (mEq/L) | Interpretation |
|---|---|
| <20 | Appropriate sodium conservation: volume depletion, decreased effective arterial blood volume (HF, cirrhosis) |
| >20–30 | Normal volume status (SIADH), renal sodium wasting, adrenal insufficiency, active diuretic effect |
The Paradoxical Effect of IV Fluids
When urine osmolality exceeds infused fluid osmolality, the kidney excretes administered solute in less water than was infused — retaining free water and worsening hyponatremia.
Isotonic saline may fail to correct or may worsen hyponatremia in SIAD. Assess urine sodium plus potassium, water handling, symptoms, and the underlying cause. Total urine osmolality alone does not define an exact retained-water volume or an indication for hypertonic saline.
Chapter 4: Treatment Principles — Correction Rate Science
Correction Goals and Safety Limits
Severe neurological symptoms require prompt, monitored treatment. Initial symptom relief and the maximum permissible daily correction are different concepts. For chronic hyponatremia or an uncertain duration, choose a cautious goal and correction limit according to current guidance and individual osmotic-demyelination risk. Very low sodium, alcohol use disorder, malnutrition, advanced liver disease, and hypokalemia increase concern.
Observational associations between correction speed and mortality do not establish a universal causal optimum. There is no validated table assigning an exact ODS probability to every correction-rate band. Monitor sodium and urine output closely, especially when reversal of the cause triggers water diuresis; use a specialist relowering strategy when indicated. Treatment Guidelines for Hyponatremia: Stay the Course.
Fluid Restriction in SIAD
Fluid restriction can be appropriate in chronic SIAD, but response varies. Urine electrolyte composition, urine volume, solute intake, and adherence matter. The EFFUSE-FLUID trial studied added furosemide with or without oral sodium chloride; it does not establish a universal daily correction or outpatient adherence percentage. Reassess ineffective treatment and the diagnosis.
Chapter 5: Advanced Treatment Modalities
Hypertonic Saline: Bolus and Infusion Strategies
SALSA randomized 178 adults with symptomatic hyponatremia to rapid intermittent bolus or slow continuous infusion. It did not demonstrate a statistically significant difference in its primary overcorrection outcome. Secondary findings supported advantages of bolus treatment for some early goals, but neither approach removes the need for frequent reassessment. SALSA trial.
Use an established institutional hypertonic-saline protocol appropriate to symptom severity, weight, comorbidities, and correction risk. Reassess symptoms and sodium after treatment and account for spontaneous water diuresis. A review article or trial does not supply a universally safe automatic sequence.
Oral Urea: From Alternative to Evidence-Based Standard
Oral urea has been elevated to recognized second-line treatment for chronic SIADH. It promotes free water excretion without directly affecting sodium balance. Freely crosses cell membranes, minimizing risk of cellular dehydration.
Oral urea is an option for selected patients with persistent SIAD. Evidence includes heterogeneous and largely nonrandomized studies; dose, tolerability, monitoring, and local availability should be individualized.
SGLT2 Inhibitors: Expanding Therapeutic Horizons
The Refardt 2020 RCT (PMID 32019783) demonstrated empagliflozin 25 mg/day significantly increases sodium in patients with SIAD. Median sodium increase of 10 mmol/L with empagliflozin vs 7 mmol/L with placebo at 4 days when added to fluid restriction (n=88, p=0.04). Particularly valuable when baseline Na <125.
The dDAVP Clamp Technique: Precision Control
Administering synthetic ADH (desmopressin) maintains consistent antidiuresis while controlling sodium correction through calculated fluid administration. Prevents unpredictable water diuresis that can cause dangerous rapid correction.
Dosing: Standard-risk: 1–2 mcg IV/SC. High-risk: 2–4 mcg. Highest-risk (Na <115 + multiple risk factors): up to 6 mcg. Shift toward prophylactic use at treatment initiation rather than reactive administration.
Key indications: Thiazide-induced hyponatremia (volume repletion triggers rapid diuresis), primary polydipsia, beer potomania, recovery phase SIADH.
Chapter 6: Emerging Therapies and Novel Approaches
Protein Supplementation and the Urea Connection
Dietary protein metabolism yields approximately 0.35 g urea per gram of protein. This enables calculation of protein requirements for therapeutic urea equivalence:
| Target Urea Dose | Required Protein | Clinical Context |
|---|---|---|
| 15 g (starting) | ~43 g additional protein/day | Adjunct to lower-dose direct urea |
| 30 g (maintenance) | ~86 g additional protein/day | Moderate hyponatremia |
| 45 g (higher range) | ~129 g additional protein/day | Often impractical as sole approach |
| 60 g (maximum) | ~171 g additional protein/day | Requires direct urea supplementation |
| Product | Protein/Serving | Fluid Volume | Cost (40g protein) | Best For |
|---|---|---|---|---|
| Whey protein isolate (powder) | 25–30 g | Low (controllable) | $1.33–2.33 | Optimal choice: minimal fluid, highest density, lowest cost |
| Pea/Plant protein (powder) | 20–25 g | Low (controllable) | $2.00–3.20 | Lactose intolerance, vegan |
| Casein protein (powder) | 24–28 g | Low (controllable) | $2.25–3.50 | Sustained amino acid release |
| Core Power Elite (RTD) | 42 g | High (414 mL) | $3.50–4.50 | Caution: significant fluid volume counterproductive in hyponatremia |
Combined Saline and Furosemide Therapy
Saline provides sodium load while furosemide promotes electrolyte-free water excretion by interfering with the concentrating mechanism. Prevents volume overload from saline alone. Particularly valuable in hypervolemic hyponatremia (HF, cirrhosis) and SIADH with high urine osmolality.
Advanced Overcorrection Risk Factors
- Volume repletion: Restoring volume in hypovolemic hyponatremia suppresses ADH → sudden water diuresis (“auto-correction”)
- SIADH resolution: When underlying cause resolves (e.g., pneumonia recovery, medication discontinuation)
- Tea-and-toast / beer potomania: Resumption of normal solute intake restores free water excretion capacity
- Concurrent K+ repletion: Each 1 mEq/L K+ rise can raise Na by 0.5–1 mEq/L (transcellular shift)
- Hyperglycemia correction: Glucose normalization shifts water intracellularly, concentrating Na
Chapter 7: Special Populations and Complex Scenarios
Liver Disease: Navigating Exceptional Risk
Cirrhotic patients develop hyponatremia through multiple mechanisms: reduced effective arterial blood volume despite total body sodium/water excess, portal hypertension, decreased albumin synthesis. Hepatorenal syndrome represents the extreme.
Thiazide Diuretics: The Complex Pattern
Affects approximately 14–30% of patients on chronic therapy. Mechanism: impaired urinary dilution + mild volume depletion stimulating ADH + direct enhancement of ADH collecting duct effects. Risk factors: elderly, female, low body weight, concurrent medications.
High overcorrection risk after thiazide discontinuation as volume normalizes. Prophylactic dDAVP clamp is often warranted.
The Furst Ratio: Contemporary Understanding
(Urine Na + Urine K) / Serum Na. Developed to predict fluid restriction success, but recent validation reveals limitations:
- Tzoulis et al.: 26% of SIADH patients had ratios >1.0; 60% had at least one poor-response predictor
- EFFUSE-FLUID trial: Only 25% of patients with ratios >1.0 achieved adequate improvement with fluid restriction; 61% with favorable ratios succeeded
Contemporary predictive models: baseline fluid intake (35% weighting) > Furst ratio (25%) > urine osmolality (20%) > 24h urine volume (15%) > compliance factors (5%).
Cancer-Associated Hyponatremia
Multiple mechanisms: ectopic ADH production (lung cancers, CNS tumors), chemotherapy effects (platinum compounds, cyclophosphamide, vincristine), concurrent medications, nutritional deficiency. Urea therapy particularly valuable for chronic SIADH in cancer patients (minimal monitoring, facilitates outpatient management).
Chapter 8: Quality Improvement and System-Based Care
Institutional Protocol Development
- Incorporate 2024 treatment standards: RIB therapy for severe symptoms, systematic correction rate management
- Risk stratification algorithms for identifying high-risk patients requiring enhanced monitoring
- EMR-integrated automated alerts for dangerous correction rates and missed monitoring intervals
Monitoring Standards
| Risk Level | Monitoring Frequency | Correction Target |
|---|---|---|
| High-risk | Na every 2–4 hours | 4–6 mEq/L/24h; proactive dDAVP clamp |
| Standard-risk | Na every 4–6 hours | 6–8 mEq/L/24h |
| During RIB therapy | Na every 2 hours | Symptom resolution OR 4–6 mEq/L increase |
| Overcorrection concern | Na every 1–2 hours | Initiate rescue protocol immediately |
Cost-Effectiveness Comparisons
- Urea: $75–150/month, minimal monitoring — most cost-effective for chronic SIADH
- Vaptans: Thousands of dollars/month, intensive monitoring
- SGLT2i: Standard diabetes pricing, dual benefit in HF patients
- Protein supplementation: ~$30–60/month, provides nutritional co-benefit
Chapter 9: Future Directions and Research Priorities
- Next-generation V2 receptor antagonists: Self-limiting properties to reduce overcorrection risk; combination molecules with controlled sodium delivery
- Continuous sodium monitoring devices: Analogous to CGMs for diabetes — real-time correction rate data
- AI/ML applications: Predicting rapid spontaneous correction, optimizing therapy selection
- Precision medicine: Genetic testing for ADH sensitivity variants, biomarker-guided therapy selection
- Mild hyponatremia (130–134 mEq/L): Clarifying when intervention is warranted — fall prevention, cognitive improvement studies
- Combination therapy research: Urea + SGLT2i, protein supplementation + urea optimization
Chapter 10: Synthesis — Clinical Decision-Making Framework
Integrated Approach for High-Risk Patients (Target: 4–6 mEq/L/24h)
Combine protein supplementation (40–60 g additional protein = 14–21 g urea equivalent) with lower-dose direct urea (15–20 g) for total therapeutic urea of 30–40 g. Addresses nutritional deficits while providing gentle, physiologic correction.
Standard-Risk Patients (Target: 6–8 mEq/L/24h)
Direct urea therapy OR high-dose protein supplementation alone, depending on patient preference, baseline nutrition, and practical considerations.
Acute Symptomatic Patients
RIB therapy with 3% hypertonic saline → transition to controlled correction. Integrate dDAVP clamp for high-risk patients. Monitor Na every 2 hours during active treatment.
Key References
- Baek SH, Jo YH, Ahn S, et al. Intermittent versus continuous hypertonic saline for symptomatic hyponatremia: the SALSA randomized clinical trial. JAMA Intern Med. 2021;181(1):81-92. PMID: 33104189
- George JC, Zafar W, Bucaloiu ID, Chang AR. Risk factors and outcomes of rapid correction of severe hyponatremia. Clin J Am Soc Nephrol. 2018;13(7):984-992. PMID: 29871886
- Refardt J, Imber C, Nobbenhuis R, et al. Treatment Effect of the SGLT2 Inhibitor Empagliflozin on Chronic Syndrome of Inappropriate Antidiuresis: Results of a Randomized, Double-Blind, Placebo-Controlled, Crossover Trial. J Am Soc Nephrol. 2023;34(2):322-332. DOI | PubMed
- Spasovski G, Vanholder R, Allolio B, et al. Clinical practice guideline on diagnosis and treatment of hyponatraemia. Nephrol Dial Transplant. 2014;29(suppl 2):i1-i39. PMID: 24569496
- Sterns RH. Disorders of plasma sodium. N Engl J Med. 2015;372(1):55-65. PMID: 25551526
- Spasovski G. Hyponatraemia-treatment standard 2024. Nephrol Dial Transplant. 2024;39(10):1583-1592. DOI | PubMed
- Verbalis JG, Goldsmith SR, Greenberg A, et al. Diagnosis, evaluation, and treatment of hyponatremia: expert panel recommendations. Am J Med. 2013;126(10 Suppl 1):S1-42. PMID: 24074529
Also on this topic
The same subject at other levels of depth.
- Student handout: Hyponatremia: Student Handout