Gastrointestinal Sodium Loss and Protein-Losing Enteropathy
Visual reference
Browse the visual reference library · Download lesson Markdown
Separate Sodium Loss from Protein Loss
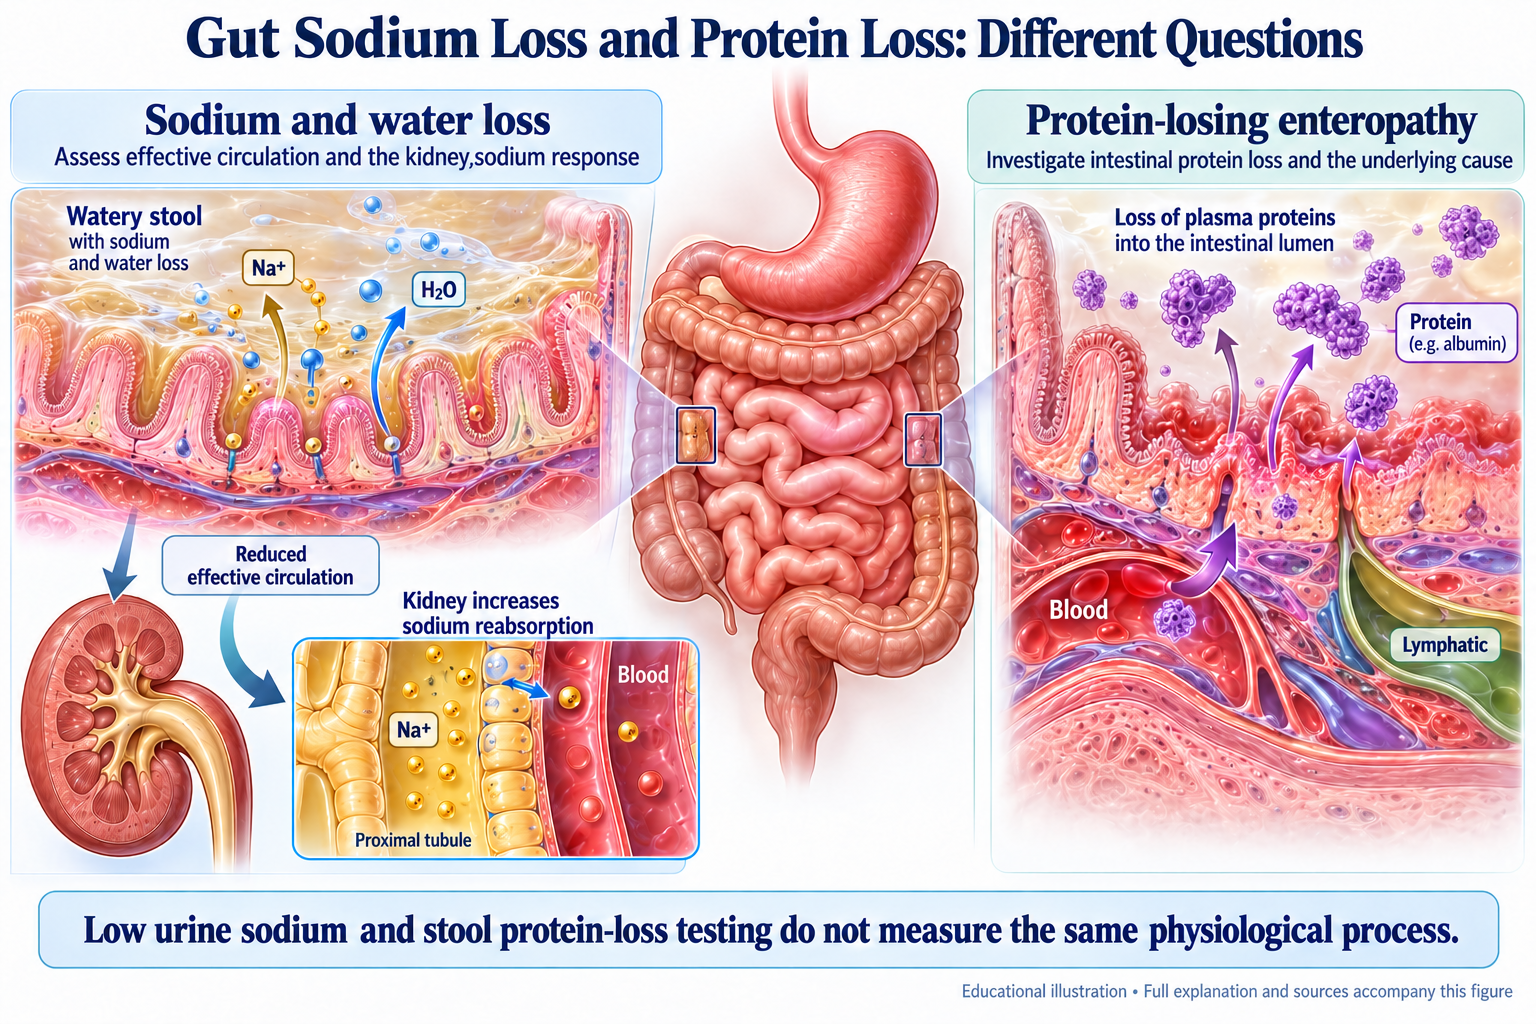
Gastrointestinal sodium loss and protein-losing enteropathy are different physiological problems. Severe diarrhea can cause sodium and water depletion. Protein-losing enteropathy means excessive loss of plasma proteins into the gastrointestinal tract and can cause hypoalbuminemia and edema. They may coexist, but neither diagnosis establishes the other. Avoid using the abbreviation SLE for a single presumed syndrome because it is easily confused with systemic lupus erythematosus.
The initial task is to identify what is being lost, how quickly, and why. Serum sodium reflects water relative to exchangeable body sodium and potassium, not simply total-body sodium content. A patient with gastrointestinal depletion can have low, normal, or high serum sodium depending on water intake, replacement fluid, and kidney responses. PubMed 30626576
Presentation and Mechanisms
Assess diarrhea or ostomy output, weight change, thirst, postural symptoms, perfusion, urine output, edema, and respiratory findings. Gastrointestinal losses may lead to AKI, potassium abnormalities, and acid-base disturbances. The physical examination alone can be misleading when low albumin, heart disease, kidney disease, and active losses coexist.
Protein loss can arise from mucosal erosion, increased permeability without erosion, or abnormal lymphatic pressure and drainage. These categories help organize a differential but are not a quantitative classification of sodium loss. Relevant disorders include inflammatory bowel disease, celiac disease, intestinal lymphangiectasia, infection, and selected cardiac or systemic conditions. PubMed 28761367
Look for the Underlying Disorder
Medication-related diarrhea, infection, inflammation, malabsorption, and short bowel or high-output stoma physiology require different investigations and treatment. Congenital sodium diarrhea is a rare early-life intestinal transport disorder; SLC9A3-related disease is one described mechanism. Its findings should not become a universal diagnostic cutoff for adult diarrhea. PubMed 31276831
In hypoalbuminemia, assess urinary protein loss, liver disease, nutrition, inflammation, and dilution as well as gastrointestinal protein loss. PLE is a syndrome with many causes, and the workup should be guided by the clinical pattern. Pediatric disease has additional congenital and cardiac considerations. PubMed 20571826
Initial Evaluation
Check serum electrolytes, kidney function, glucose, albumin, and acid-base status according to severity. Review medications, fluid intake, recent treatment, nutritional history, and output measurements. Urine osmolality and sodium can clarify the kidney response, but diuretics, CKD, recent saline, adrenal disease, and timing affect interpretation. A low urine sodium may support renal sodium conservation; it does not prove a specific intestinal diagnosis. PubMed 30626576
Stool testing should answer a defined question: infection, inflammation, malabsorption, electrolyte composition, or protein loss. Do not order an undirected panel or perform invasive studies solely because the serum sodium is low. Select imaging, endoscopy, and biopsy when the suspected disease warrants them. PubMed 31619925
Fecal Sodium and Alpha-1-Antitrypsin Answer Different Questions
Fecal sodium and potassium help characterize selected diarrheal disorders and can support assessment of electrolyte losses. Concentration alone is not daily loss: output volume and collection quality matter. There is no single stool-sodium threshold that diagnoses all gastrointestinal salt loss.
Fecal alpha-1-antitrypsin testing evaluates gastrointestinal protein loss. Clearance uses stool output, stool concentration, and serum concentration; follow laboratory collection and reference guidance. Diarrhea and other clinical factors affect interpretation. Alpha-1-antitrypsin has not replaced fecal sodium testing as though both measured the same process. PubMed 3919562; PubMed 31619925
When PLE is demonstrated, localization and causal investigation may require endoscopy, appropriate imaging, or specialist lymphatic assessment. A positive protein-loss test does not identify the underlying disease or independently prescribe treatment. PubMed 28761367
Hyponatremia: Keep the Differential Open
Confirm hypotonic hyponatremia and assess symptoms and time course. Consider medications, adrenal insufficiency, impaired water excretion, low solute intake, SIAD, and renal salt loss as well as gastrointestinal depletion. Cerebral/renal salt wasting is a separate and sometimes difficult differential in neurological illness.
Fractional urate excretion has been proposed as one component of distinguishing SIAD from cerebral/renal salt wasting. A pediatric review proposes an algorithm for that setting; it does not validate fractional urate excretion as a diagnostic test for intestinal protein or sodium loss. Interpret such proposals within their population and limitations. PubMed 34468821
Replace Losses and Monitor the Response
Stabilize patients with hemodynamic compromise or severe neurological symptoms promptly. Fluid composition and route should reflect perfusion, symptoms, ongoing losses, kidney function, and ability to take oral therapy. Oral rehydration can be appropriate in selected diarrheal illness; substantial depletion or inability to drink may require IV fluid and monitored care.
Neither fixed high daily salt intake nor routine hypertonic saline is a general treatment for PLE. In hypotonic hyponatremia, use an established monitored protocol appropriate to symptom severity and risk of osmotic demyelination. Volume restoration can trigger water diuresis and unexpectedly rapid sodium correction. Reassess serum electrolytes, urine output, clinical volume status, and ongoing losses rather than relying on a one-time calculation.
Address potassium, magnesium, nutrition, and the cause of diarrhea. Diet and protein prescriptions must account for the specific disease and coexisting CKD, heart failure, or frailty. The goal is adequate replacement and recovery without inducing congestion or another electrolyte problem.
Cause-Specific PLE Therapy
Treat the mechanism: examples include dietary treatment for celiac disease, control of intestinal inflammation, infection treatment, or assessment of Fontan and lymphatic physiology. Low-fat strategies with medium-chain triglycerides may be used in selected lymphatic disorders. Albumin infusion, steroids, octreotide, or lymphatic interventions are specialist options in selected settings, not interchangeable treatments for every patient with low albumin. PubMed 20571826
For CD55-deficient PLE (CHAPLE disease), the FDA approved pozelimab in August 2023 for patients at least one year old. That indication does not extend to nonspecific diarrhea or all PLE. Complement inhibition carries serious infection risks and requires product-specific prevention and monitoring. FDA approval information.
Checkpoint Inhibitor Enterocolitis
New diarrhea during or after checkpoint-inhibitor therapy needs assessment for infection, treatment toxicity, and other causes. Severity and complications determine treatment setting and oncology/gastroenterology involvement. Corticosteroids and biologic therapy are used in selected immune-mediated cases according to current guidance. Do not equate all treatment-associated diarrhea with immune colitis, or apply investigational rescue treatments routinely. Monitor volume, electrolytes, and kidney function throughout. PubMed 35917654
Clinical Takeaways
- Document sodium/water loss separately from protein loss.
- Use stool electrolytes and alpha-1-antitrypsin for their distinct purposes.
- Interpret urine chemistry with medications, kidney function, and recent treatment.
- Replace measured and estimated losses with repeated reassessment.
- Treat the underlying intestinal, cardiac, lymphatic, or immune disorder.
References
- Palmer BF, Clegg DJ. The Use of Selected Urine Chemistries in the Diagnosis of Kidney Disorders. Clin J Am Soc Nephrol 2019. PubMed 30626576.
- Levitt DG, Levitt MD. Protein losing enteropathy: comprehensive review of the mechanistic association with clinical and subclinical disease states. Clin Exp Gastroenterol 2017. PubMed 28761367.
- Dimitrov G, Bamberger S, Navard C, et al. Congenital Sodium Diarrhea by mutation of the SLC9A3 gene. Eur J Med Genet 2019. PubMed 31276831.
- Braamskamp MJ, Dolman KM, Tabbers MM. Clinical practice. Protein-losing enteropathy in children. Eur J Pediatr 2010. PubMed 20571826.
- Kasırga E. The importance of stool tests in diagnosis and follow-up of gastrointestinal disorders in children. Turk Pediatri Ars 2019. PubMed 31619925.
- Buffone GJ, Shulman RJ. Characterization and evaluation of immunochemical methods for the measurement of fecal alpha 1-antitrypsin. Am J Clin Pathol 1985. PubMed 3919562.
- Bardanzellu F, Marcialis MA, Frassetto R, et al. Differential diagnosis between syndrome of inappropriate antidiuretic hormone secretion and cerebral/renal salt wasting syndrome in children over 1 year: proposal for a simple algorithm. Pediatr Nephrol 2022. PubMed 34468821.
- Nielsen DL, Juhl CB, Chen IM, et al. Immune checkpoint Inhibitor-Induced diarrhea and Colitis: Incidence and Management. A systematic review and Meta-analysis. Cancer Treat Rev 2022. PubMed 35917654.