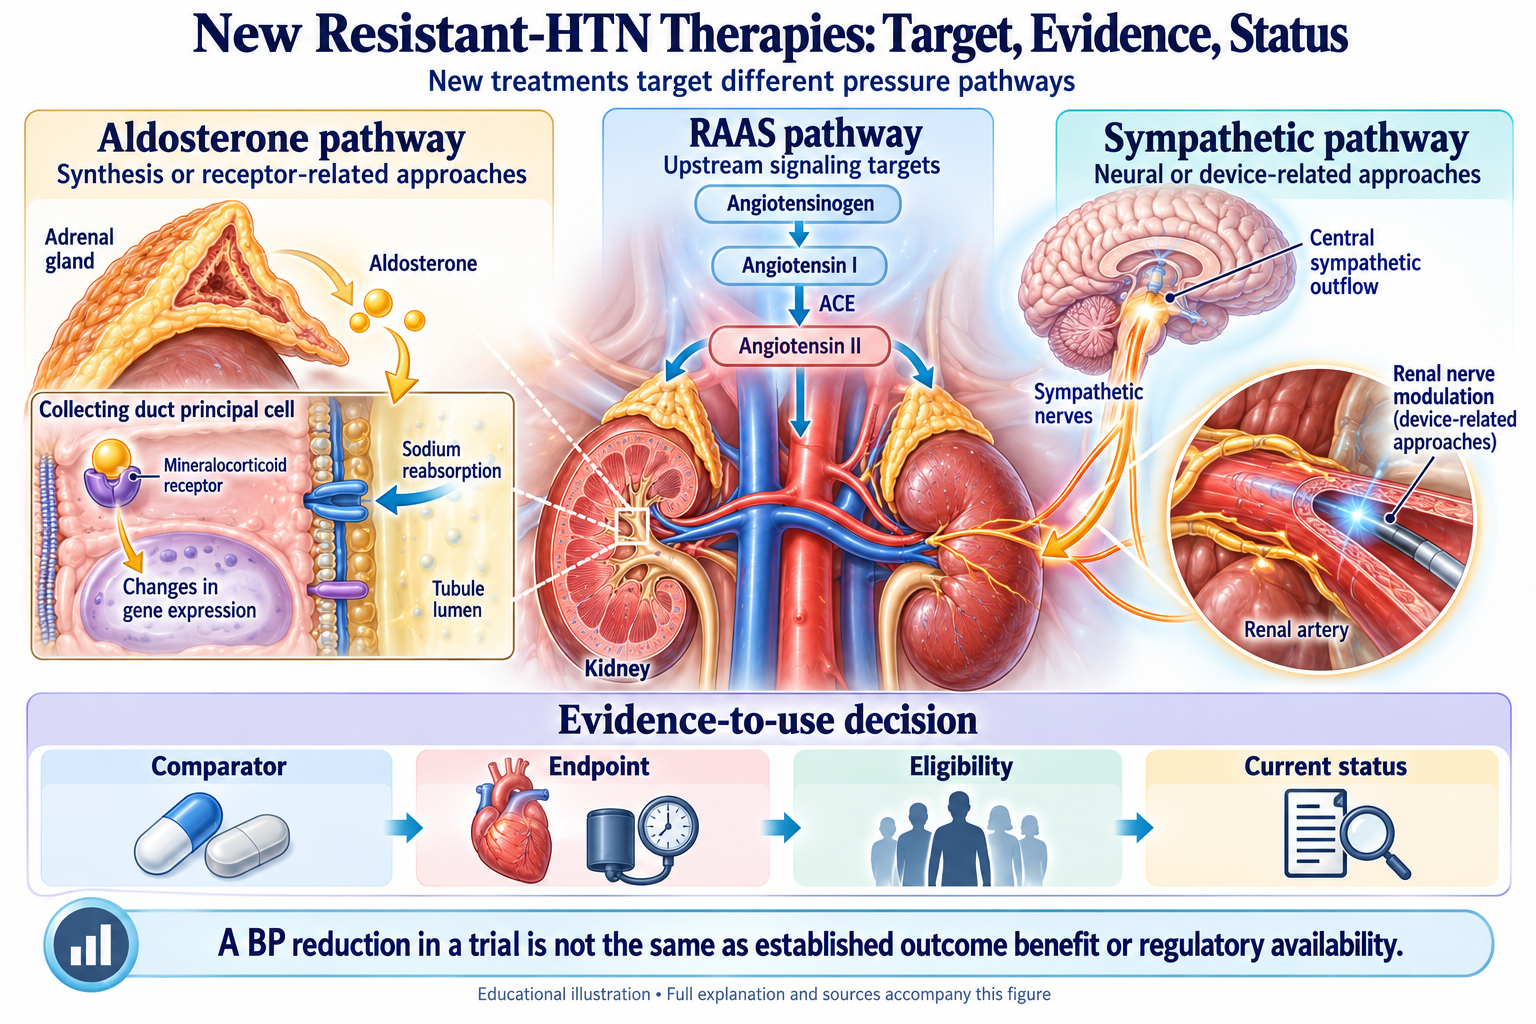
1. Mechanism of Action
1.1 The Endothelin Pathway
Endothelin-1 (ET-1) is the most potent endogenous vasoconstrictor in human biology — roughly 100-fold more potent than norepinephrine on a molar basis. Vascular endothelium synthesizes ET-1 in response to shear stress, hypoxia, angiotensin II, vasopressin, and inflammatory cytokines. Its actions are mediated by two G-protein-coupled receptors:
- ETA receptor: Vascular smooth muscle. Mediates vasoconstriction, proliferation, fibrosis, aldosterone release, and sympathetic activation. The “bad guy” of the pathway in chronic HTN and CKD pathophysiology.
- ETB receptor: Endothelial cells (NO and prostacyclin release — vasodilation), renal tubules (natriuresis, water excretion), pulmonary clearance of circulating ET-1. Largely counter-regulatory — the “good guy” in normal physiology.
Selective ETA blockade (atrasentan, ambrisentan) produces strong vasodilation and antifibrotic effects but leaves ETB-mediated natriuresis intact. Counterintuitively, selective ETA blockers also cause significant fluid retention because ETA blockade increases ET-1 levels, which then over-activate unblocked ETB receptors in distal nephron, paradoxically driving sodium retention. Dual ETA/ETB blockade (bosentan, macitentan, aprocitentan) blocks both receptors — losing some of the natriuretic ETB effect — but reduces the fluid retention magnitude in some studies. The fluid retention question is not “does dual blockade fix it” but “does dual blockade reduce it enough to be clinically tolerable.”
1.2 Aprocitentan Specifics
Aprocitentan is the active metabolite of macitentan (the pulmonary arterial hypertension drug). Idorsia recognized that macitentan’s metabolite had the right pharmacokinetics for once-daily oral systemic HTN dosing:
| Parameter |
Value |
| Receptor selectivity |
Dual ETA + ETB antagonist (modest preference for ETA, ratio approximately 16:1) |
| Half-life |
Approximately 41 hours (long — supports steady-state once-daily dosing) |
| Time to steady state |
8 days |
| Bioavailability |
Oral, not affected by food |
| Metabolism |
Non-CYP, no major drug interactions |
| Renal dose adjustment |
None required (eGFR ≥15) |
| Hepatic dose adjustment |
Avoid in moderate-to-severe impairment |
The non-CYP metabolism is a significant advantage in nephrology populations who are already on multiple drugs. No interaction with statins, no interaction with calcineurin inhibitors, no interaction with the dihydropyridines or thiazides used as background therapy.
1.3 Why Endothelin Antagonism Took 20 Years to Reach HTN Approval
Bosentan (the first dual ERA, approved for PAH in 2001) was tried in HTN and failed on hepatotoxicity. Darusentan (selective ETA) reached Phase 3 in resistant HTN — DORADO and DORADO-AC — and missed primary endpoints with significant edema. Atrasentan in DKD nearly killed the program when SONAR was stopped early for HF events. The lesson the field learned: dose matters, patient selection matters, and the fluid retention signal is unforgiving in HF-prone populations.
Aprocitentan’s case rests on three engineering choices: dose-titrated low (12.5 mg start), dual blockade to preserve some natriuretic effect, and patient selection that explicitly excluded HF (NYHA III-IV) in PRECISION.
flowchart LR
    A[Endothelin-1 Release] --> B[ETA Receptor]
    A --> C[ETB Receptor]
    B --> D[Vasoconstriction<br/>Fibrosis<br/>Aldosterone Release]
    C --> E[NO Release<br/>Natriuresis<br/>ET-1 Clearance]
    F[Aprocitentan] -.blocks.-> B
    F -.blocks.-> C
    D -.suppressed.-> G[BP Lowering]
    E -.partially suppressed.-> H[Fluid Retention<br/>Side Effect]
    style F fill:#ffe066,color:#1a1a1a
    style G fill:#a3e4d7,color:#1a1a1a
    style H fill:#f5b7b1,color:#1a1a1a
2. Clinical Evidence — PRECISION Trial Deep Dive
2.1 PRECISION Design (Schlaich et al., Lancet 2022, PMID 36356632)
| Element |
Detail |
| Design |
Phase 3, three-part, blinded RCT |
| Sites |
Europe, North America, Asia, Australia |
| Enrollment dates |
June 2018 – April 2022 |
| Inclusion |
Sitting SBP ≥140 mmHg despite 3-drug background therapy including a diuretic |
| Background therapy |
Standardized fixed-dose single-pill triple combination |
| Run-in |
4-week placebo run-in to exclude placebo responders |
| Part 1 |
4-week DB RCT — 12.5 mg vs 25 mg vs placebo, 1:1:1 |
| Part 2 |
32-week single-blind, all patients on 25 mg |
| Part 3 |
12-week DB withdrawal — re-randomized 25 mg vs placebo, 1:1 |
| Primary endpoint |
Office SBP change baseline → week 4 |
| Key secondary |
Office SBP change withdrawal baseline → week 40 |
| ClinicalTrials.gov |
NCT03541174 |
2.2 The Pseudoresistance Lesson (The Most Important Finding Most People Miss)
PRECISION screened 1,965 patients referred for resistant HTN. After the screening process — switching to a single-pill triple combination, requiring 4 weeks of confirmed adherence, and confirming office SBP remained ≥140 — only 730 patients (37.2%) met criteria for randomization.
The single most common reason for screening failure (44.4% of all screened patients) was that BP normalized once patients were switched to a fixed-dose combination pill and given proper run-in adherence support. This is non-adherence and white-coat HTN masquerading as treatment-resistant disease. Before you reach for a fourth drug, fifth drug, or aprocitentan, the literature is screaming that you should: (1) confirm adherence (pill counts, pharmacy refill data, witnessed dosing), (2) move to single-pill combinations, (3) confirm BP elevation with home or ambulatory monitoring, (4) check for secondary causes (Conn’s, OSA, RAS, drugs). The PRECISION run-in is essentially what every “resistant HTN” workup should look like.
This is not a footnote. The Danaietash 2022 baseline paper (PMID 35686330) #ref2 explicitly framed pseudoresistance as a major finding of the screening process — and it should change clinical practice independent of whether you ever prescribe aprocitentan.
2.3 Primary Endpoint Results
Office SBP change at week 4:
| Treatment |
LS Mean Change (mmHg) |
Difference vs Placebo |
97.5% CI |
P value |
| Placebo |
−11.5 (SE 0.9) |
reference |
— |
— |
| Aprocitentan 12.5 mg |
−15.3 (SE 0.9) |
−3.8 |
−6.8 to −0.8 |
0.0042 |
| Aprocitentan 25 mg |
−15.2 (SE 0.9) |
−3.7 |
−6.7 to −0.8 |
0.0046 |
Both doses beat placebo by approximately 4 mmHg office SBP. The 25 mg dose did not produce greater BP lowering than the 12.5 mg dose at week 4 — this is unusual for an antihypertensive and supports starting at 12.5 mg as the default.
24-hour ABPM SBP change at week 4 (placebo-corrected):
| Dose |
Difference vs Placebo (mmHg) |
95% CI |
| 12.5 mg |
−4.2 |
−6.2 to −2.1 |
| 25 mg |
−5.9 |
−7.9 to −3.8 |
The ABPM signal is larger than the office signal, particularly at 25 mg, suggesting the office measurement underestimates the true effect. ABPM also revealed that the 25 mg dose has incremental nocturnal BP control that the office measurement missed. Bottom line: 12.5 mg is the right starting dose; 25 mg gives meaningful additional ABPM benefit but comes with double the edema risk.
2.4 The Withdrawal Phase — Persistence of Effect
Part 3 of PRECISION re-randomized patients at week 36 to either continued 25 mg aprocitentan or placebo for 12 weeks. After 4 weeks of withdrawal, office SBP rose 5.8 mmHg in the placebo arm vs the aprocitentan arm (95% CI 3.7–7.9, P<0.0001) — confirming the drug-attributable effect was sustained at 40 weeks of treatment and fades when you stop it.
Many resistant HTN trials report a placebo-corrected drop early but never test whether the effect persists. PRECISION’s withdrawal phase is the answer to “does this drug actually work over time, or does it lose effect?” The 5.8 mmHg pop on withdrawal at 40 weeks tells you the answer is yes, it persists. Compare this favorably to renal denervation trials where the durability question is still genuinely contested.
2.5 Safety Profile
| Adverse event |
Placebo (4-week) |
12.5 mg (4-week) |
25 mg (4-week) |
| Edema / fluid retention (any) |
2% |
9% |
18% |
| Edema → discontinuation |
0 |
small N |
7 patients (across both arms) |
| Anemia (decrease in Hb) |
minimal |
dose-related |
dose-related |
| Hepatic enzyme elevation |
minimal |
minimal |
minimal |
| Treatment-emergent deaths (entire trial) |
11 total, none judged related to study drug |
|
|
The hemoglobin signal is real but small. Class effect from endothelin antagonism — modest hemodilution from fluid shift plus mild RBC hemolysis effects. PRECISION did not show clinically significant anemia requiring intervention.
Aprocitentan liver monitoring: measure aminotransferases and total bilirubin before treatment and repeat periodically and when clinically indicated, following the current FDA label. The 2026 label does not mandate monthly liver tests for the first year. Review symptoms and label-based interruption criteria along with fluid retention and hemoglobin.
Aprocitentan is contraindicated during pregnancy because of embryo-fetal toxicity. Exclude pregnancy before initiation; advise effective contraception before treatment, throughout treatment, and for one month after stopping. Patients should promptly report suspected pregnancy; follow the current label for testing and counseling. Do not substitute obsolete pregnancy letter categories or a historical REMS schedule for current instructions.
4. The CKD Subgroup Question
PRECISION did not report a pre-specified CKD subgroup analysis in the primary publication, but enrollment criteria allowed eGFR ≥15. The Heidari Nejad/Schlaich Future Cardiology 2024 review (PMID 38953510) #ref4 specifically frames aprocitentan as “a particularly useful antihypertensive option for individuals with advanced age, chronic kidney disease, and albuminuria.”
The mechanistic case for aprocitentan in CKD borrows from the SONAR atrasentan experience — selective ETA blockade reduced UACR by approximately 35% and slowed eGFR decline in patients with T2D and CKD before the trial was stopped early for fluid retention/HF events. The Smeijer/Heerspink Nature Reviews Nephrology 2024 review (PMID 39643698) #ref5 is the definitive synthesis of where the endothelin pathway fits in CKD: real antifibrotic and proteinuria-lowering effects, real fluid retention liability, and best deployed in patients without HF and in combination with SGLT2i to mitigate the fluid retention.
PRECISION did not measure UACR change as a primary or key secondary outcome. It did not report eGFR slope. It did not report a CKD-specific subgroup BP analysis. Anyone selling you an “aprocitentan for CKD” story is extrapolating from PATHWAY trials and the SONAR atrasentan experience, not citing dedicated aprocitentan CKD data. The renal/proteinuria question requires either a post-hoc PRECISION analysis or a dedicated trial that does not yet exist.
4.1 The Combination With SGLT2i
The most rational future trial design — and the position taken by Smeijer/Heerspink in Nat Rev Nephrol — is endothelin antagonist + SGLT2i as a combination strategy. SGLT2i provides natriuresis and intravascular volume reduction that can offset the fluid retention liability of endothelin blockade. The ZENITH-CKD trial of zibotentan + dapagliflozin demonstrated this synergy in proof-of-concept. No equivalent aprocitentan + SGLT2i combination trial has been reported as of this writing. This is the obvious next study, but until it exists, combination is empirical.
5. Practical Prescribing — How to Actually Use This Drug
5.1 Patient Selection
Best candidate: - True resistant HTN confirmed by ABPM - Already on optimized triple therapy (ACEi/ARB + DHP-CCB + thiazide or thiazide-like) - Adherence verified (single-pill combinations, pharmacy data, witnessed dosing) - Pseudoresistance ruled out (proper measurement, secondary cause workup completed) - MRA contraindicated by hyperkalemia OR has caused gynecomastia OR has failed at maximum tolerated dose - No history of HF (HFrEF or HFpEF) - No active liver disease - Female of reproductive potential has reliable contraception OR not at risk of pregnancy
Avoid: - Any HF history (HFrEF, HFpEF, NYHA II–IV) - Pregnancy or potential pregnancy without contraception plan - Moderate-to-severe hepatic impairment - Severe anemia (Hb <10) at baseline - Patients unable to complete required baseline and follow-up safety monitoring
5.2 Dosing
| Step |
Dose |
Notes |
| Start |
12.5 mg PO daily |
Same efficacy as 25 mg in PRECISION at 4 weeks; less edema |
| Titration |
Consider 25 mg only if BP target not met after 4–6 weeks AND no edema |
The 25 mg dose adds ABPM benefit but doubles edema risk |
| Renal |
No adjustment ≥15 eGFR |
Dialysis data limited |
| Hepatic |
Avoid moderate-severe impairment |
Class warning |
5.3 Monitoring
| Parameter |
Baseline |
Frequency |
| LFTs (ALT, AST, bilirubin) |
Yes |
Periodically and as clinically indicated (current label) |
| Hemoglobin |
Yes |
Periodically as clinically indicated (current label) |
| Pregnancy test |
Yes (if applicable) |
As clinically indicated; follow current label |
| BP |
Yes |
2 weeks, 4 weeks, 8 weeks, then quarterly |
| Weight (edema surveillance) |
Yes |
At each BP check |
| Lower extremity edema exam |
Yes |
At each BP check |
5.4 What to Do If Edema Develops
- Mild edema (trace pitting, no symptomatic worsening): Continue, recheck in 2 weeks. Add or up-titrate loop diuretic if not already on one.
- Moderate edema (>1+ pitting, weight gain >2 kg, dyspnea): Hold aprocitentan. Diurese. Reassess HF risk. Consider rechallenge at 12.5 mg if event was clearly fluid retention without HF.
- Severe edema or any HF symptoms: Discontinue permanently. Rule out incident HF. Do not rechallenge.
5.5 The Cost Conversation
Aprocitentan list price is approximately $22,000 per year in the US. For a patient already on optimized polytherapy who would otherwise face procedural intervention or institutional placement for uncontrolled BP, the cost is justifiable. For a patient who has not had a real adherence intervention, this is a $22,000/year solution to a $0 adherence problem.
Insurance coverage: Most plans require step therapy through MRA (spironolactone or eplerenone) and documentation of either failure or hyperkalemia. Prior authorization is the norm — the /prior auth skill is built for exactly this conversation.