Cancer-Associated Electrolyte Emergencies: Comprehensive Clinical Management
Written for: Experienced nephrologist audience from onco-nephrology perspective Board-Review Depth: Yes | Practical Management: Yes
Visual reference
Browse the visual reference library · Download lesson Markdown
OVERVIEW & CLINICAL CONTEXT
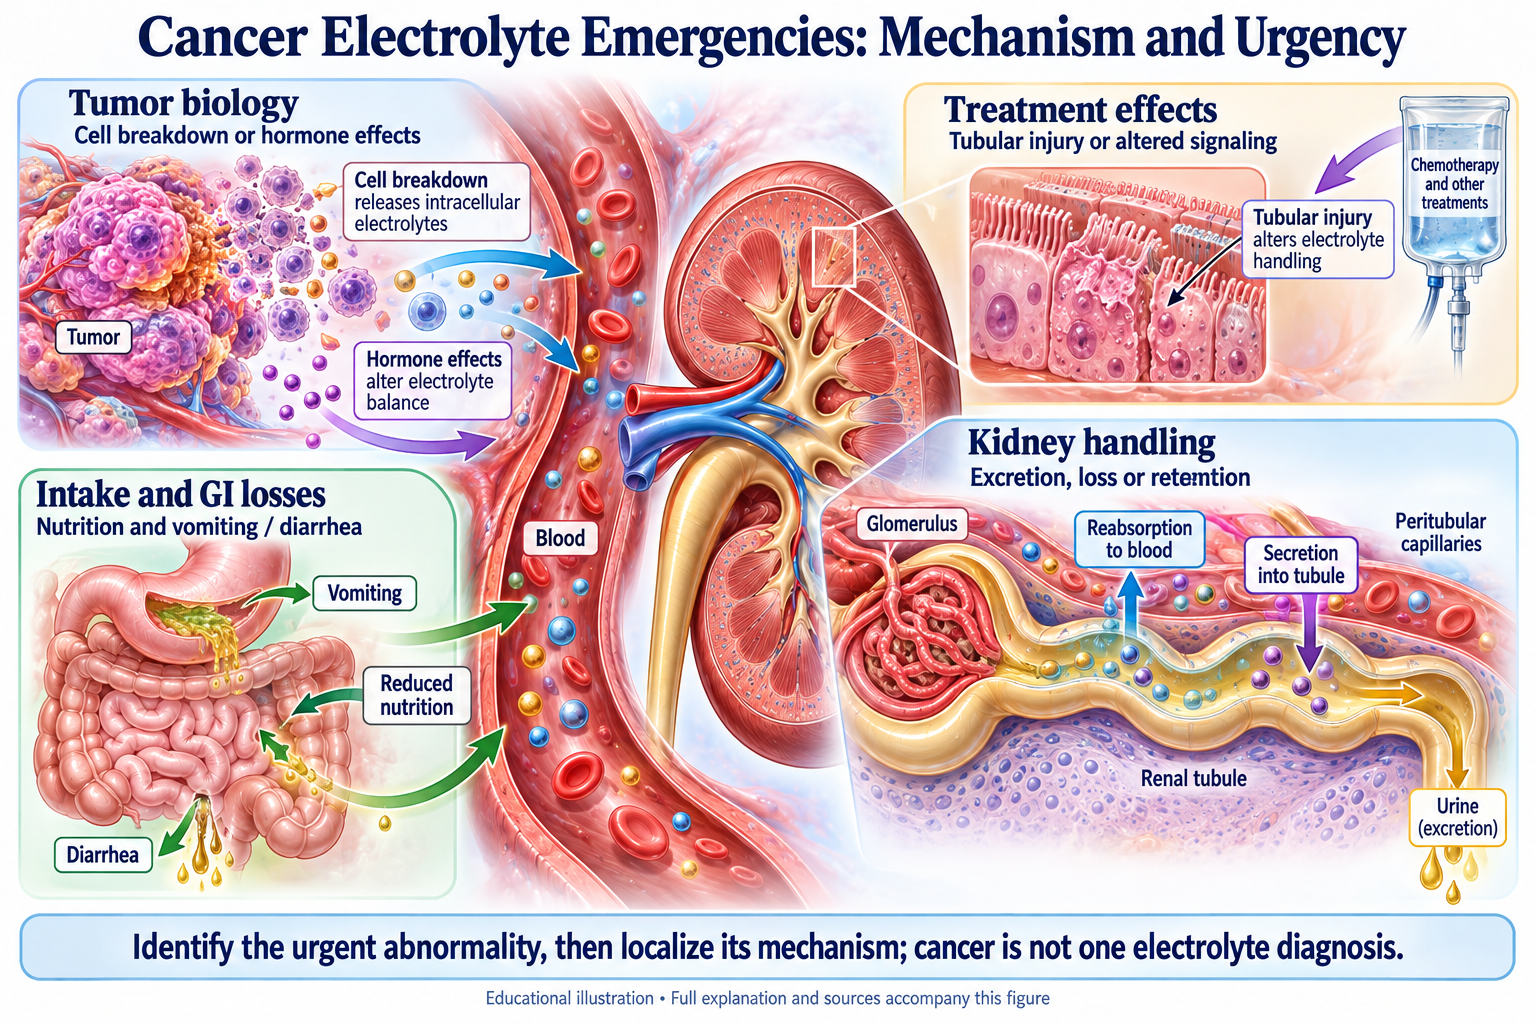
Cancer-associated electrolyte abnormalities may reflect tumor biology, anticancer therapy, reduced intake, gastrointestinal loss, kidney dysfunction, endocrine disease, or medications. Stabilize emergencies while establishing the mechanism. Mixed causes are common; the cancer diagnosis does not make every abnormal value paraneoplastic. PubMed 24359982
HYPONATREMIA IN CANCER PATIENTS
Epidemiology & Etiology
Hyponatremia may accompany SIAD, hypovolemia, kidney or heart failure, adrenal insufficiency, hyperglycemia, and drug exposure. Small-cell lung cancer is a recognized setting for SIAD, but symptoms and laboratory findings require independent evaluation. Check plasma tonicity before applying a hypotonic-hyponatremia algorithm.
SIADH in Cancer (Deep Dive)
Board Point: SIADH is the #1 cause of hyponatremia in cancer and is a paraneoplastic endocrine emergency.
Pathophysiology
Antidiuresis limits free-water excretion. It may be driven by ectopic hormone production, pulmonary/CNS disease, pain, nausea, or drugs. In SIAD, antidiuresis is inappropriate to plasma tonicity and effective circulating volume. The diagnosis requires exclusion of relevant mimics.
Diagnostic Criteria for SIADH [2]
Typical findings are hypotonic hyponatremia, urine osmolality >100 mOsm/kg despite low plasma tonicity, clinical euvolemia, and urine sodium usually >30 mmol/L with appropriate intake. Exclude adrenal insufficiency and significant thyroid dysfunction, and consider kidney impairment and diuretic confounding. Urine osmolality need not exceed plasma osmolality. No single urine value proves SIAD. PubMed 24569125
Acute vs. Chronic SIADH in Cancer
Acute hyponatremia develops within 48 hours; chronic disease lasts at least 48 hours. If duration is unknown, protect against overcorrection as for chronic disease. Treatment urgency depends on symptoms and clinical context as well as sodium level. Severe neurologic symptoms may require hypertonic saline regardless of duration.
Management of Cancer-Associated SIADH [2]
Severe Symptomatic Hypotonic Hyponatremia
Seizure, coma, or severe symptoms attributable to hypotonic hyponatremia require monitored emergency treatment with hypertonic saline according to a validated protocol. The initial aim is a small controlled rise sufficient to relieve symptoms, not immediate normalization. A sodium value below 120 mmol/L alone does not define the regimen.
Check sodium and urine output frequently during active correction. Avoid exceeding guideline correction limits; use a conservative ceiling of 8 mmol/L in any 24 hours in patients at high risk of osmotic demyelination, including malnutrition, hypokalemia, advanced liver disease, or very low starting sodium. Detect emerging water diuresis; specialist-directed desmopressin and free water may be needed to prevent or reverse overcorrection. PubMed 24569125
Chronic SIADH (Asymptomatic or Mild Symptoms)
Treat contributing drugs, nausea, pain, and underlying disease. Fluid restriction and adequate dietary solute may help but can be difficult during cancer treatment; oral urea or other therapies require individualized specialist selection. Isotonic saline is appropriate for hypovolemia but can worsen SIAD when urine remains concentrated.
Tolvaptan: a small post hoc SALT analysis included 28 patients with cancer and SIAD; improvement in sodium does not prove better cancer survival or universal superiority. In the United States, initiate or reinitiate in hospital with close sodium monitoring, assess contraindications/interactions, allow access to water and response to thirst, and avoid fluid restriction during the first 24 hours. It is not treatment for urgently correcting serious neurologic symptoms. Limit treatment to 30 days and avoid underlying liver disease under the SAMSCA label. PubMed 28251822; current prescribing information.
Treating Underlying Cancer
Cancer-directed treatment can improve tumor-related antidiuresis, but sodium stabilization and oncology treatment must be coordinated. Resolving the stimulus can trigger water diuresis and rapid correction; continue biochemical monitoring rather than assuming treatment of the tumor makes correction predictable.
Cerebral Salt Wasting (CSW) — Rare, Important Distinction
Renal salt wasting after CNS disease or selected drugs is a differential diagnosis, not a conclusion from high urine sodium alone. Both SIAD and salt wasting can have concentrated urine and elevated urine sodium. Establish the fluid balance, hemodynamics, losses, endocrine status, and medication context. Clinically meaningful salt wasting is associated with volume depletion; jugular venous distension suggests a different volume state. Replacement rather than fluid restriction is required when true hypovolemia is present.
HYPERCALCEMIA OF MALIGNANCY (HCM)
Epidemiology & Etiology
Hypercalcemia of malignancy arises through PTH-related peptide, osteolytic disease, excess calcitriol, or rarely ectopic PTH/parathyroid carcinoma. Frequency varies greatly with cancer type and stage. Check PTH early: suppression supports a PTH-independent process; an inappropriately nonsuppressed PTH requires a different workup.
Pathophysiology of HCM [1]
PTHrP-Mediated HCM (Most Common)
Tumor-derived PTH-related peptide stimulates PTH-receptor pathways, increasing bone resorption and renal calcium retention while promoting phosphate loss. Endogenous PTH is generally suppressed. The biochemical pattern must be interpreted with kidney function and other potential mechanisms.
Osteolytic HCM (Breast, Myeloma)
Local tumor–bone interactions activate osteoclasts and release calcium. Endogenous PTH is usually suppressed in osteolytic hypercalcemia, as it is in PTHrP-mediated disease. Assess the underlying malignancy and skeletal involvement; the mechanisms can coexist.
Calcitriol-Mediated HCM (Lymphomas)
Some lymphomas produce excess calcitriol through extrarenal vitamin D activation, increasing intestinal calcium absorption. Measure calcitriol when the clinical differential warrants it. Glucocorticoids can address this mechanism; persistent severe or symptomatic hypercalcemia may also require antiresorptive therapy. PubMed 36545746
Clinical Presentation of HCM
Symptoms include thirst, polyuria, volume depletion, constipation, weakness, confusion, and arrhythmia. Interpret total calcium with albumin and consider ionized calcium when binding or acid-base abnormalities make total calcium misleading. Urgency depends on symptoms, degree and rate of rise, kidney function, and cardiovascular status.
Management of HCM [1]
Severe or Symptomatic Hypercalcemia
Severe hypercalcemia is generally >14 mg/dL, but clinically important symptoms can occur at lower values. Restore intravascular volume with isotonic fluid as tolerated while assessing cardiac/kidney reserve. Use an IV bisphosphonate or denosumab for HCM; the Endocrine Society suggests denosumab over IV bisphosphonates, with low-certainty evidence. Calcitonin can provide a rapid bridge in severe HCM and is limited to 48–72 hours because of tachyphylaxis.
Antiresorptive effects are not an immediate four-hour rescue. Select bisphosphonate dose/infusion and suitability with kidney function and the product label. Denosumab does not require renal clearance but can cause marked hypocalcemia, especially with advanced CKD. Loop diuretics increase urinary calcium excretion but are not routine primary therapy; reserve them for clinically indicated fluid overload after assessment. Consider dialysis for severe refractory complications or when medical treatment is constrained. PubMed 36545746
Chronic Hypercalcemia Management
Treat the underlying cancer and select ongoing antiresorptive or mechanism-specific therapy with oncology/endocrinology. Refractory or recurrent HCM after IV bisphosphonate treatment may respond to denosumab. Parathyroid carcinoma may require calcimimetic, antiresorptive, and definitive surgical assessment. Review calcium/vitamin D use in the clinical context rather than imposing one universal regimen.
Monitoring Post-Treatment
Follow calcium, phosphate, magnesium, kidney function, symptoms, and fluid balance. Watch for delayed hypocalcemia after antiresorptive treatment, particularly in CKD or vitamin D deficiency. Arrange a clear follow-up plan matched to the drug and expected response.
TUMOR-INDUCED OSTEOMALACIA (TIO) & HYPOPHOSPHATEMIA
Epidemiology & Pathophysiology
Tumor-induced osteomalacia is usually caused by an FGF23-secreting mesenchymal tumor. Suspect it with persistent hypophosphatemia, renal phosphate wasting, bone pain, weakness, or insufficiency fractures. Assess fasting phosphate and renal phosphate handling, alkaline phosphatase, calcium, PTH, vitamin D metabolites, and FGF23 using the assay and phosphate context; an inappropriately normal FGF23 can be relevant. A universal FGF23 cutoff is inappropriate.
Localize the tumor with specialist-directed imaging. Complete resection is preferred when feasible. For unresectable or unlocalized disease, conventional phosphate/active-vitamin-D therapy or burosumab may be considered under specialist guidance, with monitoring for treatment complications. PubMed 36511653
CISPLATIN-INDUCED HYPOMAGNESEMIA
Incidence & Mechanism
Cisplatin can cause renal magnesium wasting; reduced intake, vomiting/diarrhea, and other drugs can compound the deficit. Hypomagnesemia may persist after exposure and contribute to hypokalemia or hypocalcemia. Interpret magnesium using the laboratory reference range rather than a universal target above 2 mg/dL.
Management of Magnesium Depletion
Monitor magnesium, potassium, calcium, and kidney function around treatment according to risk and the oncology protocol. Oral replacement is often suitable for mild deficits if tolerated; symptomatic or severe deficits may need monitored IV replacement. Adjust dose and infusion rate for kidney function and clinical urgency. Cisplatin hydration/magnesium protocols are regimen-specific; a fixed weekly replacement course cannot guarantee renal protection.
FANCONI SYNDROME IN CANCER PATIENTS
Etiology in Oncology
Ifosfamide, selected other drugs, and monoclonal light-chain disease can injure the proximal tubule. Cisplatin-related tubular dysfunction is possible, but no fixed incidence applies across all regimens. Review cumulative exposure, co-medications, and the underlying plasma-cell disorder.
Clinical Presentation
A proximal tubular wasting pattern may include normoglycemic glycosuria, phosphate and urate wasting, aminoaciduria, low-molecular-weight proteinuria, and bicarbonate loss. The pattern can be incomplete and may occur without a large creatinine rise. Distinguish isolated electrolyte depletion from generalized Fanconi syndrome.
Management
Coordinate withdrawal, substitution, or dose adjustment of the cause with oncology; treat the responsible clone when relevant. Replace deficits and alkali according to measured needs, symptoms, kidney function, and serial testing. Monitoring may need to be frequent during active losses; monthly testing is not sufficient for every unstable patient.
ELECTROLYTE EMERGENCIES: HYPERKALEMIA IN CANCER
Etiology in Oncology
Consider TLS, impaired potassium excretion from AKI/CKD, potassium-retaining drugs, acidosis, and primary adrenal failure. Pituitary disease generally preserves aldosterone and does not by itself explain hyperkalemia. Marked leukocytosis, thrombocytosis, or sample handling can cause pseudohyperkalemia; confirm suspicious results while urgently treating a credible dangerous presentation.
Emergency Hyperkalemia Management
Assess ECG, severity, trajectory, and renal function promptly. Give IV calcium for indicated cardiac membrane stabilization, use monitored potassium-shifting therapy with glucose surveillance, and arrange potassium removal. Repeat potassium testing because redistribution is temporary. Refractory or life-threatening hyperkalemia may require dialysis; the modality depends on urgency and hemodynamics. Follow an emergency protocol rather than treating a single threshold as a complete order set.
LACTIC ACIDOSIS IN ADVANCED CANCER
Type B Lactic Acidosis (From Tumor Burden)
First evaluate shock, sepsis, hypoxemia, medications, and other common causes of elevated lactate. Malignancy-associated type B lactic acidosis can reflect accelerated tumor glycolysis, reduced hepatic clearance, or thiamine deficiency, and does not require extensive liver metastases. Correct reversible contributors, support perfusion when needed, and involve oncology promptly for disease-directed treatment. Fluids must match volume/perfusion assessment; indiscriminate loading is unsafe. Buffering or kidney replacement may be needed for severe acid-base complications but does not reliably control ongoing tumor lactate production. Prognosis is serious but cannot be assigned from an unsupported pH-based mortality percentage.
SYNDROME OF INAPPROPRIATE ANTIDIURESIS (SIAD) — EXPANDED VIEW
Beyond Traditional SIADH
SIAD means inappropriate antidiuresis and includes mechanisms beyond measurable excess circulating ADH. It is not a separate category defined by sodium <120 mmol/L or failure of fluid restriction. Reassess the diagnosis and the cause of nonresponse before escalating treatment.
Tolvaptan in Advanced Cancers
Consider tolvaptan only in an appropriately selected euvolemic or hypervolemic hyponatremia setting, with specialist monitoring and the applicable label. Correcting sodium is not proof of improved survival. Patients unable to sense/respond to thirst or who need urgent neurologic rescue are not routine candidates. See the earlier hospital-initiation, correction-rate, liver, and duration precautions. PubMed 28251822
CITED REFERENCES
[1] Turcotte A, Achi S, Mamlouk O, et al. Electrolytes disturbances in cancer patients. Curr Opin Nephrol Hypertens. 2022;31(5):425-434. PubMed 35894276
[2] Castillo JJ, Vincent M, Justice E. Diagnosis and management of hyponatremia in cancer patients. Oncologist. 2012;17(6):756-65. PubMed 22618570
[3] Rosner MH, Dalkin AC. Electrolyte disorders associated with cancer. Adv Chronic Kidney Dis. 2014;21(1):7-17. PubMed 24359982
[5] Khan MI, Dellinger RP, Waguespack SG. Electrolyte Disturbances in Critically Ill Cancer Patients: An Endocrine Perspective. J Intensive Care Med. 2018;33(3):147-158. PubMed 28535742
[6] El-Hajj Fuleihan G, Clines GA, Hu MI, et al. Treatment of Hypercalcemia of Malignancy in Adults: An Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab. 2023;108(3):507-528. PubMed 36545746
[7] Jan de Beur SM, Minisola S, Xia WB, et al. Global guidance for the recognition, diagnosis, and management of tumor-induced osteomalacia. J Intern Med. 2023;293(3):309-328. PubMed 36511653
[8] Gralla RJ, Ahmad F, Blais JD, et al. Tolvaptan use in cancer patients with hyponatremia due to the syndrome of inappropriate antidiuretic hormone: a post hoc analysis of the SALT-1 and SALT-2 trials. Cancer Med. 2017;6(4):723-729. PubMed 28251822
[9] Spasovski G, Vanholder R, Allolio B, et al. Clinical practice guideline on diagnosis and treatment of hyponatraemia. Eur J Endocrinol. 2014;170(3):G1-47. PubMed 24569125
Reviewed: October 3, 2026.