CAR-T Cell Therapy and Kidney Disease: Emerging Frontier for Nephrologists
Written for: Experienced nephrologist audience from onco-nephrology perspective Board-Review Depth: Yes | Practical Management: Yes
Visual reference
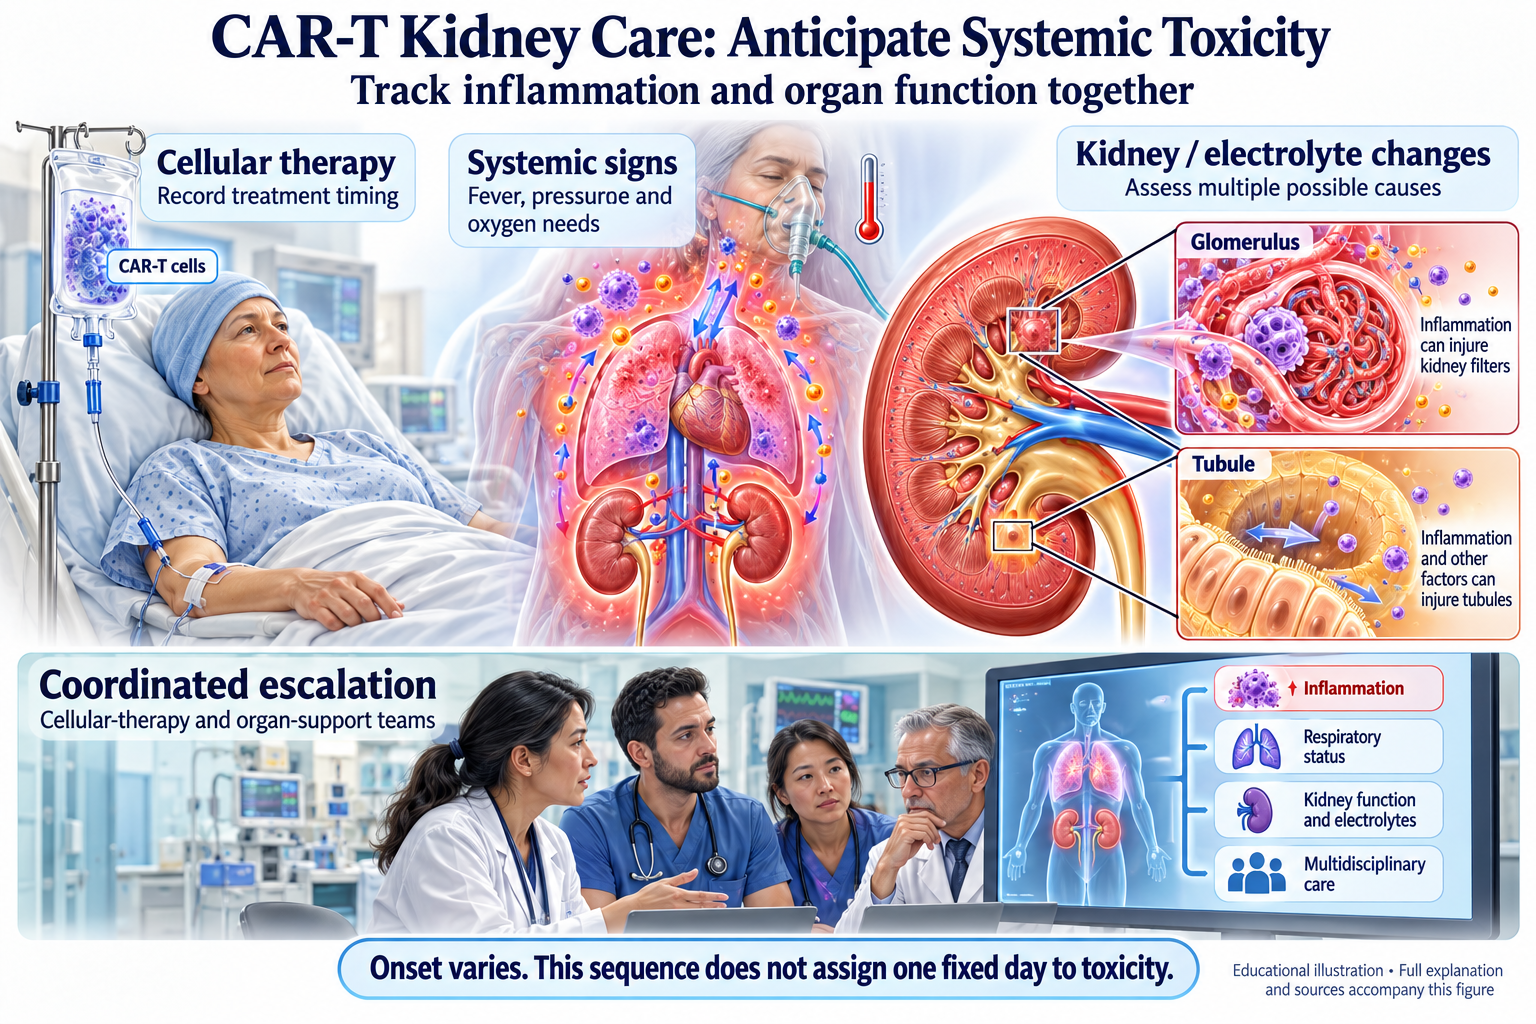
Browse the visual reference library · Download lesson Markdown
OVERVIEW & CLINICAL CONTEXT
CAR-T cell therapy represents a paradigm shift in cancer immunotherapy — autologous or allogeneic T-cells engineered to express chimeric antigen receptors targeting tumor-associated antigens, primarily CD19 and BCMA. FDA approval of multiple CAR-T products (2017–present) has expanded treatment across B-cell malignancies and multiple myeloma. However, CAR-T comes with a spectrum of immune-related toxicities, including substantial renal complications that nephrologists are increasingly asked to manage.
The kidney nephrologist is consulted for: - Pre-CAR-T baseline renal assessment and optimization - Management of cytokine release syndrome (CRS)-related AKI - Electrolyte emergencies post-CAR-T infusion - Immune effector cell-associated neurotoxicity (ICANS) and concurrent renal injury - Long-term renal outcomes in CAR-T survivors - CAR-T in patients with pre-existing CKD or ESRD
CAR-T CELL THERAPY: BASIC MECHANISMS
What Are CAR-T Cells?
CAR-T cells are genetically engineered autologous T lymphocytes that express a synthetic receptor (chimeric antigen receptor) combining:
- Extracellular domain: Single-chain variable fragment (scFv) — antibody-like structure recognizing tumor antigen
- Transmembrane domain: Bridges cell surface to intracellular
- Intracellular signaling domains:
- CD3ζ (primary): T-cell receptor signaling
- Costimulatory domains: CD28 or 4-1BB (second signal for T-cell activation)
Generation: 1. Autologous T-cell collection (leukapheresis) 2. Ex vivo transduction with CAR construct (viral or non-viral) 3. Ex vivo expansion (2–4 weeks in cell therapy facility) 4. Single infusion into patient
Selected CAR-T Products
Selected examples: CD19-directed products include tisagenlecleucel, axicabtagene ciloleucel, brexucabtagene autoleucel, and lisocabtagene maraleucel. BCMA-directed products include idecabtagene vicleucel and ciltacabtagene autoleucel. They differ in construct, indicated disease, eligibility, and toxicity profile. This is not an exhaustive current approval list; verify the exact product label and cell-therapy protocol. PubMed 40107382
CAR-T Kinetics & Renal Relevance
Cell expansion, CRS, ICANS, and AKI may overlap after infusion. Their onset and duration vary by product, disease burden, prior treatment, and patient factors. A calendar day alone cannot exclude a complication. Follow the product-specific monitoring schedule and investigate new fever, hypotension, hypoxia, neurologic change, or reduced urine output promptly.
CYTOKINE RELEASE SYNDROME (CRS) & KIDNEY DISEASE
Definition & Pathophysiology [1]
CRS is a systemic inflammatory response caused by massive CAR-T proliferation and consequent immune activation.
Cytokine cascade:
CAR-T cells recognize antigen on tumor/normal B-cells
    ↓
T-cell receptor + CD28/4-1BB signaling → T-cell activation
    ↓
CAR-T secretion of:
├─ IL-2, IL-7 (T-cell growth factors)
├─ IL-6 (pro-inflammatory; acts on IL-6R)
├─ TNF-α, IFN-γ (macrophage activation)
├─ GM-CSF (hematopoietic cell activation)
└─ Other: MCP-1, IP-10, IL-10
    ↓
Activation of:
├─ Macrophages → more IL-6, TNF-α
├─ Endothelial cells → loss of barrier function
├─ Mast cells, neutrophils → further cytokine release
└─ Systemic inflammatory cascade
    ↓
SYSTEMIC CONSEQUENCES:
CRS Grading: ASTCT Consensus
Use the ASTCT consensus rather than mixing historical systems. CRS begins with fever ≥38°C not attributable to another cause; the grade is determined by the more severe hypotension or hypoxia criterion. Once antipyretic or anti-cytokine treatment has been given for CRS, fever is no longer required for subsequent grading.
| Grade | Hypotension | Oxygen support |
|---|---|---|
| 1 | None | None |
| 2 | No vasopressors required | Low-flow nasal cannula ≤6 L/min or blow-by |
| 3 | One vasopressor, with or without vasopressin | High-flow nasal cannula, facemask, non-rebreather, or Venturi mask |
| 4 | Multiple vasopressors, excluding vasopressin | Positive-pressure support |
Assess alternative causes of shock and hypoxia, especially infection. Kidney injury is documented and staged separately; creatinine or dialysis does not independently set the ASTCT CRS grade. PubMed 30592986
IMMUNE EFFECTOR CELL-ASSOCIATED NEUROTOXICITY (ICANS)
Definition & Incidence
ICANS is a distinct neurologic toxicity that may occur with or after CRS. Assess and grade it with the ASTCT framework, including the ICE assessment in suitable adults, consciousness, seizures, motor findings, and cerebral edema. Symptoms such as new aphasia, altered handwriting, confusion, or seizure require urgent cell-therapy and neurologic assessment. PubMed 30592986
Renal Involvement in ICANS
Kidney failure, sodium disorders, drug accumulation, and infection can mimic or aggravate encephalopathy. Do not attribute every neurologic change to ICANS. Cerebral edema requires specialist management; neither routine fluid restriction nor aggressive fluid loading is a universal answer. Maintain appropriate perfusion while avoiding overload and rapid osmotic shifts. Prolonged seizures can cause rhabdomyolysis and pigment-associated tubular injury.
ELECTROLYTE ABNORMALITIES AFTER CAR-T [1]
Hypophosphatemia & Phosphate Wasting
Hypophosphatemia is common in some cohorts. Potential contributors include intracellular redistribution during cellular activation, poor intake, and renal losses; the mechanism may be multifactorial. B-cell aplasia is not evidence of loss of an FGF23-producing organ. Assess severity, symptoms, nutrition, kidney function, and concurrent potassium/calcium before oral or intravenous replacement, with serial reassessment. PubMed 31973908
Hypokalemia & Potassium Wasting
Consider gastrointestinal loss, poor intake, medications, renal wasting, and intracellular shifts. B-cell depletion is not a valid explanation based on “loss of potassium stores.” Check magnesium and ECG when indicated. Replace potassium according to severity, route feasibility, kidney function, and a monitored protocol.
Hypomagnesemia
Poor intake, gastrointestinal losses, and nephrotoxic or diuretic exposures can lower magnesium. Investigate contributing drugs and replace with monitoring; magnesium deficiency may impede correction of hypokalemia. Kidney failure changes replacement safety.
TUMOR LYSIS SYNDROME (TLS) IN CAR-T SETTING
Rapid destruction of susceptible malignant cells may release potassium, phosphate, and nucleic acids, producing hyperkalemia, hyperphosphatemia, hyperuricemia, hypocalcemia, and AKI. Risk depends on tumor burden, treatment sensitivity, and baseline kidney function. CAR-T expansion alone is not a substitute for evidence of tumor lysis. Use risk-adapted laboratory surveillance, fluids compatible with cardiac/kidney reserve, and appropriate urate-lowering prophylaxis or treatment. The CLL targeted-agent review provides TLS background, not a CAR-T-specific incidence estimate. PubMed 28851760
PRE-CAR-T RENAL ASSESSMENT & OPTIMIZATION
Baseline Workup
Document stable baseline creatinine and an appropriate eGFR estimate, urinalysis/proteinuria, sodium, potassium, bicarbonate, calcium, magnesium, phosphate, urate, and medication exposures. Evaluate blood pressure, fluid balance, cardiac disease, and prior AKI. Creatinine-based eGFR is unreliable while kidney function is changing rapidly. The 2021 CKD-EPI equation is an estimating equation, not a “KDIGO 2021 formula.”
Pre-CAR-T Optimization
Eligibility is individualized with the cell-therapy team; a single eGFR threshold does not define candidacy for every product. Correct reversible hypovolemia or electrolyte deficits and review medication doses, interactions, and avoidable nephrotoxins. Fludarabine-containing lymphodepletion requires particular attention to kidney function and exposure. Temporarily holding RAAS therapy depends on hypotension, AKI, potassium, and indication rather than a label of universal nephrotoxicity. PubMed 37010812
POST-CAR-T RENAL MONITORING & MANAGEMENT
Post-Infusion Monitoring
Follow the product and center protocol, with more frequent assessment for CRS, TLS risk, AKI, unstable electrolytes, or neurologic change. Track vital signs, fluid intake/output, weight, creatinine, electrolytes, magnesium, and phosphate. Add urate, LDH, and other TLS studies when indicated. Monitoring continues after discharge according to risk; a fixed days 0–14 schedule is not sufficient for every patient.
Renal Function Monitoring Details
Apply standard AKI criteria using the creatinine trajectory and urine output, while examining possible causes. A percentage change in creatinine alone is not a dialysis trigger. Review hypotension, sepsis, congestion, TLS, obstruction, and drugs; use urinalysis and imaging as appropriate. Adjust drug dosing as kidney function evolves.
SPECIAL POPULATIONS
CAR-T in Pre-Existing CKD
Baseline CKD reduces physiologic reserve and affects lymphodepleting-drug dosing, fluid tolerance, and monitoring. Coordinate oncology, nephrology, pharmacy, and critical care. CKD alone does not establish a universal exclusion threshold, a nonexistent “grade 2.5 CRS,” or an automatic earlier dialysis threshold. PubMed 37010812
CAR-T in Dialysis Patients
Published experience demonstrates feasibility in selected dialysis patients, but evidence is limited and treatment requires individualized planning. Coordinate lymphodepletion dosing, drug dialyzability, dialysis timing, volume, and electrolyte management with the cell-therapy team. Do not routinely omit dialysis on infusion day or promise outcomes equivalent to patients without kidney failure. PubMed 37010812
CAR-T in Cardiac Dysfunction
Baseline cardiac dysfunction increases the complexity of CRS-related shock and congestion. Establish an individualized cardiac assessment and monitoring plan, with cardiology input when indicated. Treat perfusion deficits and excess fluid according to repeated clinical assessment; neither universal fluid restriction nor routine fluid loading is appropriate.
LONG-TERM RENAL OUTCOMES IN CAR-T SURVIVORS
Post-CAR-T Kidney Recovery
Recovery varies with cohort, injury severity, and associated organ dysfunction. In a 46-patient retrospective lymphoma series, no patient required dialysis and most AKI recovered toward baseline within 30 days. That finding should not be generalized to severe ICU-associated AKI or converted into an individual recovery probability. PubMed 32088364
Chronic Renal Function Post-CAR-T
Persistent kidney dysfunction occurs after severe illness. A retrospective ICU cohort found substantial CKD among a small number of AKI survivors with available follow-up; it does not establish an all-recipient incidence. Reassess kidney recovery after discharge and evaluate for new or worsened CKD, with earlier follow-up for persistent AKI or dialysis. PubMed 38915438
CLINICAL MANAGEMENT PEARLS
- Identify CRS, infection, TLS, drug injury, obstruction, and congestion; more than one process may coexist.
- Use ASTCT grading and the current product-specific treatment protocol.
- Escalate promptly for shock, rising oxygen requirements, neurologic change, or worsening AKI.
- Individualize fluids, replacement, and kidney replacement therapy to clinical need.
- Explain recovery uncertainty and arrange follow-up after AKI.
CITED REFERENCES
[1] Kanbay M, Mizrak B, Alper EN, et al. Acute kidney injury following CAR-T cell therapy: a nephrologist's perspective. Clin Kidney J. 2025;18(1):sfae359. PubMed 39781479
[2] Russo E, Gambella M, Raiola AM, et al. Acute kidney injury in hematological patients treated with CAR-T cells: risk factors, clinical presentation and impact on outcomes. Sci Rep. 2024;14(1):26886. PubMed 39506012
[3] Gupta S, Seethapathy H, Strohbehn IA, et al. Acute Kidney Injury and Electrolyte Abnormalities After Chimeric Antigen Receptor T-Cell (CAR-T) Therapy for Diffuse Large B-Cell Lymphoma. Am J Kidney Dis. 2020;76(1):63-71. PubMed 31973908
[4] Gutgarts V, Jain T, Zheng J, et al. Acute Kidney Injury after CAR-T Cell Therapy: Low Incidence and Rapid Recovery. Biol Blood Marrow Transplant. 2020;26(6):1071-1076. PubMed 32088364
[5] Khan I, Khan N, Wolfson N, et al. Safety of CAR-T Cell Therapy in Patients With Renal Failure/Acute Kidney Injury: Focused Review. Clin Hematol Int. 2023;5(2-3):122-129. PubMed 37010812
[6] Vincendeau M, Joseph A, Thieblemont C, et al. Acute kidney injury after CAR-T cell therapy: exploring clinical patterns, management, and outcomes. Clin Kidney J. 2024;17(6):sfae123. PubMed 38915438
[7] Frey N, Porter D. Cytokine Release Syndrome with Chimeric Antigen Receptor T Cell Therapy. Biol Blood Marrow Transplant. 2019;25(4):e123-e127. PubMed 30586620
[8] Sadowski K, Ploch W, Downar A, et al. Nephrotoxicity in CAR-T Cell Therapy. Transplant Cell Ther. 2025;31(7):407-418. PubMed 40107382
[9] Cheson BD, Heitner Enschede S, Cerri E, et al. Tumor Lysis Syndrome in Chronic Lymphocytic Leukemia with Novel Targeted Agents. Oncologist. 2017;22(11):1283-1291. PubMed 28851760 Background on CLL targeted agents; not a CAR-T cohort.
[10] Lee DW, Santomasso BD, Locke FL, et al. ASTCT Consensus Grading for Cytokine Release Syndrome and Neurologic Toxicity Associated with Immune Effector Cells. Biol Blood Marrow Transplant. 2019;25(4):625-638. PubMed 30592986
Reviewed: October 3, 2026.