Key Points
- A patient presenting with massive albuminuria (protein/Cr 7.9), hypoalbuminemia, 3+ edema, and worsening renal function should prompt immediate evaluation for plasma cell dyscrasia regardless of the absence of CRAB features
- Free light chains reported as kappa 17.4 / lambda 3.24 / ratio 5.37 in mg/dL correspond to kappa 174 mg/L and lambda 32.4 mg/L in standard units -- both the ratio and the absolute kappa are elevated above the renal-adjusted reference range, confirming a true clonal kappa-dominant process
- BNP 4,598 pg/mL and troponin I 59 ng/L with echocardiographic LVH, impaired relaxation, and EF 45% meet criteria for advanced cardiac involvement -- this is an oncologic and cardiorenal emergency
- The differential in a kappa-dominant FLC pattern with nephrotic-range albuminuria is led by Light Chain Deposition Disease (LCDD), followed by kappa AL amyloidosis; kidney biopsy is the only test that resolves this distinction
- Dara-VCd is the FDA-approved standard of care for newly diagnosed AL amyloidosis (ANDROMEDA trial)
- Multi-disciplinary care involving nephrology, cardiology, and hematology/oncology with amyloid expertise is required within 24 hours of biomarker confirmation
Visual reference
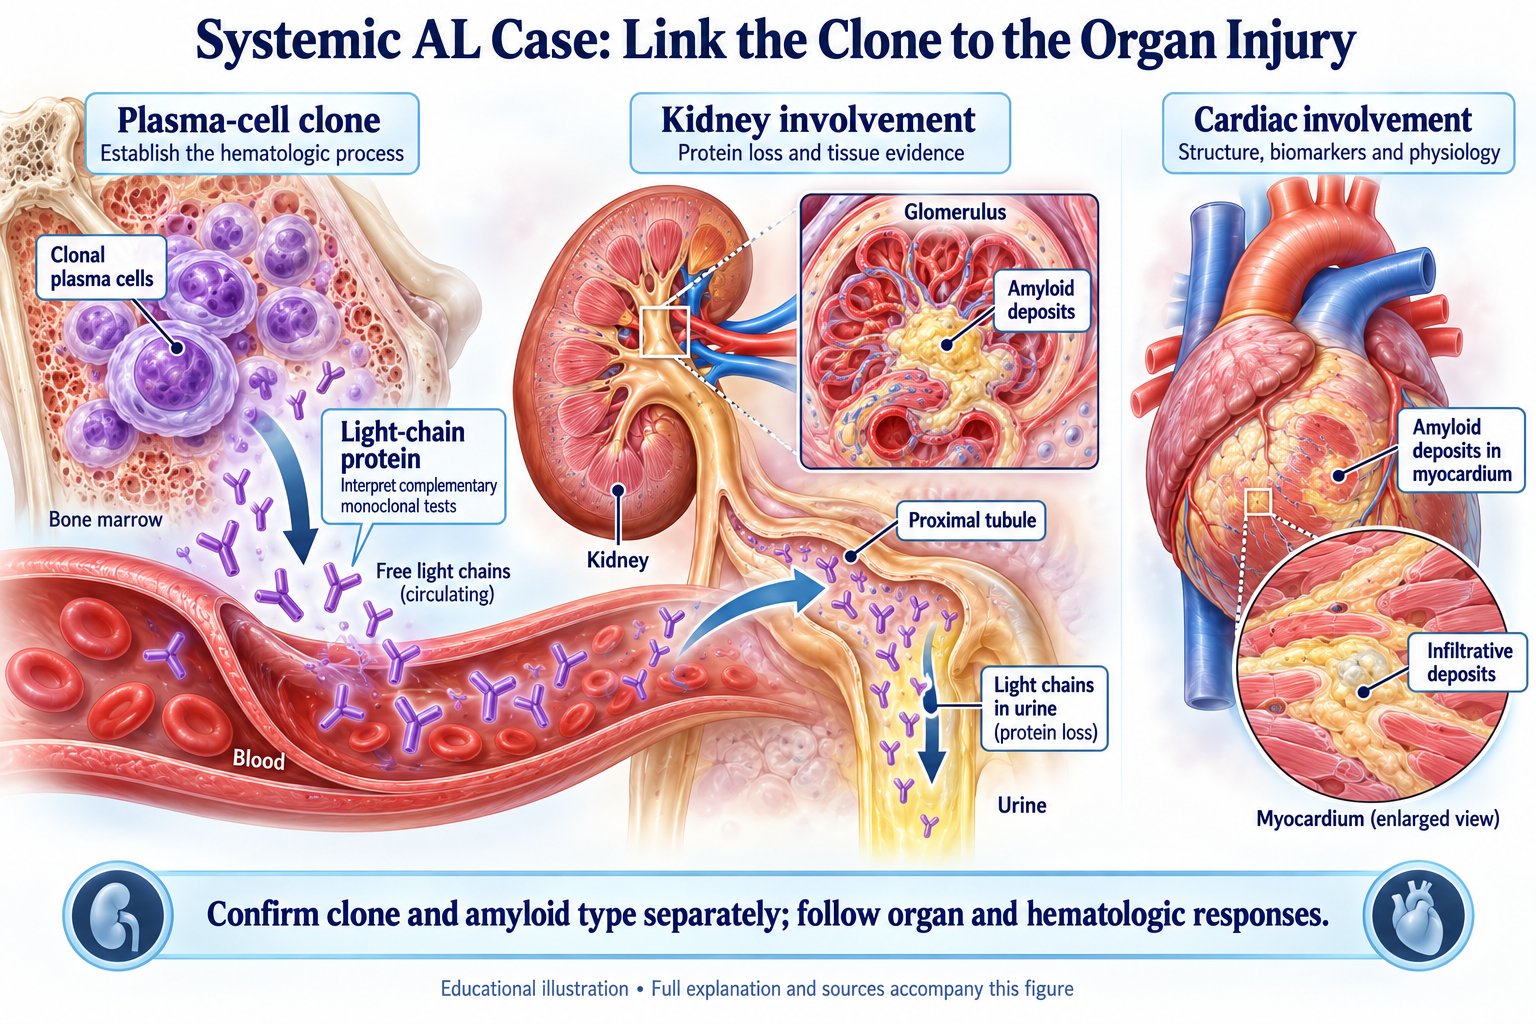
Browse the visual reference library · Download lesson Markdown
1. Case Presentation
Clinical Syndrome
The patient presented with a clinical syndrome characterized by progressive renal insufficiency and volume overload in the setting of prior evaluation by an outside oncologist for severe anemia. Nephrology involvement reframed the presentation from "anemia workup with CKD" to a potential monoclonal gammopathy of renal significance (MGRS) or systemic AL amyloidosis.
Admission Data
| Parameter | Value |
|---|---|
| Creatinine | 2.5 mg/dL (rising to 4.0 with diuresis) |
| Bicarbonate | 21 mEq/L (mild metabolic acidosis) |
| Albumin | 3.1 g/dL |
| Hemoglobin | 8.2 g/dL (prior range 7-9) |
| Platelets | 192 x 103/uL (normal) |
| Calcium | 8.8 mg/dL (normal) |
| Parameter | Value |
|---|---|
| Edema | 3+ bilateral |
| Urine albumin/Cr | >4 |
| Urine protein/Cr | 7.9 |
| Volume response | Minimal; creatinine worsened |
Subsequent Evaluation
| Test | Value | Significance |
|---|---|---|
| Free light chain kappa | 17.4 mg/dL (= 174 mg/L) | ~9x upper limit of normal |
| Free light chain lambda | 3.24 mg/dL (= 32.4 mg/L) | Mildly elevated (CKD artifact) |
| Kappa/Lambda ratio | 5.37 | Above renal-adjusted ULN of 3.1 |
| Echocardiogram | EF 45%, LVH, impaired relaxation | Grade I-II diastolic dysfunction |
| BNP | 4,598 pg/mL | Markedly elevated |
| Troponin I | 59 ng/L | Above cardiac threshold |
Initial Clinical Impression
The combination of massive albuminuria, hypoalbuminemia, preserved platelet count, normal calcium, and absent bone pain placed this patient outside the classical CRAB framework of symptomatic multiple myeloma. Nephrology involvement reframed the presentation from "anemia workup with CKD" to a potential MGRS or systemic AL amyloidosis. The outside oncologic workup had not specifically addressed plasma cell dyscrasia with renal-organ manifestation.
2. Proteinuria Phenotyping -- Glomerular Disease, Not Cast Nephropathy
The urine protein/Cr of 7.9 with albumin/Cr >4 establishes that the proteinuria is albumin-predominant and glomerular in origin. This is the first and most diagnostically decisive point in the case.
| Feature | Cast Nephropathy (Myeloma Kidney) | Glomerular Amyloid / LCDD |
|---|---|---|
| Primary pathology | Distal tubular casts | Mesangial/GBM fibril or non-fibrillar deposits |
| Proteinuria type | Bence Jones (light chains) | Albumin-dominant |
| Urine dipstick | Trace or negative (misses light chains) | 3-4+ positive |
| Serum albumin | Usually preserved | Low -- hypoalbuminemia |
| FLC threshold | Typically >500-1,500 mg/L | Often lower (<500 mg/L) |
| Volume physiology | Variable | Oncotic-driven underfilling |
Clinical Pearl
When a patient with a suspected plasma cell dyscrasia has 3-4+ dipstick proteinuria with hypoalbuminemia and edema, the lesion is glomerular (amyloid, LCDD, or membranoproliferative pattern), not tubular cast nephropathy. Aggressive loop diuresis without this distinction risks AKI from intravascular depletion in a patient who cannot refill from the interstitium due to insufficient oncotic pressure.
3. Free Light Chain Interpretation in Renal Failure
3.1 Unit Conversion -- A Critical Potential Error Source
Serum free light chains are measured and reported in mg/L at most reference laboratories. When values are reported in mg/dL (as in this case), conversion is mandatory: 1 mg/dL = 10 mg/L
| Analyte | Reported (mg/dL) | Converted (mg/L) | Standard Reference (mg/L) |
|---|---|---|---|
| Kappa | 17.4 | 174 | 3.3-19.4 |
| Lambda | 3.24 | 32.4 | 5.7-26.3 |
| Ratio | 5.37 | 0.26-1.65 | |
3.2 Renal-Adjusted Reference Range
The standard FLC reference range (0.26-1.65) was established in patients with normal renal function. The extended reference range for renal impairment is approximately 0.37-3.1. This patient's ratio of 5.37 exceeds the renal-adjusted upper limit, confirming a true clonal process rather than a CKD artifact.
3.3 Delta FLC (dFLC) Calculation
dFLC = Involved - Uninvolved FLC
dFLC = 174 - 32.4 = 141.6 mg/L
The measured dFLC is 174 − 32.4 = 141.6 mg/L, below the Mayo 2012 dFLC threshold of 180 mg/L. Heavy total proteinuria does not quantify urinary light-chain loss and cannot justify increasing the measured dFLC or treating it as an underestimated floor. Stage with the actual required biomarkers and assay definitions.
Warning
In patients with heavy nephrotic-range proteinuria, serum FLC levels are spuriously lowered by urinary losses. The degree of clonal disease burden is likely greater than the serum FLC values imply. Do not use the dFLC alone to assess clone burden in this setting.
4. Differential Diagnosis -- Kappa-Dominant FLC Pattern
The kappa-dominant FLC pattern changes the differential hierarchy compared to a lambda-dominant presentation. Lambda accounts for approximately 70-75% of AL amyloidosis cases, while kappa predominates in multiple myeloma (approximately 60-65%).
1. Light Chain Deposition Disease (LCDD) -- Leading Diagnosis
LCDD most commonly involves kappa light chains (approximately 60-70% of LCDD cases), producing a non-fibrillar, Congo red-negative glomerular deposit along the GBM and mesangium. Presentation is nephrotic-range albuminuria with preserved or mildly reduced GFR and absent CRAB features -- precisely this patient's profile.
2. Kappa AL Amyloidosis -- Close Second
Kappa AL amyloidosis accounts for approximately 25-30% of AL cases. Congo red staining of kidney biopsy will be positive with apple-green birefringence under polarized light if this is the diagnosis.
3. MGRS-class Disease -- Broadest Category
Either of the above may represent a Monoclonal Gammopathy of Renal Significance (MGRS) -- renal disease caused by a clonal immunoglobulin that does not meet criteria for overt myeloma.
Clinical Pearl
Do not wait for overt myeloma criteria before investigating possible monoclonal organ injury. Abnormal free light chains with heavy proteinuria raise concern but do not prove the clone caused the renal lesion. Confirm with immunofixation and appropriate tissue examination, including reliable amyloid typing when amyloid is found; disease-directed treatment follows the established lesion.
SLiM Criteria Assessment
The involved/uninvolved FLC ratio criterion for a myeloma-defining biomarker event requires ≥100 (kappa direction). This patient's ratio of 5.37 does not meet that threshold. This does not diminish the urgency of evaluation; MGRS-class disease causes dialysis-driving renal failure from clones that by definition do not qualify as myeloma.
5. Cardiac Evaluation -- Confirmed Advanced Involvement
5.1 Biomarker Staging
| Measured finding | Value | Interpretation |
|---|---|---|
| BNP | 4,598 pg/mL | Markedly elevated; not numerically interchangeable with NT-proBNP |
| High-sensitivity troponin I | 59 ng/L | Interpret with the exact assay and validated staging system |
| Formal cardiac stage | Not established here | Confirm diagnosis and required biomarkers before assigning a stage |
The reported BNP and high-sensitivity troponin I indicate a concerning cardiac phenotype but are not interchangeable with the NT-proBNP and specified troponin assays of another staging system. Confirm amyloid diagnosis and apply a validated assay-specific scheme before assigning a stage or stage-based prognosis. CKD also affects biomarker interpretation.
5.2 Echocardiographic Reinterpretation
The echocardiogram showing EF 45%, LVH, and impaired relaxation was initially framed as hypertensive heart disease. The biomarker and hemodynamic findings warrant reassessment for infiltrative and other causes; a formal stage remains unconfirmed:
- EF 45% in cardiac amyloidosis does not represent mild systolic dysfunction -- it represents the transition point where systolic reserve is becoming exhausted
- "LVH" in amyloidosis is infiltrative pseudohypertrophy -- amyloid fibrils depositing in the myocardial interstitium, not true myocyte hypertrophy
- The echo should be re-read with a dedicated amyloid protocol including global longitudinal strain (GLS) with apical sparing pattern
Warning
A patient with suspected cardiac amyloidosis and EF 45% has already lost significant systolic reserve. Standard heart failure medications that reduce preload (aggressive diuretics), afterload (ACEi, ARBs), or heart rate (beta-blockers, non-DHP CCBs) may be poorly tolerated or harmful. Cardiology co-management with amyloid expertise is required.
6. Renal Staging (Palladini 2014 System)
| Risk Factor | Patient Status |
|---|---|
| eGFR <50 mL/min/1.73m2 | YES -- Cr 4.0, eGFR estimated 15-20 mL/min |
| Proteinuria >5 g/day | YES -- Protein/Cr 7.9, consistent with >15-20 g/day |
| Renal Stage | Stage III (both adverse criteria present) |
If AL amyloidosis is confirmed, cardiac and renal risk must be staged separately using each system’s required measurements. Patients with Palladini Renal Stage III have a 60-85% probability of requiring dialysis within 3 years.
Clinical Pearl
The 5-year cumulative incidence of renal replacement therapy for Stage III patients approaches 51%. This does not mean dialysis is inevitable -- rapid and deep hematologic response to Dara-VCd can halt amyloid production and allow gradual clearance of fibril deposits. However, the window for meaningful renal recovery is time-dependent and narrows with further injury.
7. The Diuresis Problem -- Cardiorenal Physiology of Amyloidosis
Why Diuresis Failed
Creatinine rising from 2.5 to 4.0 during aggressive loop diuretic therapy with minimal fluid removal is the pathognomonic hemodynamic signature of advanced cardiorenal amyloidosis:
- Oncotic failure: With albumin at 3.1 g/dL, plasma oncotic pressure is insufficient to draw interstitial edema fluid back into the intravascular compartment
- Stiff ventricle dependence on preload: The amyloid-infiltrated LV requires elevated filling pressures to maintain stroke volume; diuresis drops cardiac output, reducing renal perfusion
- Tubular light chain toxicity: Loop diuretics concentrate tubular fluid, potentially increasing tubular light chain concentration and promoting Tamm-Horsfall protein binding
Warning: Screen for Factor X Deficiency
Systemic AL amyloid fibrils adsorb and sequester clotting Factor X, producing an acquired Factor X deficiency in up to 14% of AL amyloidosis patients. A Factor X activity level should be sent before kidney biopsy or right heart catheterization.
8. Tissue Diagnosis -- Required, Not Optional
Kidney biopsy is necessary to differentiate between entities with identical laboratory profiles but distinct pathology:
| Finding | AL Amyloidosis | LCDD |
|---|---|---|
| Congo red stain | Positive -- apple-green birefringence | Negative |
| Electron microscopy | Fibrils 8-12 nm, randomly arranged | Non-fibrillar, organized, granular deposits |
| Immunofluorescence | Restricted light chain (Congo red confirms fibril) | Linear kappa or lambda staining along GBM |
| Mass spectrometry amyloid typing | Required -- confirms AL vs. AA vs. ATTR | N/A |
| Treatment implication | Dara-VCd | Clone-directed therapy (similar but biopsy defines urgency) |
Abdominal fat pad biopsy is a less invasive alternative with approximately 60-80% sensitivity for systemic AL amyloidosis. Bone marrow biopsy is required for clone characterization, cytogenetics, and assessment of plasma cell percentage.
9. Treatment Framework
Standard of Care: Dara-VCd
The ANDROMEDA phase 3 trial established Dara-VCd as the first FDA-approved therapy for newly diagnosed AL amyloidosis. In 388 patients, daratumumab addition to VCd resulted in a hematologic complete response rate of 53.3% versus 18.1% with significantly superior survival free from major organ deterioration.
Key ANDROMEDA Eligibility Nuances for This Patient
- Patients with cardiac Stage IIIB (NT-proBNP >8,500 ng/L) were excluded -- this patient's NT-proBNP equivalent needs verification
- eGFR ≥20 mL/min was required -- this patient's current eGFR is borderline
- Symptomatic multiple myeloma (meeting CRAB criteria) was an exclusion
These nuances underscore why a hematologist with specific AL amyloidosis expertise -- not general oncology -- is required for treatment planning.
Three Pillars of Outcome Improvement
The Three Pillars
- Early disease recognition before advanced organ damage -- partially failed here (delayed diagnosis with Cr already 4.0 and concerning cardiac involvement)
- Rapid and deep hematologic response -- the dominant modifiable variable going forward
- Comprehensive multi-specialty supportive care -- cardiology, nephrology, hematology working in parallel, not sequentially
Supportive Care Considerations
- Diuresis: Hold or dramatically reduce; if volume management is mandatory, consider ultrafiltration after RHC-guided hemodynamic assessment
- Albumin infusions: Physiologically intuitive but not proven to improve outcomes; may precipitate pulmonary edema -- use with caution
- Avoid: ACE inhibitors, ARBs, beta-blockers, non-DHP calcium channel blockers
- Coagulopathy surveillance: Factor X level, CBC, INR before procedures
- Renal support: If creatinine continues to rise, early renal replacement therapy planning should begin
10. Priority Diagnostic and Management Checklist
Immediate (Within 24 Hours)
- Hematology/oncology consultation -- amyloid-experienced center preferred
- Cardiology consultation with dedicated amyloid echo re-read (GLS, strain imaging)
- NT-proBNP to complement BNP (define IIIA vs. IIIB status)
- Factor X activity level (pre-procedure coagulopathy screen)
- Serum immunofixation + urine immunofixation (characterize M-protein isotype)
- 24-hour urine protein (formal Palladini renal staging)
- Alkaline phosphatase (hepatic amyloid screening)
Within 48-72 Hours
- Bone marrow biopsy (clone characterization, cytogenetics, plasma cell percentage)
- Kidney biopsy (or fat pad biopsy as interim)
- RHC consideration (hemodynamic-guided volume management)
- Echocardiogram with dedicated amyloid protocol including GLS
- Nerve conduction study if neuropathic symptoms present
- Consider cardiac MRI if echocardiogram is technically limited
11. Summary
This case represents systemic AL amyloidosis (or LCDD -- tissue biopsy will distinguish) with confirmed multi-organ involvement. The key diagnostic milestones and their clinical implications:
- The proteinuria phenotype (albumin/Cr >4, protein/Cr 7.9, hypoalbuminemia, 3+ edema) established glomerular disease and excluded cast nephropathy as the primary lesion
- The kappa FLC of 174 mg/L with ratio 5.37 above the renal-adjusted reference range confirmed a clonal kappa-dominant plasma cell dyscrasia
- The albumin-rich proteinuria, abnormal free-light-chain ratio, kidney decline, and severe cardiac findings warrant urgent coordinated evaluation. They do not by themselves establish amyloid type or a validated Mayo cardiac stage. Complete serum/urine immunofixation, tissue diagnosis and typing when indicated, and the exact biomarkers required for the selected staging system. Manage congestion and perfusion while hematology, cardiology, and nephrology clarify the cause.
- The combination of absent CRAB features with glomerular nephrotic syndrome and a small-to-moderate kappa clone makes LCDD the leading tissue diagnosis, with kappa AL amyloidosis as a close alternative -- only the kidney biopsy resolves this
- The diuresis failure reflects the hemodynamic paradox of the amyloid cardiorenal phenotype: simultaneous total body volume overload and intravascular depletion from oncotic failure and a stiff, preload-dependent ventricle
- Multidisciplinary emergent care coordination is the clinical priority
References
- Dispenzieri A, Kyle RA, Katzmann JA, et al. Immunoglobulin free light chain ratio is an independent risk factor for progression of smoldering multiple myeloma. Blood. 2008;111(2):785-789. PubMed
- Hutchison CA, Plant T, Drayson M, et al. Serum free light chain measurement aids the diagnosis of myeloma in patients with severe renal failure. BMC Nephrol. 2008;9:11. PubMed
- Dispenzieri A, Gertz MA, Kyle RA, et al. Serum cardiac troponins and N-terminal pro-brain natriuretic peptide: a staging system for primary systemic amyloidosis. J Clin Oncol. 2004;22(18):3751-3757. PubMed
- Palladini G, Hegenbart U, Milani P, et al. A staging system for renal outcome and early markers of renal response to chemotherapy in AL amyloidosis. Blood. 2014;124(15):2325-2332. PubMed
- Kastritis E, Palladini G, Minnema MC, et al. Daratumumab-based treatment for immunoglobulin light-chain amyloidosis. N Engl J Med. 2021;385(1):46-58. PubMed
- Leung N, Bridoux F, Batuman V, et al. The evaluation of monoclonal gammopathy of renal significance: a consensus report. Nat Rev Nephrol. 2019;15(1):45-59. PubMed
- Rajkumar SV, Dimopoulos MA, Palumbo A, et al. International Myeloma Working Group updated criteria for the diagnosis of multiple myeloma. Lancet Oncol. 2014;15(12):e538-e548. PubMed
- Lilleness B, Ruberg FL, Mussinelli R, Doros G, Sanchorawala V. Development and validation of a survival staging system incorporating BNP in patients with light chain amyloidosis. Blood. 2019;133(3):215-223. PubMed
- Kumar S, Dispenzieri A, Lacy MQ, et al. Revised prognostic staging system for light chain amyloidosis. J Clin Oncol. 2012;30(9):989-995. PubMed
- Merlini G, Dispenzieri A, Sanchorawala V, et al. Systemic immunoglobulin light chain amyloidosis. Nat Rev Dis Primers. 2018;4(1):38. PubMed
Related Content
Case prepared for educational purposes. All patient identifiers have been removed.
© Urine Nephrology Now | Clinical Mastery Series
Andrew Bland, MD, FACP, FAAP