Non-Dilated Obstructive Uropathy
Visual reference
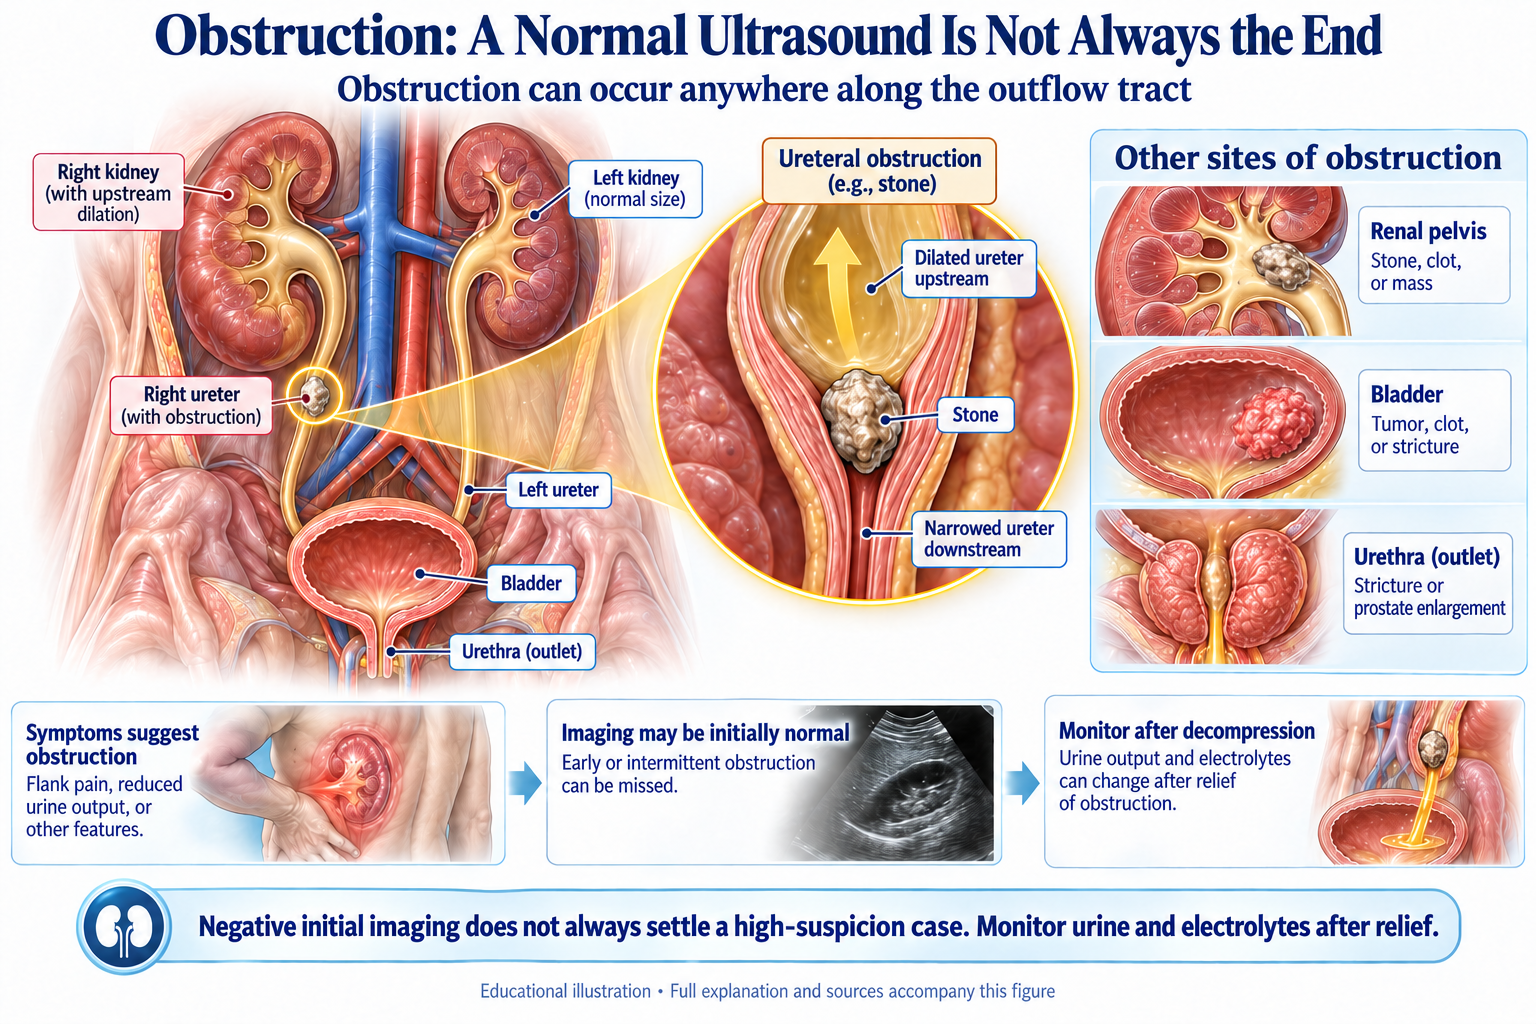
Browse the visual reference library · Download lesson Markdown
AKI Without Hydronephrosis: A Comprehensive Review
Andrew Bland, MD, FACP, FAAP
Executive Summary
- Non-dilated obstructive uropathy (NDOU) accounts for approximately 5% of urinary obstruction cases and represents a clinically underdiagnosed entity (1,2)
- Malignancy is the most common etiology (66%), followed by urolithiasis (14%) (1)
- Mean presenting creatinine is 10.5 mg/dL despite minimal or absent hydronephrosis (1)
- Absence of hydronephrosis does not exclude obstruction when clinical suspicion remains high (1,3).
- When clinical suspicion is high, proceed to definitive testing (retrograde or antegrade pyelography) regardless of imaging findings (4,5)
- The urology literature has recognized this entity since 1979, with explicit statements that it is “imperative” to exclude obstruction in high-risk patients “even in the absence of dilatation” (6,7)
1. Introduction
The clinical axiom that “obstruction causes hydronephrosis” is deeply ingrained in medical education. However, this assumption can lead to missed diagnoses and preventable harm. Non-dilated obstructive uropathy (NDOU), also termed non-dilated obstructive nephropathy (NDON), represents a clinical scenario in which severe urinary tract obstruction causes acute kidney injury without the expected finding of collecting system dilation on imaging.
This review examines the evidence base for NDOU, focusing on etiologies, pathophysiologic mechanisms, radiographic pearls, and the interdisciplinary challenges that arise when imaging appears reassuring but clinical suspicion remains high. Special attention is given to the urology literature, which has recognized this entity for over four decades but which remains underappreciated in practice.
2. Definition and Prevalence
NDOU is defined as urinary tract obstruction causing AKI with minimal or absent collecting system dilation on ultrasound or CT imaging (1). The 2024 CKJ narrative review by Feliciangeli et al. identified 49 patients across 23 published reports from 1979–2023, representing the first systematic review of this entity (1).
Prevalence estimates vary, but the most commonly cited figure is that approximately 4–5% of patients with obstructive uropathy present without hydronephrosis (6,7). Many experts believe this condition is underdiagnosed rather than uncommon; patients with unexplained AKI may never receive the definitive testing (retrograde or antegrade pyelography) needed to confirm the diagnosis.
3. Clinical Presentation
The typical NDOU patient presents with the following features (1):
| Feature | Finding |
|---|---|
| Mean age | 59 years |
| Gender | 80% male |
| Mean presenting creatinine | 10.5 mg/dL |
| Oliguria/anuria | 82% |
| Abdominal pain | 24.5% |
| Volume overload (edema, effusions) | 16% |
| Nausea/vomiting | 18% |
Clinical Pearl: The severity of AKI in NDOU is often striking. Mean presenting creatinine of 10.5 mg/dL indicates advanced renal failure at presentation, emphasizing the importance of maintaining clinical suspicion even when imaging appears reassuring (1).
4. Etiologies
Malignancy is the dominant etiology, accounting for 66% of NDOU cases. The following table summarizes the etiologic distribution (1):
| Etiology | Percentage |
|---|---|
| Malignancy (total) | 66% |
| - Prostate cancer | 20% |
| - Bladder cancer | 18% |
| - Colorectal cancer | 10% |
| - Lymphoma | 8% |
| - Breast cancer | 4% |
| - Uterine cancer | 4% |
| - Pancreatic cancer | 2% |
| Urolithiasis | 14% |
| Retroperitoneal fibrosis | 12% |
| Iatrogenic/traumatic | 8% |
⚠️ Warning: Malignancy is the most common cause of NDOU. Any patient with a history of pelvic malignancy who presents with unexplained AKI should be considered at high risk, regardless of imaging findings (6,7).
5. Pathophysiologic Mechanisms
Several mechanisms explain why obstruction can occur without dilation:
5.1 Encasement Without Compression
Malignant infiltration can encase the ureters, preventing both urine flow and ureteral dilation. The surrounding tumor mass creates a rigid environment that restricts collecting system expansion even as obstruction develops (1,8).
5.2 Acute Obstruction
Hydronephrosis requires time to develop. In acute complete obstruction, early imaging may precede visible dilation (1,3).
5.3 Volume Depletion
Patients with significant intravascular volume depletion produce less urine, limiting the distending pressure needed to cause hydronephrosis (1,5).
5.4 Reduced Baseline GFR
Patients with pre-existing CKD or severely reduced GFR from any cause produce less urine and are therefore less likely to develop detectable hydronephrosis (1,5).
6. Radiographic Pearls: Beyond Presence or Absence of Hydronephrosis
Understanding the imaging nuances in NDOU can mean the difference between diagnosis and missed opportunity. This section provides practical guidance for interpreting imaging studies when clinical suspicion for obstruction remains high despite apparent absence of hydronephrosis.
6.1 Ultrasound Limitations and Pitfalls
Renal ultrasound remains the first-line imaging modality for evaluating AKI, but its limitations in detecting obstruction are well-documented:
| Parameter | Value |
|---|---|
| Overall sensitivity for hydronephrosis | 77–98% |
| False-negative rate for obstruction | Up to 35% |
| Point-of-care ultrasound sensitivity | 77–93% |
| Point-of-care ultrasound specificity | 72–88% |
Causes of false-negative ultrasound include: early acute obstruction, significant volume depletion reducing urine output, encasement by tumor or fibrosis preventing dilation, reduced baseline GFR limiting urine production, and operator or technical factors in bedside imaging (1,3,9).
6.2 Renal Resistive Index
Doppler ultrasound can provide functional information beyond anatomic assessment. The renal resistive index (RI) is calculated as (peak systolic velocity – end diastolic velocity) / peak systolic velocity.
| RI Value | Interpretation |
|---|---|
| < 0.70 | Normal |
| 0.70–0.80 | Indeterminate (may suggest early obstruction) |
| > 0.80 | Elevated (concerning for obstruction) |
The resistive index is influenced by age, vascular properties, systemic hemodynamics and intrinsic kidney disease. It may contribute to assessment but cannot independently establish or exclude obstruction (10,11,12,13).
Clinical Pearl: An elevated RI (>0.70) in the setting of clinical suspicion for obstruction but absent hydronephrosis should prompt further investigation. However, a normal RI does not exclude obstruction, and the test has significant limitations (10,11,12,13).
6.3 CT Secondary Signs
When hydronephrosis is absent, CT may demonstrate secondary signs of obstruction:
- Dense nephrogram: Increased parenchymal enhancement persisting into delayed phases
- Delayed pyelogram: Contrast excretion delayed relative to the contralateral kidney
- Perinephric stranding: Fat stranding around the kidney suggesting acute process
- Pyelosinus extravasation: Forniceal rupture from high collecting system pressure
The combination of dense nephrogram with delayed pyelogram was first described by Harrison et al. in 1979 as a marker of obstruction even when collecting system dilation is minimal (8).
⚠️ Warning: The combination of dense nephrogram with delayed pyelogram should raise suspicion for obstruction regardless of the appearance of the collecting systems (8).
7. The Urology Challenge: Landmark Publications and Literature Quality Analysis
When clinical and imaging findings disagree, discuss the diagnostic uncertainty directly among nephrology, urology and radiology. Case reports show that obstruction can be missed without dilation; procedural decisions should weigh the complete clinical picture and risks (14,15).
7.1 Landmark Urology Publications
Spital et al., 1988: Four cases illustrated severe obstruction despite minimal or absent dilation on noninvasive imaging, with improvement after relief (2).
Kocurek et al., 1991: The review emphasizes possible obstruction without dilation in patients with pelvic malignancy (6).
Spital, 2020: An editorial highlights continuing underrecognition; it is not a diagnostic-accuracy study (7).
Harrison et al., 1979: A case of tumor-encased ureters illustrates a delayed pyelogram and dense nephrogram despite minimal dilation (8).
7.2 Literature Quality Analysis
The evidence base for NDOU consists primarily of case reports and small case series. The 2024 CKJ systematic review by Feliciangeli et al. represents the most comprehensive analysis to date, identifying only 49 patients across 23 publications over 44 years (1). Several limitations affect the literature:
- Publication bias: Cases are reported because they are unexpected; the true denominator of missed diagnoses is unknown
- Confirmation bias: Diagnosed cases require definitive testing; patients who never receive retrograde/antegrade pyelography cannot be counted
- Inconsistent definitions: Some studies define NDOU as “no hydronephrosis” while others include “minimal dilation”
- Heterogeneous populations: Case series mix malignancy, stones, and retroperitoneal fibrosis with different pathophysiology
Despite these limitations, the consistency of the phenomenon across decades, institutions, and etiologies supports the validity of NDOU as a clinical entity. The publication of case series in urology journals by urologists provides internal validation from the specialty most equipped to evaluate urinary tract obstruction.
7.3 Documented Urology Skepticism: Case Examples from the Literature
The literature contains explicit documentation of urology declining intervention despite clinical suspicion for NDOU:
Onuigbo et al. (2010): Three patients with severe AKI and absent or limited collecting-system dilation recovered kidney function after decompression. This small case series supports retaining obstruction in the differential despite reassuring imaging; it does not establish a universal intervention rule (14).
El-Alali et al. (2022): A case report described anuric AKI from malignant retroperitoneal fibrosis as a presentation of metastatic breast cancer, with little initial evidence of obstruction on renal imaging (15).
Clinical coordination: Discuss persistent concern promptly with urology and interventional radiology. Select further imaging or decompression collaboratively, considering severity, likely obstruction site, infection and procedural risk (14).
7.4 Understanding Urology Skepticism
Urology skepticism is understandable from a training perspective. Urologists are surgical specialists whose entire approach to obstruction is predicated on identifying a problem amenable to procedural intervention. Hydronephrosis serves as the “target” that justifies intervention. When that target is absent, the indication for invasive procedures becomes less clear.
Furthermore, retrograde pyelography and cystoscopy are not without risk: anesthesia, instrumentation trauma, infection, and ureteral perforation are all potential complications. Proceeding to these procedures without imaging evidence of obstruction requires confidence in clinical judgment over objective findings—a difficult position for any specialist.
The solution is not to criticize urology colleagues but to provide them with the clinical context and literature support needed to make an informed decision. Citing the urology literature directly demonstrates that the request is grounded in evidence from their own specialty.
When obstruction remains plausible despite absent hydronephrosis, communicate the risk factors, AKI course, prior imaging, and reason for concern to urology. Nondilated obstruction is described in the literature, particularly in selected high-risk settings; a negative ultrasound is not an absolute exclusion. The need for further imaging or invasive evaluation should be determined with the treating specialists rather than from a universal prevalence estimate.
8. Chronic Bladder Outlet Obstruction: The High PVR Without Hydronephrosis Scenario
A distinct clinical scenario deserves separate consideration: the patient with chronic bladder outlet obstruction (typically from BPH), markedly elevated post-void residual (PVR) volume, AKI, but no hydronephrosis on imaging. This raises the question: will bladder drainage alone improve renal function, and what is the evidence base?
8.1 Clinical Scenario
The typical patient is an elderly male with known BPH, progressive urinary symptoms, and presentation with AKI. Ultrasound demonstrates a markedly distended bladder (PVR > 500 mL or even > 1 L) but no hydronephrosis. Catheter placement drains large volumes of urine. The question arises: will renal function improve with drainage alone, or has chronic obstruction already caused irreversible injury?
8.2 Evidence Base: Limited but Supportive
Recovery after decompression depends on obstruction duration/severity, infection and pre-existing kidney disease. The prospective study by Khalaf et al. concerns unilateral obstruction with a normal opposite kidney; it should not be treated as a TURP or nondilated chronic-retention trial (17). Following relief, monitor urine output, fluid balance and electrolytes because post-obstructive diuresis can cause clinically important losses (4).
8.3 The Evidence Gap
The specific question—does renal function improve in patients with chronic retention, high PVR, AKI, and NO hydronephrosis—has not been directly addressed in prospective studies. The available evidence is largely clinical observation:
- Clinicians report improvement in creatinine after catheterization in this population, but published series specifically isolating these patients are lacking
- The pathophysiology would suggest that if the AKI is due to bladder-level obstruction impairing renal function (even without visible upper tract dilation), relief should improve function
- The absence of hydronephrosis may indicate a compliant upper tract that decompresses into the distended bladder, but this does not preclude functional obstruction
In summary, the improvement observed in these patients is supported by physiologic reasoning and clinical experience but lacks the high-quality evidence of prospective trials. Most nephrologists and urologists would agree that a trial of catheter drainage is low-risk and reasonable, but the predictive factors for recovery are not well-defined.
Clinical Pearl: In patients with chronic retention, high PVR, and AKI without hydronephrosis, a trial of bladder drainage is reasonable. Post-obstructive diuresis after catheterization requires monitoring and is not a guarantee of complete kidney recovery. However, the evidence base for this specific population is limited to clinical observation rather than prospective data (4,16,17).
9. Management Principles
9.1 Diagnostic Approach
When NDOU is suspected, the following approach is recommended:
- Assess for high-risk features: pelvic malignancy, recent stone passage, retroperitoneal process, severe unexplained oliguria/anuria
- Review imaging critically for secondary signs: perinephric stranding, dense nephrogram, delayed pyelogram, asymmetric enhancement
- Consider Doppler RI if available, recognizing its limitations
- If clinical suspicion remains high despite negative imaging, proceed to definitive testing
9.2 Definitive Testing
Options for definitive evaluation include:
- Retrograde pyelography: Performed by urology, allows direct visualization and potential intervention
- Antegrade pyelography: Performed by interventional radiology, can be combined with nephrostomy placement
- Empiric nephrostomy: In critically ill patients with high suspicion, therapeutic trial of drainage may be diagnostic
9.3 Communication Strategy
Effective interdisciplinary communication is essential. When consulting urology or IR, provide:
- Specific high-risk features present in this patient
- Summary of current renal function and trajectory
- Explicit citation of the urology literature supporting NDOU
- Clear statement of the requested intervention
⚠️ Warning: Missing the diagnosis of NDOU converts a potentially reversible cause of AKI into permanent kidney failure. When clinical suspicion is high, advocate persistently for definitive testing (4,5,14,15).
10. Conclusions
Non-dilated obstructive uropathy is a clinically important, underdiagnosed entity that challenges the assumption that obstruction requires hydronephrosis. The urology literature has recognized this phenomenon since 1979, with explicit recommendations that obstruction must be excluded in high-risk patients “even in the absence of dilatation.”
Key takeaways for the practicing clinician include: maintaining high suspicion in patients with pelvic malignancy and unexplained AKI; recognizing the limitations of ultrasound and CT in excluding obstruction; identifying secondary radiographic signs such as dense nephrogram with delayed pyelogram; advocating persistently for definitive testing when clinical suspicion remains high; and citing the urology literature directly when consulting colleagues to facilitate appropriate evaluation.
The diagnosis of NDOU requires close collaboration between nephrology, urology, and interventional radiology. When the clinical picture suggests obstruction but imaging does not, the clinician must prioritize the patient over the picture.
References
Feliciangeli V, Noce A, Montalto G, et al. Non-dilated obstructive nephropathy. Clin Kidney J. 2024. PubMed PMID 39391590
Spital A, Valvo JR, Segal AJ. Nondilated obstructive uropathy. Urology. 1988. PubMed PMID 3287742
Faubel S, Patel NU, Lockhart ME, et al. Renal relevant radiology: use of ultrasonography in patients with AKI. Clin J Am Soc Nephrol. 2014. PubMed PMID 24235286
Yaxley J, Yaxley W. Obstructive uropathy - acute and chronic medical management. World J Nephrol. 2023. PubMed PMID 36704657
Pérez-Aizpurua X, Cabello Benavente R, Bueno Serrano G, et al. Obstructive uropathy: Overview of the pathogenesis, etiology and management of a prevalent cause of acute kidney injury. World J Nephrol. 2024. PubMed PMID 38983763
Kocurek JN, Orihuela E, Saltzstein DR. Nondilated obstructive uropathy and renal failure as a result of carcinoma of the intrapelvic area. Surg Gynecol Obstet. 1991. PubMed PMID 1948605
Spital A. Nondilated Obstructive Uropathy - Still Underappreciated. Urology. 2020. PubMed PMID 32504684
Harrison RB, Widner LA, Johnstone WH, et al. Subtle obstructive uropathy resulting from encasement of the ureters by tumor. J Urol. 1979. PubMed PMID 583167
Sasipattarapong P, Omer T, Sajed D, et al. Point-of-care renal ultrasound: Are longitudinal views of the kidney alone sufficient to rule out hydronephrosis? J Am Coll Emerg Physicians Open. 2022. PubMed PMID 35978655
Tublin ME, Bude RO, Platt JF. Review. The resistive index in renal Doppler sonography: where do we stand? AJR Am J Roentgenol. 2003. PubMed PMID 12646425
Miletić D, Fuckar Z, Sustić A, et al. Resistance and pulsatility indices in acute renal obstruction. J Clin Ultrasound. 1998. PubMed PMID 9460635
Granata A, Zanoli L, Clementi S, et al. Resistive intrarenal index: myth or reality? Br J Radiol. 2014. PubMed PMID 24734937
Shokeir AA, Abdulmaaboud M. Resistive index in renal colic: a prospective study. BJU Int. 1999. PubMed PMID 10210556
Onuigbo MA, Lawrence K, Onuigbo NT. Non-dilated obstructive uropathy - an unrecognized cause of acute renal failure in hospitalized US patients: three case reports seen over 6 months in a northwestern Wisconsin nephrology practice. Ren Fail. 2010. PubMed PMID 20954986
El-Alali E, Moreno C, Al Jaber E. Thinking Beyond Acute Kidney Injury. Case Rep Nephrol Dial. 2022. PubMed PMID 35433843
Kaplan SA, Wein AJ, Staskin DR, et al. Urinary retention and post-void residual urine in men: separating truth from tradition. J Urol. 2008. PubMed PMID 18485378
Khalaf IM, Shokeir AA, El-Gyoushi FI, et al. Recoverability of renal function after treatment of adult patients with unilateral obstructive uropathy and normal contralateral kidney: a prospective study. Urology. 2004. PubMed PMID 15491695
Document prepared for educational purposes. Last updated: January 2026.
Educational Resources
- Student Guide: Daptomycin Aki Review — PA/medical student educational guide
- Student Guide: Aki Workup Summary — PA/medical student educational guide
- Student Guide: Diagnosis Of Acute Kidney Injury Biomarkers — PA/medical student educational guide
- Student Guide: Well Water Contamination, Diarrhea And Aki — PA/medical student educational guide
- Student Guide: Appendix E Pain Management Deep Dive — PA/medical student educational guide