Chapter 9: ATN & Loop Diuretics
Urine Nephrology Now: A Primer for Students in Nephrology
📖 Ready for a Deeper Dive?
Explore these related Lecture Series modules and Clinical Mastery reviews:
Visual reference
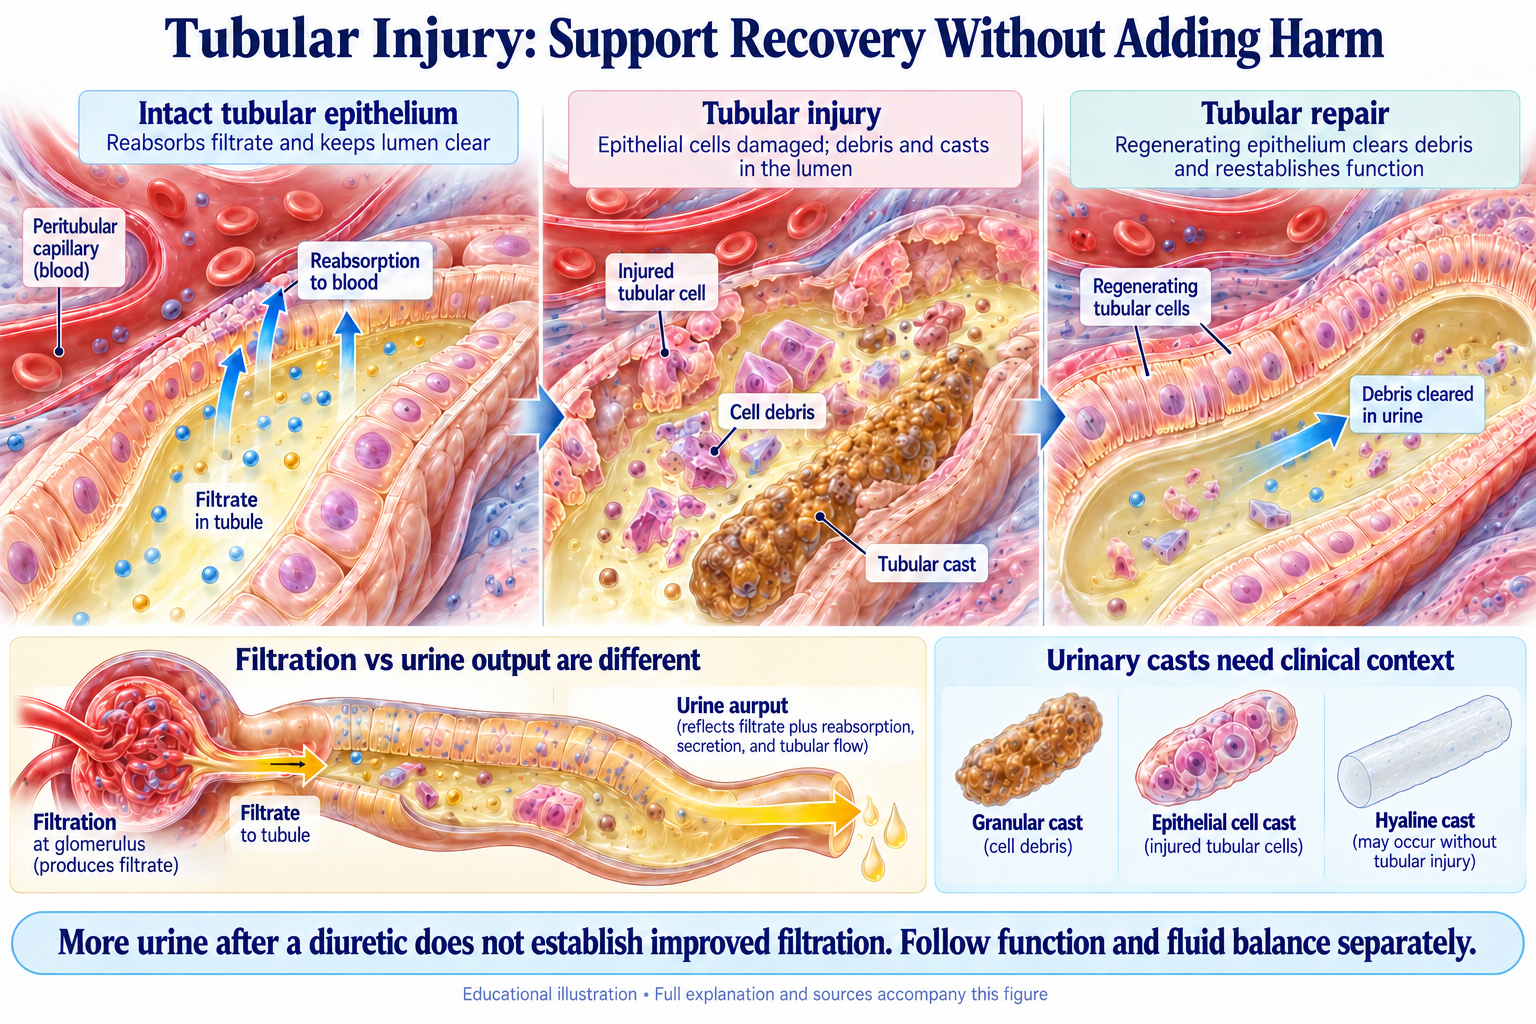
Browse the visual reference library · Download lesson Markdown
Introduction
Acute tubular necrosis represents the most common cause of intrinsic acute kidney injury in hospitalized patients and is associated with significant morbidity and mortality. Loop diuretics have been employed in this clinical setting based on theoretical benefits derived from their mechanism of action, which includes inhibition of the sodium-potassium-chloride cotransporter in the thick ascending limb of Henle, resulting in reduced cellular energy demands and increased tubular flow.
Theoretical Foundation and Mechanisms of Action
Cytoprotective Mechanisms
Loop diuretics theoretically provide renal protection through several interconnected mechanisms. These agents decrease the metabolic demand of renal tubular cells by reducing their oxygen requirement, potentially increasing resistance to ischemia and other toxic insults. The inhibition of active sodium transport in the thick ascending limb of Henle reduces adenosine triphosphate utilization, thereby decreasing the net oxygen consumption of the kidney.
Hemodynamic and Tubular Flow Effects
Enhanced tubular flow represents another theoretical benefit. Greater urine flow may reduce the incidence of tubular obstruction and higher hydraulic pressures may reduce the back-leak of glomerular filtrate. Loop diuretics may also improve renal blood flow through vasodilatory effects, potentially enhancing oxygen delivery to vulnerable renal tissue.
Clinical Evidence for Treatment of Established ATN
Systematic Reviews and Meta-Analyses
Comprehensive systematic reviews have consistently demonstrated the lack of clinical benefit from loop diuretics in established ATN. A major meta-analysis found that furosemide had no impact on mortality or the need for renal replacement therapy. While diuretic treatment may convert oliguric ATN to non-oliguric ATN, it does not appear to alter the course of acute renal failure.
Safety Considerations
The administration of loop diuretics in ATN carries significant risks. Adverse events include electrolyte abnormalities (hypokalemia, hyponatremia), volume depletion, and potential ototoxicity with high-dose administration. The same diuretic that might improve renal function in fluid-overloaded patients may have detrimental effects on kidney perfusion if a patient becomes volume-depleted.
The Furosemide Stress Test (FST) as a Diagnostic Tool
Development and Standardization
The FST has emerged as a validated functional assessment tool for predicting AKI progression. The standardized protocol involves administration of 1.0 mg/kg furosemide for loop diuretic-naive patients (or 1.5 mg/kg for prior exposure). Urine output is then measured, with the two-hour output being the key predictor.
Diagnostic Performance
A prediction meta-analysis reported pooled sensitivity of 0.81 and specificity of 0.88 for AKI progression. Less than 200 mL in two hours was a studied threshold in selected early-AKI cohorts, not a universal dialysis trigger. Performance depends on patient selection and protocol. Prediction review.
Clinical Applications
The FST can provide prognostic information in selected, appropriately resuscitated and monitored patients. It does not independently determine when to start or stop RRT. Clinical indications and the complete trajectory remain decisive; urgent treatment should not be delayed for testing. FST pilot trial; CRRT-discontinuation cohort.
Early Intervention and Prevention Protocols
The RenalGuard System: Technological Innovation
The RenalGuard System is a closed-loop device designed to achieve high urine output through forced diuresis while maintaining euvolemia by automatically matching intravenous hydration with urine output. The rationale is to reduce contrast-induced AKI by lowering contrast concentration and transit time in the kidneys.
Clinical Evidence for RenalGuard
Initial meta-analyses showed significant reduction in contrast-induced nephropathy, major adverse events, and need for RRT. However, more recent large-scale trials (e.g., the STRENGTH study) have shown mixed results, with no significant difference in CI-AKI incidence compared to control groups.
Current Guidelines and Recommendations
KDIGO Guideline Summary
The published KDIGO 2012 guideline advises against using diuretics to prevent AKI and against treating AKI with diuretics except for volume overload. The KDIGO 2026 AKI/AKD public-review draft proposes selected FST risk assessment and an initial diuretic approach to volume overload when there is no other RRT indication; it is not final guidance. Increasing urine output alone does not establish recovery.