Chapter 20: Prevention of Recurrent UTIs
Urine Nephrology Now: A Primer for Students in Nephrology
📖 Ready for a Deeper Dive?
Explore these related Lecture Series modules and Clinical Mastery reviews:
Visual reference
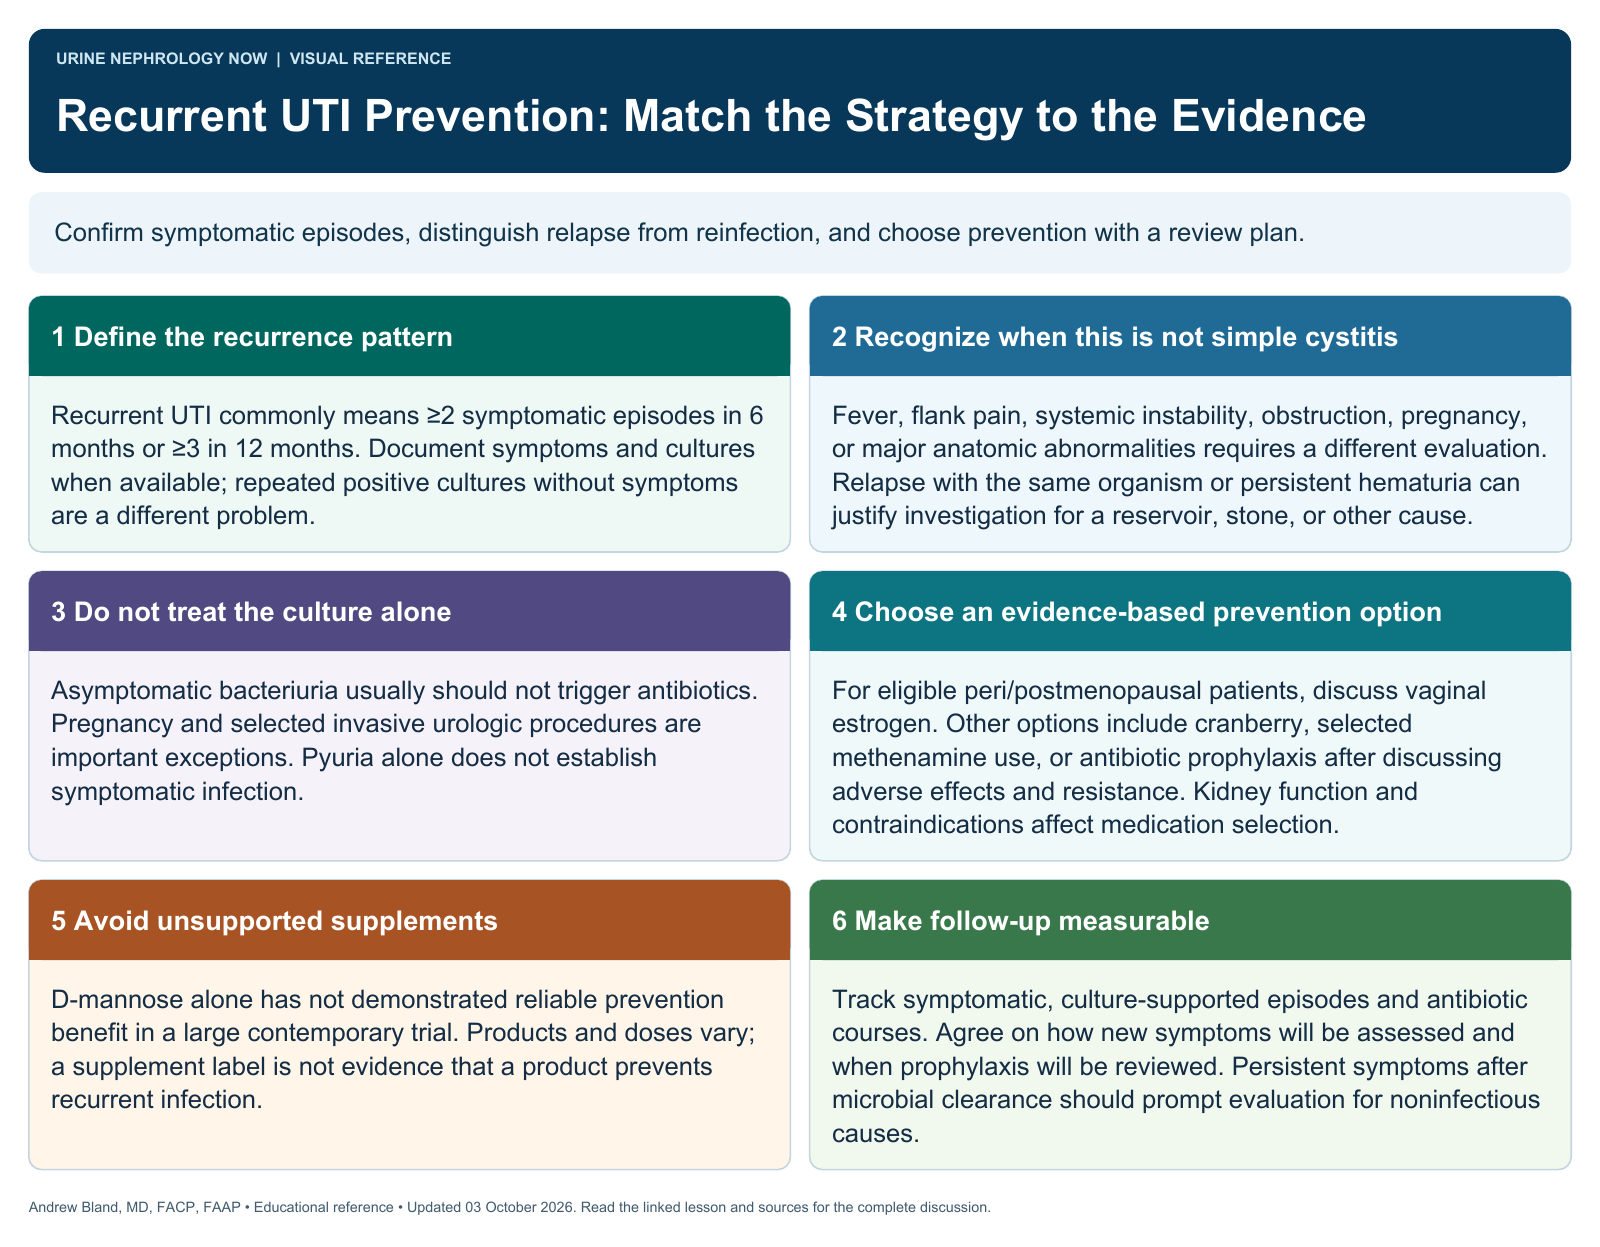
Browse the visual reference library · Download lesson Markdown
Chapter 20: Prevention of Recurrent UTIs
Recurrent UTIs (≥3 in 12 months or ≥2 in 6 months) are a significant health burden. Concerns about antibiotic resistance have increased interest in non-antibiotic preventive strategies. This section analyzes the evidence for three common options: vaginal estrogen, cranberry supplements, and D-mannose.
Vaginal Estrogen for Postmenopausal Women
Mechanism of Action
Vaginal estrogen restores normal vaginal flora (Lactobacilli), normalizes vaginal pH to be more acidic, reduces colonization by uropathogens, and improves tissue integrity. It is a key non-antibiotic option for postmenopausal women.
Clinical Evidence
Multiple high-quality randomized controlled trials (RCTs) and systematic reviews have demonstrated that vaginal estrogen (cream, ring, or tablet) significantly reduces UTI recurrence in postmenopausal women, with risk reductions of 50-60%. The American Urological Association (AUA) guidelines give this a moderate recommendation (Grade B evidence). It is considered a first-line non-antibiotic preventive strategy in this population.
Cranberry Supplements
Mechanism of Action
Cranberries contain A-type proanthocyanidins (PACs) that inhibit the adherence of E. coli to bladder epithelial cells, preventing infection.
Clinical Evidence
A 2023 Cochrane Review update, including 50 studies and over 8,800 participants, found that cranberry products reduced the risk of UTIs by about 30% with moderate certainty evidence. The benefit appears most consistent in women with recurrent UTIs, children, and people susceptible to UTIs following interventions. Evidence suggests juice may be more effective than capsules, but product formulation and PAC content vary widely, making recommendations difficult.
D-Mannose
Mechanism of Action
D-mannose is a simple sugar that theoretically binds to E. coli, preventing the bacteria from attaching to the bladder wall.
Clinical Evidence
Recent High-Quality Trial Shows No Benefit
The 2024 Hayward et al. trial in JAMA Internal Medicine randomized 598 women with recurrent UTIs. A medically attended UTI occurred in 51.0% of the D-mannose group and 55.7% of the placebo group over six months, without a statistically significant difference.
Conclusion: Based on the highest quality current evidence, D-mannose should not be recommended for preventing recurrent UTIs in women in primary care.
Evidence-Based Recommendations
| Population | First-Line Recommendation | Alternative/Adjunct | Not Recommended |
|---|---|---|---|
| Postmenopausal Women | Vaginal Estrogen | Cranberry Products | D-Mannose |
| Premenopausal Women | Cranberry Products | Discuss evidence-supported prevention according to menopausal status, recurrence pattern, cultures and preferences; D-mannose did not prevent medically attended recurrence in the 2024 placebo-controlled primary-care trial. | N/A |