Visual reference
Browse the visual reference library · Download lesson Markdown
Learning objectives
Connect a monoclonal immunoglobulin to a pattern of kidney injury. Distinguish an incidental monoclonal gammopathy from monoclonal gammopathy of renal significance (MGRS), recognize urgent myeloma-related AKI, and explain why tissue evaluation and hematologic assessment answer different questions.
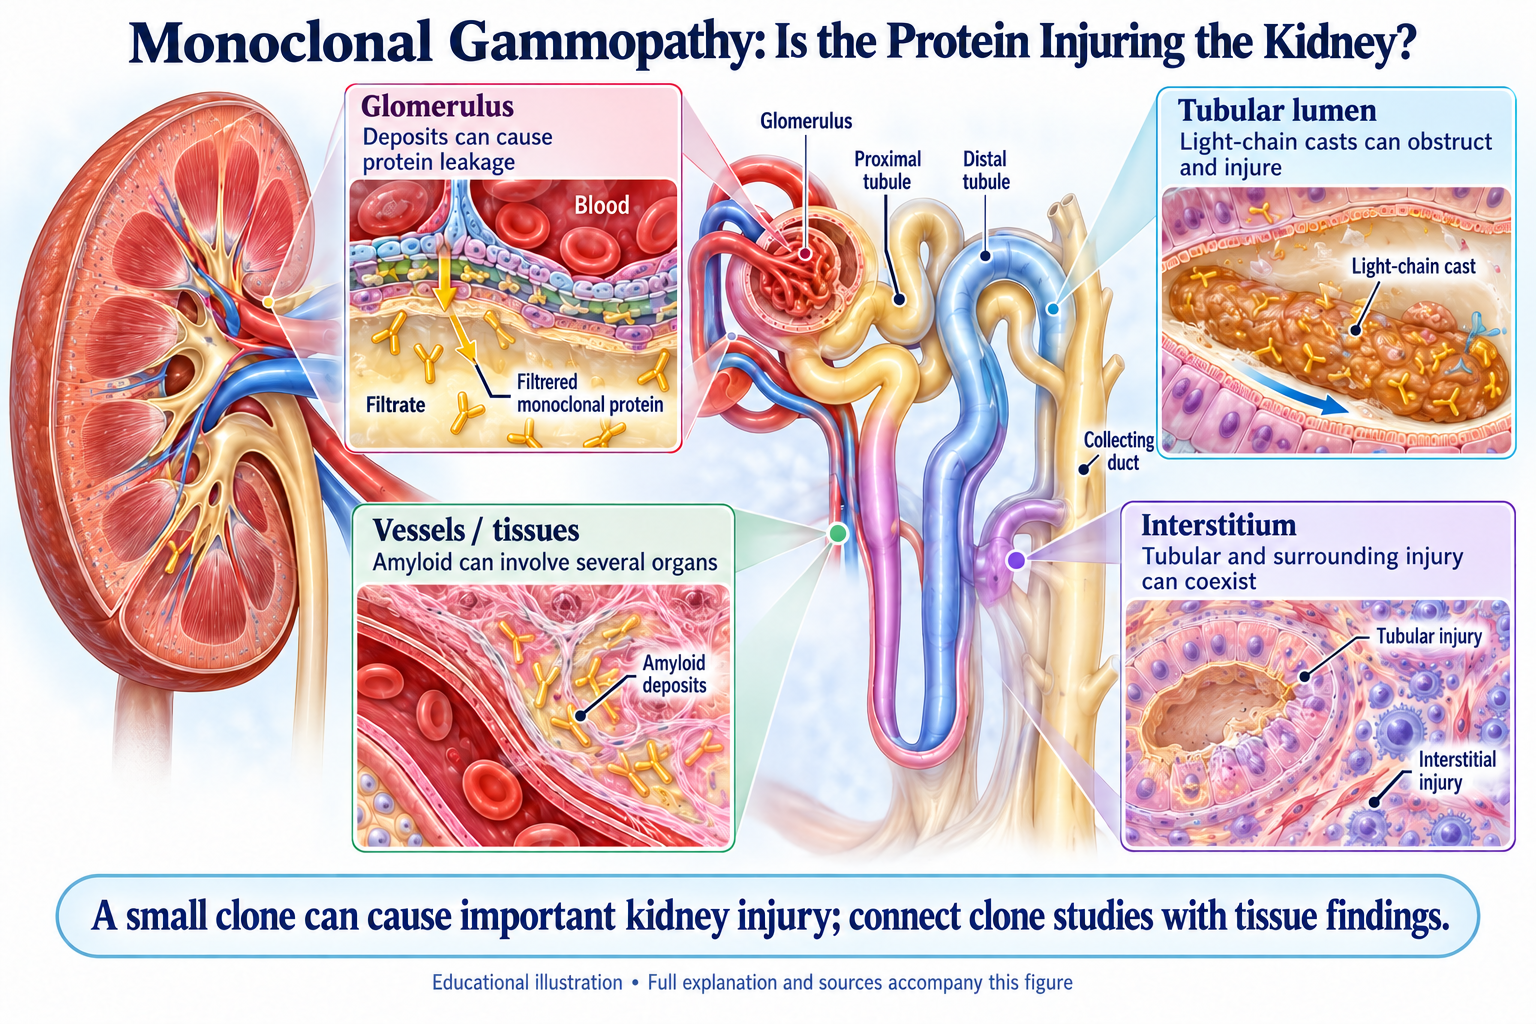
The central question is whether the protein produced by a clone is injuring the kidney. A small clone can make a nephrotoxic protein, while a monoclonal protein can also coexist with unrelated diabetic, vascular, or other kidney disease [1,2].
Start with the terminology
MGUS describes a monoclonal gammopathy without the defining organ injury or hematologic features of a condition requiring treatment. MGRS describes kidney injury attributable to a nephrotoxic monoclonal immunoglobulin produced by a clone that does not otherwise meet established hematologic criteria for treatment. The renal lesion creates clinical significance. It is not defined by a universal marrow percentage or by the concentration of an M-spike alone [1,3].
Multiple myeloma is a separate hematologic diagnosis. Cast nephropathy in that setting is myeloma-related kidney disease, not a reason to call all monoclonal kidney injury MGRS. A patient with a small M-spike can still require urgent evaluation if kidney function is deteriorating [1,4].
Recognize the kidney presentation
Presentations include proteinuria or nephrotic syndrome, hematuria, declining filtration, unexplained AKI, and proximal tubular dysfunction. A discrepancy between total urinary protein and albumin can suggest a substantial nonalbumin component. Routine dipsticks chiefly detect albumin and can miss light-chain proteinuria [1,2].
Review the trajectory, urine sediment, quantified protein excretion, blood count, calcium, and clinical evidence of systemic disease. Consider alternative or concurrent causes of AKI such as infection, volume depletion, hypercalcemia, obstruction, and nephrotoxins. Do not assume that every creatinine rise in a patient with a monoclonal protein is caused by that protein.
Use complementary laboratory tests
Serum and urine electrophoresis, immunofixation, and serum free light chains provide complementary information. Immunofixation can detect a monoclonal protein not apparent as a large electrophoretic peak. Reduced kidney clearance changes free light-chain concentrations and their interpretation; use the assay and laboratory’s appropriate reference context [1,2].
A serum free light-chain ratio alone does not establish the renal pathology. Conversely, failure to identify a circulating clone does not exclude every monoclonal deposit-related lesion. Hematology may need marrow, flow cytometry, and other directed testing to identify the responsible plasma-cell or B-cell process [1,3].
Let pathology establish the renal lesion
Kidney biopsy is usually central to establishing MGRS when clinically appropriate. Light microscopy, immunofluorescence, and electron microscopy are complementary. Specialized methods, including deposit typing, may be needed. The pathologist assesses the distribution and organization of deposits, immunoglobulin restriction, associated injury, and competing diagnoses [1,2].
Interpret biopsy findings with the detected clone. A monoclonal serum protein is common enough in older adults that its presence alone cannot establish causality. Discuss biopsy benefits and procedural risks individually rather than applying a fixed proteinuria or creatinine threshold to every patient.
Compare the principal patterns
| Pattern | Useful distinction |
|---|---|
| AL amyloidosis | Amyloid fibrils require confirmation and typing; evaluate systemic organ involvement. |
| Monoclonal immunoglobulin deposition disease | Nonamyloid deposits may involve glomerular, tubular, and vascular compartments. |
| Proliferative GN with monoclonal deposits | A glomerular inflammatory pattern may occur even when a circulating clone is difficult to detect. |
| Light-chain proximal tubulopathy | May produce proximal tubular dysfunction, including Fanconi features. |
| Cast nephropathy | Light chains injure tubules; myeloma-related AKI demands rapid coordinated assessment. |
These are different lesions with different treatment implications. Fibrillary and immunotactoid patterns require careful classification; do not infer a monoclonal cause from the name or morphology alone [1-4].
Avoid the amyloid diagnostic shortcut
AL amyloidosis can involve the kidneys, heart, nerves, liver, and other organs. Proteinuria, heart-failure symptoms, orthostatic hypotension, or neuropathy can provide clues. A monoclonal protein plus cardiac imaging does not by itself type amyloid. Tissue confirmation and accurate typing are essential when AL is suspected [5,6].
Cardiac biomarkers inform validated staging systems but cannot be mixed across assays or staging versions to assign an exact individual survival time. Assess organ involvement promptly and discuss prognosis using current treatment context and specialist interpretation. A preserved ejection fraction does not exclude important cardiac involvement [5,6].
Treat the clone and protect the kidney
MGRS treatment generally aims to reduce production of the pathogenic immunoglobulin. The regimen depends on the clone, renal lesion, extra-renal disease, frailty, treatment toxicity, and patient goals. A single chemotherapy combination is not appropriate for all MGRS lesions [3].
In suspected myeloma-related AKI, coordinate urgently with hematology and nephrology. Rapid effective antimyeloma treatment is central. Correct reversible contributors and individualize fluid treatment, particularly when cardiac involvement or congestion limits tolerance. Kidney replacement therapy addresses clinical complications; it is not triggered by a free light-chain result alone [4].
Supportive care includes appropriate blood-pressure and proteinuria management, medication adjustment, avoidance of nephrotoxins, infection prevention, and monitoring for treatment complications. Mechanical light-chain removal does not replace clone-directed therapy [3,4].
Follow hematologic and organ responses separately
A falling monoclonal protein or free light-chain burden is a hematologic response. Changes in proteinuria and kidney function describe organ response and may follow a different time course. Track both, together with treatment toxicity. Persistent or recurrent clone activity can affect transplant planning and recurrence risk; use multidisciplinary assessment [1,3].
Apply the framework: synthetic teaching cases
A small M-spike with worsening proteinuria
An older adult has a small monoclonal band and new nephrotic-range proteinuria. The M-spike size does not establish that the gammopathy is harmless, and it does not prove causality. Quantify protein, assess other causes, obtain complementary monoclonal studies, and discuss kidney biopsy and hematologic evaluation [1,2].
AKI with disproportionately high nonalbumin protein
A patient with a plasma-cell disorder develops rapidly rising creatinine. Consider cast nephropathy while evaluating infection, volume status, calcium, obstruction, and drugs. Escalate promptly; avoid reflexive large fluid volumes in a congested patient. Treatment selection and any need for dialysis require the combined clinical assessment [4].
Self-check: Explain why kidney pathology, clone size, and organ response are related but distinct. Which finding establishes that an immunoglobulin is monoclonal, and which establishes that it caused this patient’s renal lesion?
References
- Leung N, Bridoux F, Batuman V, et al. The evaluation of monoclonal gammopathy of renal significance: a consensus report of the International Kidney and Monoclonal Gammopathy Research Group. Nat Rev Nephrol. 2019. PubMed 30510265
- Bridoux F, Leung N, Hutchison CA, et al. Diagnosis of monoclonal gammopathy of renal significance. Kidney Int. 2015. PubMed 25607108
- Jain A, Haynes R, Kothari J, et al. Pathophysiology and management of monoclonal gammopathy of renal significance. Blood Adv. 2019. PubMed 31409583
- Dimopoulos MA, Merlini G, Bridoux F, et al. Management of multiple myeloma-related renal impairment: recommendations from the International Myeloma Working Group. Lancet Oncol. 2023. PubMed 37414019
- Hasib Sidiqi M, Gertz MA. Immunoglobulin light chain amyloidosis diagnosis and treatment algorithm 2021. Blood Cancer J. 2021. PubMed 33993188
- Fotiou D, Dimopoulos MA, Kastritis E. Systemic AL Amyloidosis: Current Approaches to Diagnosis and Management. Hemasphere. 2020. PubMed 32885146
Continue to the hematologic kidney disease handout
Compare the kidney patterns
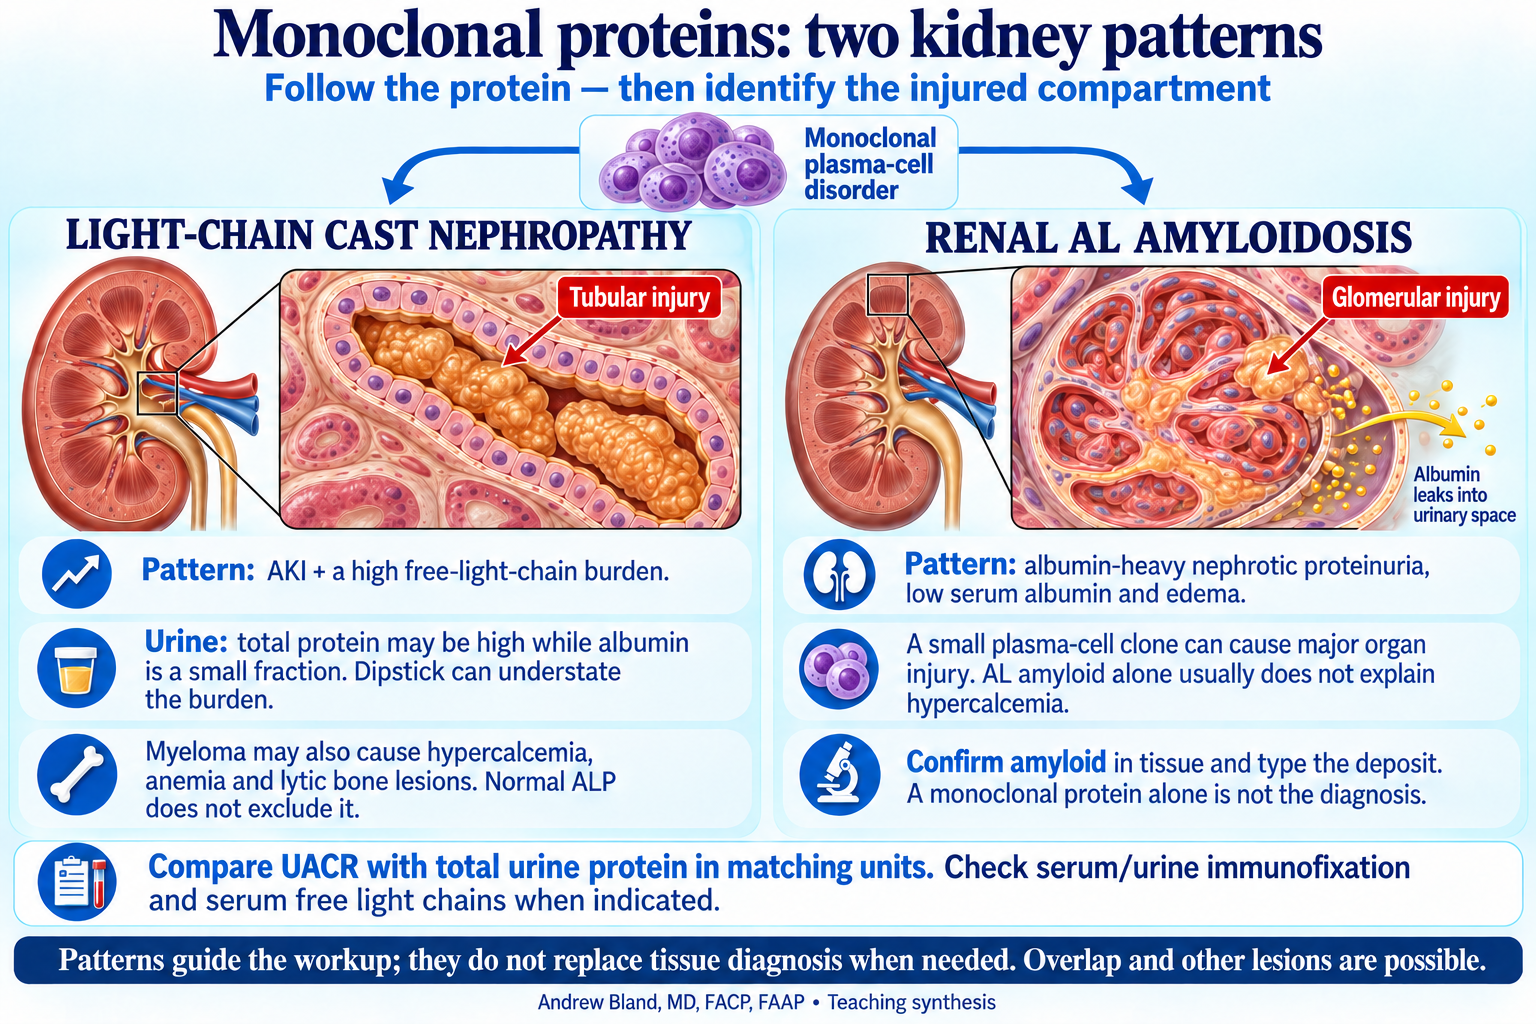
Tubular light-chain cast injury versus glomerular AL amyloid deposition.
Practice the myeloma versus AL amyloid comparison in the summary-day capstone →