Student Handout: Hematologic Malignancies & Kidney Disease
Learning objective: Understand renal complications of blood cancers, focusing on myeloma kidney, MGRS, lymphoma/leukemia effects, and stem cell transplant-related nephropathy
Visual reference
Browse the visual reference library · Download lesson Markdown
Overview
Blood cancers have unique mechanisms of causing kidney disease due to high protein production, immune dyscrasia, and treatment-related complications. This handout covers the major entities:
- Multiple Myeloma → Myeloma kidney (cast nephropathy)
- Monoclonal Gammopathy of Renal Significance (MGRS)
- Lymphomas → Immune complex disease, TLS
- Acute Leukemias → TLS, blast lysis
- Stem Cell Transplantation → TLS, thrombotic complications
MULTIPLE MYELOMA & MYELOMA KIDNEY
Epidemiology
- Incidence: ~200,000 new cases/year in US; 10–20 cases/million/year
- Renal involvement: 20–50% of patients at diagnosis have AKI or baseline CKD
- Clinical significance: Renal impairment = adverse prognostic factor; impacts chemotherapy dosing & prognosis
Pathophysiology of Myeloma Kidney
The mechanism (step-by-step):
- Clonal plasma cell proliferation → Produces large amounts of monoclonal immunoglobulin (usually IgG or IgA)
- Free light chain production → Clones make excess κ or λ light chains (>20 mg/dL)
- Glomerular filtration → Small light chains (22 kDa) filtered by glomerulus
- Proximal tubule uptake → Light chains reabsorbed via endocytosis
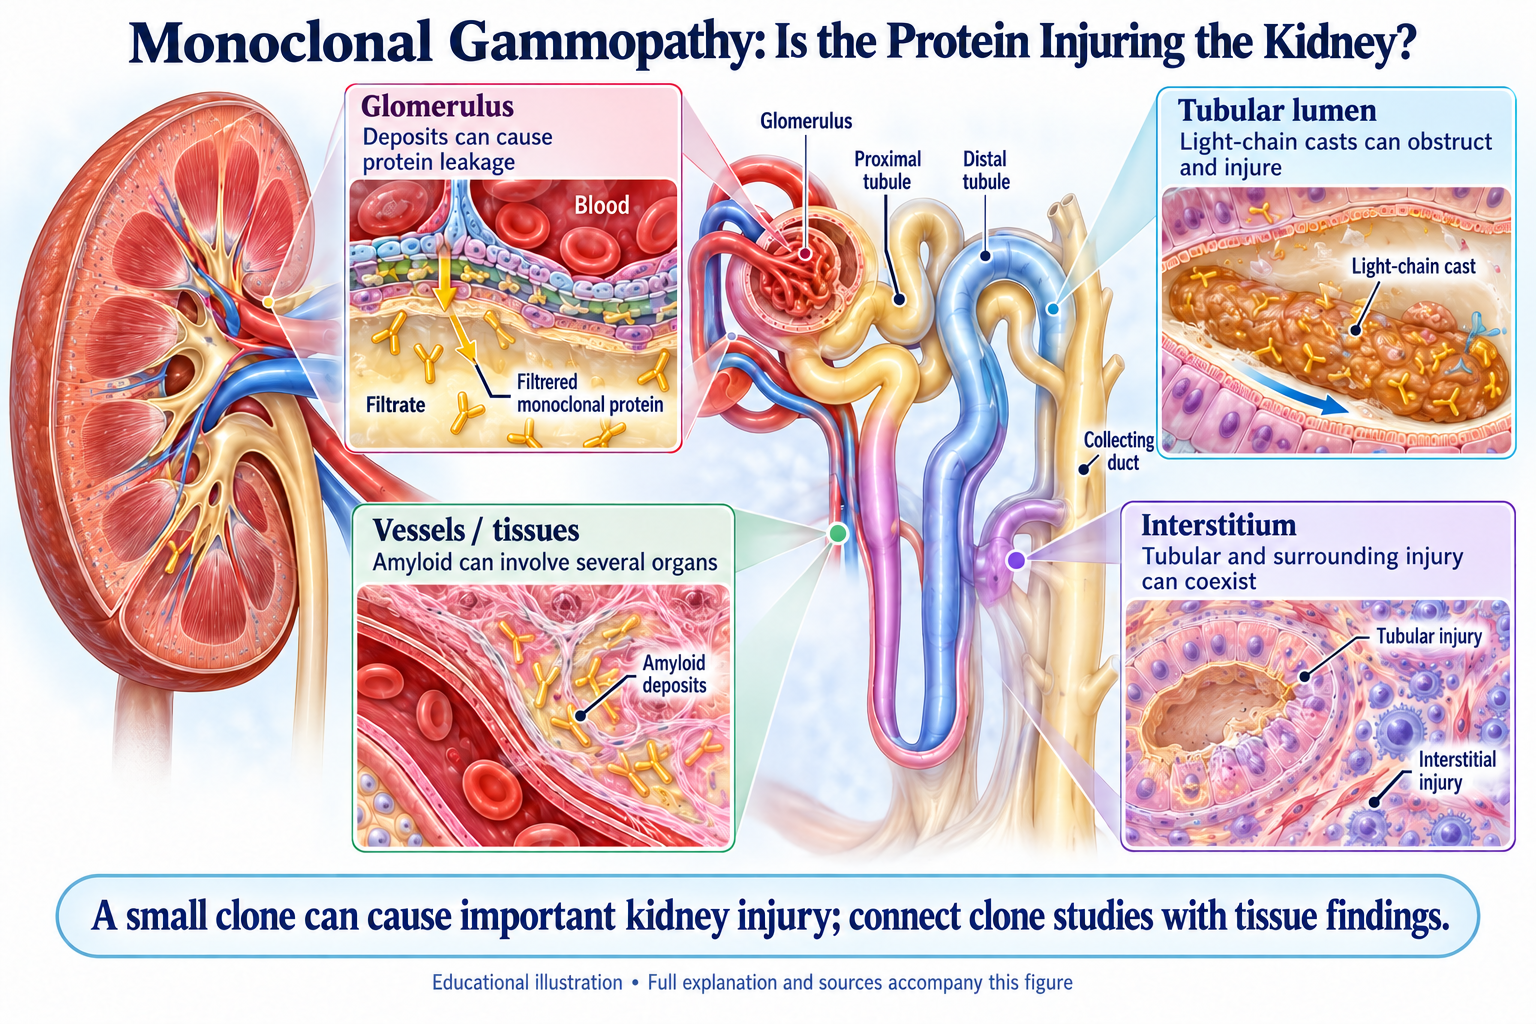
- Tubular cast formation → Light chains precipitate with Tamm-Horsfall protein (THP) to form refractory casts
- Tubular obstruction → Casts occlude tubular lumen → AKI
- Interstitial inflammation → Lytic lesions trigger innate immunity
- Result: Acute tubular necrosis + interstitial nephritis
Clinical Presentation
| Feature | Details |
|---|---|
| Acute presentation | Rapid ↑ Cr (days to weeks); oliguric AKI possible |
| Chronic | Progressive CKD over months; proteinuria <1 g/day (not nephrotic) |
| Labs | ↑ Cr, ↑ BUN, normal anion gap often; abnormal SPEP/UPEP |
| Urinalysis | Crystal-like casts, epithelial cells; NOT typically hematuria/RBC casts |
| Light chains | Serum free light chain ratio abnormal (κ/λ >100 or <0.01) |
Diagnosis
The gold standard: Kidney biopsy
| Modality | Finding |
|---|---|
| Light microscopy | Fractured light-chain casts, often with an associated inflammatory reaction; typically in distal tubules and collecting ducts |
| Electron microscopy | Cast ultrastructure varies; interpret with light microscopy and light-chain staining |
| Immunofluorescence | Casts stain with κ or λ light chain antibodies (usually one predominates) |
Supporting labs: - SPEP: M-spike (monoclonal paraprotein) - UPEP: Bence Jones protein (free light chains in urine) - FLC assay: ↑ Involved light chain; abnormal ratio
Management of Acute Myeloma Kidney
Medical Management:
- Hydration: Correct depletion with fluid therapy tailored to urine output, cardiac status, and repeated assessment for overload.
- Diuretics: Do not use furosemide routinely to force urine flow in cast nephropathy. Treat congestion only for a separate clinical indication.
- Alkalinization: Routine urine alkalinization has no demonstrated renal recovery benefit in myeloma-related renal impairment.
- Avoid contrast, NSAIDs: ↓ GFR further
- Anti-myeloma therapy: Prompt initiation of chemotherapy (bortezomib, lenalidomide, etc.) → ↓ light chain production → Resolution of casts
IMWG recommendations for myeloma-related renal impairment (2023).
Renal Replacement Therapy: - Indications: Oliguric renal failure unresponsive to hydration, severe hyperkalemia, fluid overload - Modality: CRRT or hemodialysis (some argue CRRT preferred because continuous) - Outcome: 30–50% of oliguric patients recover renal function with supportive care + chemotherapy
Prognosis: - Early treatment: ~50–70% recover renal function if caught early - Delayed treatment: ~10–20% recover if AKI prolonged - Late diagnosis: Often results in permanent dialysis dependence
Long-Term Monitoring
- Serial Cr, FLC assay (response to therapy reflected in ↓ FLC)
- Suppress light chain production aggressively
- Avoid nephrotoxic drugs
- ACEi/ARB if proteinuria >1 g/day
MGRS (Monoclonal Gammopathy of Renal Significance)
What is MGRS?
A B-cell or plasma-cell clone produces a nephrotoxic monoclonal immunoglobulin, with related kidney injury, without otherwise meeting hematologic criteria for clone-directed treatment. Kidney injury can nevertheless require treatment. A marrow plasma-cell cutoff alone does not define MGRS.
Pathology Patterns
Examples include AL amyloidosis, monoclonal immunoglobulin deposition disease, proliferative GN with monoclonal deposits, and light-chain proximal tubulopathy. Lesions may affect glomeruli, tubules, vessels, or several compartments. Some associated lesions lack monoclonal deposits.
Clinical Presentation
Proteinuria, hematuria, tubular dysfunction, AKI, or CKD may occur. Normal blood counts do not establish or exclude MGRS.
Diagnosis
Integrate kidney biopsy, immunofluorescence and ultrastructure with serum/urine immunofixation, free light chains interpreted in kidney context, and hematologic evaluation. A monoclonal band alone does not prove renal causation.
Management
Coordinate renal and hematologic expertise for lesion- and clone-specific treatment, supportive care, and longitudinal monitoring.
IKMG consensus: definition and evaluation of MGRS (2019).
LYMPHOMA & KIDNEY DISEASE
Types & Mechanisms
| Lymphoma Type | Renal Complication | Mechanism |
|---|---|---|
| Hodgkin Lymphoma | Immune complex GN, FSGS | Circulating immune complexes, nephrotic syndrome common |
| Non-Hodgkin (Burkitt) | TLS (high risk), immune complex GN | Massive cell turnover → hyperkalemia, hyperuricemia, AKI |
| Non-Hodgkin (Indolent) | Cryoglobulinemia, MPGN | Monoclonal Ig deposition similar to MGRS |
| Post-transplant lymphoproliferative | Glomerular disease, interstitial nephritis | EBV-driven; responds to reduction of immunosuppression |
Clinical Features
High-grade (Burkitt, aggressive): - Peak risk: TLS (see prior handout) - AKI common (20–30% of patients) - Monitors: K+, uric acid, PO4 closely
Indolent (Low-grade): - Gradual proteinuria, hematuria - CKD progression over years - May have cryoglobulinemia (RNP, C4 ↓, Cr, mixed cryoglobulins)
Management
- Chemotherapy → Cell destruction, monitor for TLS
- Supportive: Hydration, rasburicase (if high risk)
- Renal-specific: ACEi/ARB, BP control
- Monitor: Renal function, UA, electrolytes q 1–2 weeks during/after chemotherapy
ACUTE LEUKEMIA & KIDNEY DISEASE
Mechanisms
| Complication | Details |
|---|---|
| TLS | HIGH RISK — Acute leukemias have highest TLS incidence; rapid cell death post-chemo → hyperkalemia, hyperuricemia |
| Leukostasis | WBC obstruction of renal vessels → AKI (rare but severe) |
| Uric acid nephropathy | Massive purine load from blasts → Urate crystal obstruction |
| Blast infiltration | Direct renal parenchymal infiltration (rare) |
AML-Specific
- Higher TLS risk if WBC >100,000 and high LDH
- Bladder involvement: Hemorrhagic cystitis (from chemotherapy)
- AKI incidence: 20–50% of hospitalized AML patients
ALL-Specific
- Highest TLS risk — ALL cells most chemosensitive
- Risk factors: Age <10 or >50, WBC >100,000, bulky disease, elevated LDH
- Management: Assess TLS risk and select prophylaxis, hydration, and monitoring accordingly; rasburicase is appropriate for selected high-risk patients with attention to G6PD safety.
Management
- Prevention: Before therapy, assess disease, treatment, and patient-specific TLS risk. Select urate-lowering treatment and hydration accordingly.
- Monitor: Baseline K+, uric acid, FLC; q6h labs during first 48 h
- Kidney replacement therapy: Escalate refractory hyperkalemia, severe acidosis, fluid overload, or uncontrolled metabolic complications. Ongoing lysis and falling urine output warrant early nephrology involvement; uric acid alone is not an automatic dialysis trigger.
- Duration: Usually 5–7 days of intensive monitoring
BSH guideline: TLS risk assessment, prevention, and kidney support (2025).
STEM CELL TRANSPLANTATION (SCT) & KIDNEY DISEASE
Timing & Complications
| Phase | Complication | Mechanism |
|---|---|---|
| Pre-transplant conditioning | AKI from chemotherapy (TLS-like) | Myeloablative regimen toxicity |
| Engraftment (days 0–30) | Acute kidney injury, sepsis | Infection, medication nephrotoxicity (aminoglycosides, amphotericin) |
| Early post-transplant (months 1–3) | Calcineurin inhibitor (CNI) nephrotoxicity | Cyclosporine or tacrolimus → ↓ GFR, HTN |
| Late post-transplant (>3 months) | Chronic kidney disease, GVHD-related | CNI toxicity, chronic GVHD, infections |
Acute Kidney Injury in SCT
Incidence: 40–50% of SCT patients develop AKI; 10–15% require dialysis
Causes: - Chemotherapy nephrotoxicity (conditioning regimens contain high-dose cyclophosphamide, busulfan) - Sepsis (immune reconstitution not complete; infection risk high) - Aminoglycoside antibiotics (empiric for fever) - Amphotericin B (fungal prophylaxis) - Calcineurin inhibitors (graft-versus-host disease prophylaxis) - TLS (from rapid leukemic cell kill if allogeneic transplant for hematologic malignancy)
Chronic Kidney Disease in SCT
Long-term renal outcomes: - 5-year CKD incidence: 20–30% - Risk factors: High-dose conditioning, older age, GVHD, multiple nephrotoxic drugs, TBI (total body irradiation) - Mechanism: CNI toxicity (cyclosporine/tacrolimus) → Hyaline arteriosclerosis, glomerulosclerosis, tubular atrophy
Management Strategies
Prevention: - Minimize CNI exposure; use lowest effective dose - Alternate CNIs with sirolimus if tolerated - Avoid concurrent nephrotoxic drugs (NSAIDs, contrast agents) - Monitor BP closely (control with ACEi/ARB)
Monitoring: - Baseline renal function before conditioning - Daily Cr during conditioning & early engraftment (first 30 days) - q 1–2 week labs during months 1–3 - q 1–3 month labs long-term (look for CKD progression)
Management of AKI: - Discontinue nephrotoxic drugs if possible - Hydration (unless fluid overloaded from sepsis/capillary leak) - RRT if oliguric or severe electrolyte derangements - Empiric antibiotics with renal dosing
Management of CKD: - ACEi/ARB to slow progression - BP target <130/80 (2025 AHA/ACC, ADA); KDIGO 2021 suggests systolic <120 on standardized measurement - Reduce CNI to lowest dose; consider switch to alternative agent - Avoid NSAIDs - Monitor for bone disease (CKD-MBD from chronic GFR reduction)
Clinical Integration
Red Flags
- ✗ Myeloma patient with rapid ↑ Cr → Urgent evaluation for cast nephropathy; assess perfusion and congestion while arranging disease-directed treatment.
- ✗ High-grade lymphoma with rising potassium, phosphate, uric acid, or AKI → Evaluate urgently for TLS.
- ✗ AML with WBC >100k → Highest TLS risk; ICU-level monitoring
- ✗ SCT day +5 with ↑ Cr → Could be chemo, sepsis, CNI toxicity, or TLS overlap
Key Interventions by Scenario
| Scenario | Urgent Actions |
|---|---|
| Suspected myeloma kidney | Urgent hematology/nephrology care, individualized fluids, prompt antimyeloma treatment, and biopsy when indicated; no routine forced diuresis or urine alkalinization. |
| High-grade lymphoma starting chemo | Risk-based TLS prophylaxis, G6PD-aware rasburicase selection, individualized hydration, and monitored electrolytes and renal function. |
| AML diagnosis with WBC >100k | High-risk TLS assessment, appropriate prophylaxis, hydration and monitoring; escalate critical-care and kidney support according to clinical need. |
| SCT day +3 with AKI | Hold nephrotoxic drugs, optimize hydration status, check uric acid/K+, consider RRT if worsening |
Key Clinical Pearls
✓ Myeloma kidney = Casts — Crystal-like tubular casts on biopsy; light chain staining confirms ✓ MGRS = Biopsy essential — Distinguishes monoclonal from polyclonal immunoglobulin ✓ Lymphoma TLS = Highest risk — Burk lymphoma + bulky disease = ICU monitoring ✓ AML > ALL for volume — But ALL > AML for TLS risk per cell chemosensitivity ✓ SCT AKI multifactorial — Chemo + drugs + infection; needs systematic evaluation ✓ Early treatment = Better outcomes — Prompt chemotherapy resolves myeloma kidney; delays worsen prognosis
References
- Dimopoulos MA, et al. Management of multiple myeloma-related renal impairment: recommendations from the International Myeloma Working Group. Lancet Oncology. 2023.
- Leung N, et al. The evaluation of monoclonal gammopathy of renal significance: a consensus report of the International Kidney and Monoclonal Gammopathy Research Group. Nature Reviews Nephrology. 2019.
- Chan YLT, et al. British Society for Haematology updated guidelines for the diagnosis and management of tumour lysis syndrome in adults and children with haematological malignancies: A focus on patient safety. British Journal of Haematology. 2025.
- Wanchoo R, et al. Renal Toxicities of Novel Agents Used for Treatment of Multiple Myeloma. Clinical Journal of the American Society of Nephrology. 2017.
- Kidney injury and disease in patients with haematological malignancies. Nature Reviews Nephrology. 2021.
Study Tips: - Myeloma kidney: Fractured casts on kidney biopsy with restriction to one light chain (κ or λ), interpreted with the full pathology findings - MGRS: Link the kidney lesion to the nephrotoxic clone; no universal marrow cutoff - Lymphoma: Think TLS for high-grade, cryoglobulinemia for indolent - AML/ALL: TLS prevention depends on disease, treatment, and patient risk - SCT: Triplet problem — chemo + drugs + infection; manage all three
Created: 2026-02-28