AKI Biomarkers for Early Detection: Student Handout
Visual reference
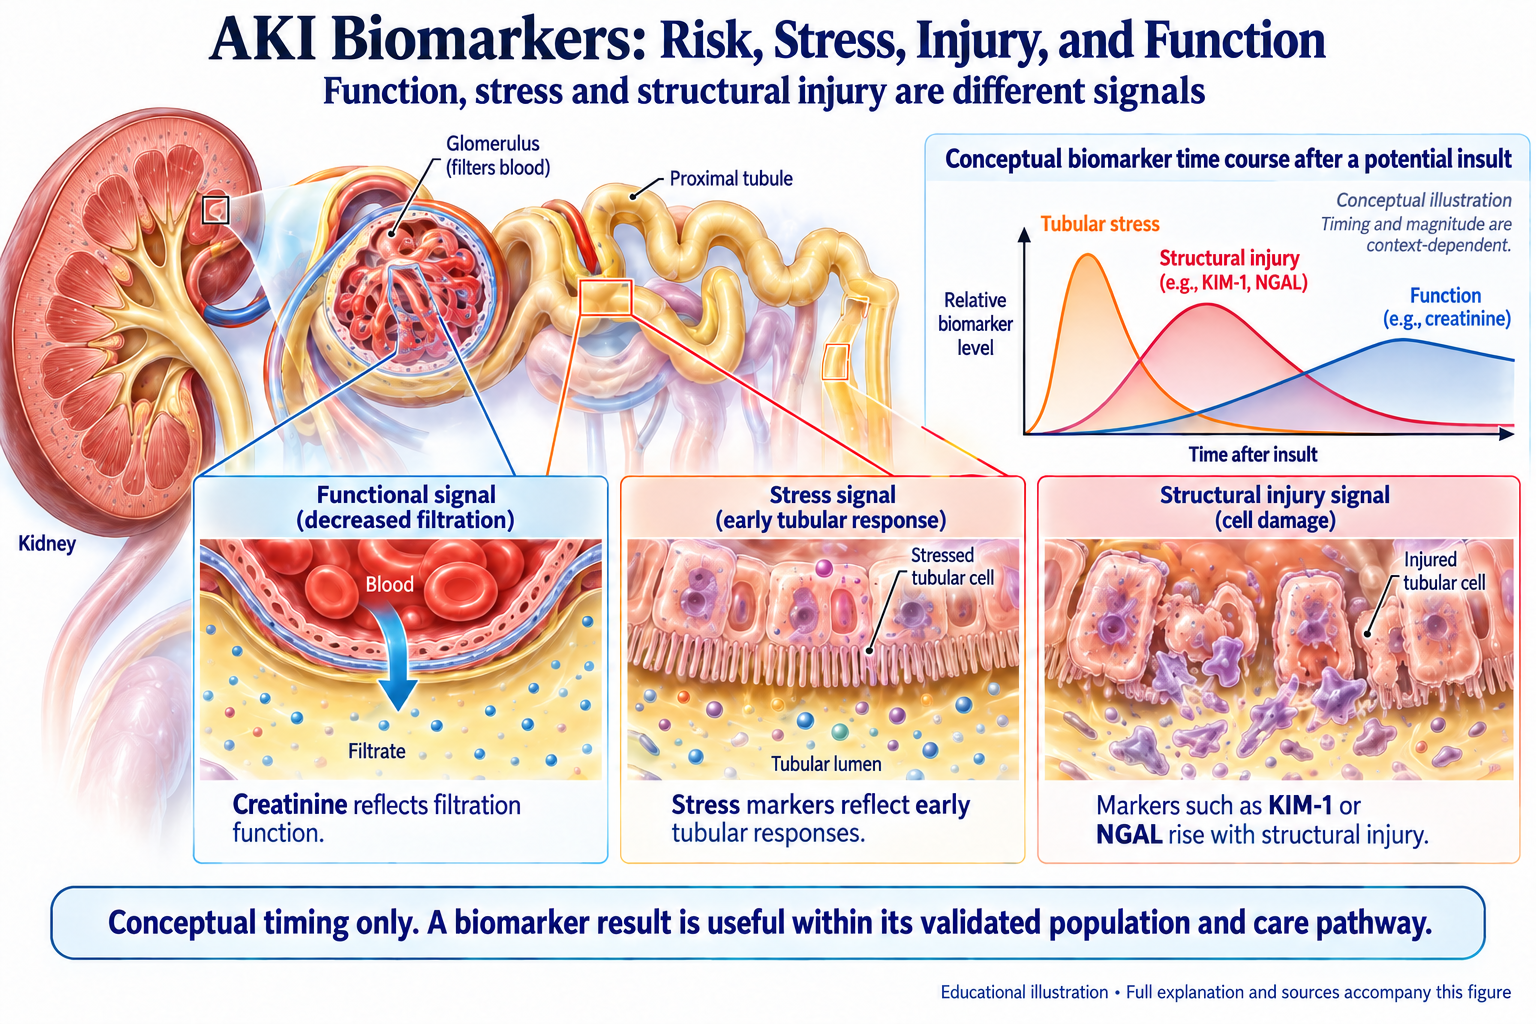
Browse the visual reference library · Download lesson Markdown
Learning Objectives
By the end of this handout, you should be able to: - Explain the limitations of traditional AKI markers (creatinine, urine output) - Identify and compare first-generation biomarkers (NGAL, KIM-1, IL-18, cystatin C) - Understand second-generation biomarkers (TIMP-2, IGFBP-7) and their clinical utility - Apply biomarkers appropriately in high-risk clinical scenarios - Recognize that biomarker combinations outperform single markers
Why New Biomarkers Matter: The Creatinine Problem
The Temporal Gap: Serum creatinine is a delayed marker of kidney injury. It may take 24-48 hours after initial AKI onset before creatinine rises above baseline. By that time, the critical therapeutic window for intervention has often closed.
Why Delay Matters: - Early intervention with hemodynamic optimization, toxin avoidance, or medication adjustments may prevent progression - Loop diuretics, fluid management, and nephrotoxin avoidance are most effective in early AKI - Once established ATN develops, treatment options become largely supportive
Urine Output Limitations: - Preserved urine output can mask significant kidney injury - Non-oliguric AKI has better outcomes but still requires recognition - Patients on diuretics may maintain urine output despite declining kidney function
Clinical Pearl: “The kidney injury exists hours before creatinine tells you it does.”
Traditional Markers: When and How to Use Them
Serum Creatinine
Pros: - Widely available, inexpensive - Defines AKI stage (KDIGO criteria)
Cons: - 24-48 hour lag after initial injury - Affected by muscle mass, age, sex, diet - Not specific for kidney injury vs. other causes of azotemia
Urine Output
Pros: - Easy to measure, real-time data
Cons: - Can be maintained despite significant tubular injury - Non-specific (many conditions reduce urine output) - Doesn’t distinguish injury type or mechanism
First-Generation Biomarkers: Detecting Early Injury
These biomarkers identify kidney injury hours to days before creatinine elevation.
Neutrophil Gelatinase-Associated Lipocalin (NGAL)
What It Is: 25-kilodalton protein rapidly upregulated in kidney tubular cells following injury.
When It Rises: 3-6 hours post-injury in most clinical settings.
Key Performance: | Metric | Value | |——–|——-| | Time to detection | 3-6 hours post-injury | | Lead time over creatinine | 24-48 hours | | Measured in | Plasma and urine | | Common assay | Point-of-care available |
Clinical Utility: - Cardiac surgery: Identifies CSAKI within 4 hours post-op - Sepsis: Early AKI detection before hemodynamic deterioration - Pediatric populations: Especially valuable (smaller baseline creatinine changes) - Cirrhosis-associated AKI (PP 2.5.6): NGAL helps distinguish true structural kidney injury (ATN) from functional/prerenal AKI (hepatorenal syndrome) in cirrhotic patients, where creatinine is particularly unreliable due to low muscle mass, impaired hepatic creatine synthesis, and volume overload
NGAL is now a guideline-recommended biomarker alongside TIMP-2·IGFBP7 (Rec 2.4.1, 2B). A positive NGAL satisfies the B1 biomarker axis in the new three-axis staging system.
Limitations: - Elevated in sepsis, burns (not kidney-specific) - Performance varies by clinical context - Requires standardized cutoffs for interpretation
Clinical Pearl: NGAL is most useful in controlled settings (post-op) where timing of potential injury is known. In cirrhosis, it adds value precisely where creatinine fails.
Kidney Injury Molecule-1 (KIM-1)
What It Is: Type 1 transmembrane glycoprotein expressed on injured proximal tubular cells.
Why It’s Special: Not expressed in healthy kidneys; dramatically upregulated only after injury (high specificity).
Key Features: - FDA-approved for preclinical drug development - Excellence in ischemic ATN detection - Predicts drug-induced AKI before creatinine rises (especially platinum-based chemotherapy) - Measured via noninvasive urine testing
Clinical Application: Monitoring patients receiving known nephrotoxic agents (cisplatin, vancomycin) to detect early injury and modify therapy.
Limitation: Less extensively validated across all AKI contexts compared to NGAL.
Interleukin-18 (IL-18)
What It Is: Inflammatory cytokine elevated in ischemic injury.
Timeline: Rises 6-12 hours post-injury (slightly later than NGAL).
Key Advantage: Synergistic with NGAL — combining both improves diagnostic accuracy.
Clinical Context: Particularly useful in: - Sepsis-associated AKI - Post-cardiac surgery AKI - Septic shock requiring risk stratification
Limitation: Elevated in other inflammatory conditions (not specific to kidney injury).
Cystatin C
What It Is: Small protein (13 kDa) produced by all nucleated cells; freely filtered by glomerulus.
Why It’s Different: Unlike creatinine, NOT affected by: - Muscle mass - Age - Sex - Diet
Clinical Advantage: Better detection in populations where creatinine is unreliable: - Elderly patients with low muscle mass - Cachectic/critically ill patients - Frail populations
Performance: - Detects AKI 24-48 hours before serum creatinine - More accurate eGFR equations when combined with creatinine
Limitation: Rises more gradually than NGAL or KIM-1 (not true “early” detection).
Second-Generation Biomarkers: Cell Cycle Arrest Markers
TIMP-2 and IGFBP-7 (Now Guideline-Recommended)
TIMP-2·IGFBP7 and NGAL are now guideline-recommended biomarkers for AKI risk assessment (Recommendation 2.4.1, Grade 2B). They are no longer just research tools — they are part of the formal AKI definition and staging system.
Revolutionary Concept: These don’t detect dead cells or inflammation — they detect cellular stress and protective mechanisms.
Biology: Both proteins are induced by G1 cell cycle arrest — a protective response where tubular cells pause division when DNA damage is detected.
Combined Metric: NephroCheck® test = [TIMP-2] × [IGFBP-7]
Clinical use and evidence: NephroCheck was FDA-cleared for the specified ICU risk-assessment population and 12-hour horizon. Test performance varies by population, timing, comparator, and outcome; do not infer universal superiority for structural-injury detection. Prediction accuracy does not itself demonstrate improved outcomes. FDA decision summary.
Assay-specific risk interpretation: For the original FDA-cleared NephroCheck use, an AKIRisk score >0.3 is a risk signal for moderate/severe AKI within 12 hours in ICU patients age ≥21 with recent acute cardiovascular or respiratory compromise. It is not a diagnosis, a universal Stage-3 probability, or a dialysis trigger. Follow actual units, intended population, and clinical context. FDA decision summary.
The Biomarker Axis: B0/B1 in KDIGO 2026 draft Three-Axis Staging
KDIGO 2026 draft introduces biomarkers as the third axis of AKI staging alongside creatinine (C0–C3) and urine output (U0–U3):
| Biomarker Stage | Definition |
|---|---|
| B0 | No biomarker evidence of kidney injury/stress |
| B1 | Positive kidney injury/stress biomarker (TIMP-2·IGFBP7, NGAL, or other validated marker) |
Proposed subclinical AKI (C0/U0/B1): The KDIGO 2026 AKI/AKD public-review draft proposes a biomarker axis for injury/stress despite no qualifying creatinine or urine-output change. This remains draft terminology, not a final replacement for published routine AKI criteria.
Clinical Pearl: TIMP-2·IGFBP7 and NGAL are the primary biomarkers that satisfy B1 criteria. A positive result moves a patient from “no AKI” to “subclinical AKI” even with normal Cr and UO.
Limitations: - Bilirubin interference (>7.2 g/dL causes false elevation) - Proteinuria interference (>125 mg/dL) - Not validated across all AKI etiologies yet
Clinical Applications by Setting
Cardiac Surgery (Highest Evidence Base)
Why It Matters: AKI occurs in 20-50% of cardiac surgery patients and worsens outcomes.
Recommended Biomarker Strategy: 1. Baseline: Measure TIMP-2/IGFBP-7, cystatin C, NGAL 2. Post-op 2-4 hours: Repeat TIMP-2/IGFBP-7 3. If elevated: Implement protective measures (optimize hemodynamics, avoid nephrotoxins) 4. High-risk patients: Consider RRT earlier if biomarkers show severe elevation
Evidence: Multi-institutional data shows biomarker-guided RRT timing reduces complications and ICU stays.
Sepsis and Septic Shock
Challenge: Multiple competing mechanisms (ischemia, inflammation, endothelial dysfunction) require broader biomarker panel.
Recommended Combination: - NGAL + IL-18 (detect injury + inflammation) - TIMP-2/IGFBP-7 (assess progression risk) - Cystatin C (baseline renal function)
Clinical Decision: High-risk biomarker profile should prompt: - Aggressive hemodynamic optimization - Avoidance of additional nephrotoxins - More intensive renal function monitoring
Nephrotoxic Drug Monitoring (Platinum Chemotherapy)
Special Application: Detecting drug-induced AKI before irreversible damage.
Biomarker of Choice: KIM-1 (detects tubular injury 2 days before creatinine rise)
Clinical Protocol: 1. Baseline KIM-1 before chemotherapy initiation 2. Serial measurement during treatment (every 2-3 days) 3. If KIM-1 rises >50% from baseline: consider dose adjustment or treatment modification 4. May prevent progression to clinically significant AKI
Evidence: Studies show early KIM-1 elevation predicts treatment-limiting nephrotoxicity.
Biomarker Panels: Combining Tests for Better Accuracy
Key Concept: No single biomarker achieves perfect diagnostic accuracy. Combining markers improves performance.
Example Panel Strategy
| Clinical Scenario | Recommended Panel | Rationale |
|---|---|---|
| Cardiac surgery, high-risk | TIMP-2/IGFBP-7 + Cystatin C + NGAL | Detect stress, structural damage, GFR |
| Septic shock ICU | IL-18 + NGAL + TIMP-2/IGFBP-7 | Inflammation + injury + progression |
| Drug monitoring | KIM-1 + NGAL | Tubular toxicity detection |
| Cardiac surgery + CKD | All above markers | Multiple risk factors require comprehensive assessment |
Interpretation Strategy: - All normal: Low risk of progression; standard monitoring - 1-2 markers elevated: Intermediate risk; close observation, optimize conditions - 3+ markers elevated: High risk; consider early RRT, aggressive nephroprotection
Table: Biomarker Comparison
| Biomarker | Time to Rise | Specificity | Test Type | Clinical Use | Limitations |
|---|---|---|---|---|---|
| Creatinine | 24-48 hrs | Low | Serum | Define AKI stage | Delayed, non-specific |
| NGAL | 3-6 hrs | Moderate | Serum/Urine | Early AKI detection | Non-kidney specific |
| KIM-1 | 2-4 hrs | High | Urine | Drug-induced AKI | Less validated overall |
| IL-18 | 6-12 hrs | Moderate | Urine | Sepsis, ischemia | Non-specific |
| Cystatin C | 24-48 hrs | Moderate | Serum | eGFR accuracy | Slower rise than others |
| TIMP-2/IGFBP-7 | 12-24 hrs | High | Urine (NephroCheck®) | Progression risk | Bilirubin/protein interference |
Regulatory Status and Clinical Implementation
FDA-Qualified Biomarkers (for drug development): - Cystatin C - KIM-1 - NGAL - TIMP-2 - IGFBP-7 - Osteopontin - Clusterin
This FDA qualification enables pharmaceutical companies to use these in drug trials as evidence of nephrotoxicity or nephroprotection—accelerating drug development.
Commercially Available Tests: - NephroCheck®: TIMP-2 × IGFBP-7 (point-of-care available) - NGAL: Multiple lab platforms - KIM-1: Research assays primarily - Cystatin C: Widely available
Current Guidelines and Evidence-Based Recommendations
KDIGO 2026 draft Guidelines Position:
- KDIGO 2026 AKI/AKD draft: Proposed biomarker recommendations remain under public review. Distinguish those proposals from assay-specific FDA clearance and from the published creatinine/urine-output definition of AKI.
- Biomarkers form the third axis (B0/B1) of the new three-axis AKI staging system
- Subclinical AKI (C0/U0/B1) is now a recognized staging category — biomarkers alone can define AKI
- Should complement, not replace, clinical assessment
- Not recommended for routine screening of low-risk patients
Urine Eosinophils: A Critical Teaching Point
Urine eosinophils have LOW sensitivity for excluding AIN (acute interstitial nephritis). A negative urine eosinophil test does NOT rule out AIN. Do not rely on urine eosinophils as a standalone diagnostic test for AIN — clinical suspicion, medication history, and kidney biopsy remain the gold standard.
Evidence Gap: Biomarker-Guided Treatment Trials
Existing diuretic treatment trials in AKI were conducted without biomarker-guided enrollment. Patients were selected based on creatinine and urine output criteria alone. This creates a significant research opportunity: future trials using the C/U/B three-axis staging system for enrollment could identify patients who benefit most from intervention — particularly those with subclinical AKI (C0/U0/B1) who were invisible to prior trial designs.
Best Practice Implementation:
- High-risk settings preferred: Cardiac surgery, ICU, sepsis
- Appropriate comparator: Compare to baseline when possible
- Serial measurement: Single values less useful than trends
- Integrate with clinical context: Don’t use biomarkers in isolation
- Understand limitations: Biomarkers enhance but don’t replace clinical judgment
- Check the B axis: In high-risk patients, consider biomarker testing even when Cr and UO are normal
Practical Clinical Scenarios
Scenario 1: Post-Cardiac Surgery Day 1
Patient’s creatinine is 1.1 (baseline 0.9), unchanged from pre-op. Does he need intervention?
Without Biomarkers: Might reassure—creatinine stable.
With Biomarkers: TIMP-2/IGFBP-7 = 0.8 (high-risk). Indicates developing AKI despite stable creatinine.
Clinical Action: Implement nephroprotective measures (optimize hemodynamics, avoid NSAIDs, monitor for progression). Risk-stratified RRT timing.
Scenario 2: Septic Shock, Day 2
Patient receiving sepsis treatment. Creatinine 1.8 (baseline 1.0). NGAL 400 ng/mL (elevated), IL-18 elevated.
Interpretation: Active kidney injury with inflammatory component despite antimicrobial therapy.
Clinical Action: Aggressive hemodynamic optimization, avoid additional nephrotoxins, prepare for possible RRT, consider high-dose vasopressor response.
Scenario 3: Patient on Cisplatin Chemotherapy
KIM-1 rises 150% from baseline after dose 1.
Interpretation: Early tubular toxicity detected.
Clinical Action: Dose adjustment/timing change for dose 2, enhanced hydration, avoid concurrent nephrotoxins, may prevent progression to dialysis-requiring AKI.
Practice Questions
Question 1: A 64-year-old undergoes elective cardiac surgery with CABG. Post-op day 1: creatinine 1.0 (baseline 0.9), urine output 1.8 L/24hr, TIMP-2/IGFBP-7 = 0.95. Which statement is most accurate? A) No AKI is developing; standard post-op care sufficient B) Patient is at high risk for AKI progression; implement nephroprotective measures C) Elevated biomarker indicates existing AKI Stage 2; start RRT D) Biomarkers unreliable in post-op period; ignore and follow creatinine
Answer: B) Use the positive risk result to reassess and monitor. In the appropriate intended population, a TIMP-2·IGFBP7 result >0.3 supports increased risk of moderate/severe AKI within 12 hours. Reassess perfusion/congestion, exposures, dosing, urine output, and creatinine. It does not prove Stage-3 AKI will occur or justify automatic fluids.
Question 2: Which biomarker combination would be most appropriate for a 58-year-old receiving cisplatin-based chemotherapy? A) NGAL and IL-18 B) TIMP-2/IGFBP-7 and cystatin C C) KIM-1 and NGAL D) Creatinine and BUN
Answer: C) KIM-1 and NGAL. For drug-induced (chemotherapy) AKI monitoring, KIM-1 is most sensitive to tubular toxicity and detects injury 2 days before creatinine rise. NGAL adds complementary information. This combination allows early detection permitting dose modification or timing changes.
Question 3: A 72-year-old with septic shock (day 3) has creatinine 2.1 (baseline 1.2). NGAL = 350 ng/mL, IL-18 elevated, TIMP-2/IGFBP-7 = 1.8. Which interpretation is most accurate? A) Multiple mechanisms of kidney injury (ischemia + inflammation + progressive tissue damage) warrant comprehensive management B) Only NGAL is reliable; others are nonspecific C) High biomarker levels indicate end-stage renal disease D) Biomarkers confirm ATN; biopsy needed
Answer: A) Multiple mechanisms of kidney injury (ischemia + inflammation + progressive tissue damage) warrant comprehensive management. The panel shows: NGAL (early ischemic injury), IL-18 (inflammatory component), and TIMP-2/IGFBP-7 (high risk for progression). This indicates sepsis-associated AKI with multiple pathophysiologic mechanisms requiring aggressive hemodynamic optimization, vasopressor optimization, and heightened vigilance for RRT needs.
Key Takeaways
- Creatinine has a lag — biomarkers detect injury earlier
- KDIGO 2026 draft made biomarkers official — TIMP-2·IGFBP7 and NGAL are now guideline-recommended (Rec 2.4.1, 2B), forming the B axis of three-axis staging
- Subclinical AKI (C0/U0/B1) is real — biomarkers alone can define AKI even with normal Cr and UO
- TIMP-2·IGFBP7: An assay-specific AKI risk tool in a defined ICU population; use its validated time horizon and population, not a universal claim of superiority.
- KIM-1 excels at drug-induced AKI detection
- NGAL differentiates ATN from HRS in cirrhosis (PP 2.5.6)
- Urine eosinophils have low sensitivity for excluding AIN — do not rely on a negative result (PP 2.5.2)
- Combinations outperform single markers for diagnostic accuracy
- Clinical context matters — don’t interpret biomarkers in isolation
- Evidence gap exists — diuretic trials lacked biomarker-guided enrollment, creating research opportunity for C/U/B-guided interventions
See Also
Clinical Content (01-Clinical-Medicine/Nephrology)
- AKI Hub - Full Clinical Reference
- Essential Renal Laboratory Tests
Atomic Notes (ZK)
- Cell Cycle Arrest Biomarkers in AKI Detection
- Cell Cycle Arrest Biomarkers Updated
- Functional Biomarkers in Early AKI
Butler-COM Resources
- Butler COM - Nephrology Deep Dive