AKI BMP Pattern Recognition Guide
Visual reference
Browse the visual reference library · Download lesson Markdown
Overview
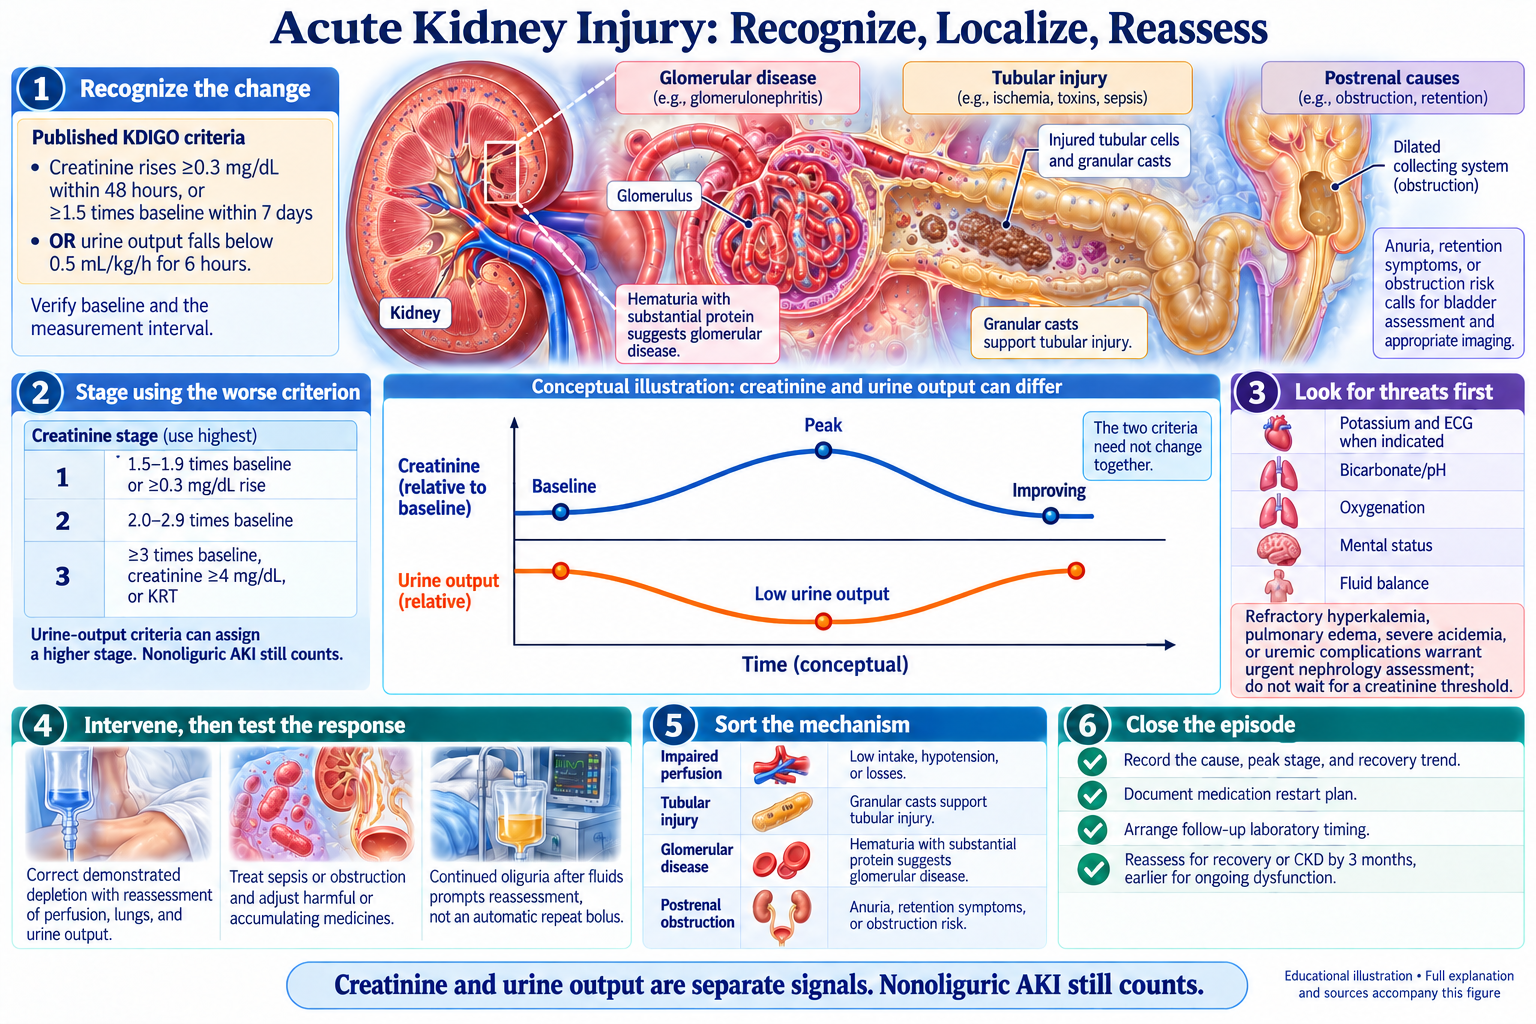
Recognize AKI from a change in creatinine or urine output, then determine its cause and complications. The published KDIGO framework includes a creatinine rise of at least 0.3 mg/dL within 48 hours, at least 1.5 times baseline within 7 days, or urine output below 0.5 mL/kg/hour for 6 hours [1]. Creatinine is a delayed functional marker influenced by muscle mass, fluid balance, and medications [2].
The BMP helps identify dangerous electrolyte and acid-base abnormalities. It cannot, by itself, reliably distinguish prerenal, intrinsic, and postrenal AKI. Calcium is usually part of the BMP; phosphorus, creatine kinase, albumin, lactate, and measured osmolality require separate tests. Use the clinical history, examination, urine studies, and appropriate imaging in parallel [1,11].
Key Clinical Pearl
Use patterns to generate hypotheses, not to assign a diagnosis. Normal potassium does not establish prerenal AKI; a high potassium concentration does not establish tubular injury. A creatinine cutoff, BUN:creatinine ratio, or isolated urine index cannot determine the mechanism.
Part 1: Three-Compartment AKI Framework
Prerenal physiology
Reduced effective renal perfusion can lower filtration before structural injury occurs. Causes include volume depletion, impaired circulation, and altered glomerular hemodynamics. Prerenal physiology and structural injury can coexist or evolve over time.
BUN may rise disproportionately, but protein intake, catabolism, gastrointestinal bleeding, liver function, and medications confound the BUN:creatinine ratio. Sodium, potassium, chloride, and bicarbonate vary with the illness and treatment. There is no maximum creatinine that defines prerenal AKI.
Low urine sodium or a low fractional excretion of sodium can support sodium avidity in selected patients. They are not proof of fluid responsiveness or a mandate to give fluids [6,11].
Intrinsic kidney injury
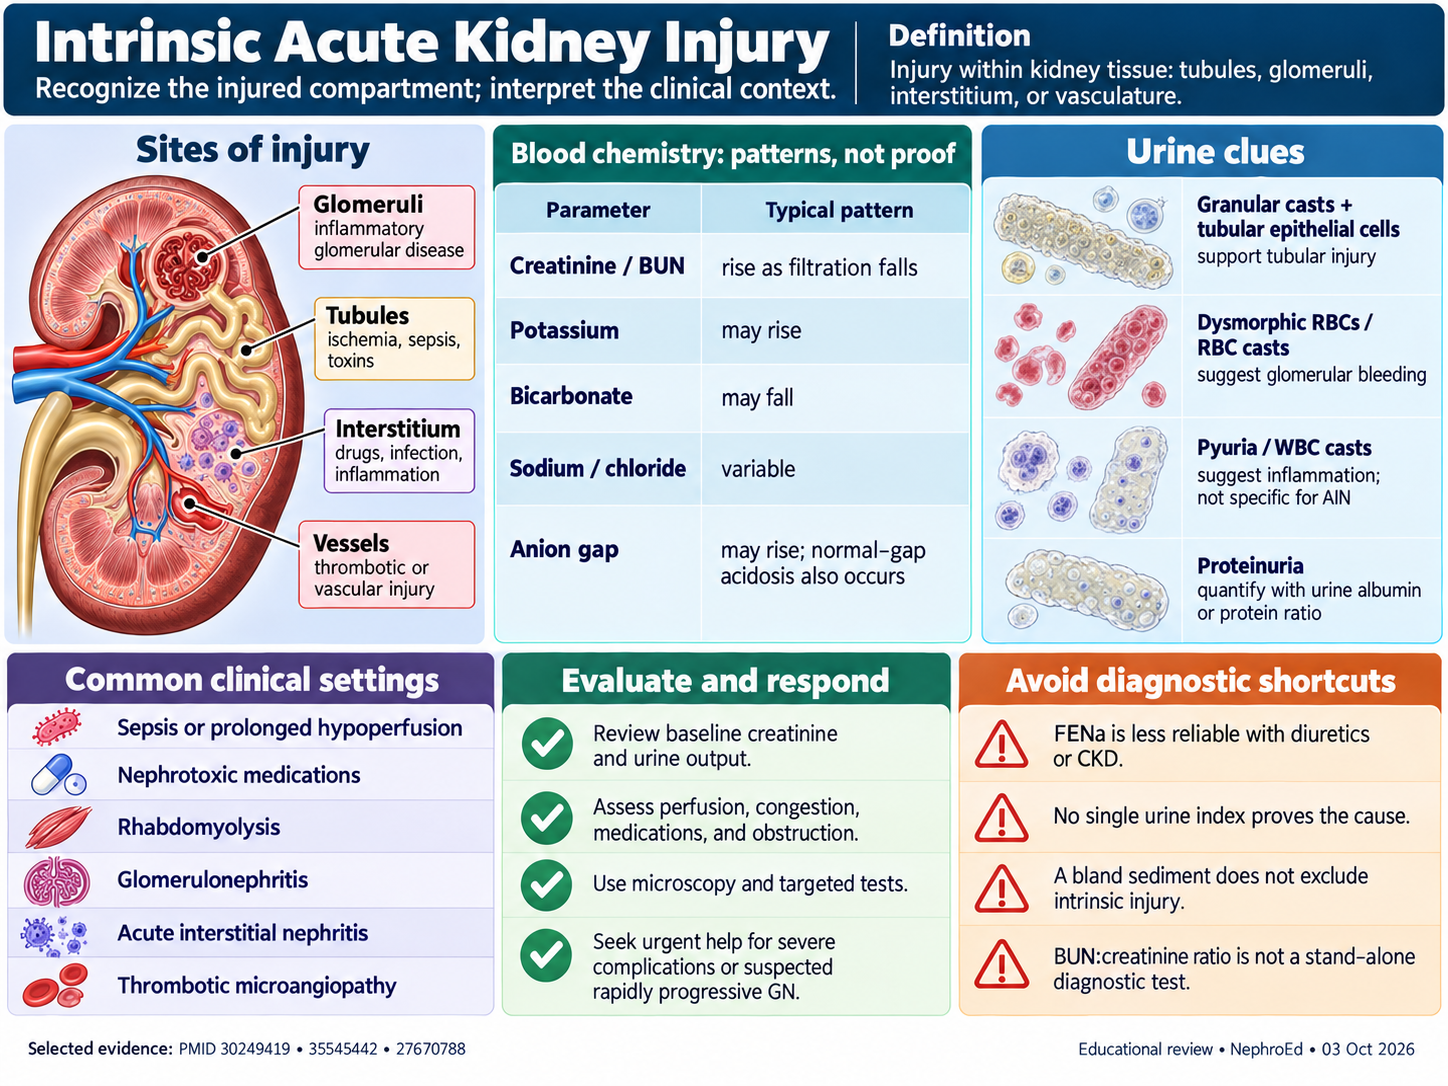
Injury may involve tubules, glomeruli, interstitium, or vessels. Creatinine and BUN can rise as filtration falls; potassium may rise and bicarbonate may fall. Sodium and chloride are variable. Metabolic acidosis can have a normal or increased anion gap.
Urine findings help localize injury: granular casts and tubular epithelial cells support tubular injury; dysmorphic red cells or red cell casts suggest glomerular bleeding. Pyuria or white cell casts suggest inflammation but are not specific for acute interstitial nephritis. Quantify albuminuria or proteinuria when appropriate [10].
Drugs can cause hemodynamic changes, tubular injury, interstitial nephritis, or crystal injury. Review exposure, timing, dose, and concurrent illness; a creatinine rise alone does not establish structural drug toxicity [5].
Postrenal obstruction
Obstruction in the collecting system, ureters, bladder outlet, or urethra can impair filtration. Renal artery obstruction is a vascular cause, not postrenal urinary obstruction. The BMP pattern depends on severity and duration and is not diagnostic [4].
Consider bladder retention, catheter malfunction, stones, malignancy, or neurogenic bladder. Use a bladder assessment and appropriate imaging. A normal initial ultrasound does not exclude every obstruction, particularly early or nondilated obstruction. An infected obstructed system, anuria, or severe complications requires urgent specialist assessment [4].
Part 2: Specialized BMP Patterns—Key Etiologies
Rhabdomyolysis pattern
Muscle injury may cause a marked CK rise, hyperkalemia, hyperphosphatemia, and early hypocalcemia; findings vary with timing and severity. A heme-positive urine dipstick with few red cells can suggest pigmenturia. CK and phosphorus are separate tests, not BMP components.
Assess the cause, volume status, urine output, and complications promptly. Give isotonic crystalloid when indicated with repeated reassessment, particularly when oliguria or congestion limits safe fluid administration. Routine bicarbonate or mannitol to prevent rhabdomyolysis-associated AKI is not supported by the cited guideline; bicarbonate may have a separate indication, such as selected severe acidemia [7].
AKI after iodinated contrast
A creatinine rise following contrast is contrast-associated AKI; temporal association alone does not prove contrast caused it. Hypotension, sepsis, congestion, embolic disease, and other exposures may contribute. There is no diagnostic sodium, potassium, or anion-gap pattern [8].
For intravenous contrast, prevention is individualized to AKI status, kidney function, and the risk of volume overload. Isotonic saline prophylaxis is used in selected high-risk patients when appropriate. N-acetylcysteine is not recommended for routine prophylaxis. Metformin is not a nephrotoxin; withholding decisions relate to AKI or severe kidney dysfunction and lactic-acidosis risk, following the applicable contrast protocol [8].
AKI in cirrhosis and HRS-AKI
Cirrhosis with ascites increases the risk of several AKI phenotypes, including hypovolemia, sepsis-associated injury, drug injury, and HRS-AKI. Hyponatremia may coexist but does not diagnose HRS. BUN production can be reduced by liver disease, so a high BUN:creatinine ratio is not a required HRS pattern [9].
Use contemporary HRS-AKI criteria and evaluate volume status and competing causes. Vasoconstrictor therapy with carefully titrated albumin is used after HRS-AKI is established, with close respiratory and volume monitoring. Do not start HRS treatment solely because sodium is below a numerical threshold [9].
Cardiorenal physiology
Heart failure can affect kidney function through venous congestion, impaired forward flow, neurohormonal activation, and treatment effects. Both reduced and preserved ejection fraction can be relevant.
Sodium may fall with impaired water excretion. Potassium may be low with diuretics or high with reduced excretion and medications. Diuretics can cause metabolic alkalosis; shock can produce lactic acidosis. Respiratory acidosis is a separate acid-base process and does not explain a low bicarbonate by itself.
Interpret the creatinine trend alongside perfusion, congestion, urine output, treatment response, and relevant cardiac assessment. A rise during decongestion does not automatically require fluids or establish structural tubular injury [11].
Part 3: Diagnostic sequence
- Confirm the change: compare with a credible baseline, check timing, urine output, and possible laboratory or medication effects.
- Identify urgent complications: evaluate significant hyperkalemia, acidemia, pulmonary edema, and uremic manifestations promptly.
- Assess circulation and exposures: look for hypovolemia, shock, congestion, infection, and medication-related mechanisms.
- Examine urine: microscopy and protein or albumin quantification can identify clues to glomerular, tubular, interstitial, or crystal disease.
- Assess obstruction when plausible: bladder evaluation and kidney imaging complement the examination.
- Order targeted tests: examples include CK for muscle injury, serologies for suspected glomerular disease, and hemolysis studies when microangiopathy is suspected.
- Reassess: mixed mechanisms are common. Change the working diagnosis when the course or new evidence no longer fits.
This sequence complements clinical assessment and does not use a single BMP or urine threshold as a diagnostic rule [1,4,5,10,11].
Part 4: Interpretation of FeNa and FeUrea
Fractional excretion of sodium (FeNa)
Formula: FeNa (%) = 100 × (urine sodium × serum creatinine) / (serum sodium × urine creatinine). Use compatible units and samples obtained close together.
A low FeNa suggests sodium avidity; a higher value may reflect reduced sodium reabsorption. Traditional thresholds below 1% and above 2% are contextual clues. FeNa performs best in selected oliguric patients without CKD or recent diuretic exposure; it is less reliable in broader populations. Low FeNa can occur in intrinsic disease, and diuretics can raise it despite reduced effective perfusion [6].
Fractional excretion of urea (FeUrea)
Formula: FeUrea (%) = 100 × (urine urea × serum creatinine) / (serum urea × urine creatinine). Match urea or urea-nitrogen units consistently.
A value below 35% has been studied as a clue to reduced effective perfusion, including in some patients receiving diuretics [3]. It is not a definitive separator of prerenal and intrinsic AKI and is not uniformly reliable in sepsis, CKD, or diuretic-treated patients. Interpret it with the clinical course and other findings [11].
Part 5: Patterns that prompt targeted evaluation
| Finding | Consider | Useful next assessment |
|---|---|---|
| AKI with high CK and muscle symptoms | Rhabdomyolysis | Potassium, phosphorus, calcium, volume status, and urine output |
| Hematuria, proteinuria, or red cell casts | Glomerular disease | Quantify protein; seek timely nephrology assessment and targeted serologies |
| AKI after a new drug | Hemodynamic, tubular, interstitial, or crystal injury | Exposure timeline, dose, microscopy, and alternative causes |
| AKI with retention symptoms or anuria | Urinary obstruction | Bladder evaluation, catheter assessment when relevant, and imaging |
| AKI with cirrhosis and ascites | Several phenotypes, including HRS-AKI | Infection, hemodynamics, volume status, exposures, and diagnostic criteria |
| AKI after contrast | Contrast-associated AKI and competing causes | Timeline, circulation, medications, and illness severity |
No row is a stand-alone diagnostic rule [4,5,7–11].
Part 6: BMP-Guided Clinical Decision-Making
When to obtain urine electrolytes
Order selectively when the result could clarify a specific question. Recognize diuretic, CKD, and sepsis confounding. Persistent oliguria after substantial fluid administration requires reassessment for congestion, intrinsic injury, or obstruction; it is not evidence that more fluid is automatically needed [6,11].
When to examine urine sediment
Microscopy is useful in unexplained AKI and suspected glomerular, tubular, interstitial, or crystal disease. Urine eosinophils neither establish nor exclude AIN. Interpret casts and cells as clues alongside the history and other tests [5,10].
When to obtain kidney and bladder imaging
Evaluate obstruction when retention, anuria, stones, pelvic or retroperitoneal disease, catheter problems, or unexplained AKI make it plausible. The BMP cannot exclude obstruction. Interpret a residual volume and ultrasound in the clinical context rather than treating one cutoff as diagnostic [4].
When to consider kidney biopsy
Discuss biopsy with nephrology when unexplained AKI or suspected glomerular, interstitial, vascular, or paraprotein-related disease could change treatment. Normal complement does not establish lupus or membranoproliferative disease, and negative serologies do not exclude every treatable lesion [5,10,11].
Part 7: Key Warnings
Warning 1: Urine indices are not definitive
Neither FeNa nor FeUrea proves a mechanism or predicts that fluids are safe. Use trends, sediment, perfusion, congestion, and the exposure history [3,6,11].
Warning 2: Rhabdomyolysis can evolve
Creatinine may lag muscle injury. Monitor the clinical course and complications, and individualize fluids. A high CK alone is not an instruction for unlimited fluids or routine urine alkalinization [7].
Warning 3: An osmolal gap requires context
With sodium in mmol/L and glucose and BUN in mg/dL, a common calculated osmolality is 2 × sodium + glucose/18 + BUN/2.8. Compare with measured osmolality and account for relevant alcohols or other osmoles.
An elevated gap is not specific for toxic alcohol exposure, and a normal gap does not exclude it, especially later in the course. If exposure is plausible, obtain urgent toxicology guidance; do not rely on the gap alone [11].
Warning 4: Severe hyponatremia needs prompt assessment
Assess symptoms, acuity, and the cause. Severe hyponatremia in cirrhosis does not by itself diagnose HRS-AKI or justify immediate vasoconstrictor treatment. Plan correction carefully and evaluate the AKI phenotype [9].
References
[1] Kellum JA, Lameire N; KDIGO AKI Work Group. Diagnosis, evaluation, and management of acute kidney injury: a KDIGO summary (Part 1). Crit Care. 2013;17:204. PubMed
[2] Waikar SS, Bonventre JV. Creatinine kinetics and the definition of acute kidney injury. J Am Soc Nephrol. 2009;20:672–679. PubMed
[3] Carvounis CP, Nisar S, Guro-Razuman S. Significance of the fractional excretion of urea in the differential diagnosis of acute renal failure. Kidney Int. 2002;62:2223–2229. PubMed
[4] Yaxley J, Yaxley W. Obstructive uropathy – acute and chronic medical management. World J Nephrol. 2023;12(1):1–9. doi:10.5527/wjn.v12.i1.1. PubMed (PMID: 36704657)
[5] Perazella MA, Rosner MH. Drug-Induced Acute Kidney Injury. Clin J Am Soc Nephrol. 2022;17(8):1220–1233. doi:10.2215/CJN.11290821. PubMed (PMID: 35273009)
[6] Diagnostic Performance of Fractional Excretion of Sodium for the Differential Diagnosis of Acute Kidney Injury: A Systematic Review and Meta-Analysis. 2022. PubMed (PMID: 35545442)
[7] Management of rhabdomyolysis: A practice management guideline from the Eastern Association for the Surgery of Trauma. 2022. PubMed (PMID: 34836603)
[8] Use of Intravenous Iodinated Contrast Media in Patients with Kidney Disease: Consensus Statements from the American College of Radiology and the National Kidney Foundation. 2020. PubMed (PMID: 31961246)
[9] Acute kidney injury in patients with cirrhosis: ADQI and ICA joint multidisciplinary consensus meeting. 2024. PubMed (PMID: 38527522)
[10] Urine Sediment Examination in the Diagnosis and Management of Kidney Disease: Core Curriculum 2019. 2019. PubMed (PMID: 30249419)
[11] Acute kidney injury 2016: diagnosis and diagnostic workup. 2016. PubMed (PMID: 27670788)
Last updated: 2026-10-03 Board-review quality curriculum for nephrology education.