AKI Workup and Diagnostic Approach: Student Handout
Updated March 2026 to reflect KDIGO 2026 draft guideline
Visual reference
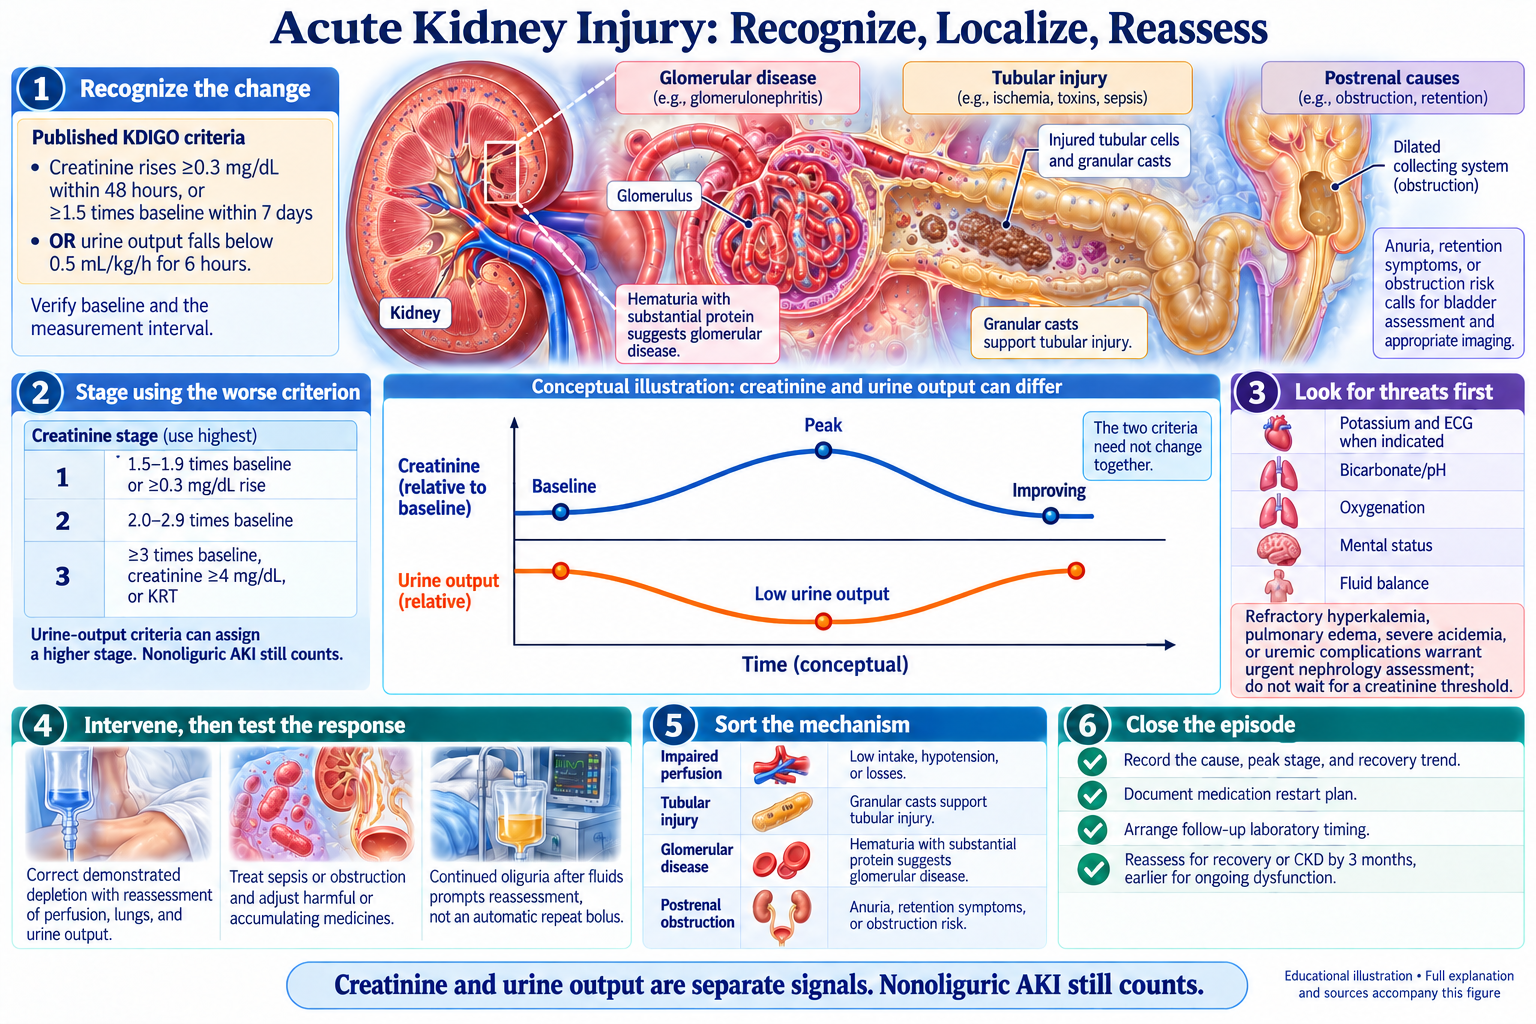
Browse the visual reference library · Download lesson Markdown
Learning Objectives
By the end of this handout, you should be able to: - Classify AKI into prerenal, intrarenal, and postrenal causes - Interpret urine microscopy findings to differentiate AKI types — urine microscopy is a key diagnostic tool interpreted with the clinical context - Understand why FeNa has limited clinical utility and when it can (and cannot) be used - Explain why eGFR on the BMP is invalid during AKI and how to track kidney function instead - Perform systematic diagnostic evaluation of acute kidney injury - Recognize rapidly progressive glomerulonephritis and acute cortical necrosis as nephrologic emergencies - Apply the furosemide stress test for AKI risk stratification
Overview: What is Acute Kidney Injury?
Definition: Acute kidney injury represents a complex clinical syndrome with rapid deterioration in kidney function. Approximately 20% of hospitalized patients experience AKI, making it one of the most common serious complications in hospital medicine.
Key Concept: AKI exists on a spectrum with chronic kidney disease (CKD). The traditional distinction has evolved; we now recognize an intermediate category called “acute kidney disease” that bridges the acute-to-chronic transition, occurring between 7-90 days after initial injury.
Clinical Pearl: Many patients present with “acute-on-chronic” kidney disease (AKI superimposed on existing CKD), representing a particularly high-risk population requiring specialized management approaches.
The Diagnostic Framework: Three Categories
PRERENAL AKI (Reduced Kidney Perfusion)
Mechanism: Decreased blood flow to kidneys triggers activation of the renin-angiotensin-aldosterone system. The kidney attempts to preserve function through sodium and water retention.
Common causes: - Gastrointestinal losses (vomiting, diarrhea) - Hemorrhage or dehydration - Sepsis with distributive shock - Heart failure (reduced cardiac output) - Medications that alter renal hemodynamics (NSAIDs, ACE inhibitors in certain settings)
Key Laboratory Findings: | Test | Finding | Significance | |——|———|————-| | Fractional Excretion of Sodium (FENa) | <1% | Intact tubular sodium reabsorption | | Urine specific gravity | >1.020 | Concentrated urine | | Urine osmolality | >500 mOsm/kg | Preserved concentrating ability | | BUN:Creatinine ratio | >20:1 | Preferential urea reabsorption |
Urine Microscopy: Minimal abnormalities. May see occasional hyaline casts (composed of Tamm-Horsfall protein) indicating preserved tubular function. Absence of significant cellular elements supports functional rather than structural injury.
Important Caveat — FeNa Has Limited Clinical Utility (KDIGO 2026 draft PP 2.5.4):
Fresh microscopy and FENa provide complementary clues. FENa performs best in oliguric AKI without CKD or diuretics; low values do not exclude GN, pigment or tubular injury, and high values do not prove ATN. Interpret the clinical course and imaging.
FeNa confounders that render it uninterpretable: - Diuretics — the most common confounder; recent loop or thiazide use can raise FENa and reduce specificity for tubular injury - CKD — baseline tubular dysfunction elevates FeNa even in prerenal states - Sepsis — can cause low FeNa despite intrinsic injury (sepsis-related vasoconstriction) - Contrast exposure — variable effects on tubular sodium handling - Early obstruction — FeNa may be low in the first hours of obstructive AKI
FeUrea was proposed to overcome the diuretic limitation, but its diagnostic performance remains poor in clinical studies. KDIGO 2026 draft explicitly states FeNa/FeUrea have “limited overall clinical utility” (Practice Point 2.5.4).
Bottom line: A urine sediment with muddy brown casts gives more diagnostic information than FeNa. Spin the urine and look at it yourself before calculating indices.
Clinical Pearl: Hyaline casts in concentrated urine from an oliguric patient represent a strong indicator of prerenal azotemia.
INTRARENAL AKI (Primary Kidney Damage)
Intrarenal AKI encompasses multiple distinct pathologic processes affecting different kidney compartments: glomeruli, tubules, and interstitium.
Acute Tubular Necrosis (ATN)
Mechanisms:
- Ischemic ATN (most common, ~50% of hospitalized AKI)
- Results from prolonged hypotension or severe volume depletion
- Damages tubular epithelial cell membrane
- Causes tubular obstruction from cellular debris
- Creates tubular leak of filtered glomerular filtrate
- Nephrotoxic ATN (endogenous toxins)
- Hemoglobin-induced: Massive intravascular hemolysis
- Myoglobin-induced: Rhabdomyolysis (muscle breakdown)
- Light chains: Plasma cell disorders (multiple myeloma)
Key Laboratory Findings: | Test | Finding | Significance | |——|———|————-| | Fractional Excretion of Sodium | >2% | Loss of tubular reabsorption | | Urine specific gravity | <1.015 | Loss of concentrating ability | | Urine osmolality | ~300 mOsm/kg | Isoosmotic with plasma |
Urine Microscopy — Recognize a Tubular Injury Pattern: - Muddy brown granular casts — strongly support tubular injury and result from tubular debris - Renal tubular epithelial cells (RTECs) and RTEC casts - RBC casts, if present, raise concern for glomerular disease; their absence does not exclude it - KDIGO 2026 draft emphasizes urine microscopy as superior to FeNa/FeUrea for AKI diagnosis. A trained examiner can identify patterns that urine indices cannot resolve; neither a bland sample nor a single sediment finding settles every cause of AKI.
Clinical Pearl: “Muddy brown” casts strongly support acute tubular injury. Review ischemic, septic, drug, and pigment exposures; the sediment pattern does not identify the specific cause or prove that more fluid is appropriate.
Rapidly Progressive Glomerulonephritis (RPGN)
Clinical Urgency: This is a NEPHROLOGIC EMERGENCY requiring rapid diagnosis and treatment to preserve kidney function.
Pathophysiology: Severe glomerular injury causes crescent formation (proliferating cells in Bowman’s space), destroying filtration capacity within days.
Key Findings: - Rapidly rising creatinine (often doubling within days to weeks) - Active urinary sediment: RBCs, dysmorphic RBCs, RBC casts, proteinuria - May present with systemic symptoms (hemoptysis, arthralgia, rash)
Urine Microscopy: Shows numerous RBCs, RBC casts, and WBCs indicating active glomerular bleeding.
Classification (by immunofluorescence pattern): 1. Anti-GBM disease (linear IgG) — Goodpasture syndrome 2. Immune complex RPGN (granular staining) — lupus, post-infectious 3. ANCA-associated vasculitis (pauci-immune) — MPO-ANCA or PR3-ANCA
Diagnostic Evaluation: - ANCA panel (MPO, PR3 antibodies) - Anti-GBM antibodies - Complement levels (C3, C4) - Kidney biopsy for definitive diagnosis
Critical Point: Combination of rapidly rising creatinine + active sediment with RBC casts = emergency requiring immediate nephrology referral and biopsy within 24-48 hours.
Acute Interstitial Nephritis (AIN)
Mechanism: Immune-mediated inflammatory response affecting the tubulointerstitium, most commonly from medications.
Common causative agents: - Antibiotics (amoxicillin, ciprofloxacin) — most common - Proton pump inhibitors (omeprazole) - NSAIDs - Diuretics - Allopurinol
Clinical Presentation: - May include fever, rash, eosinophilia (but absent in ~2/3 of cases) - AKI typically develops days to weeks after drug initiation - Usually nonoliguric (maintenance of urine output despite rising creatinine)
Urine Findings: - Mild proteinuria (usually <1 g/day) - Elevated WBCs (>5 cells/hpf, often 13-138 cells/µL) - White blood cell casts (supportive but not diagnostic) - Note: Urine eosinophils lack diagnostic utility (poor sensitivity/specificity)
Definitive Diagnosis: Kidney biopsy showing lymphoplasmacytic infiltration of interstitium with sparing of glomeruli.
Treatment: Early discontinuation of offending agent + corticosteroids (if started within 2-3 weeks, better outcomes).
Clinical Pearl: Classic triad of fever, rash, eosinophilia occurs in <10% of drug-induced AIN cases.
Light Chain Nephropathy
Association: Multiple myeloma or other plasma cell disorders.
Mechanism: Overproduction of monoclonal light chains causes tubular obstruction and direct toxic injury.
Key Features: - AKI in setting of myeloma (confirmed by serum/urine protein electrophoresis) - Urine shows characteristic large, fractured casts with angular edges - Diagnosis requires kidney biopsy for pathologic confirmation
Urine Microscopy: Look for characteristic large casts with angular fracture patterns.
POSTRENAL AKI (Urinary Obstruction)
Mechanism: Mechanical blockade of urine flow at any level from renal pelvis to urethral meatus.
Common causes: - Nephrolithiasis (kidney stones) - Malignancy with urinary tract compression - Benign prostatic hyperplasia (in males) - Blood clots or papillary necrosis - Retroperitoneal fibrosis
Clinical Features: - Colicky flank pain (with stones) or silent obstruction - May have oliguria, anuria, or paradoxical polyuria (with partial obstruction) - Suprapubic distention or flank mass on examination
Diagnostic Approach: 1. First-line: Renal ultrasound (no radiation, rapid assessment for hydronephrosis) 2. Important caveat: Early obstruction (<24 hours) may show minimal dilatation on ultrasound 3. Definitive: CT scan without contrast for precise obstruction location (especially stone detection) 4. Alternative: MR urography for soft tissue evaluation (pregnant patients, retroperitoneal masses)
Urine Microscopy: Usually minimal abnormalities in pure obstruction; may show crystals, RBCs (stone trauma), or WBCs (concurrent infection).
Clinical Pearl: Retroperitoneal fibrosis can cause functional obstruction without classical hydronephrosis pattern on imaging.
Special Emergency Situations
Anuria (Urine Output <100 mL/24 hours)
Clinical Significance: Nephrologic emergency requiring immediate evaluation and intervention.
Differential Diagnosis Includes: - Bilateral renal artery stenosis/occlusion (consider in patients with severe atherosclerosis) - Bilateral renal vein thrombosis (nephrotic syndrome, severe dehydration) - Complete bilateral urinary obstruction (emergency decompression needed) - Acute cortical necrosis (ominous sign, poor prognosis)
Immediate Management: 1. Bladder catheterization to rule out lower urinary tract obstruction 2. Urgent imaging (renal US, CT angiography as indicated) 3. Emergency nephrology consultation 4. Prepare for possible emergent intervention or dialysis
Acute Cortical Necrosis
Severity: Most severe form of AKI; necrosis of renal cortex with medullary sparing.
Triggers: - Severe prolonged hypotension - Septic shock - Obstetric catastrophes (placental abruption, postpartum hemorrhage) - Severe dehydration in infants
Clinical Recognition: - Anuria or severe oliguria with gross hematuria - Flank pain - Chronic phase: characteristic “rim-like” calcification on imaging
Prognosis: Poor; most patients require chronic dialysis.
Special Topic: Contrast-Associated Acute Kidney Injury
Paradigm Shift: “Contrast-induced nephropathy” has been renamed “contrast-associated AKI” (CA-AKI) to reflect the understanding that multiple factors—not contrast alone—contribute to injury.
Risk Factors: - Chronic kidney disease - Diabetes mellitus - Volume depletion - Heart failure - Concurrent nephrotoxin exposure
Presentation: Non-oliguric ATN developing 24-72 hours post-contrast, with peak elevation 3-5 days.
Prevention Strategies: - Most important: Adequate hydration with isotonic crystalloid - Minimize contrast volume - Use iso-osmolar or low-osmolar agents - Avoid concurrent nephrotoxins when possible - N-acetylcysteine prophylaxis: controversial, minimal benefit in recent studies
CRITICAL Concept: eGFR is INVALID in AKI (KDIGO 2026 draft Rec 2.3.2)
The eGFR on the BMP is a STEADY-STATE equation. It assumes creatinine production equals creatinine excretion — a condition that is not met when creatinine is actively rising or falling. This means:
- During AKI, the eGFR printed on the BMP is WRONG. Ignore it.
- A patient whose creatinine goes from 1.0 to 2.0 in 24 hours may have a true GFR near zero, while the BMP cheerfully prints “eGFR 38 mL/min.” That number is dangerously misleading.
- Conversely, during AKI recovery, eGFR will underestimate true kidney function because creatinine is lagging behind.
Kinetic eGFR (KeGFR): KDIGO 2026 draft recommends KeGFR (Recommendation 2.3.2, Grade 2B), which accounts for the rate of creatinine change to estimate GFR during non-steady-state conditions. However, the evidence base is small with no large RCTs validating its use.
The practical lesson for the wards: 1. IGNORE the eGFR on the BMP during AKI — it will mislead you 2. Track the creatinine TREND — the trajectory IS your GFR estimate 3. A rising creatinine = declining GFR; a plateauing creatinine = GFR stabilizing at a new level 4. KeGFR can be calculated if you need a number, but the trend alone guides most clinical decisions
Kidney Functional Reserve (KDIGO 2026 draft PP 2.3.1)
Concept: Kidney functional reserve (KFR) describes the difference between the maximal achievable GFR (under protein or amino acid loading) and the baseline resting GFR. Patients with low KFR have kidneys operating near their ceiling — with minimal capacity to compensate for additional insults.
Clinical relevance: - Patients with reduced KFR are at higher risk for AKI when exposed to nephrotoxins, surgery, or hemodynamic stress - KFR assessment may be useful before planned nephrotoxic exposures (e.g., cisplatin, major cardiac surgery, iodinated contrast in high-risk patients) - Standard eGFR does not capture reserve — two patients with the same eGFR of 60 may have vastly different reserves
Practical application: While formal KFR testing (protein loading with GFR measurement) is not yet routine, the concept reinforces why baseline CKD patients are disproportionately vulnerable to AKI. Consider KFR conceptually when risk-stratifying patients before nephrotoxic exposures.
Renal Doppler Ultrasound and POCUS in AKI (KDIGO 2026 draft)
Renal Resistive Index (RRI) — Practice Point 2.5.8
What it is: Renal Doppler ultrasound measures the resistive index (RRI) of intrarenal arteries: RRI = (peak systolic velocity - end diastolic velocity) / peak systolic velocity.
Clinical utility: - Elevated RRI (>0.70-0.75) indicates increased intrarenal vascular resistance - May help differentiate prerenal from intrinsic AKI — persistently elevated RRI despite volume resuscitation suggests structural injury - Serial RRI measurements can track AKI recovery - Useful in transplant kidneys to detect early rejection or vascular complications
Limitations: Operator-dependent, affected by heart rate, extrarenal vascular disease, and hydronephrosis. Should be interpreted alongside clinical context, not in isolation.
Point-of-Care Ultrasound (POCUS) — Practice Point 2.5.9
Role in AKI evaluation: - Volume assessment: IVC diameter and collapsibility to guide fluid management (prerenal vs. volume overload) - Cardiac function: Rapid assessment of LV function, pericardial effusion - Kidney imaging: Kidney size, echogenicity, hydronephrosis — at the bedside without waiting for radiology - Lung assessment: B-lines indicating pulmonary edema (fluid overload in oliguric AKI)
KDIGO 2026 draft endorses POCUS as a valuable bedside tool in AKI assessment, complementing traditional imaging.
The Furosemide Stress Test: A Functional Assessment Tool
Purpose: Predicts AKI progression and guides clinical decision-making by evaluating tubular function.
Principle: Furosemide requires active tubular secretion (not glomerular filtration) to work; response reflects tubular integrity.
Standardized Protocol: 1. Confirm adequate resuscitation (volume replete) before testing 2. Administer 1.0 mg/kg IV furosemide (loop diuretic-naive patients) 3. OR 1.5 mg/kg if prior furosemide exposure within 7 days 4. Measure urine output hourly for 2-6 hours 5. Interpret based on 2-hour urine volume
Clinical Interpretation: - FST-responsive (>200 mL in 2 hours): Low risk of progression; only 13.6% require RRT - FST-nonresponsive (<200 mL in 2 hours): High risk; 75-98% require renal replacement therapy
Diagnostic Performance: - Sensitivity: 81% for AKI progression prediction - Specificity: 88% for AKI progression prediction - Predicts: progression to Stage 3 AKI, need for RRT, and inpatient mortality
Clinical Application: Can identify patients with severe intrinsic renal failure in whom urine output becomes an unreliable perfusion marker, helping avoid futile fluid resuscitation.
Systematic Diagnostic Approach to AKI
Step 1: Clinical Assessment
- Volume status: Euvolemia? Dehydration? Edema/fluid overload?
- Hemodynamics: BP, orthostatics, perfusion signs
- Recent medications: NSAIDs, ACE inhibitors, diuretics, nephrotoxic drugs
- Relevant history: Prior renal disease? Diabetes? Systemic illness?
Step 2: Laboratory Evaluation (First-Tier)
- Complete metabolic panel (electrolytes, creatinine, BUN, calcium, phosphorus)
- IGNORE the eGFR on the BMP — it is a steady-state equation and is INVALID when creatinine is changing. Track the creatinine trend instead.
- Urinalysis (specific gravity, proteinuria, hematuria, WBCs)
- Fresh urine microscopy (structural clues interpreted with the clinical course and imaging)
- Complete blood count
Step 3: Urinalysis Interpretation
Matches the clinical context with microscopy findings to narrow differential: | Microscopy Pattern | Most Likely Diagnosis | Key Finding | |—|—|—| | Hyaline casts, no cells | Prerenal AKI | Preserved tubular function | | Muddy brown casts, RTECs | Acute tubular necrosis | Tubular damage | | RBC casts, dysmorphic RBCs | RPGN or GN | Glomerular bleeding | | WBC casts, WBCs | Acute interstitial nephritis | Tubulointerstitial inflammation | | Large fractured casts | Light chain disease | Associated with myeloma |
Step 4: Calculate Fractional Excretion (if appropriate — see limitations)
FENa (%) = [(Urine Na x Plasma Cr) / (Plasma Na x Urine Cr)] x 100 - FENa <1% suggests prerenal physiology; FENa >2% suggests intrinsic renal disease - Best studied in oliguric patients without CKD or recent diuretic use; not a standalone diagnosis - Confounded by CKD, sepsis, contrast, early obstruction - FeUrea does NOT reliably overcome the diuretic limitation (KDIGO 2026 draft PP 2.5.4) - In most clinical scenarios, urine microscopy provides better diagnostic information than FeNa
Step 5: Imaging (if indicated)
- Renal ultrasound: First-line for obstructive symptoms
- Renal Doppler with RRI: Consider when prerenal vs. intrinsic differentiation unclear after volume resuscitation (PP 2.5.8)
- POCUS: Bedside volume status (IVC), cardiac function, lung B-lines, kidney size/hydronephrosis (PP 2.5.9)
- CT without contrast: For stone, obstruction detail
- MR urography: Soft tissue, pregnant patients
Step 6: Additional Tests Based on Clinical Context
- Urine and serum protein electrophoresis (light chain disease)
- ANCA/anti-GBM (RPGN)
- Complement levels (post-infectious GN)
- Creatine kinase (rhabdomyolysis)
Practice Questions
Question 1: A 65-year-old with CKD Stage 3b presents with AKI. Urinalysis shows muddy brown granular casts and renal tubular epithelial cells. BUN:Cr ratio is 15:1. FENa is 3.2%. What is the most likely diagnosis? A) Prerenal AKI B) Acute tubular necrosis C) Acute interstitial nephritis D) Rapidly progressive glomerulonephritis
Answer: B) Acute tubular injury (often called ATN) is most likely because the sediment contains muddy brown casts and tubular epithelial cells. FENa and the BUN:creatinine ratio are supporting clues, not independent proof, and CKD can affect their interpretation. Assess exposures, perfusion, and the kidney-function trend.
Question 2: A 28-year-old presents with hemoptysis, arthralgia, hematuria, and rapidly rising creatinine (baseline 0.9, now 2.1 in 3 days). Urinalysis shows proteinuria and RBC casts. What is the most appropriate immediate next step? A) Start prednisone 1 mg/kg B) Urgent nephrology referral for kidney biopsy C) Ultrasound to rule out obstruction D) Measure FENa to assess tubular function
Answer: B) Urgent nephrology referral for kidney biopsy. The constellation of rapidly progressive AKI with active urinary sediment (RBC casts) and systemic symptoms (hemoptysis, arthralgia) suggests rapidly progressive glomerulonephritis—a nephrologic emergency. Biopsy is essential for diagnosis and guides immunosuppressive therapy. Delays >48 hours risk permanent kidney loss.
Question 3: A 58-year-old with hypertension and diabetes develops AKI after starting an ACE inhibitor for proteinuria. Urinalysis is bland; urinary specific gravity is 1.003. Which additional finding is most compatible with sodium avidity, while still requiring clinical assessment of the AKI mechanism? A) FENa of 0.6% B) Urine WBC casts C) Fever and rash D) Recent NSAID use
Answer: A) FENa of 0.6% is compatible with sodium avidity, but does not prove prerenal AKI or exclude intrinsic disease. Specific gravity 1.003 is dilute, not the concentrated urine classically expected with intact water conservation in volume depletion. Review perfusion, volume status, medications, obstruction risk, sediment, and the creatinine trend before assigning a cause or giving fluids. WBC casts or fever/rash may support inflammation but are also not definitive.
Key Takeaways
- Classify first: Prerenal, intrarenal, or postrenal — this shapes management
- Fresh microscopy and FENa provide complementary clues. FENa performs best in oliguric AKI without CKD or diuretics; low values do not exclude GN, pigment or tubular injury, and high values do not prove ATN. Interpret the clinical course and imaging.
- RPGN is an emergency: Rapidly rising creatinine + RBC casts = biopsy urgently
- Fresh microscopy and FENa provide complementary clues. FENa performs best in oliguric AKI without CKD or diuretics; low values do not exclude GN, pigment or tubular injury, and high values do not prove ATN. Interpret the clinical course and imaging.
- eGFR on the BMP is INVALID in AKI: Steady-state equation. Track the creatinine trend instead. Ignore the printed eGFR number.
- Kidney functional reserve matters: Patients with low reserve are vulnerable to nephrotoxic insults even with “normal” eGFR
- POCUS and renal Doppler are endorsed bedside tools for volume assessment and AKI differentiation
- The furosemide stress test helps predict progression and guides RRT timing
- AKI and CKD overlap: Consider acute-on-chronic disease patterns
- Medications matter: NSAIDs, ACE inhibitors, and antibiotics are common culprits
See Also
Clinical Content (01-Clinical-Medicine/Nephrology)
- AKI Hub - Full Clinical Reference
- Kidney Biopsy Guide
- Essential Renal Laboratory Tests
- Acid-Base Disorders in AKI
Atomic Notes (ZK)
- CRRT Principles
- Cell Cycle Arrest Biomarkers in AKI
- Cardiorenal Syndrome
Butler-COM Resources
- Butler COM - Nephrology Deep Dive
FENa and fresh microscopy: interpret the pattern
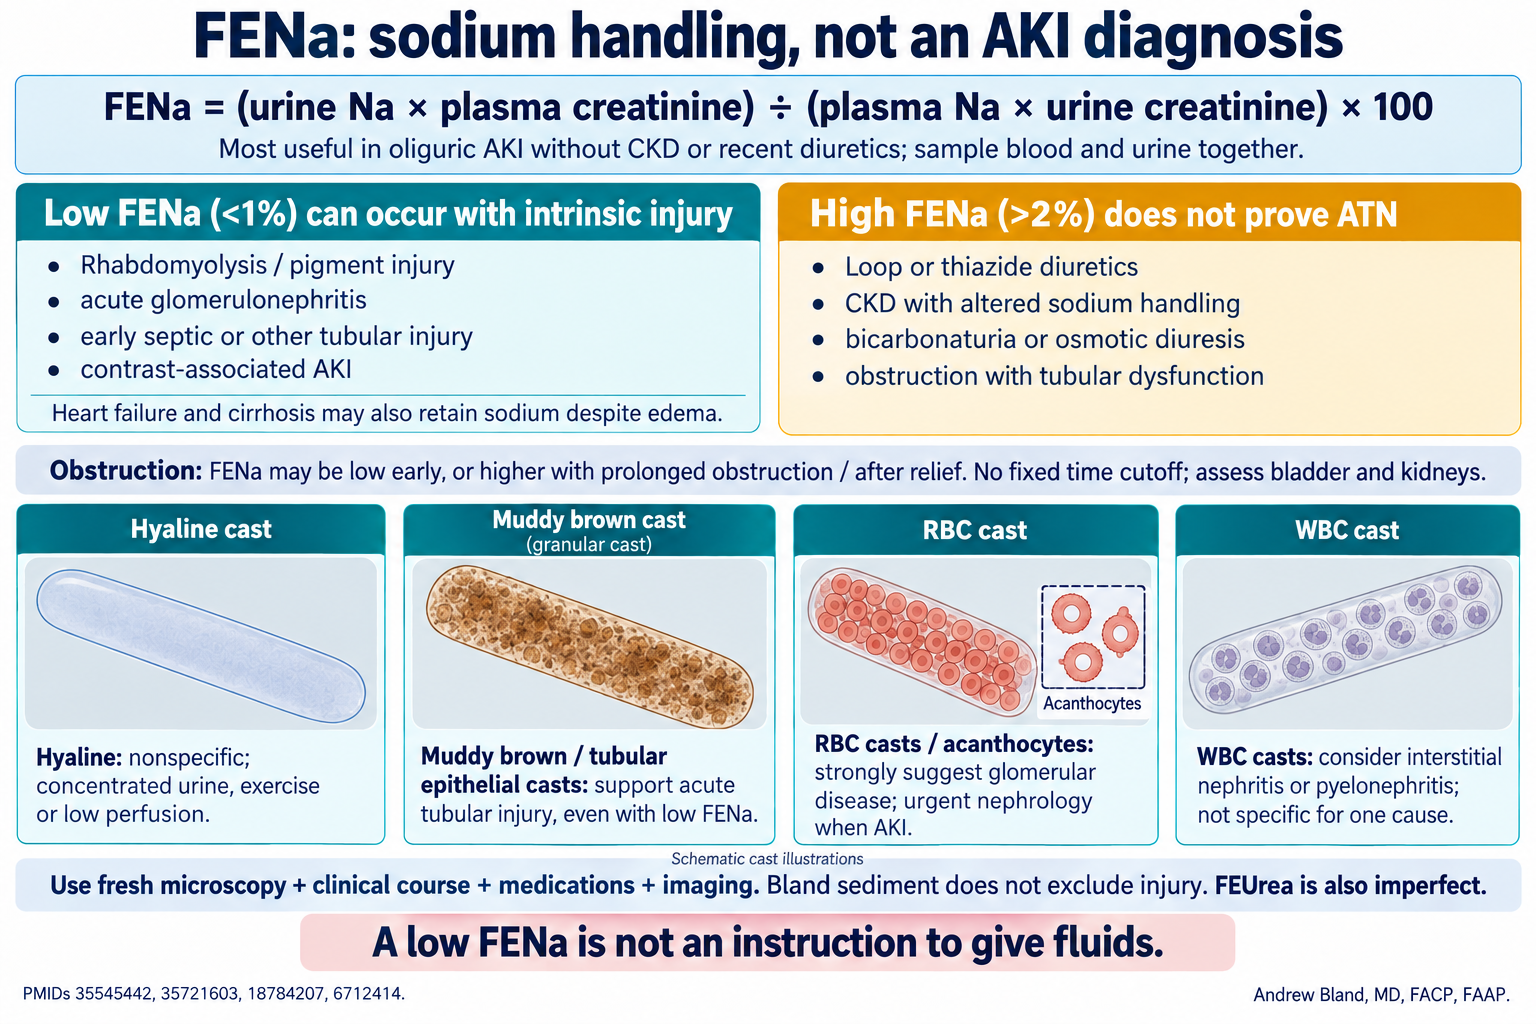
FENa diagnostic review, 2022 — PubMed · Varghese et al., muddy brown casts with low FENa — PubMed · Perazella et al., urine microscopy — PubMed · Corwin et al., pigment AKI with low FENa — PubMed · Zarich et al., FENa exceptions — PubMed · Cox et al., loop diuretics alter FEUrea — PubMed
Read diagram text and evidence
FENa = (urine sodium × plasma creatinine) / (plasma sodium × urine creatinine) × 100, using contemporaneous specimens and matching units. It describes sodium handling. Conventional low (<1%) and high (>2%) bands are clues with overlap, not diagnostic boundaries. Performance is best in oliguric AKI without CKD or recent diuretics.
Low FENa can occur in rhabdomyolysis/pigment injury, acute GN, septic or other tubular injury and contrast-associated AKI. Heart failure and cirrhosis can retain sodium despite edema. High FENa may reflect loop/thiazide diuretics, CKD adaptation, bicarbonaturia or osmotic diuresis rather than ATN. Obstruction can produce low FENa early and higher values with tubular dysfunction or after relief; duration is one influence, not a reliable clock. Assess bladder and kidneys regardless of FENa.
Fresh microscopy adds structural clues. Hyaline casts are nonspecific. Muddy brown granular casts and renal tubular epithelial cells/casts support tubular injury even with a low FENa. RBC casts or acanthocytes strongly suggest glomerular disease; AKI with active nephritis needs urgent nephrology assessment. WBC casts raise interstitial nephritis or pyelonephritis but do not distinguish them alone. Casts are schematics, not diagnostic photomicrographs. Bland sediment does not exclude injury, and operator/sample quality matters. FEUrea can also change with diuretics and is not a definitive rescue test. A low FENa is not an instruction to give fluids.
Andrew Bland, MD, FACP, FAAP