Acute Tubular Necrosis (ATN): Ischemic & Nephrotoxic Patterns
Updated March 2026 to reflect KDIGO 2026 draft AKI/AKD guideline recommendations.
Visual reference
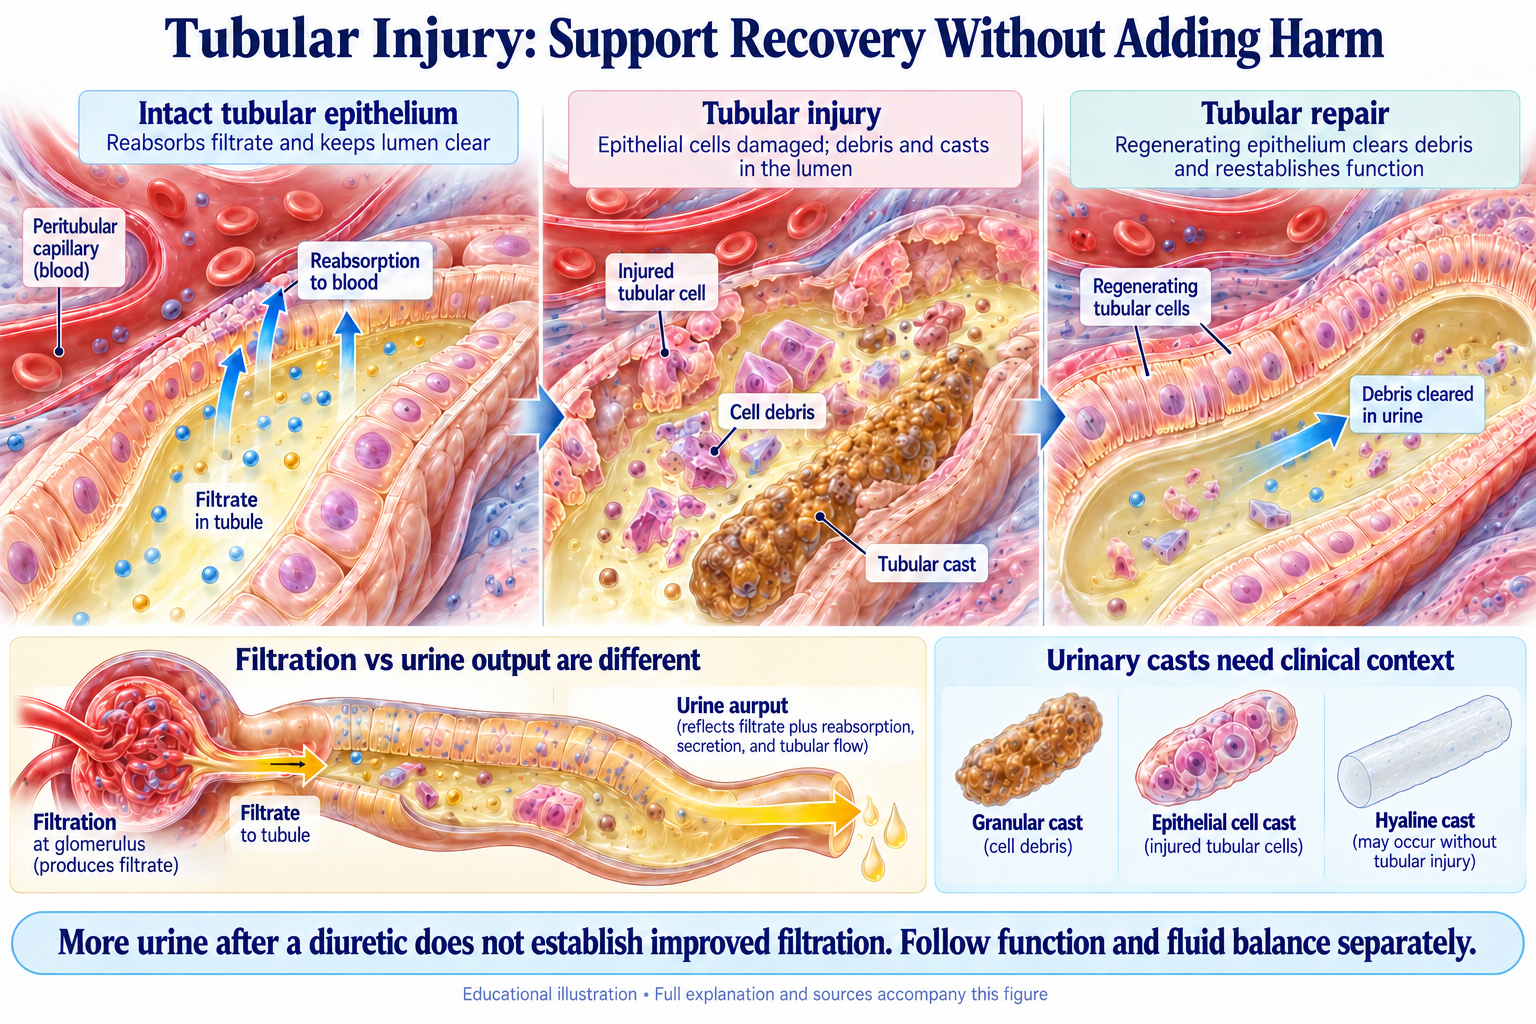
Browse the visual reference library · Download lesson Markdown
Definition & Epidemiology
ATN is acute injury to the proximal and distal tubular epithelium from either: 1. Ischemia (shock, sepsis, major surgery) → 45–50% of ATN 2. Nephrotoxins (drugs, pigments, contrast) → 35–40% of ATN 3. Combined (sepsis + aminoglycosides) → 15–20%
ATN is the #1 cause of intrinsic AKI in ICU (50% of ICU AKI cases). Unlike AIN, damage is necrotic (tubular epithelial death), not inflammatory.
Key feature of ATN: Tubular epithelial cells DIE and slough into urine. Diagnosis confirmed by muddy brown casts (hemoglobin- or myoglobin-laden cellular debris).
Pathophysiology: The Three Phases
Phase 1: Initiation (0–24 hours)
Ischemic ATN: - Reduced renal perfusion → hypoxia in proximal tubule (S3 segment = most vulnerable) - ATP depletion → loss of Na-K-ATPase function - Cellular swelling, brush border loss, cell death
Nephrotoxic ATN: - Direct tubular epithelial toxicity (aminoglycoside, myoglobin, hemoglobin) - ROS generation, mitochondrial dysfunction - Tubular obstruction (pigment casts in pigmenturia) - Sodium handling may be impaired; pigment injury can still have FENa below 1%
Phase 2: Maintenance (1–3 weeks)
- Continued GFR decline despite removal of offending agent
- Persistent tubular dysfunction
- Tubular obstruction from casts
- Back-leak of glomerular filtrate across damaged epithelium
- Urine output variable: Oliguric (40%) vs non-oliguric (60%)
- Oliguric = worse prognosis (higher mortality, longer recovery)
Phase 3: Recovery (1–4 weeks)
- Tubular epithelial regeneration (cells redifferentiate)
- Restoration of tight junctions, brush border, transporter function
- GFR gradually improves
- Timeline: Non-oliguric recovers in 1–3 weeks; oliguric in 3–8 weeks
Clinical pearl: If patient enters oliguric ATN phase, mortality risk ↑ 2–3× despite same initial AKI severity. Early RRT, tight fluid balance, and avoidance of secondary insults critical.
Ischemic ATN: Hypoperfusion Patterns
Classic Scenarios
- Cardiogenic shock — MI, acute decompensated HF, severe bradycardia
- Septic shock — vasodilation + hypovolemia
- Major surgery — especially bypass, vascular surgery
- Massive hemorrhage — inadequate fluid resuscitation
- Aortic dissection/cross-clamp — renal artery occlusion
Tubular Vulnerability: The S3 Segment
Proximal tubule has 3 segments: - S1 & S2: Glucose, amino acid reabsorption; better oxygenation - S3 ( proximal straight tubule ): High Na reabsorption, low oxygen supply → FIRST to die in hypoxia
Tubular injury may impair sodium reabsorption, but FENa can remain low, including in pigment or septic injury.
Laboratory & Urinalysis Signature
- Fresh microscopy can strongly support tubular injury, including when FENa is low. Interpret sample quality, clinical context and the limitations of both FENa and FEUrea. See the updated teaching figure below.
- Fresh microscopy can strongly support tubular injury, including when FENa is low. Interpret sample quality, clinical context and the limitations of both FENa and FEUrea. See the updated teaching figure below.
- Granular casts (coarse or fine — tubular protein + cells)
- Urine osmolality: <400 mOsm/L (tubular concentration failure)
- No hematuria or proteinuria >3 g/day (unless rhabdo)
Fresh microscopy can strongly support tubular injury, including when FENa is low. Interpret sample quality, clinical context and the limitations of both FENa and FEUrea. See the updated teaching figure below.
Nephrotoxic ATN: Drug & Pigment Mechanisms
Aminoglycoside-Induced ATN
Mechanism: - Uptake by proximal tubule via megalin/cubilin (high specificity) - Accumulation in lysosomes → generation of free radicals - Dose-dependent (correlates with cumulative dose) - Onset: 2–5 days (sometimes up to 2 weeks)
Risk factors: - Age >70, female - CKD or DM baseline - Volume depletion, sepsis - Concurrent nephrotoxins (vancomycin, amphotericin, NSAIDs)
Prevention: - Extended-interval dosing (15 mg/kg Q24-48h) safer than conventional divided dosing - Monitor aminoglycoside levels (peak, trough) - Check baseline renal function, adjust dose - Avoid polypharmacy with other nephrotoxins
Contrast-Induced Nephropathy (CIN) / Contrast-Associated AKI (CA-AKI)
Mechanism: - Osmotic load → tubular obstruction, hypoxia, ROS - Direct tubular epithelial toxicity (rare with modern iso-osmolar agents)
Risk stratification (KDIGO): - High risk: eGFR <30, DM + CKD, elderly, dehydration, CHF - Moderate risk: eGFR 30–60 - Low risk: eGFR >60, no DM, young
Prevention (evidence-based): 1. Hydration: IV isotonic saline 1–1.5 L before/after (best prevention) 2. Hold metformin 48h post-contrast if Cr ↑ 3. Avoid NSAIDs × 48h post-contrast 4. Use iso-osmolar or low-osmolar agents if possible 5. Minimize contrast volume (not >5 mL/kg body weight)
Bicarbonate, N-acetylcysteine, theophylline: NOT proven effective in recent RCTs. Hydration + careful dosing sufficient.
Rhabdomyolysis & Myoglobinuria-Induced ATN
Mechanism: - Muscle breakdown → myoglobin release (molecular weight 17 kDa, filtered freely) - Myoglobin precipitation in acidic tubular fluid (forms casts) - Tubular obstruction + direct cytotoxicity - Dark urine (cola-colored); dipstick+ for blood BUT no RBCs on microscopy
Severity assessment: CK above 5 times the upper limit of normal or above 1,000 IU/L supports rhabdomyolysis, but a CK band does not define kidney injury severity. Assess creatinine trend, urine output, potassium, acid–base status, perfusion, and the cause.
Common causes: - Trauma, crush injuries, prolonged immobilization - Statin-induced (especially with gemfibrozil or other CYP3A4 inhibitor) - Statins + NSAIDs + AKI precipitant - Exertional (extreme exercise, heat stroke, malignant hyperthermia) - Infections (influenza, HIV, EBV), seizures
Management: Treat the cause and assess for compartment syndrome. Give isotonic crystalloid when resuscitation is indicated, with repeated assessment of perfusion, urine output, and lungs. Do not force a urine-output target with continued fluid in persistent anuria or overload. Routine bicarbonate or mannitol is not recommended to prevent AKI; acidic urine alone is not an indication. Monitor CK, creatinine, potassium/ECG, calcium, phosphate, and acid–base status. KRT is for refractory hyperkalemia, severe acidemia, pulmonary edema, or uremic complications. AAST consensus.
Clinical pearl: Early recognition and treatment of hypovolemia can reduce risk, but fluids do not guarantee prevention of AKI. CK above 1,000 with dark urine calls for prompt assessment; the fluid prescription depends on perfusion, kidney function, and congestion.
Cisplatin & Other Chemotherapy-Induced ATN
Mechanism: - Cisplatin: Nephrotoxicity in S3 proximal tubule; cumulative dose-dependent; up to 35% patients develop AKI - Amphotericin B: Lipid formulations safer; conventional more toxic - Ifosfamide, methotrexate, gemcitabine: Variable toxicity
Prevention: Use the oncology regimen’s saline hydration and electrolyte protocol, with baseline and follow-up creatinine, magnesium, and other electrolytes and repeated volume assessment. Mannitol is an option in selected cisplatin regimens under local protocol, not a requirement for all patients; routine forced diuresis is not established. Review NSAIDs, other nephrotoxins, and medicines that affect perfusion with the treatment team. eviQ cisplatin prevention guidance.
Hemoglobinuria-Induced ATN (Intravascular Hemolysis)
Mechanism: Hemoglobin precipitates in acidic tubular fluid; same mechanism as myoglobin
Causes: - Massive transfusion reaction - Prosthetic valve hemolysis - Microangiopathic hemolytic anemia (MAHA) - Snake bite envenomation
Diagnostic clue: - Dipstick+ for blood, but RBC count <3 on microscopy - Serum LDH ↑, haptoglobin ↓, indirect bilirubin ↑
Management: Identify and treat the hemolysis cause urgently, support perfusion with reassessment, and manage electrolyte/AKI complications. Routine urinary alkalinization should not be inferred from the pigment mechanism alone.
Clinical Decision Tree: Ischemic vs Nephrotoxic ATN
ATN Suspected (muddy brown granular casts on microscopy support tubular injury in context; FeNa supportive but not required)
    │
    ├─ ISCHEMIC ATN?
    │  History: shock, sepsis, major surgery, cardiogenic event
    │  Timing: AKI coincides with hypotensive episode
    │  Exam: Hypotension (current or recent), cool extremities
    │  Labs: Lactate ↑, base deficit, CK normal, urine myoglobin−
    │  Prognosis: 60–80% recover; ICU patients have 20–60% mortality (multiorgan failure)
    │
    └─ NEPHROTOXIC ATN?
       History: aminoglycoside, contrast, rhabdo, hemolysis, cisplatin
       Timing: AKI 2–7 days post-drug
       Exam: Normal BP if volume replete
       Labs:
         └─ If myoglobin/hemoglobin: Dark urine, dipstick+/RBC−, CK ↑↑, LDH ↑
       Prognosis: Better if toxic agent removed early; rhabdo/hemolysis: mortality 10–30%
Management Principles (Both Types) — Updated per KDIGO 2026 draft
Acute Phase
- Remove trigger: Stop drug, restore perfusion, treat shock
- Fluid resuscitation: Buffered crystalloids preferred over 0.9% NaCl (KDIGO 2026 draft Rec 3.1.2, 1B) — except in traumatic brain injury where NS remains appropriate
- Hemodynamic targets:
- MAP ≥65 mmHg (KDIGO 2026 draft Rec 3.2.1, 2C) — individualize; higher targets not proven beneficial
- No low-dose dopamine for renal protection (KDIGO 2026 draft Rec 3.2.2, 1A) — unchanged from prior guidelines but frequently violated in practice. Low-dose dopamine does not prevent, treat, or improve outcomes in AKI.
- Avoid secondary hits: No NSAIDs, ACE-I, nephrotoxins, contrast
Volume Management & Diuretics (KDIGO 2026 draft)
KDIGO 2026 draft formally endorses diuretics in AKI — a shift from prior guideline ambiguity.
- Diuretics for volume overload in AKI (Rec 3.3.1, 2B) — use to treat fluid overload, not to “prevent” AKI or convert oliguric to non-oliguric
- Try diuretics BEFORE extracorporeal fluid removal (Rec 3.3.2, 1C) — give the patient a chance to respond to diuretics before initiating ultrafiltration or RRT for volume alone
- Intermittent IV boluses as initial strategy (PP 3.3.1) — start with bolus dosing before continuous infusion
Furosemide Stress Test (FST) — now guideline-recommended (KDIGO 2026 draft Rec 2.3.1, 2B–2C): - 1.0 mg/kg IV furosemide (1.5 mg/kg if prior loop diuretic use) - Urine output <200 mL in 2 hours = high risk for severe AKI / need for RRT - Useful for prognostication and triage in AKI Stage 2–3
Diuretic Escalation Pathway (KDIGO 2026 draft Table 22):
| Step | Strategy | Details |
|---|---|---|
| 1. Assessment | Evaluate volume status | Clinical exam, urine output trend, lung ultrasound |
| 2. Escalation | Increase loop diuretic dose | Double furosemide dose if inadequate response; switch to bumetanide if gut edema |
| 3. Synergism | Add thiazide (sequential nephron blockade) | Metolazone 5–10 mg PO or chlorothiazide 500 mg IV 30 min before loop diuretic |
| 4. Intensify | Continuous infusion | Furosemide 10–40 mg/h after bolus loading dose |
| 5. Failure → RRT | Diuretic resistance | If escalation pathway fails, proceed to extracorporeal fluid removal |
Maintenance Phase
- Monitor K, Ca, PO4, Mg daily
- Renal dosing medications
- Nutrition: 30 kcal/kg/day, 1–1.2 g/kg/day protein (catabolic state)
RRT Timing (KDIGO 2026 draft)
- Deferred (watchful waiting) RRT preferred over early/preemptive initiation (Rec 5.1.1, 1C) — unless life-threatening indications exist (refractory hyperkalemia, severe acidosis, uremic symptoms, refractory volume overload after diuretic escalation)
- Initiate RRT for emergent indications regardless of timing strategy
Recovery Phase
- Watch for recovery-phase diuresis if oliguric phase (may occur during recovery)
- Continue supportive care even as Cr improves
- Follow-up: ~50% develop CKD long-term; monitor at 3–6 months
Board-Style Questions
- 35M post-MVA with crush injury to leg; CK 120,000; dark urine; Cr 0.8 → 2.6 in 8h
- Diagnosis: Rhabdomyolysis-induced ATN
- Immediate management: assess trauma/compartment syndrome, potassium/ECG, perfusion, and kidney function; give volume-guided crystalloid if indicated with repeated lung/urine-output assessment. Do not routinely add bicarbonate for urine alkalinization; escalate for clinical KRT indications.
- 72F post-cardiac angiography; baseline Cr 1.2; now Cr 1.8; muddy brown casts; FeNa 3%
- Diagnosis: Contrast-induced ATN (CA-AKI)
- Prevention for future: Hydration, minimize contrast, hold metformin
- Pt on gentamicin × 10 days for sepsis; AKI onset day 5; FeNa 2.5%; granular casts
- Diagnosis: Aminoglycoside-induced ATN
- Action: Switch to alternative AB, aggressive hydration, consider RRT
Version 2.0 | PA/Medical student level | Updated 2026-03-29 per KDIGO 2026 draft AKI/AKD Guidelines
References: Kellum et al. Acute kidney injury (2021); KDIGO 2012 AKI guideline; Koyner et al. Furosemide Stress Test and Biomarkers for the Prediction of AKI Severity (2015).
FENa and fresh microscopy: interpret the pattern
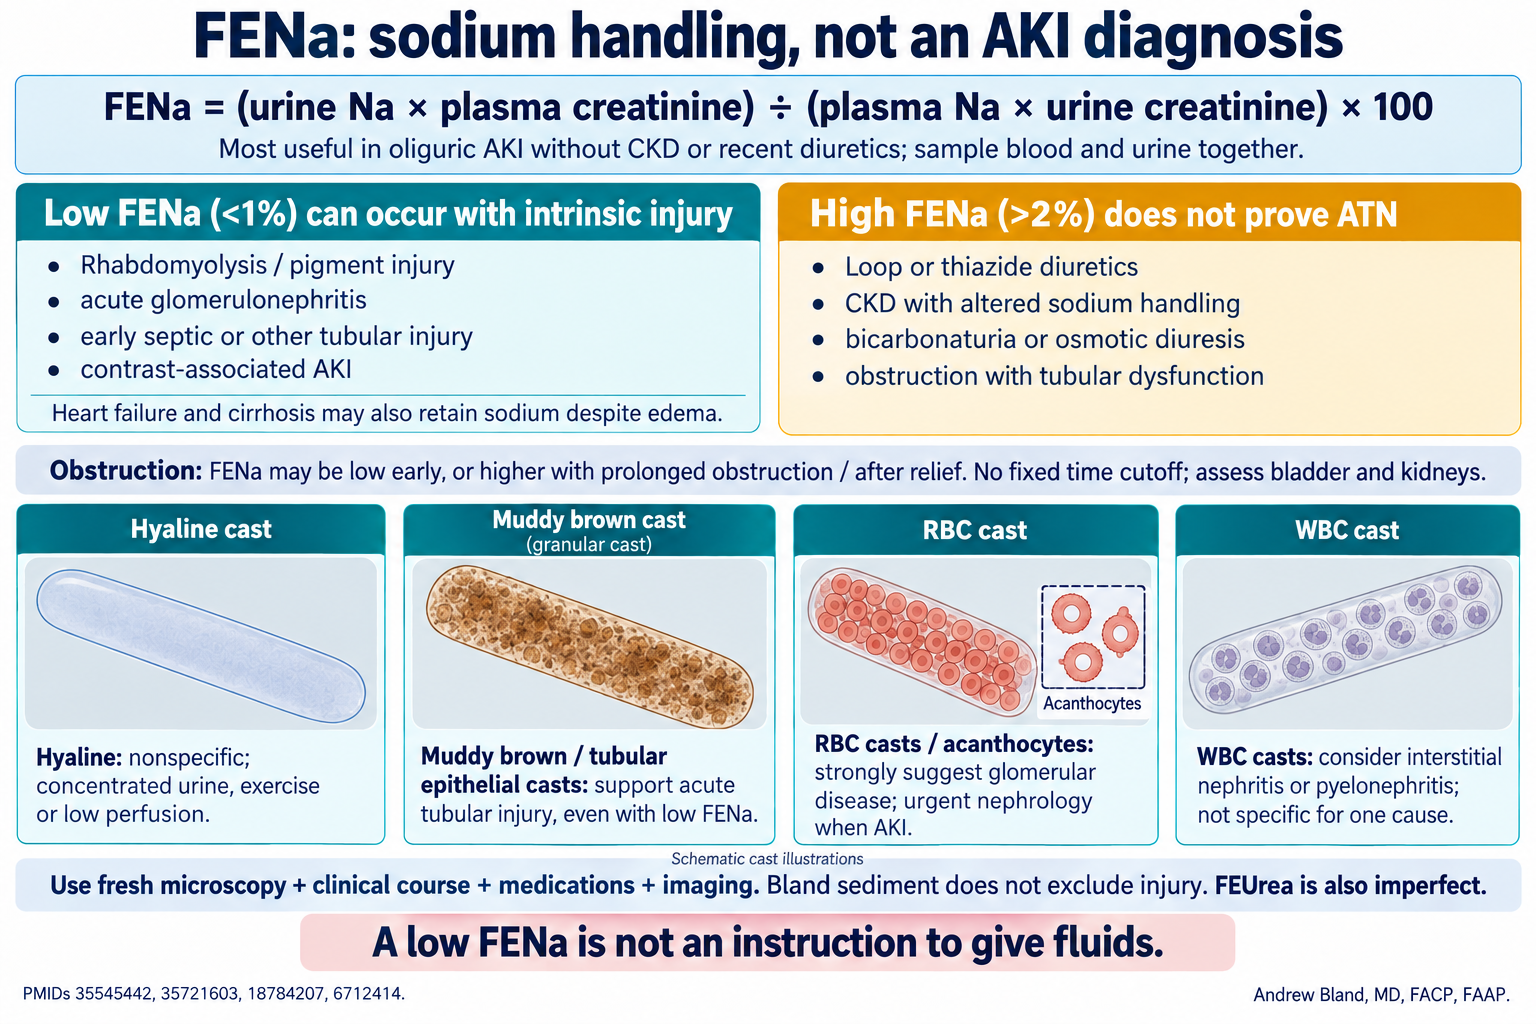
FENa diagnostic review, 2022 — PubMed · Varghese et al., muddy brown casts with low FENa — PubMed · Perazella et al., urine microscopy — PubMed · Corwin et al., pigment AKI with low FENa — PubMed · Zarich et al., FENa exceptions — PubMed · Cox et al., loop diuretics alter FEUrea — PubMed
Read diagram text and evidence
FENa = (urine sodium × plasma creatinine) / (plasma sodium × urine creatinine) × 100, using contemporaneous specimens and matching units. It describes sodium handling. Conventional low (<1%) and high (>2%) bands are clues with overlap, not diagnostic boundaries. Performance is best in oliguric AKI without CKD or recent diuretics.
Low FENa can occur in rhabdomyolysis/pigment injury, acute GN, septic or other tubular injury and contrast-associated AKI. Heart failure and cirrhosis can retain sodium despite edema. High FENa may reflect loop/thiazide diuretics, CKD adaptation, bicarbonaturia or osmotic diuresis rather than ATN. Obstruction can produce low FENa early and higher values with tubular dysfunction or after relief; duration is one influence, not a reliable clock. Assess bladder and kidneys regardless of FENa.
Fresh microscopy adds structural clues. Hyaline casts are nonspecific. Muddy brown granular casts and renal tubular epithelial cells/casts support tubular injury even with a low FENa. RBC casts or acanthocytes strongly suggest glomerular disease; AKI with active nephritis needs urgent nephrology assessment. WBC casts raise interstitial nephritis or pyelonephritis but do not distinguish them alone. Casts are schematics, not diagnostic photomicrographs. Bland sediment does not exclude injury, and operator/sample quality matters. FEUrea can also change with diuretics and is not a definitive rescue test. A low FENa is not an instruction to give fluids.
Andrew Bland, MD, FACP, FAAP