Guideline-Directed Medical Therapy: Four Pillars of Cardiorenal Protection
Visual reference
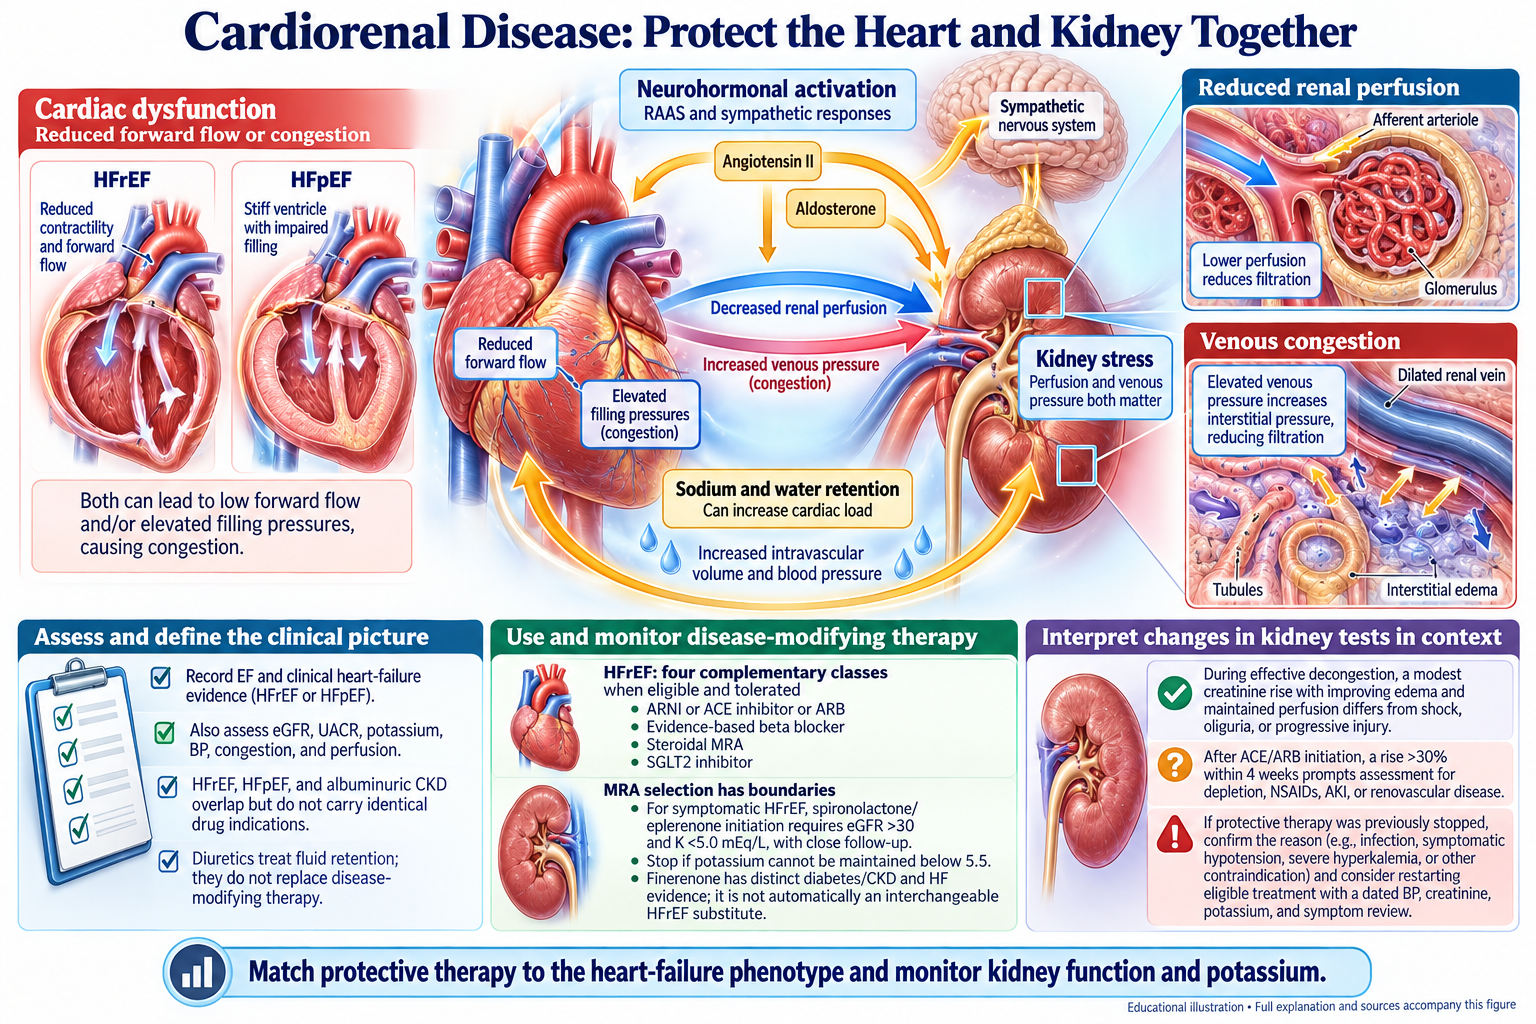
Browse the visual reference library · Download lesson Markdown
Learning Objectives
By the end of this session, identify the four foundational HFrEF drug classes, choose appropriate RAAS therapy, distinguish HFrEF from HFpEF and CKD indications, initiate treatment promptly in eligible stable patients, and plan monitoring and illness-related medication review.
The Four Pillars: Overview
The four foundational classes below apply to eligible patients with HFrEF. HFpEF and CKD use overlapping medicines with different indications; do not apply the entire HFrEF regimen automatically.
| HFrEF class | Examples | Key use and safety |
|---|---|---|
| ARNI, or ACE inhibitor/ARB when appropriate | Sacubitril/valsartan; indicated alternatives | Use one RAAS strategy; monitor BP, potassium, and kidney function |
| SGLT2 inhibitor | Dapagliflozin, empagliflozin | Benefits eligible HFrEF patients with or without diabetes; check agent-specific eligibility |
| Steroidal MRA | Spironolactone, eplerenone | HFrEF eligibility generally eGFR >30 and potassium <5.0; monitor closely |
| Evidence-based beta-blocker | Carvedilol, metoprolol succinate, bisoprolol | Start/titrate when clinically stable; monitor heart rate, BP, and congestion |
Expected Outcomes with Optimal Therapy
Benefits depend on population, endpoint, comparator, and follow-up. Do not add relative reductions from separate trials or promise a universal mortality reduction or NNT of 4 from counting drug classes.
Pillar 1: Choose RAAS Therapy for the Indication
For eligible symptomatic HFrEF, ARNI is preferred when feasible. ACE inhibitors or ARBs remain appropriate alternatives in specified circumstances; CKD treatment selection also depends on albuminuria, tolerability, and safety.
ACE Inhibitors vs. ARBs: A Critical Distinction
ACE inhibitors: Have outcome evidence in HFrEF and albuminuric CKD. A percentage or NNT from one meta-analysis cannot prove universal superiority over ARBs across different populations.
ARBs: Are evidence-based alternatives when ARNI is not feasible and ACE inhibitors are not tolerated, and have important albuminuric-CKD indications. Avoid combined ACE inhibitor/ARB therapy.
Clinical pearl: Choose therapy using the HFrEF guideline and contraindications. ARNI should not be used with an ACE inhibitor or in patients with a history of angioedema; ACE intolerance needs individualized review.
Special Consideration: RAAS Inhibitors in CKD
CKD: Either an ACE inhibitor or an ARB may provide kidney protection in appropriately selected albuminuric CKD. Titrate the chosen agent as tolerated with BP, potassium, and creatinine monitoring.
Approach: An eligible HFrEF patient need not first reach a target ACE-inhibitor dose before ARNI or other foundational therapy is considered. Use at least a 36-hour separation when switching between an ACE inhibitor and ARNI.
Angiotensin Receptor-Neprilysin Inhibitors (ARNIs)
The New Gold Standard
Sacubitril/valsartan combines: - Valsartan (ARB component) - Sacubitril (neprilysin inhibitor)
PARADIGM-HF: Sacubitril/valsartan reduced first CV death/HF hospitalization versus enalapril (21.8% vs 26.5%; HR 0.80). All-cause death was 17.0% vs 19.8% (HR 0.84). NNT about 21 refers to the primary composite over trial follow-up, not one death prevented. Trial.
How it Works: - Valsartan blocks angiotensin II (like ARB) - Sacubitril inhibits neprilysin (which normally breaks down natriuretic peptides) - Result: Enhanced natriuretic peptide signaling PLUS angiotensin blockade = synergistic benefit
ACE inhibitor–ARNI transition: The prescribing information requires at least 36 hours between doses when switching in either direction. Never overlap them. CKD does not establish a universal 5–7-day washout rule; assess renal dosing, BP, potassium, and contraindications. Label.
Clinical pearl: Sacubitril/valsartan already contains an ARB; discontinue separate ACE inhibitor/ARB therapy when switching, with the required ACE-inhibitor washout.
Pillar 2: SGLT2 Inhibitors—The Game Changer
SGLT2 inhibitors benefit eligible people across multiple HF and CKD trial populations, with or without diabetes. They are not suitable for every patient; indication, agent-specific eGFR limits, volume status, ketoacidosis risk, and contraindications matter.
Mechanism: Elegantly Simple, Powerfully Effective
Normal kidney: SGLT2 mediates most proximal glucose reabsorption; SGLT1 reabsorbs the remainder.
SGLT2 inhibitor effect: 1. Natriuresis & diuresis without RAAS activation (unlike loop diuretics which trigger neurohormonal compensation) 2. Reduced renal hypoxia by decreasing metabolic workload on proximal tubule 3. Hemodynamic adjustment through afferent arteriole vasoconstriction (reduces intraglomerular pressure—this is BENEFICIAL long-term) 4. Metabolic reprogramming creating fasting-like state
Clinical Evidence Across the Spectrum
| Trial | Studied population | Main lesson |
|---|---|---|
| DAPA-HF | HFrEF | 26% reduction in CV death/worsening HF; kidney composite was not significantly reduced |
| EMPEROR-Reduced | HFrEF | Reduced CV death/HF hospitalization and slowed eGFR decline |
| EMPEROR-Preserved | HF with LVEF >40% | 21% reduction in CV death/HF hospitalization; kidney composite not significantly reduced |
| DAPA-CKD | Albuminuric CKD, with or without T2D | 39% reduction in the primary kidney/CV-death composite; not exclusively kidney failure |
| EMPA-KIDNEY | Broad eligible CKD population | 28% reduction in kidney progression/CV death; HF hospitalization/CV death alone was not significantly reduced |
Expected Changes on SGLT2 Inhibitors
Expected changes: A small early eGFR dip and modest BP reduction can occur. Review volume status and the trend; a large or progressive decline, hypotension, or acute illness needs assessment. Genital fungal infection is an adverse effect to recognize and treat, not a desired response.
Urgent red flags: Nausea, vomiting, abdominal pain, malaise, or rapid breathing may signal ketoacidosis even with near-normal glucose. Stop the SGLT2 inhibitor and obtain urgent assessment if suspected; severe genital/perineal pain, swelling, or fever also needs emergency evaluation.
Which Agent to Choose?
Dapagliflozin: The usual HF/CKD dose is 10 mg daily. US labeling does not recommend initiation below eGFR 25; established treatment may continue below 25 for cardiorenal indications when appropriate. Distinguish this from glucose-lowering eligibility.
Empagliflozin: The usual HF/CKD dose is 10 mg daily. Major HF/CKD trials included eGFR down to 20; check current labeling and clinical eligibility. Do not assume either agent should be newly started on dialysis.
Choose the agent by its indication, studied population, current label, tolerability, and access; the trials are not identical.
Pillar 3: Mineralocorticoid Receptor Antagonists (MRAs)
Aldosterone blockade addresses the “final common pathway” of RAAS activation.
Steroidal MRAs: Established but Limited
Spironolactone (RALES Trial): - 30% mortality reduction in severe HFrEF - NNT = 10 (impressive!) - BUT: Gynecomastia in 10% of men, menstrual irregularities in women - High hyperkalemia risk (5-10% absolute increase)
Eplerenone (EMPHASIS-HF): - 37% reduction in CV death/HF hosp in mild HFrEF - More selective, fewer endocrine side effects - Still carries hyperkalemia risk
Non-Steroidal MRA: Finerenone (The Future)
Finerenone: A nonsteroidal MRA with distinct CKD-T2D and HF LVEF ≥40% indications. It causes less antiandrogenic activity than spironolactone but still increases hyperkalemia risk; FINEARTS-HF does not establish a head-to-head potassium-safety advantage over steroidal MRAs.
FINEARTS-HF: In 6,001 adults with HF and LVEF ≥40%, finerenone reduced total worsening-HF events plus CV death by 16% (rate ratio 0.84, 95% CI 0.74–0.95), not 29%. CV death alone was not significantly reduced; hyperkalemia was more common than with placebo. Trial.
MRA eligibility: For HFrEF, spironolactone/eplerenone generally require eGFR >30 and potassium <5.0. Finerenone is not an interchangeable substitute for this HFrEF evidence. In CKD with T2D, consider it for persistent albuminuria despite tolerated RAAS therapy when eligible; US labeling generally requires eGFR ≥25 and does not allow initiation if potassium >5.0. Its separate HF LVEF ≥40% indication also requires label-based selection and monitoring.
Pillar 4: Beta-Blockers
Three beta-blockers have proven mortality benefit in HFrEF:
| HFrEF beta-blocker | Selection |
|---|---|
| Carvedilol | Evidence-based option; consider BP and clinical stability |
| Metoprolol succinate | Evidence-based extended-release option |
| Bisoprolol | Evidence-based option |
These drugs have HFrEF outcome evidence. Percentages from different trials are not head-to-head comparisons of which beta-blocker is best.
Ejection fraction matters: Beta-blockers have established outcome evidence in HFrEF. HFmrEF decisions depend on the clinical phenotype and evidence; HFpEF alone is not a universal mortality indication. Rate control, ischemia, and other indications may still warrant treatment.
Implementation Strategy: Getting Patients to Optimal Therapy
Speed Matters
Evidence supports rapid sequential initiation rather than months-long titration:
Individualized early initiation: Introduce the four HFrEF classes at tolerated doses promptly in a clinically stable eligible patient, often over days to weeks with close follow-up. Do not wait for one class to reach target before starting another, or defer every MRA until weeks 4–12. BP, heart rate, congestion, eGFR, potassium, and access determine sequence and titration.
Expected Outcomes
Expected benefit: Comprehensive HFrEF therapy improves outcomes. The magnitude for an individual depends on baseline risk, medications already used, adherence, and follow-up.
A registry association or cross-trial model cannot establish a universal randomized NNT for quadruple therapy. State the endpoint and time horizon whenever reporting an absolute benefit.
The Critical Vulnerability: Sick Day Management
Acute illness can change perfusion, volume, potassium, and medication tolerance. Patients need an individualized illness plan and a clear route to clinical advice.
Why This Matters
During vomiting, diarrhea, poor intake, hypotension, or severe infection, assess dehydration versus congestion, BP, kidney function, potassium, and ketoacidosis risk. The appropriate response depends on the problem and the medicine.
Significant dehydration, AKI, hyperkalemia, or hemodynamic instability may require urgent assessment and temporary medication changes.
Sick Day Protocol
Medication review: Temporarily withhold SGLT2 inhibitors during prolonged fasting, major surgery, or critical illness and when ketoacidosis is suspected. ACE inhibitor/ARB/ARNI, MRA, and diuretic changes depend on hypotension, volume, AKI, and potassium; do not automatically stop all GDMT for every minor illness.
Other medicines: Beta-blocker continuation depends on hemodynamic stability and the treating team’s plan. Congestion may require continued diuresis; dehydration may require a different approach.
Restart plan: Reassess clinical stability, oral intake, volume, kidney-function trend, and potassium, with named follow-up and repeat labs where needed. CKD need not return to a normal eGFR; avoid unplanned permanent withdrawal of beneficial treatment.
Potassium safety: Check potassium and kidney function when clinically indicated during illness. Diet changes or potassium binders should follow an individualized clinical plan; severe symptoms or ECG changes require urgent treatment.
Clinical Pearls
- RAAS therapy follows the indication. ARNI is preferred for eligible HFrEF when feasible; ACE inhibitor/ARB alternatives remain useful.
- ACE inhibitor–ARNI washout is at least 36 hours in either direction. Never overlap; CKD is not a blanket indication for 5–7 days.
- SGLT2 benefit is broad but eligibility is specific. Check indication, eGFR, volume, and ketoacidosis risk.
- Interpret the eGFR trend. A small early dip may be expected; a large decline, hypotension, or acute illness needs review.
- MRA evidence is indication-specific. Spironolactone/eplerenone are HFrEF options; finerenone has distinct indications and monitoring.
- Create an illness plan. Specify symptoms, medication review, urgent contact, and restart follow-up rather than a blanket drug holiday.
- Initiate the four HFrEF classes early when eligible. Complementary mechanisms do not justify adding cross-trial percentages.
Practice Questions
Question 1: A 58-year-old with HFrEF (EF 32%) and eGFR 48 is on lisinopril 10 mg daily and furosemide 40 mg daily. Creatinine is stable. Which steps should you take next?
Answer: Assess BP, heart rate, congestion, potassium, contraindications, and follow-up capacity. If stable and eligible, introduce an SGLT2 inhibitor, an evidence-based beta-blocker, and a steroidal MRA (eGFR >30, potassium <5.0), and consider ARNI with at least 36 hours after the last lisinopril dose. Sequence and doses are individualized; do not wait for maximal lisinopril or a fixed week before adding other classes.
Question 2: A 72-year-old on full GDMT (lisinopril, SGLT2-i, MRA, beta-blocker) presents with 3-day history of vomiting and diarrhea from gastroenteritis. K+ is 5.2 mEq/L. What’s your advice?
Answer: Arrange prompt clinical assessment of volume, BP, creatinine, potassium, and possible ketoacidosis. SGLT2 therapy should be withheld during significant poor intake/illness; RAAS and MRA treatment may need temporary interruption according to AKI, BP, and potassium. Fluid replacement must account for HF and congestion; do not prescribe unrestricted salt/fluid loading. Specify repeat labs and a supervised restart plan.
Question 3: Why can an NNT from an ACE-inhibitor trial not be directly compared with a modeled NNT for four-drug therapy?
Answer: NNT depends on baseline risk, comparator, endpoint, absolute risk difference, and follow-up. Separate trial populations and time horizons do not support an “18 times more effective” claim or a universal NNT of 4.
Key Takeaways
✓ Four foundational classes improve HFrEF outcomes in eligible patients; benefits are not a fixed sum.
✓ Use ARNI or an appropriate ACE inhibitor/ARB alternative with contraindication and washout checks.
✓ SGLT2 inhibitors benefit many HF/CKD populations; apply drug-specific eligibility.
✓ Select the MRA for the indication and monitor potassium and kidney function.
✓ Introduce eligible HFrEF therapies promptly with an individualized sequence and follow-up.
✓ Illness plans include medication review and restart criteria; do not automatically stop all GDMT.
✓ Communicate absolute benefit with its endpoint and time horizon.
See Also
Clinical Content (01-Clinical-Medicine/Nephrology & Cardiology)
- Cardio-Renal Ecosystem Hub
- Heart Failure Clinical Reference
- CKD Hub - Full Clinical Reference
Atomic Notes (ZK)
- Cardiorenal Syndrome as Bidirectional Dysfunction
- RAAS System and Blood Pressure Regulation
Butler-COM Resources
- Butler COM - Nephrology Deep Dive
- Butler COM - Heart Failure GDMT Deep Dive