Heart Failure with Preserved EF: Cardiac, Kidney, and Metabolic Interactions
Visual reference
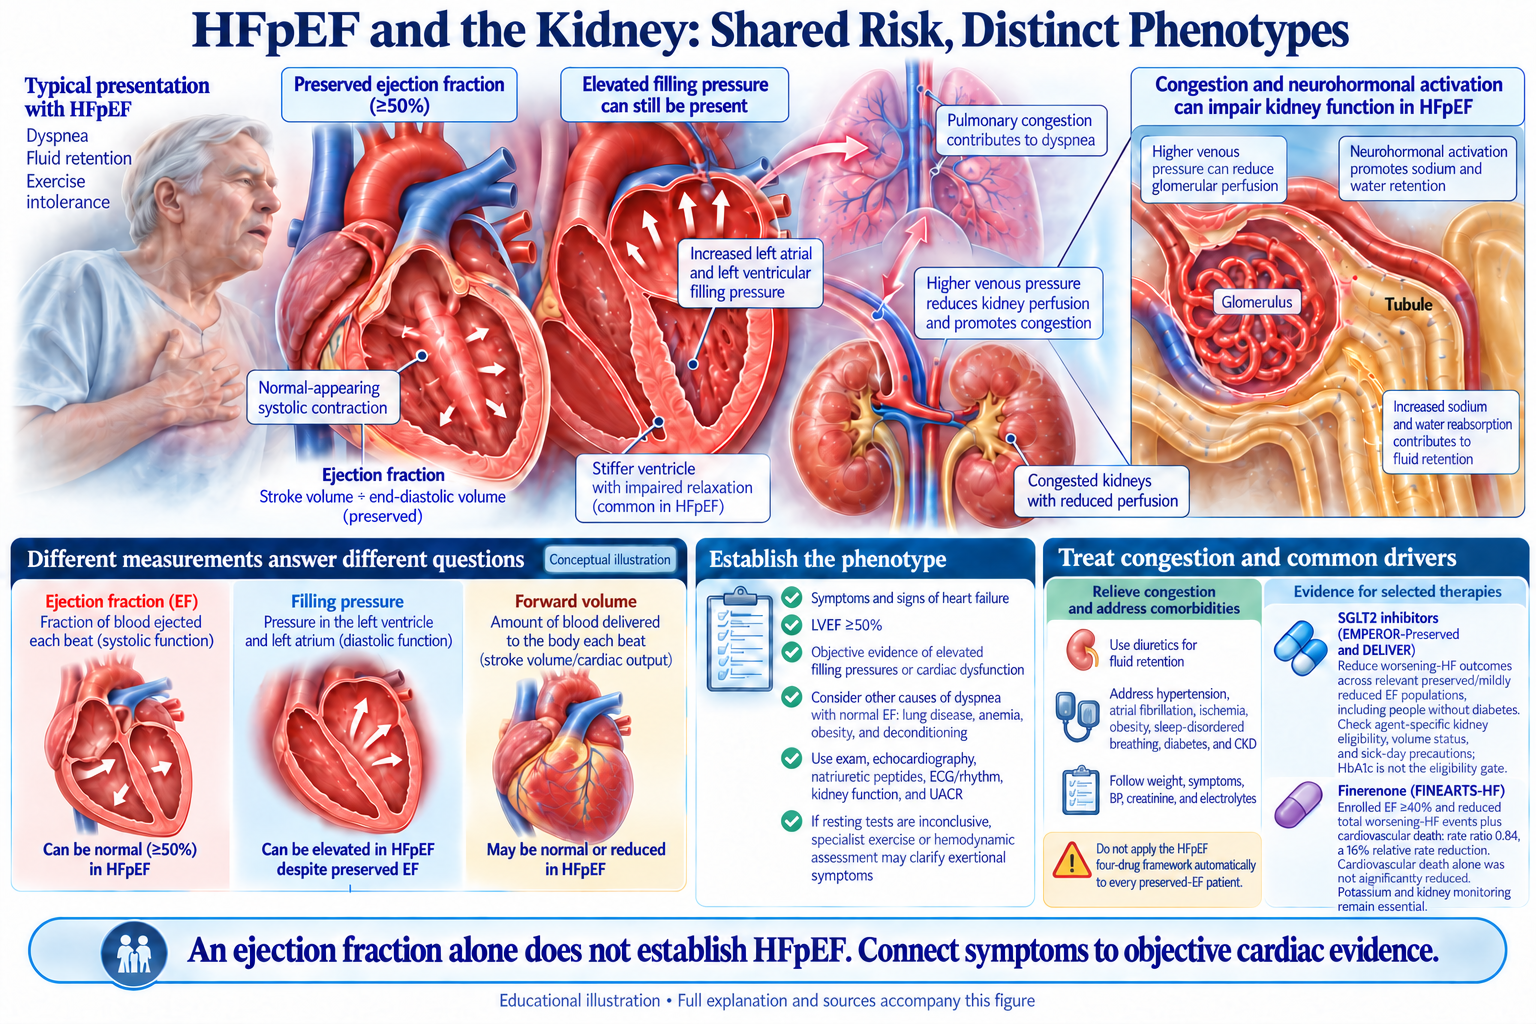
Browse the visual reference library · Download lesson Markdown
Learning Objectives
By the end of this session, you should be able to recognize heterogeneous HFpEF phenotypes; assess kidney function and albuminuria alongside cardiac findings; apply a validated diagnostic algorithm; distinguish trial endpoints from mechanisms; and select therapy using the patient’s phenotype, eligibility, and monitoring needs.
The Cardiorenal View: HFpEF Is a Heterogeneous Syndrome
An Incomplete Cardiac-Only View
“Patient has heart failure → their ejection fraction is preserved → it’s a purely cardiac problem”
An Integrated View
HFpEF reflects interacting cardiac, vascular, kidney, and metabolic abnormalities. CKD is common and can contribute, but HFpEF is not universally a primary kidney disease.
The Evidence
Temporal relationship: Kidney dysfunction can precede HFpEF and predicts risk; established heart failure can also worsen kidney function through congestion and perfusion changes. Association does not establish a single direction of causation.
Reversibility: Cardiac abnormalities may improve after kidney transplantation in selected patients. This does not establish kidney disease as the primary cause of all HFpEF or guarantee reversal.
Kidney tubular dysfunction: Tubular biomarkers are being studied as risk markers. They do not replace standard HFpEF diagnosis or establish a kidney-first mechanism in an individual patient.
Mineralocorticoid activation: MR signaling is one relevant pathway. A urine sodium-to-potassium ratio also reflects diet, diuretics, and kidney function; it is not a diagnostic test for MR-driven HFpEF.
Epidemiology: Why HFpEF Is Important
The Growing Problem
- 50%+ of heart failure cases now present with preserved EF (HFpEF)
- More common in:
- Older adults (age >70)
- Women
- Hypertension
- Obesity
- Chronic kidney disease
Why HFrEF Gets More Attention (But Shouldn’t)
- HFrEF: Well-established therapies, proven mortality benefits (GDMT)
- HFpEF: Trials have established benefits for HF events and, for selected therapies and phenotypes, symptoms; mortality claims require endpoint-specific evidence.
- Result: HFrEF heavily studied, HFpEF neglected
The Clinical Reality
HFpEF can cause substantial dyspnea, impaired quality of life, hospitalization, and death despite preserved EF. Comparisons with HFrEF depend on the cohort, comorbidities, and follow-up.
Pathophysiology: Bidirectional Cardiorenal and Metabolic Pathways
One Contributing Pathway: Mineralocorticoid Receptor Activation
In the kidney: - Hyperglycemia and obesity cause LIGAND-INDEPENDENT MR activation - This occurs even with normal aldosterone levels - Leads to distal nephron sodium retention and potassium loss
Systemic consequence: - Volume expansion → hypertension → concentric LVH - Central venous pressure elevation → “renal tamponade” (pressure backflow reduces GFR)
In the heart: - MR activation in cardiomyocytes causes TGF-β and inflammatory pathway activation - Results in cardiac fibrosis and diastolic dysfunction
The Paulus-Tschöpe Paradigm
Comorbidities (obesity, DM, hypertension, CKD) trigger:
- Systemic inflammation (IL-6, TNF-α, CRP)
- Endothelial dysfunction in coronary microvasculature
- Reduced nitric oxide bioavailability
- Impaired cGMP signaling → titin hypophosphorylation
- Cardiomyocyte stiffness → diastolic dysfunction
All of these mechanisms are also happening in the kidney, creating bidirectional organ damage.
Galectin-3: The Molecular Bridge
Galectin-3 is a protein that: - Precedes development of BOTH CKD and HFpEF - Mediates TGF-β signaling in fibrosis - Levels correlate with diastolic dysfunction severity - Reduced by MRA therapy
Clinical correlation: Galectin-3 remains a research and prognostic biomarker; a single threshold does not diagnose CKD or establish the cause of HFpEF.
The HFpEF Phenotype Map
Shah Phenomapping Study
Research identified THREE distinct HFpEF phenotypes with vastly different prognoses:
Phenotype 1: The original phenomapping study identified a younger group with less adverse remodeling. Observational clusters describe risk; they do not establish which treatment will work best.
Phenotype 2: A distinct metabolic/relaxation phenotype was identified. Pulmonary hypertension associated with left-heart disease does not automatically justify pulmonary arterial hypertension drugs.
Phenotype 3: Older patients with more CKD and adverse cardiac features had greater HF hospitalization risk (adjusted HR 4.2 in the original cohort). This was not a mortality effect estimate or a randomized demonstration of superior MRA response. Original study.
Clinical Pearl
The CKD-dominant phenotype—the highest risk group—is exactly the type of patient your nephrology colleagues see daily. This explains why nephrologists are essential in HFpEF management.
Albuminuria: An Important Risk Marker
Interpret Albuminuria Alongside eGFR
Albuminuria adds prognostic information even when eGFR is preserved. Use both measures and the clinical context rather than declaring one universally dominant.
ARIC Study (n=10,975): Incident heart failure risk by albuminuria status | UACR Category | Relative Risk | |—|—| | <5 mg/g (optimal) | Reference | | 5-9 mg/g (intermediate-normal) | 1.54 | | 10-29 mg/g (high-normal) | 1.91 | | 30-299 mg/g (microalbuminuria) | 2.49 | | ≥300 mg/g (macroalbuminuria) | 3.47 |
ARIC: Atherosclerosis Risk in Communities Study - see references for full citation
Clinical translation: Both preserved eGFR with substantial albuminuria and low eGFR with little albuminuria can carry important risk. Do not rank two patients’ absolute HF risk from those two measurements alone.
The “Albuminuria Paradox”
In adults with albuminuria and preserved eGFR: - Absolute risk of CV events >> risk of dialysis - Without intervention, more likely to suffer MI/stroke/HF hosp than to need dialysis - This explains why CV-protective therapy (SGLT2-i, GLP-1 RA) should be prioritized over “kidney-protective” strategies alone
KDIGO Heat Map: Integrated Cardiorenal Risk
The KDIGO GFR and albuminuria grid classifies CKD prognosis. It is not a table of fixed HF hazard ratios for every cell. G1–G2 with A1 does not establish CKD without another marker of kidney disease.
| GFR category | A1: UACR <30 mg/g | A2: 30–300 mg/g | A3: >300 mg/g |
|---|---|---|---|
| G1–G2 | Low risk if no other CKD marker | Moderately increased | High |
| G3a | Moderately increased | High | Very high |
| G3b | High | Very high | Very high |
| G4–G5 | Very high | Very high | Very high |
Key insight: Advanced CKD confers high cardiovascular risk. Choose prevention using the full clinical picture; CKD alone does not make every secondary-prevention intervention appropriate.
Diagnostic Approach to HFpEF
Three-Step Diagnosis
Step 1: Suspect HFpEF - Dyspnea + peripheral edema + preserved EF on echo - Risk factors: age >70, hypertension, obesity, CKD
Step 2: Biomarker assessment: Elevated natriuretic peptides support HFpEF, but normal values do not exclude it, especially with obesity. CKD and atrial fibrillation may raise values; interpret the assay and rhythm within a validated algorithm.
Step 3: Echocardiographic Confirmation - HFA-PEFF diagnostic algorithm (scores three domains: functional, morphological, biomarker) - Scores ≥5 = HFpEF confirmed - Scores 2-4 = further testing needed (stress echo or invasive)
HFA-PEFF: Use the Validated Domain Score
| Domain | Scoring principle |
|---|---|
| Functional | Use validated echo criteria; major criteria earn 2 points and minor criteria 1 |
| Morphological | Use rhythm- and sex-appropriate structural criteria |
| Biomarker | Use rhythm-appropriate natriuretic-peptide thresholds |
| Total | Maximum 2 points per domain; maximum 6 overall |
A total ≥5 supports definite HFpEF in the appropriate clinical setting; 2–4 calls for functional testing, and ≤1 makes HFpEF unlikely. Do not award a point for every abnormal measurement within one domain. HFA-PEFF consensus.
Evidence-Based Therapy for HFpEF
SGLT2 Inhibitors: Class I, Level A (2023 ESC)
EMPEROR-Preserved: Empagliflozin reduced first CV death or HF hospitalization by 21% (HR 0.79), primarily through fewer HF hospitalizations. It slowed eGFR decline, but the prespecified kidney composite was not significantly reduced. An eGFR-slope effect is not a 43% reduction in kidney failure. Trial.
DELIVER (Dapagliflozin): PubMed | Outcome | Benefit | |———|———| | CV death/worsening HF | 18% reduction | | Consistent benefit even in LVEF >60% | ✓ |
Clinical Pearl: SGLT2-i is the FIRST class of drug with proven Class I benefit in HFpEF. This is a major advance.
Finerenone: FINEARTS-HF (2024) PubMed
Study Design: 6,001 patients with symptomatic HF, LVEF ≥40%
FINEARTS-HF results: Finerenone reduced total worsening-HF events plus CV death by 16% (rate ratio 0.84, 95% CI 0.74–0.95). Total worsening-HF events were reduced by 18%; CV death alone was not significantly reduced (HR 0.93, 95% CI 0.78–1.11). The 18% figure is not a proven effect specific to LVEF >60%.
Hyperkalemia: Finerenone increased hyperkalemia compared with placebo. FINEARTS-HF was not a head-to-head comparison with SGLT2 inhibitors or steroidal MRAs; check potassium and kidney function according to the label.
Current US indication: Finerenone is indicated for adults with HF and LVEF ≥40%, subject to kidney-function and potassium eligibility and monitoring. This includes HFmrEF as well as HFpEF. Prescribing information.
ARNi (Sacubitril/Valsartan): PARAGON-HF PubMed
Study: Narrowly missed primary endpoint (p=0.059)
Subgroup interpretation: PARAGON-HF did not meet its primary endpoint overall. Signals in selected subgroups inform individualized decisions but do not prove a universal HFpEF benefit.
Clinical Use: Now FDA-approved across HF spectrum, with Class 2b recommendation for HFpEF. Most useful in women or those with mildly reduced EF.
Combination Therapy: Synergistic Approach
SGLT2 inhibitor plus finerenone: CONFIDENCE studied adults with type 2 diabetes, CKD, and albuminuria. Combination therapy reduced UACR more than either alone at 180 days. This surrogate-endpoint study did not establish combined HFpEF mortality or hospitalization benefit. Assess potassium, eGFR, volume, and follow-up capacity before starting either or both. CONFIDENCE.
SGLT2 inhibitor plus GLP-1 therapy: Select each drug for its demonstrated indication and the patient’s phenotype. Benefits from individual trials do not establish an additive HFpEF outcome effect for every combination.
Other Therapies: Treat the Indication
- Beta-blockers: Use for indications such as rate control, ischemia, or prior HFrEF; they are not a universal mortality therapy for HFpEF.
- ACE inhibitor/ARB: Use for appropriate blood-pressure, albuminuric-CKD, or other indications; do not transfer HFrEF mortality effects to all HFpEF.
- Diuretics: Treat congestion and improve symptoms; adjust to volume status and monitor kidney function and electrolytes.
CKM Framework Integration
Advanced CKD Signals High Cardiovascular Risk
The CKM framework integrates cardiovascular, kidney, and metabolic risk. Advanced CKD warrants careful cardiovascular prevention, but clinical CVD, overall risk, contraindications, and treatment indication still determine care. Do not prescribe every secondary-prevention treatment solely because eGFR is below 30.
Patient Communication Strategies
The “Heart and Kidney Work Together” Message
Accessible explanation: “Heart and kidney problems can affect each other. We will look at fluid balance, blood pressure, urine protein, and your other conditions, then choose medicines whose benefits apply to you.”
Risk Visualization Using AHA PREVENT Calculator
The PREVENT calculator incorporates eGFR and UACR to provide personalized 10-year and 30-year CV risk estimates. Showing patients their position on this risk spectrum motivates medication adherence.
KDIGO Heat Map for Patient Education
Show the patient their GFR and albuminuria categories. In the conventional CKD risk grid, yellow is moderately increased risk, orange is high risk, and red is very high risk; treatment aims to improve health rather than promise a particular color change.
Clinical Pearls
- HFpEF has multiple mechanisms. Kidney disease is an important contributor and comorbidity, not a universal primary cause.
- CKD identifies important risk. Observational phenogroups do not establish that CKD predicts the best response to a particular therapy.
- Measure UACR and eGFR together. Albuminuria matters even with preserved filtration; select evidence-based treatment rather than chase a surrogate in isolation.
SGLT2-i are Class I for HFpEF. For the first time, we have a proven therapy for HFpEF (unlike years of HFrEF focus).
Finerenone works in HFpEF. Unlike limited steroidal MRA data, finerenone showed consistent benefit across LVEF spectrum.
- Combination therapy requires selection and monitoring. CONFIDENCE supports greater short-term UACR reduction in studied T2D-CKD patients, not universal safety or proven combined HFpEF outcome benefit.
Nephrologists’ expertise is essential. Managing volume status, medication dosing in CKD, and cardiorenal interaction makes nephrologists ideal coordinators of HFpEF care.
Practice Questions
Question 1: A 72-year-old woman with hypertension, obesity (BMI 34), eGFR 42, UACR 180 mg/g presents with dyspnea on exertion. Echocardiography shows preserved EF (58%), E/e’ ratio 14, LA volume index 38 mL/m². NT-proBNP is 350 pg/mL. Diagnose and outline initial therapy.
Answer: HFpEF is strongly suspected. If she is in sinus rhythm, E/e’ 14 contributes 1 functional point, LAVI 38 contributes 2 morphological points, and NT-proBNP 350 contributes 2 biomarker points, giving 5. Rhythm matters and must be confirmed; do not invent other findings. Evaluate alternative causes, congestion, BP, kidney function, and potassium. Use an SGLT2 inhibitor if eligible; consider finerenone under its HF indication with label-based eligibility and monitoring. Individualize obesity/diabetes therapy and diuretics rather than require a fixed four-week sequence.
Question 2: Compare HFrEF and HFpEF in terms of: (a) patient demographics, (b) prognosis, (c) evidence-based therapies.
Answer: HFpEF often occurs in older people with hypertension, obesity, atrial fibrillation, and CKD. Both HFpEF and HFrEF carry substantial risk; mortality percentages depend on the population and follow-up. HFrEF has four foundational drug classes. HFpEF treatment includes SGLT2 inhibitors, congestion/comorbidity care, and phenotype-appropriate additional therapy such as finerenone for eligible adults with LVEF ≥40%. FINEARTS-HF is a trial result, not itself a Class I guideline designation.
Question 3: A patient with HFpEF, CKD stage 3b, hypertension, obesity, and T2DM asks why several medicines are being considered. Explain individualized combination therapy.
Answer: “These conditions interact, but each medicine has a specific purpose. We will choose treatments shown to help people with your conditions and check blood pressure, kidney function, potassium, and symptoms. The HFrEF four-pillar regimen does not automatically apply to everyone with HFpEF.”
Key Takeaways
✓ HFpEF is heterogeneous: assess cardiac, kidney, vascular, and metabolic contributors.
✓ CKD increases risk: it does not prove a superior response to a specific medicine.
✓ Use eGFR and UACR together for CKD risk and treatment eligibility.
✓ SGLT2 inhibitors are Class I for HFpEF (first proven therapy for this population)
✓ Finerenone provides additional benefit across full LVEF spectrum in HFpEF
✓ Combination evidence is population- and endpoint-specific; monitor safety rather than assume synergy.
✓ Coordinate heart and kidney care according to patient needs.
✓ Advanced CKD warrants cardiovascular prevention tailored to indications and risk.
See Also
Clinical Content (01-Clinical-Medicine/Nephrology & Cardiology)
- Cardio-Renal Ecosystem Hub
- CKD Hub - Full Clinical Reference
- Heart Failure Clinical Reference
- Hypertension Management
Atomic Notes (ZK)
- Cardiorenal Syndrome as Bidirectional Dysfunction
Butler-COM Resources
- Butler COM - Nephrology Deep Dive
- Butler COM - Heart Failure GDMT Deep Dive