Visual reference
Browse the visual reference library · Download lesson Markdown
Definition & Epidemiology
CKD-associated anemia (CKD-AA): Hemoglobin <13 g/dL in males, <12 g/dL in females with CKD, caused by EPO deficiency and reduced RBC lifespan.
Prevalence: - Stage 3b-4 CKD: ~45% prevalence - Stage 5 CKD: ~85% prevalence - Strongest predictor: Degree of GFR reduction
CKD-associated anemia is iron-deficient in ~60% of cases and must be distinguished from anemia of chronic disease. Iron supplementation is foundational.
Pathophysiology: The “Iron Trinity”
1. Erythropoietin (EPO) Deficiency (Primary)
- Kidneys produce ~90% of EPO (peritubular fibroblasts in renal cortex)
- GFR <45 → ↓ EPO production → reduced RBC precursor stimulation
- Loss correlates with degree of renal fibrosis, not just GFR
- Board point: EPO levels are relatively low-normal or low in CKD anemia (inappropriate for degree of anemia)
2. Iron Deficiency (Common Complicating Factor)
- Absolute iron deficiency: Depleted body iron stores (TSAT <20%, ferritin <100 ng/mL)
- Causes: GI blood loss, dialysis membrane loss, phlebotomy for labs
- Enteral iron absorption impaired in CKD (uremia, phosphate binders)
- Functional iron deficiency: Adequate body iron but EPO resistance due to impaired iron mobilization
- ESA therapy without concurrent iron repletion → worsening iron stores
3. Reduced RBC Lifespan (Moderate)
- Normal RBC lifespan: 120 days
- CKD RBC lifespan: 60-90 days (shortened by ~30-50%)
- Mechanisms: Uremic toxins, oxidative stress, altered RBC membrane
- Clinical significance: Even with normal EPO, RBC production cannot match increased turnover
4. Additional Contributing Factors
- Chronic inflammation: CRP, IL-6, TNF-α → hepcidin ↑ (blocks iron absorption)
- Nutritional deficiencies: B12, folate, copper
- Medications: ACE-I/ARB ↓ EPO; PPI ↓ iron absorption
- Comorbidities: Bleeding (GI ulcers, varices in liver disease), hemolysis
Clinical Presentation & Symptoms
| Symptom | Mechanism | Board Relevance |
|---|---|---|
| Fatigue, dyspnea | ↓ O2 carrying capacity | Most common presenting complaint |
| Restless leg syndrome | Iron deficiency + uremia | May improve with IV iron |
| Cognitive dysfunction | Chronic hypoxia | Improves with Hb correction |
| Reduced exercise tolerance | Blunted cardiac output response | QOL metric in trials |
| Palpitations, tachycardia | Compensatory ↑ HR | May precipitate arrhythmias if HTN |
Diagnostic Approach
When to Screen for Anemia in CKD
- GFR <60 mL/min/1.73m² → annual screening
- GFR 30-59 → at least annual
- GFR <30 → every 3-6 months (higher risk)
Don’t miss anemia in early CKD (GFR 45-60). EPO deficiency begins at GFR <60, but many clinicians only think about it at stage 4-5. Early treatment may improve outcomes.
Iron Status Assessment (Critical Before ESA Therapy)
| Test | Interpretation | Clinical Action |
|---|---|---|
| Serum ferritin | <100 ng/mL = depleted stores | Replete iron before ESA |
| Transferrin saturation (TSAT) | <20% = insufficient iron delivery | Use the population-specific ferritin/TSAT criteria below; in nondialysis CKD/PD choose oral or IV iron individually. |
| Serum iron | Variable; less specific | Use TSAT instead |
| Soluble transferrin receptor | >8.5 mcIU/mL = iron deficiency | More specific than ferritin in inflammation |
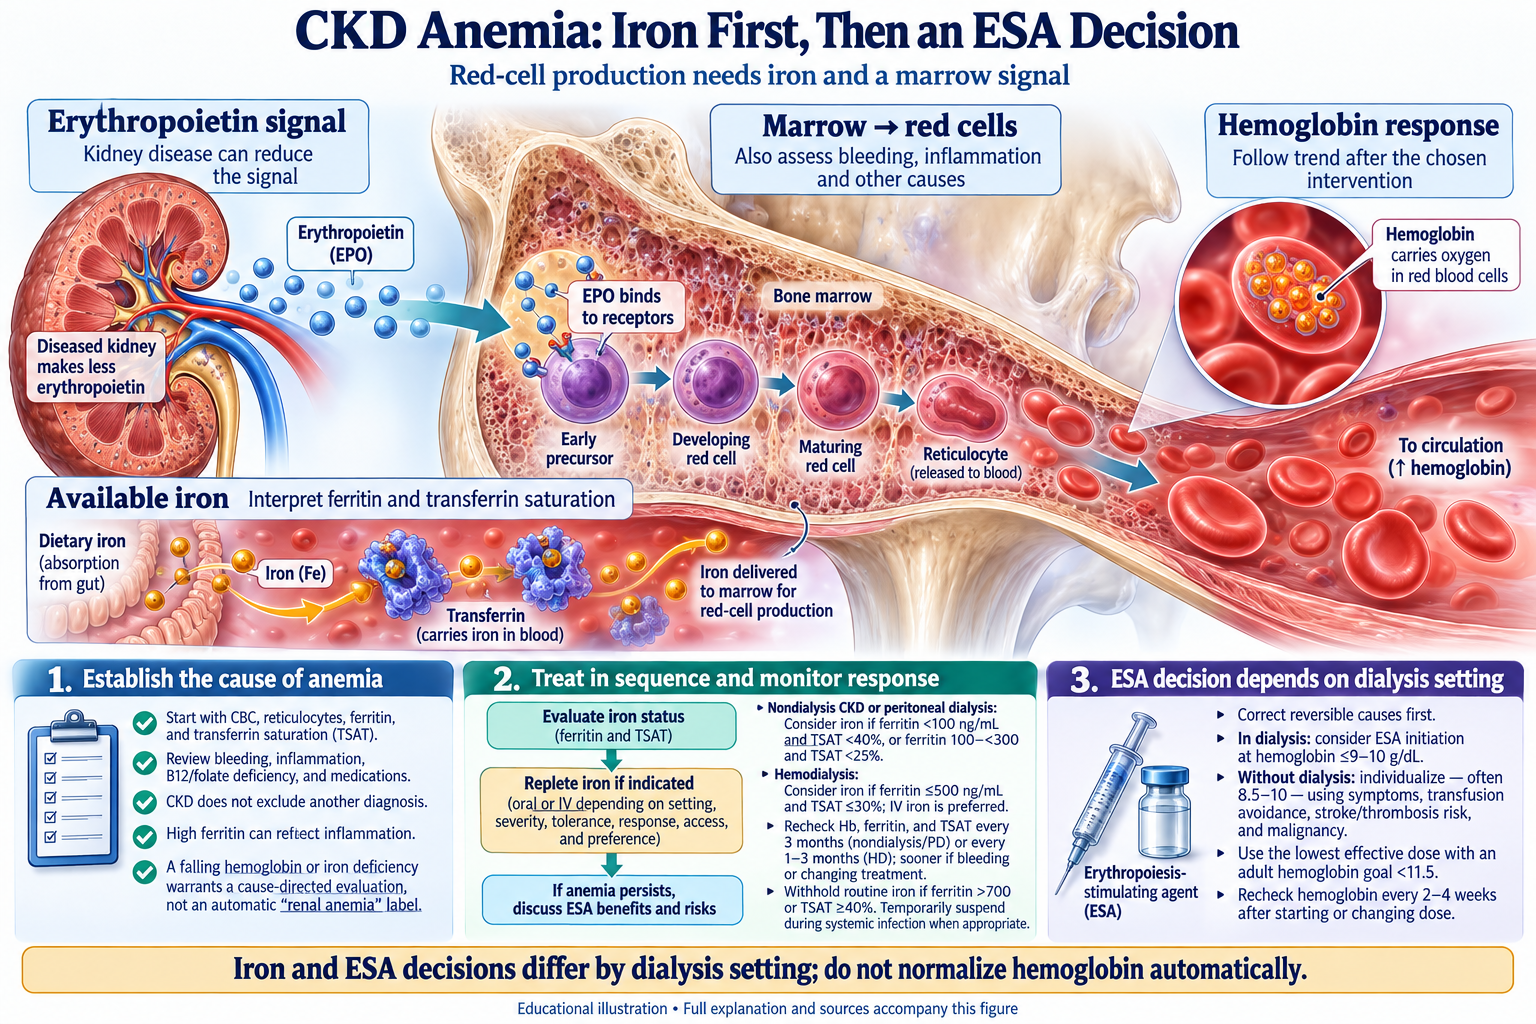
Interpret ferritin with TSAT and clinical context: Inflammation can raise ferritin despite restricted iron availability. A high ferritin with low TSAT is not an automatic IV-iron order. Evaluate both values, Hb response, infection, prior iron, and dialysis status. KDIGO 2026 suggests iron initiation in nondialysis CKD/PD for ferritin <100 ng/mL with TSAT <40%, or ferritin 100–<300 with TSAT <25%; in HD, ferritin ≤500 with TSAT ≤30%. Withhold routine iron when ferritin >700 or TSAT ≥40%; consider temporary suspension during systemic infection. KDIGO 2026 anemia guideline.
Additional Labs
- CBC: Hemoglobin, MCV (microcytic if iron deficiency)
- Reticulocyte count: Should be elevated if EPO working; low reticulocyte count suggests inadequate EPO response or iron deficiency
- EPO level: Rarely needed; not used for dosing (many “normal” labs are inappropriately LOW for degree of anemia)
- B12, folate, copper: Screen if macrocytic anemia or neuropathy present
- Peripheral smear: Rule out hemolysis, schistocytes (HUS/TTP)
Iron Supplementation
Oral Iron
- Route selection: In nondialysis CKD/PD, choose oral or IV iron by anemia severity, iron deficit, tolerability, response, access, and preference; eGFR 45 is not a route threshold.
- Formulations: Ferrous sulfate (FeSO₄) 325 mg daily = 65 mg elemental iron; ferrous gluconate (less GI upset)
- Select elemental iron dose and schedule by formulation, tolerance and response; the tablet mass is not the elemental iron dose.
- Timing: On empty stomach for better absorption; separate from calcium binders (↓ absorption by 40%)
- Side effects: GI upset (~30%), constipation, black stools, adherence issues
- Expected response: ↑ Hb by 0.5-1 g/dL per month
- Pitfall: Enteric-coated formulations bypass absorption site; avoid
Intravenous Iron (Preferred in Dialysis; Consider if Oral Fails)
Advantages: Bypasses GI barrier, doesn’t require gastric acid, rapid iron repletion
IV iron formulations differ: Use the specific product label for dose, dilution, interval, and monitoring. All products can cause hypersensitivity; ferric carboxymaltose also warrants attention to hypophosphatemia. Do not transfer one product’s schedule to another or claim zero anaphylaxis risk.
Iron replacement: Use the selected product label and a population-appropriate repletion plan, with baseline Hb, ferritin and TSAT. An iron-deficit calculation using Hb 15 g/dL is not an ESA hemoglobin target. During iron treatment, check Hb/ferritin/TSAT about every 3 months in nondialysis CKD/PD and every 1–3 months in HD; assess sooner after blood loss, treatment changes or an unexpected response.
Adverse effects: Transient hypophosphatemia (FCM), arthralgias/myalgias (transient), rare anaphylaxis (mostly iron dextran; <1% with modern formulations)
Erythropoiesis-Stimulating Agent (ESA) Therapy
Pathophysiology of ESA Action
- Recombinant EPO (epoetin alfa/beta) or long-acting darbepoetin alfa
- Binds EPO receptor on erythroid progenitors → ↑ proliferation, maturation
- Requires adequate iron, B12, folate
Indications for ESA Initiation
- ESA initiation: Correct reversible causes first. In dialysis, consider initiation around Hb ≤9–10 g/dL. Without dialysis, individualize the decision—often in the 8.5–10 range—using symptoms, transfusion avoidance, and cardiovascular/thrombotic or malignancy risks.
- Hb alone does not mandate ESA or transfusion; active bleeding, ischemic symptoms, instability, expected benefit, and treatment risks change the decision.
- Correct iron deficiency and other reversible causes, then reassess Hb trajectory and symptoms. Do not impose a universal 4–6-week delay before an individualized ESA decision.
ESA dosing is highly individualized. Older patients and those with shorter dialysis vintage often require lower doses. Document “dose” and “response” at each visit to avoid excessive dosing and cardiovascular complications.
ESA Agents & Dosing
| Agent | Formulation | Dosing | Half-life | Use |
|---|---|---|---|---|
| Epoetin alfa (EPO) | IV/SC | 50-100 U/kg 2-3× week | 4-13 hr | Short-acting; flexible dosing |
| Epoetin beta | IV/SC | Similar to alfa | 4-13 hr | Primarily European use |
| Darbepoetin alfa (Aranesp) | IV/SC | 0.45 mcg/kg weekly (or 2-3× month) | 25-40 hr | Long-acting; less frequent dosing |
Dosing principles: Use the product-specific initial regimen and the lowest effective dose, with reassessment of hemoglobin trajectory, iron status, and reversible causes of poor response. Avoid automatic escalation or rapid hemoglobin rise. Individualize the target below 11.5 g/dL during adult ESA treatment.
ESA hyporesponsiveness: Investigate inadequate response or rising dose requirements using the specific ESA and clinical trajectory. Check iron availability, inflammation/infection, blood loss, hemolysis and other causes; do not use 300 U/kg/week as a universal threshold across products or escalate repeatedly without reassessment.
Target Hemoglobin & Cardiovascular Safety
- TREAT Trial (2009): Darbepoetin to Hb approximately 13 g/dL vs placebo (rescue darbepoetin only if Hb <9) in T2DM + non-dialysis CKD → NO reduction in death/CV events or death/ESRD; stroke nearly doubled (HR 1.92, 95% CI 1.38–2.68) [1]
- CHOIR Trial (2006): Epoetin alfa to Hb 13.5 vs 11.3 g/dL → ↑ composite of death, MI, HF hospitalization, and stroke (HR 1.34, 95% CI 1.03–1.74) [2]
- ESA treatment: KDIGO 2026 recommends an adult hemoglobin target below 11.5 g/dL during ESA treatment. Initiation and maintenance should be individualized using symptoms, transfusion risk, dialysis status, iron status, and cardiovascular or thrombotic risk. Avoid normalizing hemoglobin with ESAs.
ESAs increase thrombotic risk (ESA-induced hypertension, erythrocytosis, polycythemia). Patients on ESAs have ↑ risk of vascular access thrombosis, DVT/PE, and stroke if Hb overshoot.
HIF-Prolyl Hydroxylase Inhibitors (HIF-PHIs) — Newer Class
Mechanism
- Blocks degradation of HIF (hypoxia-inducible factor) → ↑ endogenous EPO production
- HIF stabilization can reduce hepcidin and improve iron availability; its effects and clinical safety are agent- and population-dependent.
- Oral agents: roxadustat, daprodustat, vadadustat
Agents & Evidence
- Roxadustat: Oral, dosed 3× weekly. Approved outside the US (including China and Japan); not FDA-approved in the United States
- Daprodustat: FDA approval in 2023 covered adults receiving dialysis for at least 4 months. US Jesduvroq was subsequently discontinued commercially; FDA determined withdrawal from sale was not for safety or effectiveness. Approval history does not establish current local availability.
- Vadadustat: The US label covers adults with CKD anemia receiving dialysis for at least 3 months. Review contraindications, cardiovascular/thrombotic risks and the product-specific monitoring plan; it is not indicated for nondialysis CKD anemia.
- INNO2VATE (dialysis-dependent CKD): non-inferior to darbepoetin alfa for MACE (HR 0.96, 95% CI 0.83–1.11) and for Hb correction/maintenance [3]
- PRO2TECT (non–dialysis-dependent CKD): met the Hb non-inferiority margin but did NOT meet the cardiovascular non-inferiority margin (MACE HR 1.17, 95% CI 1.01–1.36) [4]
- Class advantage: oral dosing; ↓ hepcidin may improve iron availability
- Class caution: cardiovascular safety is not uniform across agents or across dialysis status — do not assume a class effect
When to Use HIF-PHI vs ESA
- HIF-PHI selection: KDIGO 2026 generally favors an ESA as first-line erythropoietic therapy after correcting reversible causes. A HIF-PHI decision requires approved local eligibility, treatment risks, and shared choice; injection refusal or ESA hyporesponsiveness alone does not establish eligibility.
- Neither an ESA nor a HIF-PHI provides immediate correction of unstable acute anemia; use an urgent cause-directed and transfusion assessment when appropriate.
- Monitoring: Follow hemoglobin trend, blood pressure, iron status, and product-specific safety guidance. Individualize treatment rather than pursuing a normal hemoglobin.
HIF-PHIs affect iron handling, but mechanistic effects do not establish superior overall safety or a preferred first-line role. Use final KDIGO 2026 anemia guidance and the specific product’s current local availability and label.
Management Algorithm: Putting It All Together
Step 1: Confirm Iron Sufficiency
- Use the dialysis-status-specific ferritin AND TSAT initiation criteria described above. Choose route by clinical need and response; low TSAT alone is not an automatic iron order.
- Reassess iron response and other correctable causes before ESA escalation; use Hb trajectory, symptoms and the product label rather than a mandatory waiting interval.
- Recheck ferritin and TSAT before starting ESA
Step 2: Initiate ESA or HIF-PHI
- ESA: Use an individualized indication and the actual product’s initial dosing guidance; do not extrapolate an IV hemodialysis schedule to every nondialysis patient.
- HIF-PHI: Confirm the product’s approved population and discuss harms/benefits; this is not an automatic substitute whenever an ESA is contraindicated.
- Individualize the hemoglobin target; in adults treated with an ESA, keep the target below 11.5 g/dL.
Step 3: Titrate Dose
- Reassess Hb about every 2–4 weeks after starting or changing ESA therapy; use the product-specific adjustment rules, Hb trajectory, and lowest effective dose rather than a universal increment.
- During iron treatment, monitor Hb, ferritin and TSAT every 3 months in nondialysis CKD/PD and every 1–3 months in HD; shorten the interval when clinical changes require it. Reticulocytes are part of assessment when indicated, not a universal monthly order.
- Avoid maintaining adult Hb at or above 11.5 g/dL with an ESA. Reduce or hold dosing according to the specific product label, Hb trajectory and rapid-rise rules; do not apply one fixed 25% decrement to every product or situation.
Step 4: Monitor for Hyporesponsiveness
- If response is inadequate or dose requirements rise despite adequate iron, investigate reversible causes and reassess the treatment plan; a single epoetin-equivalent cutoff does not define all ESA hyporesponsiveness.
- Consider: Blood loss, inflammation (CRP), hemolysis (haptoglobin, LDH), malignancy, infection, copper deficiency
Step 5: Transition to Dialysis or Transplant
- Dialysis follow-up: Reassess the need for iron and ESA using Hb trajectory, ferritin/TSAT, symptoms, treatment risks and ongoing losses; neither treatment continues automatically.
- After transplant: Reassess anemia, graft function, bleeding, iron status, infection, and medication effects. Do not automatically stop or taper solely because transplantation occurred.
Clinical Pearls & Board Pearls
Iron-restricted erythropoiesis: Inflammation can produce low TSAT despite higher ferritin. Assess both values and the clinical setting, dialysis status, infection, prior iron exposure, and response; higher ferritin with low TSAT does not automatically mandate IV iron.
ESA hyporesponsiveness: Reassess iron availability, inflammation/infection, blood loss, hemolysis, delivered dialysis, nutrition, medications, and other hematologic causes. Do not explain poor response as inadequate machine clearance of erythropoietin or escalate ESA blindly.
Copper deficiency: Rare but serious cause of ESA hyporesponsiveness + microcytic anemia + myelopathy. Diagnosis: ↓ serum copper, ↓ ceruloplasmin. Treat: IV copper supplementation. Screen if anemia refractory to iron + adequate ESA.
Medication review: ACE-I/ARB can contribute to anemia in some settings, but do not routinely stop kidney- or heart-protective treatment to increase Hb. Assess other causes and discuss any change with the treating team.
Landmark Trials
[1] TREAT Trial (2009): Pfeffer MA, Burdmann EA, Chen CY, et al. A trial of darbepoetin alfa in type 2 diabetes and chronic kidney disease — darbepoetin to a hemoglobin target of approximately 13 g/dL vs placebo with rescue darbepoetin if Hb <9 g/dL. N Engl J Med. 2009;361(21):2019–2032. PMID: 19880844
[2] CHOIR Trial (2006): Singh AK, Szczech L, Tang KL, et al. Correction of anemia with epoetin alfa in chronic kidney disease — a 13.5 g/dL hemoglobin target increased the composite of death, MI, HF hospitalization, and stroke vs an 11.3 g/dL target. N Engl J Med. 2006;355(20):2085–2098. PMID: 17108343
[3] INNO2VATE (2021): Eckardt KU, Agarwal R, Aswad A, et al. Safety and efficacy of vadadustat for anemia in patients undergoing dialysis. N Engl J Med. 2021;384(17):1601–1612. PMID: 33913638
[4] PRO2TECT (2021): Chertow GM, Pergola PE, Farag YMK, et al. Vadadustat in patients with anemia and non–dialysis-dependent CKD. N Engl J Med. 2021;384(17):1589–1600. PMID: 33913637