Education Use Only
For educational use only — Not for clinical decision-making without independent verification
Medical Associates  ·  Department of Nephrology ← urinenephrology.org
Nephrology Education Series

CKD Complications: Mineral Bone Disorder, Anemia, and Systemic Manifestations

Andrew Bland, MD, FACP, FAAP UICOMP · UDPA · Butler COM 2026-02-12 21 min read

CKD Complications: Mineral Bone Disorder, Anemia, and Systemic Manifestations

Visual reference

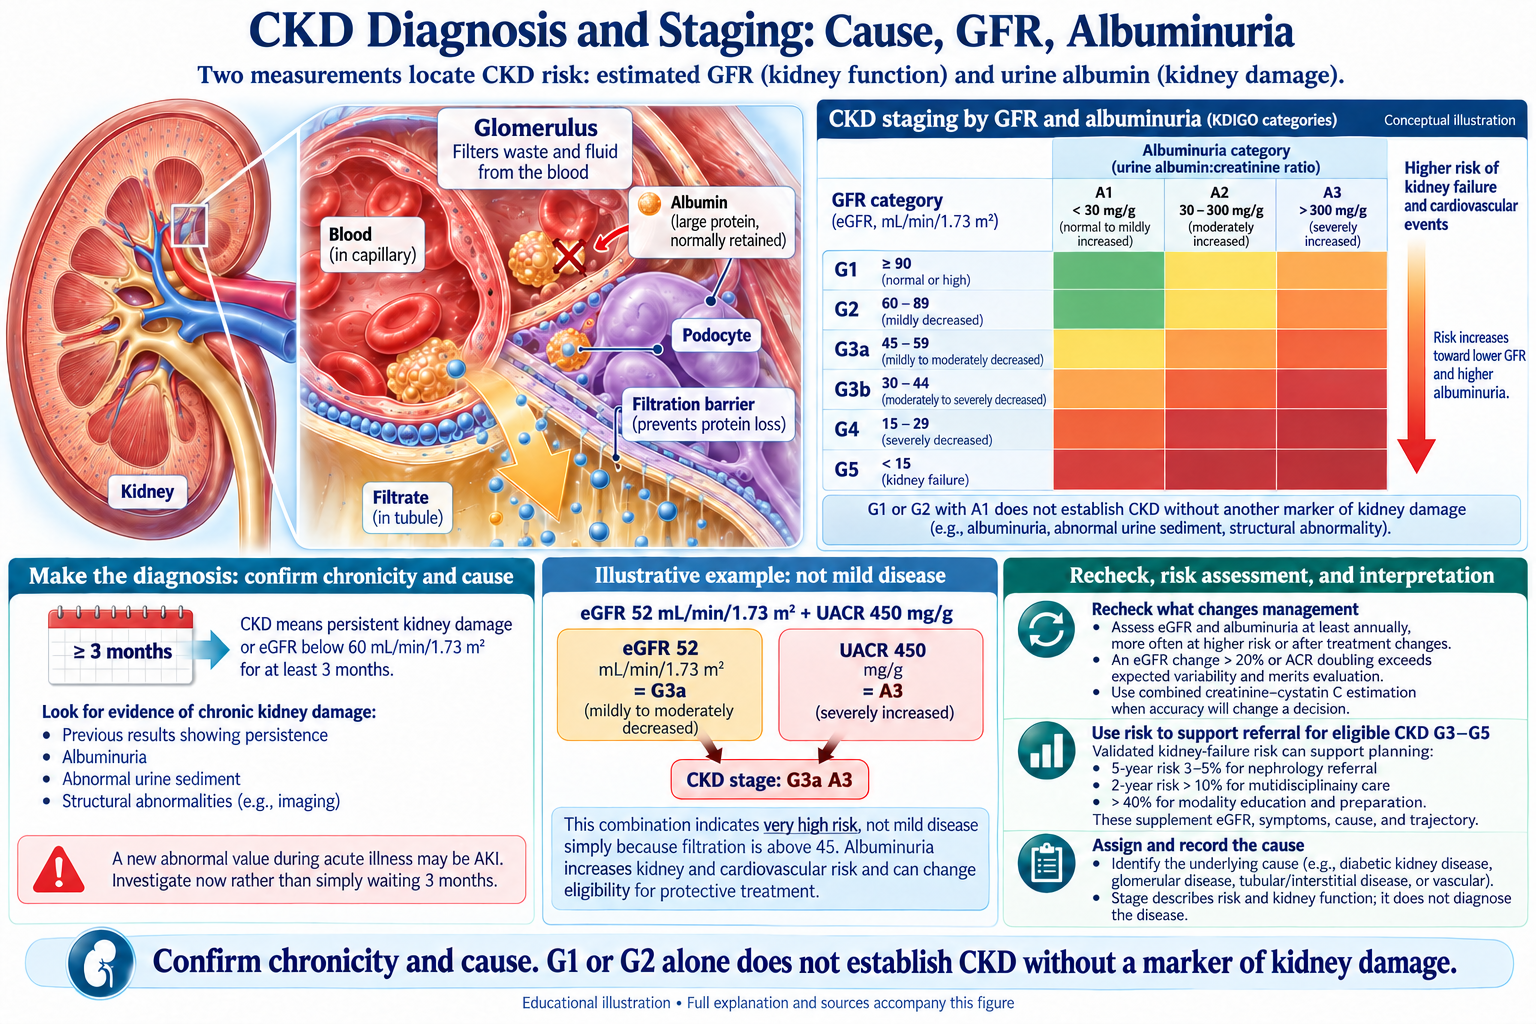
CKD Diagnosis and Staging: Cause, GFR, Albuminuria visual summary. Open for the full image and text version.
CKD Diagnosis and Staging: Cause, GFR, Albuminuria: full graphic and text version
More visual summaries for this topic
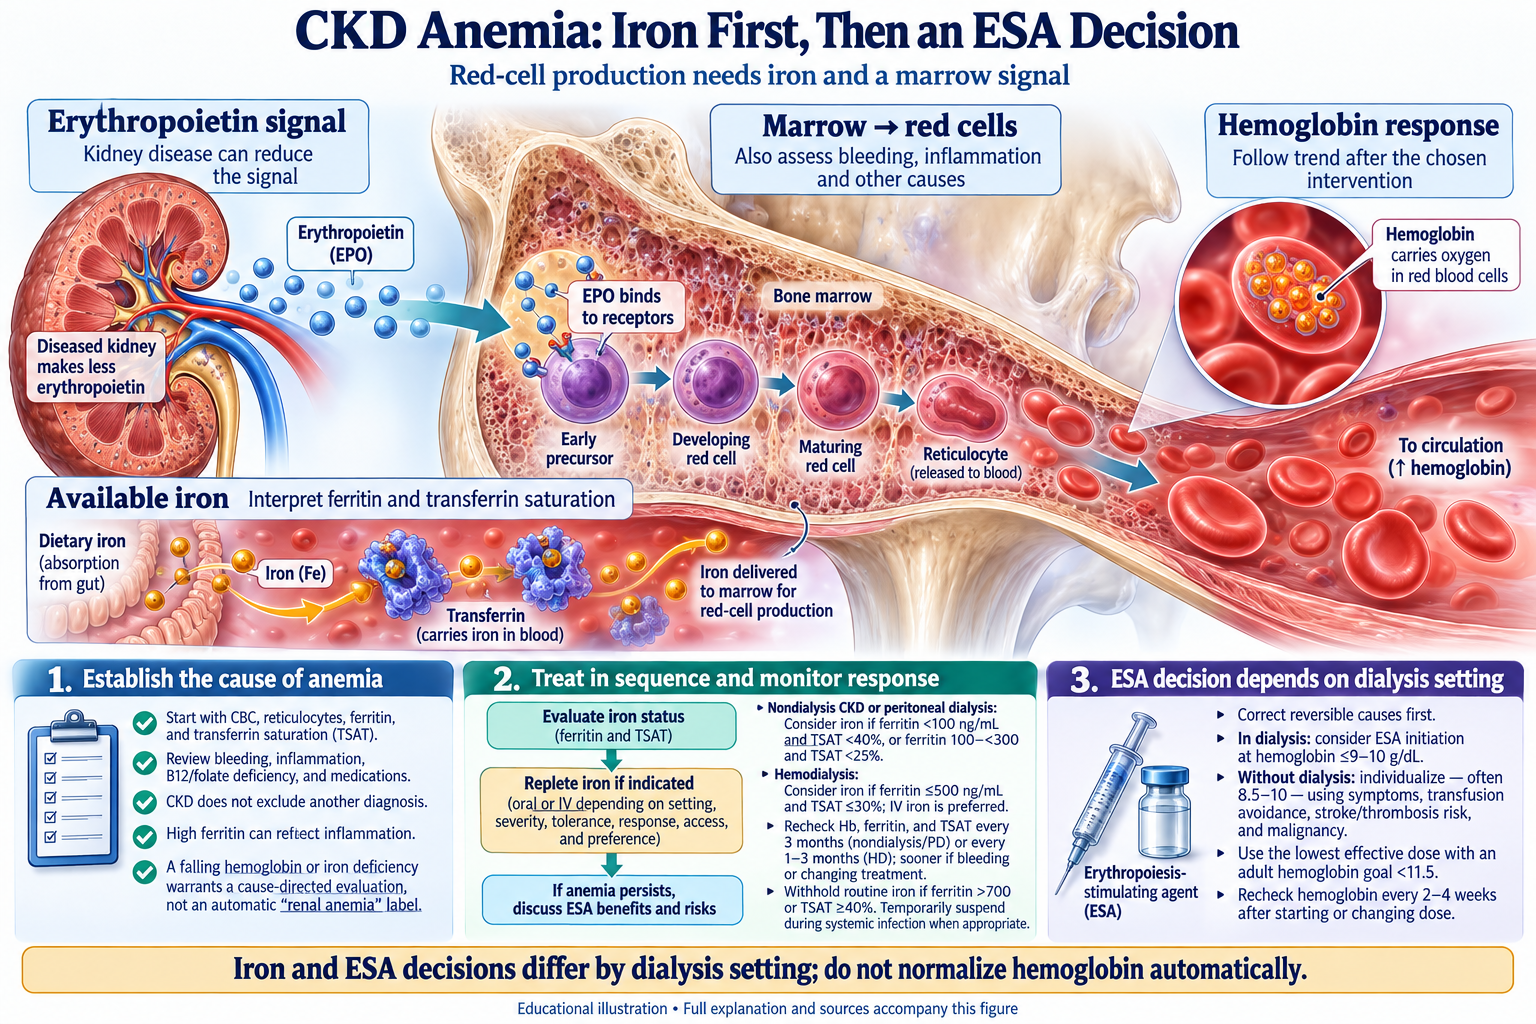
CKD Anemia: Iron First, Then an ESA Decision visual summary. Open for the full image and text version.
CKD Anemia: Iron First, Then an ESA Decision: full graphic and text version
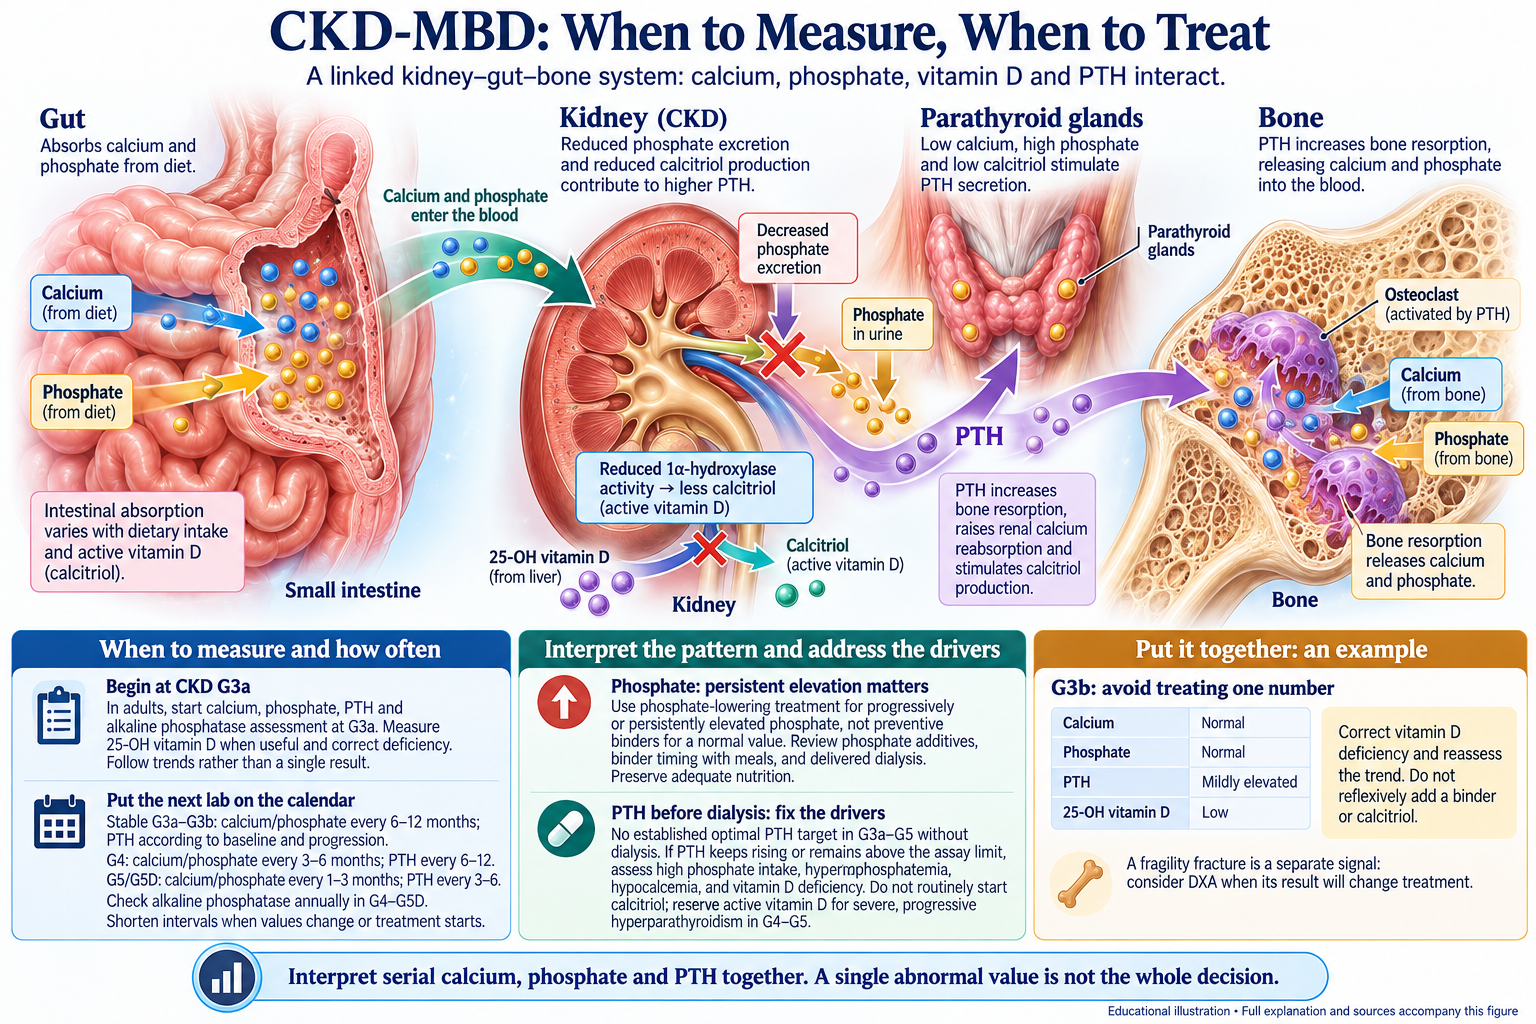
CKD-MBD: When to Measure, When to Treat visual summary. Open for the full image and text version.
CKD-MBD: When to Measure, When to Treat: full graphic and text version

Browse the visual reference library · Download lesson Markdown

Learning Objectives

By the end of this handout, students will be able to:

  1. Identify and classify CKD-mineral bone disorder (CKD-MBD) pathophysiology and distinguish between secondary and tertiary hyperparathyroidism
  2. Explain mechanisms of renal anemia including EPO deficiency, iron metabolism disruption, and uremic inhibitors
  3. Recognize clinical presentations of calciphylaxis and vascular calcification in CKD
  4. Understand uremic toxins and their systemic effects across multiple organ systems
  5. Apply mechanisms of CKD progression (glomerular hyperfiltration, fibrosis, proteinuria-induced injury)
  6. Synthesize multi-system complications of CKD affecting cardiovascular, neurologic, dermatologic, endocrine, and hematologic systems

I. CKD-Mineral Bone Disorder (CKD-MBD): Overview

Definition and Scope

CKD-MBD is a systemic disorder of mineral and bone metabolism that emerges early in CKD, characterized by abnormalities in: - Serum calcium, phosphate, PTH, and vitamin D metabolism - Vascular and soft-tissue calcification - Bone turnover, mineralization, and strength - FGF23 dysregulation

Prevalence: Begins at CKD Stage 3 (eGFR <60), with significant pathology by Stage 4.


II. Pathophysiology of Secondary Hyperparathyroidism

Early Phase (CKD Stages 3–4): Phosphate Retention & FGF23 Rise

Timeline: 1. eGFR falls → phosphate excretion decreases (kidney loses filtration capacity) 2. Serum phosphate rises (even before clinical hyperphosphatemia detected) 3. FGF23 surges in response to hyperphosphatemia 4. FGF23 suppresses: - 1α-hydroxylase (activating CYP27B1) → ↓ calcitriol synthesis - Sodium-phosphate co-transporters (NPT2a/c) → ↑ urinary phosphate loss 5. Calcitriol (1,25-OH vitamin D3) decreases → ↓ intestinal calcium absorption

Cascade to Hypocalcemia & PTH Rise

  • Decreased calcitriol + phosphate retention → ↓ serum calcium (ionized Ca2+)
  • Hypocalcemia stimulates parathyroid glands → PTH rises
  • PTH mobilizes calcium from bone (transient correction)
  • Phosphate binders and dietary restriction may partially blunt phosphate rise, but underlying deficit persists

Progressive Phase (CKD Stages 4–5): Parathyroid Gland Adaptation

Mechanism Effect Consequence
Decreased calcium-sensing receptor (CaSR) expression Parathyroid insensitivity to serum calcium PTH continues rising despite normalized Ca
FGF23 resistance Impaired FGF23 suppression of PTH Autonomous PTH secretion develops
Uremia & phosphate toxicity Direct parathyroid proliferation Gland hyperplasia, nodular formation
Vitamin D deficiency Loss of VDR-mediated PTH suppression Secondary hyperparathyroidism becomes tertiary

Result: Secondary hyperparathyroidism becomes autonomous (pseudo-tertiary hyperparathyroidism) even before transplantation.


III. Secondary vs. Tertiary Hyperparathyroidism

Secondary Hyperparathyroidism

Definition: Appropriate parathyroid response to CKD-induced hypocalcemia, hyperphosphatemia, and calcitriol deficiency.

Characteristics: - PTH elevated (often >200 pg/mL in CKD Stage 5) - Serum calcium low-normal to mildly ↓ - Serum phosphate ↑ - Parathyroid tissue is hyperplastic but responsive to suppression (in theory) - Reversible if CKD is corrected or dialysis initiated

Tertiary Hyperparathyroidism

Definition: Autonomous PTH secretion occurring after prolonged secondary hyperparathyroidism, often post-transplantation when GFR improves.

Characteristics: - PTH remains elevated despite normalized serum calcium and phosphate - Serum calcium elevated (hypercalcemia) - Serum phosphate normalized by transplant kidney - Parathyroid tissue shows nodular hyperplasia, autonomous function - Develops from long-standing secondary hyperparathyroidism with parathyroid gland structural changes - Requires parathyroidectomy if severe (PTH >800–1000 pg/mL causing hypercalcemia)

Clinical Implications

Feature Secondary HyperPTH Tertiary HyperPTH
CKD Stage 3–5D Post-transplant
Serum Ca Low-normal to ↓ ↑ (hypercalcemia)
Serum Phos ↑ Normal
Responsiveness Responsive to calcitriol, Ca, Phos control Autonomous (surgery needed)
GFR <45 mL/min >45 (improved)

IV. CKD-MBD Bone Pathology

Renal Osteodystrophy Patterns

High-Turnover Bone Disease (Secondary Hyperparathyroidism) - Increased osteoblast and osteoclast activity - ↑ bone resorption, ↑ bone formation (but formation lags resorption) - ↑ PTH drives rapid turnover - Risk: Fracture despite increased remodeling (paradox: high turnover can cause fragility) - Biochemical markers: ↑ alkaline phosphatase, ↑ P1NP (procollagen type 1 N-terminal propeptide)

Low-Turnover Bone Disease (Adynamic Bone) - Suppressed osteoblast activity, minimal bone remodeling - ↓ PTH (excessive suppression from calcitriol, calcimimetics) - ↑ Risk of calcification (paradoxically, despite low turnover) - Presents as: Fractures, proximal muscle weakness, bone pain (“bone hunger” syndrome on dialysis) - Common in: Dialysis patients, over-suppressed PTH

Mixed Uremic Osteodystrophy - Features of both high and low turnover - Defective mineralization (osteomalacia features) - ↑ Al3+ accumulation from dialysate (historical, now rare) - ↓ 25-OH vitamin D compounds problem

Bone Mineral Density (BMD) Paradox in CKD

  • BMD in CKD varies. Degenerative change or vascular calcification can artifactually elevate some DXA measurements; interpret the site and image quality rather than assuming all CKD patients have high BMD.
  • Yet fracture risk is INCREASED 2–4 fold compared to general population
  • True bone quality is impaired (higher turnover, mineralization defects, microarchitectural damage)
  • DXA can inform fracture risk in CKD G3a–G5D when its result will change treatment. It does not identify the renal bone-turnover subtype; combine results with clinical/biochemical assessment and consider biopsy when it would change management.

V. Vascular Calcification and Calciphylaxis

Mechanisms of Vascular Calcification in CKD

1. Passive Deposition (“Medial Calcification”) - Hyperphosphatemia + hypercalcemia create supersaturated local environment - Calcium-phosphate ions precipitate in media layer of arteries - Enhanced by: uremic toxins, oxidative stress, hyperparathyroidism

2. Active Osteogenic Differentiation - Vascular smooth muscle cells (VSMCs) undergo osteogenic transition - Driven by: phosphate, oxidative stress, loss of calcification inhibitors - VSMCs express bone-specific markers: alkaline phosphatase, osteocalcin, Runx2 - Morphologic result: Arterial wall calcifies, becomes rigid, loses elastic recoil

3. Loss of Mineralization Inhibitors - Fetuin-A ↓ (uremic loss) - Pyrophosphate ↓ (substrate consumed in calcification) - Matrix Gla-protein (MGP) ↓ or inactive - Osteoprotegerin (OPG) dysregulated - Net result: Unopposed calcification

Calciphylaxis (Calcific Uremic Arteriolopathy)

Definition: Rare but catastrophic syndrome of small-vessel medial calcification in CKD patients, causing painful ischemic necrosis of skin and subcutaneous tissue.

Epidemiology: - Incidence: 1–4% of hemodialysis patients - Mortality: 60–80% if untreated (sepsis, amputation complications)

Risk Factors: - Serum calcium × phosphate product >70 (historical marker; now any elevation of Ca-Phos product) - Primary hyperparathyroidism superimposed on CKD - Obesity - Female sex - Warfarin use (inhibits matrix Gla-protein carboxylation, paradoxically promotes calcification) - Hypercoagulability, thrombophilia

Clinical Presentation: - Extremely painful skin lesions (out of proportion to appearance) - Pink-to-purple, livedoid rash → black necrotic ulcers with demarcation - Typically affects lower extremities, buttocks, digits, penis, breast tissue - Often bilateral and symmetric - Subcutaneous calcification visible on imaging (small-vessel calcification)

Diagnosis: - Clinical suspicion (CKD + severe pain + skin findings) - Skin biopsy: Small-vessel calcification with medial sclerosis - Imaging: X-ray, CT showing micro-calcifications

Calciphylaxis management: Arrange urgent multidisciplinary nephrology, wound and pain care. Review phosphate/calcium loading, dialysis delivery and PTH trends without forcing PTH to normal; assess warfarin risks and alternatives with the anticoagulation team. Treat documented or suspected wound infection promptly rather than routine prophylactic antibiotics. Sodium thiosulfate and debridement require individualized specialist decisions; evidence for specific therapies is limited.


VI. Renal Anemia in CKD

Epidemiology & Classification

Prevalence: Present in >90% of CKD Stage 5D patients; begins at Stage 3–4.

Severity by CKD Stage: | CKD Stage | eGFR | Typical Hb (g/dL) | Anemia Prevalence | |———–|——|——————-|——————-| | 3a | 45–59 | 12.5–13.5 | 5–10% | | 3b | 30–44 | 11.5–12.5 | 15–25% | | 4 | 15–29 | 10.5–11.5 | 40–50% | | 5 (pre-D) | <15 | 9–10 | 80–90% | | 5D | on dialysis | <10 (without ESA) | 95%+ |

Primary Mechanism: EPO Deficiency

Normal EPO Production: - Fibroblasts in peritubular interstitium of kidney (90% of body EPO) - Small amount from liver (10%) - Stimulus: Renal hypoxia (oxygen-sensing by HIF pathway)

In CKD: - Nephron loss → fewer EPO-producing fibroblasts - Remaining fibroblasts have blunted hypoxia response (uremic milieu impairs HIF signaling) - EPO production drops disproportionately to degree of kidney loss - Even CKD Stage 3 → EPO levels inadequate for true degree of renal function loss

Result: Relative EPO deficiency (low-normal EPO level in face of anemia requiring EPO 10x normal)

Secondary Anemia Mechanisms in CKD

1. Iron Deficiency - Hepcidin dysregulation: CKD → ↑ hepcidin (from inflammation, FGF23) → ↓ ferroportin → ↓ iron absorption - Chronic blood loss: Dialysis membrane losses, occult GI bleeding in uremia - Impaired iron mobilization: Uremia impairs ferroxidase activity (ceruloplasmin) - Functional iron deficiency: Adequate iron stores but impaired utilization

2. Uremic Inhibition of Erythropoiesis - Uremic toxins (indoxyl sulfate, p-cresol, urea itself) suppress bone marrow erythroid response - Inhibit EPO signaling in erythroid progenitors - Toxic metabolites accumulate in CKD (not removed by dialysis alone)

3. Hemolysis & Reduced RBC Survival - Uremic toxins oxidize RBC membrane proteins - ↓ RBC deformability, impaired passage through spleen - Circulating RBC lifespan: 60–80 days (vs. 120 days in health) - Low-grade hemolysis (↑ bilirubin, ↑ LDH, ↓ haptoglobin)

4. Chronic Inflammation - CKD → constant low-grade uremia + fluid retention → innate immune activation - ↑ IL-6, TNF-α, C-reactive protein - Inflammatory cytokines suppress erythropoietin response and increase hepcidin - Dialysis itself triggers inflammation (endotoxemia, contact with membrane)

5. Blood Loss & Nutritional Factors - Dialysis losses: RBCs trapped in dialyzer, tubing (per treatment: 1–5 mL) - Monthly/yearly accumulation: Significant over time - Folate/B12 deficiency: Uremic anorexia, dietary restriction, dialysate losses - Aluminum toxicity (historical): Suppressed RBC production (now rare with modern dialysate)

ESA Therapy and Resistance

Erythropoiesis-Stimulating Agent (ESA) Target in CKD: - Adult ESA-treated target hemoglobin: below 11.5 g/dL (no benefit to higher; increased thrombosis/hypertension risk) - Avoid target >13 g/dL (increased CV events, stroke in clinical trials)

ESA hyporesponsiveness: Inadequate response or rising dose requirements warrant reassessment of iron, inflammation/infection, bleeding and other reversible causes. Use the specific ESA, dose history and Hb trajectory; route-specific epoetin cutoffs are not a universal definition for every product.

Mechanisms of ESA Resistance: - Persistent iron deficiency (even with IV iron) - Ongoing hemolysis (severe uremia) - Hyperparathyroidism (PTH suppresses erythropoietin signaling) - ACE inhibitor/ARB use (can reduce EPO; controversial benefit/harm) - Chronic infection or malignancy - Aluminum accumulation (rare now) - Underlying hematologic disorder (myelodysplasia, thalassemia trait)


VII. Uremic Toxins and Uremia Syndrome

Definition of Uremia

Uremia is the clinical syndrome resulting from retention of nitrogenous and organic compounds normally cleared by kidneys. Not merely elevated BUN/creatinine, but the metabolic milieu of compounds causing symptoms and organ dysfunction.

Classification of Uremic Toxins

Category Examples Effects
Small Water-Soluble Urea, creatinine, uric acid Readily dialyzable; moderate uremic effects
Protein-Bound Indoxyl sulfate, p-cresol, indole-3-aldehyde, phenolic compounds Poorly dialyzable; potent toxins; resist HD/PD
Middle Molecules β2-microglobulin, myoinositol, adenosine Size 300–50,000 Da; partially dialyzed; cause amyloidosis
Large Molecules Advanced glycation end products (AGEs), uremic “super-oxides” Potent inflammatory triggers

Key Uremic Toxins and Their Organ Effects

1. Indoxyl Sulfate (Indican) - Source: Tryptophan metabolism by gut microbiota → indole → liver sulfation - Actions: Aryl hydrocarbon receptor (AhR) agonist; oxidative stress; endothelial dysfunction; promotes CKD progression (feeds forward) - Toxicity: Cardiovascular, gut barrier breakdown

2. p-Cresol (p-CS) - Source: Tyrosine fermentation; gut dysbiosis increases production - Actions: Aryl hydrocarbon receptor; vascular oxidative stress; immune suppression - Toxicity: Vascular calcification, infection risk, CKD progression

3. Asymmetric Dimethylarginine (ADMA) - Action: Competitive inhibitor of nitric oxide synthase (NOS) → ↓ NO → vasoconstriction, endothelial dysfunction - Effect: Potent vascular toxin; increases CV risk

4. β2-Microglobulin - Source: Constant shedding from leukocyte surface; normally filtered and reabsorbed by kidney - Accumulation in CKD: Forms amyloid fibrils - Condition: Dialysis-related amyloidosis (DRA) with prolonged HD/PD - Deposits in: Bones, joints, tendons → carpal tunnel, pathologic fractures, destructive arthropathy - Newer high-flux dialyzers and hemodiafiltration reduce β2-microglobulin better

5. Phosphate (Phosphoric Acid) - Toxic at elevated levels (>6 mg/dL) - Promotes vascular calcification, soft-tissue precipitation - Stimulates FGF23 (feeds forward CKD progression and hyperparathyroidism)

Systemic Effects of Uremia (Multi-Organ)

Cardiovascular: - Atherosclerosis acceleration (ADMA, oxidative stress, dyslipidemia) - Vascular calcification (phosphate, FGF23) - Left ventricular hypertrophy (hypertension, anemia, fluid overload) - Arrhythmias (hyperkalemia, uremia, volume overload) - Heart failure (from all above)

Neurologic: - Uremic encephalopathy: Altered mental status, confusion, seizures (high BUN); reversible with dialysis - Peripheral neuropathy: Demyelinating (from uremia) or entrapment (from amyloidosis) - Central pontine myelinolysis: Risk with rapid correction of hyponatremia in dialysis - Sleep disturbance (uremia, restless leg syndrome from iron deficiency, phosphate imbalance)

Gastrointestinal: - Uremic gastroparesis (delayed emptying, nausea, poor appetite) - Uremic colitis (mucosal ischemia, ulceration) - GI bleeding (angiodysplasia, aspirin/anticoagulation use) - Enteritis, dysmotility from toxins

Hematologic (beyond anemia): - Platelet dysfunction (uremic toxins impair aggregation) → prolonged bleeding time despite normal count - ↑ Infection risk (immune suppression from uremia, impaired chemotaxis) - Hemolysis (as discussed)

Dermatologic: - Uremic pruritus: Mast cell activation, phosphate accumulation in skin; severe, distressing - Pigmentation changes (retained urochrome, anemia) - Skin atrophy, fragility - Calciphylaxis (already discussed)

Endocrine: - Hypothalamic-pituitary dysfunction (uremic suppression of GnRH, ACTH) - ↓ Testosterone, ↓ Estrogen (amenorrhea common) - ↑ Prolactin (loss of dopamine inhibition) - Thyroid: Usually maintained, but TSH may be blunted - Insulin resistance (uremic toxins, chronic inflammation) - Impaired glucose sensing

Immune: - T-cell dysfunction (impaired cell-mediated immunity) - B-cell response attenuated (poor vaccine response) - ↑ Infection rates (respiratory, urinary, access-related) - Altered complement regulation


VIII. CKD Progression Mechanisms

Hyperfiltration Hypothesis

Normal physiology: - ~1 million nephrons per kidney - Baseline single-nephron GFR (SNGFR): ~50 nL/min - Total GFR: ~100–120 mL/min

After nephron loss (from any cause): - Remaining nephrons increase SNGFR via afferent arteriolar vasodilation - Mediated by: ↓ systemic BP → renin-angiotensin activation → efferent arteriole vasoconstriction → glomerular pressure ↑ - Also: Compensatory renal growth (hypertrophy)

Problem: Elevated intraglomerular pressure (Pg) causes: 1. Mechanical injury to capillaries 2. Increased protein filtration → proteinuria (toxin to tubules) 3. Podocyte foot process fusion (ultrafiltration barrier damage) 4. Activation of fibrogenic pathways (TGF-β, CTGF)

Result: Progressive glomerulosclerosis, tubulointerstitial fibrosis, accelerated nephron loss.

Role of Proteinuria in CKD Progression

Glomerular origin of filtered proteins: - Albumin: Charge-selective; some normally filtered (<150 mg/day) - Immunoglobulins, other proteins: Normally absent - Proteinuria >0.5–1 g/day indicates loss of charge and size selectivity (damaged filter)

Proteinuria toxicity to tubules: - Proximal tubule endocytosis: Proximal cells reuptake filtered proteins via megalin/cubilin receptors - Lysosomal overload: Proteins digest in lysosomes; lipids, iron accumulate → lipid peroxidation, ROS - TGF-β activation: Filtered proteins trigger epithelial-mesenchymal transition (EMT) in tubules → fibroblasts - Complement activation: Alternative pathway; C5a and C3a drive inflammation - Acidification: Tubule reabsorption of proteins → tubular acidosis (metabolic acidosis worsens proteinuria)

Clinical implication: ACE-I/ARB reduce intraglomerular pressure → ↓ proteinuria → slows CKD progression (proven benefit in all CKD etiology)

Fibrosis Cascade: Glomerular and Tubulointerstitial

Initiating factors: - Chronic glomerular/tubular injury (proteinuria, hemodynamic stress, toxic metabolites) - Repeated injury-repair cycles → myofibroblast accumulation

TGF-β pathway (central to fibrosis): 1. Injured tubular epithelium + infiltrating macrophages → ↑ TGF-β production 2. TGF-β → myofibroblast differentiation (via pericyte-to-fibroblast transition) 3. Myofibroblasts → excessive collagen synthesis (type I, III) 4. EMT (Epithelial-Mesenchymal Transition): Tubular epithelial cells lose adhesion → gain fibroblast characteristics 5. Collagen accumulation → tubular and glomerular stiffness → progressive function loss

CTGF (Connective Tissue Growth Factor): - Downstream of TGF-β - Amplifies fibrogenic response - Cross-talk with Wnt/β-catenin pathway

Outcome: Progressive replacement of functional parenchyma with fibrotic scar tissue.

Metabolic Acidosis and CKD Progression

Mechanism: - CKD → ↓ NH4+ excretion (loss of ammoniogenesis in proximal tubule) - ↓ HCO3- reabsorption - Net H+ retention → metabolic acidosis (typically mild, pH 7.3–7.35)

Effect on CKD progression: - Acidosis → ↑ ammonia and glutaminase in proximal tubule → local tissue injury - ↑ Ammoniagenesis damages tubulointerstitium - Acidosis triggers protein catabolism, worsens CKD mineral bone disease - Alkali therapy (sodium bicarbonate, sodium citrate) slows CKD progression (KDIGO recommendation)


IX. Multi-System Complications of CKD: Organ-System Summary

Organ System Key Complications Pathophysiology Management Pearls
Cardiovascular LVH, HF, CAD, arrhythmia, sudden cardiac death Hypertension, anemia, vascular calcification, uremia BP target <120 SBP; ACE-I/ARB; treat anemia judiciously
Renal/Urologic Progressive GFR loss, proteinuria, hematuria Hyperfiltration, glomerulosclerosis, fibrosis ACE-I/ARB; SGLT2i; phosphate control
Bone-Mineral Secondary HPT, low-turn bone disease, fractures, calciphylaxis FGF23 rise, phosphate retention, calcitriol ↓ No established optimal PTH in nondialysis CKD; approximately 2–9 times assay ULN in G5D. Assess calcium, phosphate, PTH trends and vitamin D together; no calcium–phosphate product treatment target.
Hematologic Anemia, bleeding tendency, ↑ infection risk EPO deficiency, iron loss, immune dysfunction, toxins Individualize anemia treatment after correcting reversible causes; adult ESA maintenance target is below 11.5 g/dL. Iron route depends on dialysis status, iron indices and response. Antibiotics require a specific indication.
Neurologic Uremic encephalopathy, neuropathy, seizures, sleep disorder Uremic toxins, electrolyte abnormalities (K, Ca-Phos), amyloidosis Dialysis adequacy; electrolyte management; treat HTN
GI Uremia, bleeding, gastroparesis, enteritis Mucosal ischemia, uremic toxins, vascular disease Dietary restriction; H2-blocker or PPI; avoid NSAIDs
Endocrine/Metabolic Hypothyroidism, hypogonadism, insulin resistance, dyslipidemia Uremia, inflammation, hormonal dysregulation TSH screening; lipid panel; sexual dysfunction counseling
Dermatologic Uremic pruritus, skin fragility, pigmentation Mast cell activation, uremic toxins, microvasculature disease Phosphate control; gabapentin/pregabalin; antihistamines
Infectious UTI, sepsis, access infection, opportunistic infection Immune suppression, uremia, breach of barriers Prophylaxis in high-risk; aggressive management

X. Clinical Pearls

  1. CKD-MBD monitoring begins in G3a: Assess calcium, phosphate, PTH and alkaline phosphatase. Early hormonal changes do not justify prophylactic binders or routine active vitamin D; treat documented abnormalities and trends.

  2. FGF23 may rise early in CKD, but routine FGF23 testing or a value above 100 RU/mL is not an established trigger for CKD-MBD treatment.

  3. Assess calcium and phosphate individually and together with PTH trends. Do not treat a calcium–phosphate product of 55 as a validated universal intervention threshold; avoid hypercalcemia and address progressively or persistently elevated phosphate.

  4. Tertiary hyperparathyroidism is autonomous PTH secretion after longstanding secondary hyperparathyroidism; it may persist after transplantation but is not restricted to transplant recipients.

  5. Adult ESA treatment: target below 11.5 g/dL: Avoid normalizing Hb with ESAs. Lower Hb does not automatically require transfusion; consider symptoms, acute illness, risks, and alternatives.

  6. Iron metabolism is disrupted by hepcidin: Even with normal ferritin, patients may be functionally iron-deficient; monitor responsiveness to IV iron.

  7. CKD-associated pruritus: Check for other skin/systemic causes, moisturize, and review delivered dialysis. For persistent moderate-to-severe symptoms, consider an approved dialysis-specific treatment or carefully selected off-label therapy with the renal team. Gabapentin/pregabalin require kidney-adjusted dosing and surveillance for sedation, falls, and neurotoxicity; 300 mg three times daily is not a routine dialysis regimen. Systemic corticosteroids are not routine treatment.

  8. Proteinuria drives CKD progression: Every 1 g/day reduction in proteinuria buys ~1 year of renal function; ACE-I/ARB + SGLT2i achieve 40–50% reduction often.

  9. Suspected calciphylaxis warrants urgent multidisciplinary assessment for painful ischemic skin lesions. Review mineral treatment, dialysis, infection and anticoagulation; individualize wound care, analgesia, sodium thiosulfate and debridement.

  10. Metabolic acidosis worsens bone disease: Alkali supplementation (e.g., sodium bicarbonate 1 g BID) has been shown to slow CKD progression and improve bone health.

  11. ACE-I/ARB are renoprotective across all CKD: Work via hemodynamic (↓ intraglomerular pressure) and non-hemodynamic (↓ inflammation, ↓ fibrosis) mechanisms; always use unless contraindicated.

  12. SGLT2 inhibitors slow CKD regardless of diabetes: Recent evidence (EMPA-KIDNEY trial) shows benefit in all CKD; consider as add-on therapy to ACE-I/ARB.


XI. Practice Questions

Question 1: A 58-year-old man with CKD Stage 4 (eGFR 22 mL/min/1.73m²) has labs: Ca 8.2 mg/dL, PO4 5.8 mg/dL, PTH 456 pg/mL, 25-OH vitamin D 18 ng/mL, 1,25-OH vitamin D (calcitriol) 12 pg/mL. Which is the PRIMARY mechanism driving the elevated PTH?

  1. Hypercalcemia suppressing PTH feedback
  2. Phosphate retention → FGF23 rise → ↓ calcitriol → hypocalcemia-driven PTH rise
  3. Direct PTH synthesis from uremia
  4. Tertiary hyperparathyroidism from prior transplant failure

Correct Answer: B. Phosphate retention, reduced calcitriol and hypocalcemia contribute to secondary hyperparathyroidism. Tertiary disease reflects autonomous secretion after longstanding secondary disease and does not require a prior transplant.


Question 2: A dialysis patient presents with severe, burning pain in the feet and lower legs, out of proportion to visible skin findings, along with a livedoid rash that has progressed to necrotic ulcers over 2 weeks. Ca-Phos product is 78 mg²/dL². What is the most likely diagnosis, and what is the first intervention?

  1. Diabetic peripheral neuropathy; optimize glucose control
  2. Calciphylaxis; urgent multidisciplinary wound, pain, infection and mineral/anticoagulation assessment
  3. Critical limb ischemia from atherosclerosis; vascular surgery consult
  4. Hyperkalemic periodic paralysis; dialysate potassium adjustment

Correct Answer: B. Severe pain and evolving livedoid or necrotic lesions raise concern for calciphylaxis, which can occur without an elevated calcium–phosphate product. Arrange urgent multidisciplinary evaluation; assess infection, perfusion, wound and pain needs, calcium/phosphate/PTH trends and anticoagulation risks. Mineral therapy, sodium thiosulfate and debridement are individualized.


Question 3: A 62-year-old woman on hemodialysis (3x/week, 4-hour sessions) with underlying diabetic CKD is found to have hemoglobin 8.9 g/dL despite weekly darbepoetin alfa 60 μg. Ferritin is 340 ng/mL (high), but transferrin saturation is 18% (low). What is the BEST next step?

  1. Increase darbepoetin to 80 μg (increase ESA dose for ESA resistance)
  2. Transfuse 2 units PRBCs to target Hb 11 g/dL
  3. Give 125 mg IV iron sucrose; recheck iron panel in 2 weeks
  4. Start systemic corticosteroids to suppress hepcidin

Correct Answer: C Explanation: This patient has functional iron deficiency (high ferritin, low transferrin saturation), consistent with hepcidin dysregulation in CKD. Despite adequate iron stores (ferritin), the iron is “locked” in macrophages and cannot be mobilized effectively. IV iron (not oral) bypasses hepcidin-driven absorption block and improves erythropoietin responsiveness. Increasing ESA without correcting iron is futile. Transfusion risks iron overload and allosensitization. Corticosteroids are not standard (some experimental evidence for hepcidin suppression but not proven).


XII. References

  1. Kidney Disease: Improving Global Outcomes (KDIGO) CKD-MBD Update Work Group. KDIGO 2017 Clinical Practice Guideline Update for the Diagnosis, Evaluation, Prevention, and Treatment of Chronic Kidney Disease-Mineral and Bone Disorder (CKD-MBD). Kidney Int Suppl (2011). 2017;7(1):1. PubMed
  2. Kidney Disease: Improving Global Outcomes (KDIGO) Blood Pressure Work Group. KDIGO 2021 Clinical Practice Guideline for the Management of Blood Pressure in Chronic Kidney Disease. Kidney Int. 2021;99(3S):S1. PubMed
  3. KDOQI, National Kidney Foundation. KDOQI Clinical Practice Guidelines and Clinical Practice Recommendations for Anemia in Chronic Kidney Disease. Am J Kidney Dis. 2006;47(5 Suppl 3):S11. PubMed
  4. Moe S, Drüeke T, Cunningham J, et al. Definition, evaluation, and classification of renal osteodystrophy: a position statement from Kidney Disease: Improving Global Outcomes (KDIGO). Kidney Int. 2006;69(11):1945-1953. PubMed
  5. Hruska KA, Mathew S, Lund R, et al. Hyperphosphatemia of chronic kidney disease. Kidney Int. 2008;74(2):148. PubMed
  6. Shik J, Parfrey PS. The clinical epidemiology of cardiovascular disease in chronic kidney disease. Curr Opin Nephrol Hypertens. 2005;14(6):550-557. PubMed
  7. Seethapathy H, Brandenburg VM, Sinha S, et al. Review: update on the management of calciphylaxis. QJM. 2019;112(1):29-34. PubMed
  8. Vanholder R, Pletinck A, Schepers E, et al. Biochemical and Clinical Impact of Organic Uremic Retention Solutes: A Comprehensive Update. Toxins (Basel). 2018;10(1):33. PubMed
  9. Scarpioni R, Ricardi M, Albertazzi V, et al. Dialysis-related amyloidosis: challenges and solutions. Int J Nephrol Renovasc Dis. 2016;9:319-328. PubMed
  10. Levey AS, Coresh J. Chronic kidney disease. Lancet. 2012;379(9811):165-180. PubMed
  11. Hirakawa Y, Tanaka T, Nangaku M. Mechanisms of metabolic memory and renal hypoxia as a therapeutic target in diabetic kidney disease. J Diabetes Investig. 2017;8(3):261-271. PubMed
  12. Ikizler TA, Burrowes JD, Byham-Gray LD, et al. KDOQI Clinical Practice Guideline for Nutrition in CKD: 2020 Update. Am J Kidney Dis. 2020;76(3 Suppl 1):S1. PubMed

See Also

Clinical Content (01-Clinical-Medicine/Nephrology)

  • CKD Hub - Full Clinical Reference
  • Hypertension Management in CKD
  • Essential Renal Laboratory Tests

Butler-COM Resources

  • Butler COM - Nephrology Deep Dive

End of Handout

Last updated: 2026-02-12 | For medical students and residents in nephrology and internal medicine

Clinical Resources

  • Clinical Review: Comprehensive Nsaid Ckd Report — Comprehensive clinical review with PubMed references
  • Clinical Review: Ckd Sacubitril Review — Comprehensive clinical review with PubMed references
  • Clinical Review: Hypocalcemia Management Severe Ckd Clinical Report — Comprehensive clinical review with PubMed references
  • Clinical Review: Ckd Protein Restriction Report — Comprehensive clinical review with PubMed references
  • Clinical Review: Ckd — Comprehensive clinical review with PubMed references
  • Clinical Review: Protein Restriction In Ckd Evidence Review — Comprehensive clinical review with PubMed references
  • Clinical Review: Ckd Mbd Comprehensive Review — Comprehensive clinical review with PubMed references
  • Clinical Review: Ckd Staging Classification Review — Comprehensive clinical review with PubMed references
  • Clinical Review: Hypertesnive Nephropathy Cause Of Ckd — Comprehensive clinical review with PubMed references
  • Clinical Review: Sglt2i Ckd Notes — Comprehensive clinical review with PubMed references