CKD Comprehensive Management Pathways
Visual reference
More visual summaries for this topic
Browse the visual reference library · Download lesson Markdown
Overview
Chronic kidney disease (CKD) is defined as abnormalities of kidney structure or function present for >3 months with health implications [1]. The KDIGO 2024 Clinical Practice Guideline revolutionized CKD management by elevating SGLT2 inhibitors and finerenone to cornerstone therapies, alongside RAAS blockade and blood pressure targets. This guide integrates the complete modern management strategy: staging, pharmacotherapy, metabolic complications, and dialysis preparation [1].
Key Clinical Pearl
SGLT2 inhibitors are foundational when CKD/HF/diabetes eligibility criteria are met. KDIGO 2024 recommends them for T2D with CKD and eGFR ≥20, or for adults with CKD and eGFR ≥20 plus UACR ≥200 mg/g or heart failure. Treatment is also suggested for eGFR 20–45 with UACR <200. Once started, continuation below eGFR 20 is reasonable if tolerated until KRT; temporarily withhold during prolonged fasting, surgery, or critical illness. These criteria do not mean universal treatment across every kidney disease.
Part 1: CKD Staging and Assessment
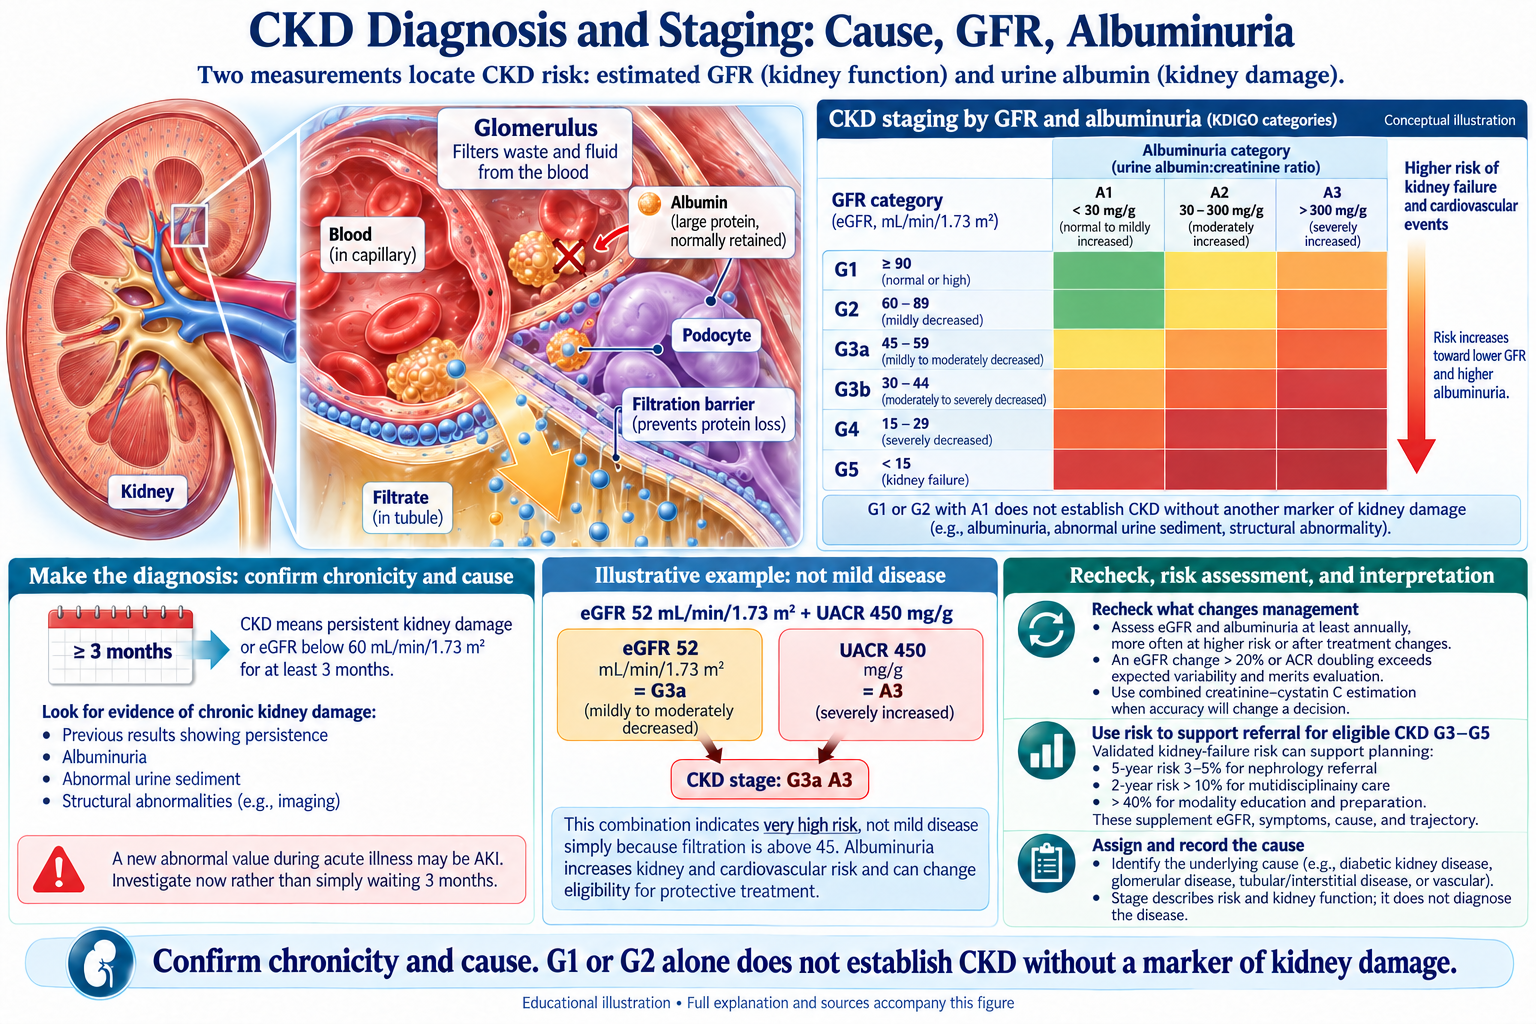
GFR-Based Stages (KDIGO 2024)
| Stage | GFR (mL/min/1.73 m²) | Interpretation |
|---|---|---|
| G1 | ≥90 | Normal or high |
| G2 | 60–89 | Mildly decreased |
| G3a | 45–59 | Mildly to moderately decreased |
| G3b | 30–44 | Moderately to severely decreased |
| G4 | 15–29 | Severely decreased |
| G5 | <15 | Kidney failure |
Albuminuria-Based Categories (Heat Map)
| Category | UACR (mg/g) | Risk |
|---|---|---|
| A1 | <30 | Normal to mildly elevated |
| A2 | 30–300 | Moderately elevated |
| A3 | >300 | Severely elevated |
Clinical Pearl: Combination of GFR + albuminuria stage predicts progression risk. A patient with G3a/A3 (eGFR 45–59 + UACR >300 mg/g) has higher risk than G3a/A1 despite same GFR.
Key Assessments at CKD Diagnosis
- Urine albumin-to-creatinine ratio (UACR) (gold standard; repeat if initial >300 mg/g)
- Blood pressure (standardized office measurement; home/ambulatory readings complement assessment and are not automatically assigned the office <120 target)
- Metabolic panel: K, PO₄, HCO₃⁻, Ca, Mg
- Bone-specific markers: Alkaline phosphatase, PTH, 25-OH vitamin D
- Lipid panel
- Hemoglobin/hematocrit (baseline for anemia management)
- Renal imaging (ultrasound or CT to assess echogenicity, size, exclude hydronephrosis)
Part 2: KDIGO 2024 Pharmacotherapy Strategy
Tier 1: SGLT2 Inhibitors (Eligibility-Based Therapy)
Recommendation: Apply the CKD, T2D, albuminuria, and HF criteria above. Check the actual product label and the disease context; major CKD trials did not establish benefit for every etiology, transplant population, or dialysis setting.
Key Evidence — DAPA-CKD: Dapagliflozin reduced the primary composite of sustained ≥50% eGFR decline, kidney failure, or kidney/CV death: HR 0.61 (39% relative reduction), median 2.4 years. The CV-death/HF-hospitalization secondary composite had HR 0.71 (29% relative reduction). A hazard ratio of 0.61 is not a 61% risk reduction. Primary trial.
- EMPA-KIDNEY trial: Empagliflozin 10 mg daily in CKD (non-diabetes cohort ≥50% of subjects)
- Primary outcome: kidney-disease progression or cardiovascular death, HR 0.72 (28% relative reduction), median 2.0 years.
- All-cause mortality did not differ significantly; do not claim a proven 25% reduction. Primary trial.
Mechanism: Proximal tubule glucose/sodium reabsorption inhibition → natriuresis, reduced intraglomerular pressure, anti-inflammatory effects.
Dosing: - Dapagliflozin: 10 mg daily (empagliflozin: 10 mg daily) - Continue even if eGFR falls below 20 mL/min/1.73 m² - Caution: genitourinary infections (5–8% increased incidence); counsel patients on symptoms
Side Effects: Euglycemic DKA (rare, <1%), genital infections, volume depletion (caution in elderly).
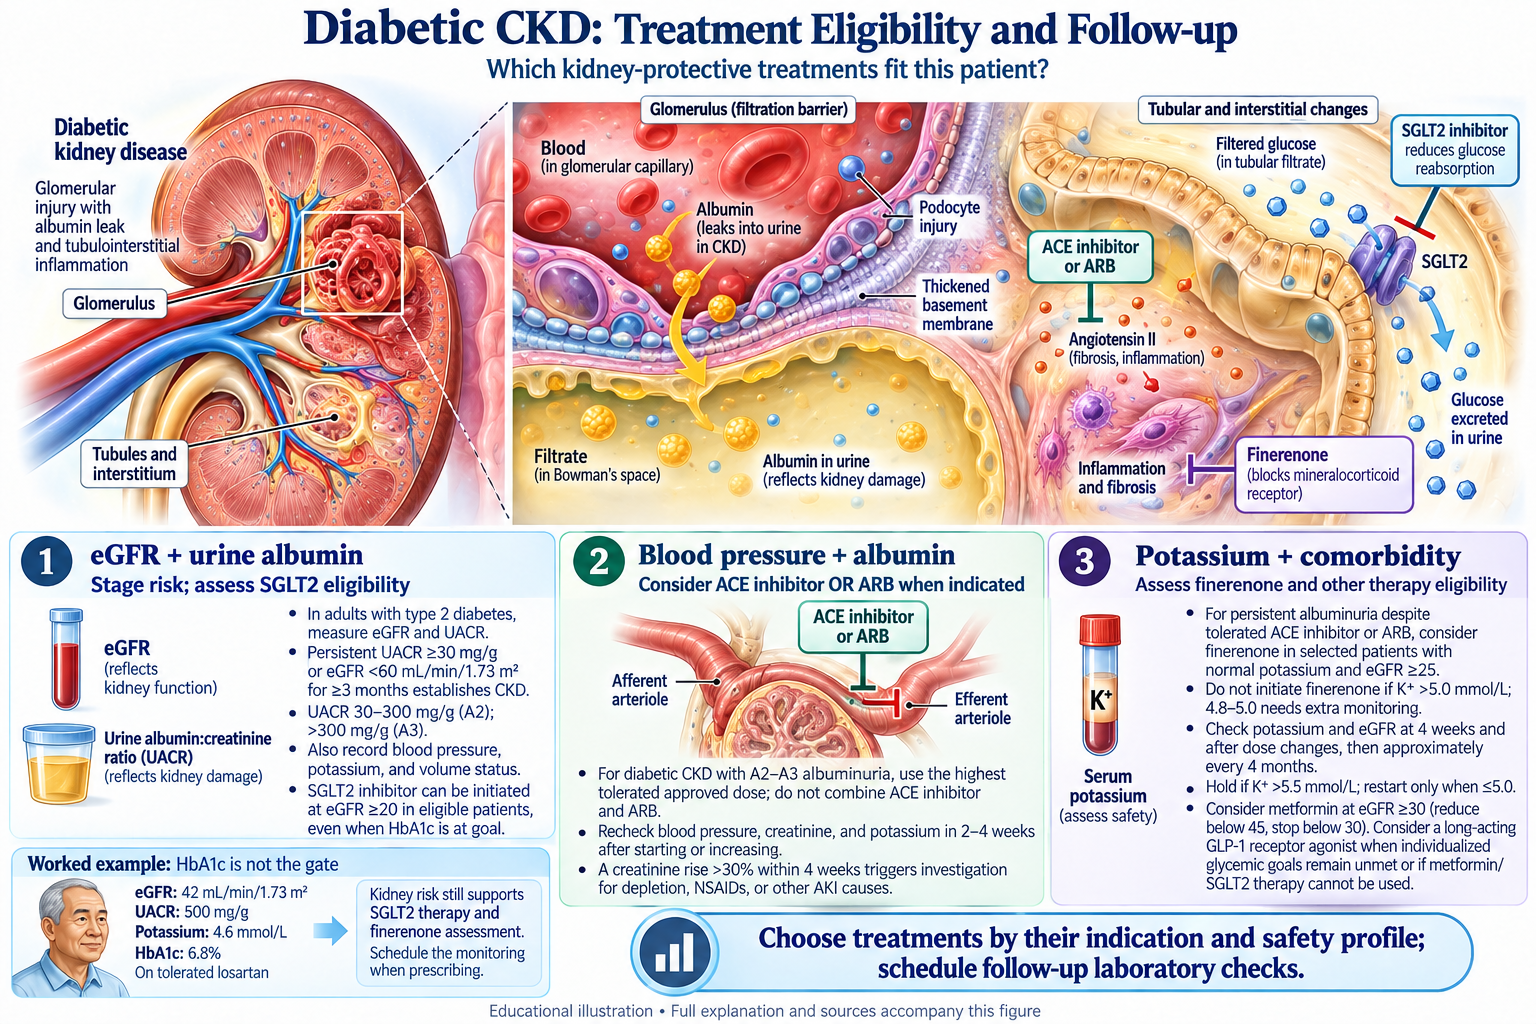
Tier 2: RAAS Blockade (ACE-I/ARB)
Recommendation: Initiate ACE inhibitor or ARB if albuminuria present (UACR ≥30 mg/g) [1].
Mechanism: Block aldosterone and angiotensin II → reduce proteinuria, lower intraglomerular pressure, anti-inflammatory.
Target: Maximum tolerated dose (not just minimum therapeutic dose).
Monitoring: Check creatinine and potassium within 2–4 weeks after starting or increasing an ACE inhibitor/ARB, sooner when risk is high. A hemodynamic creatinine rise reflects reduced efferent arteriolar tone, not afferent dilation. A rise >30% within 4 weeks prompts assessment for depletion, interacting drugs, or renovascular disease. Manage hyperkalemia when possible to preserve indicated therapy; hold/reduce when it remains uncontrolled or symptomatic hypotension occurs.
Caution: - Triple whammy: ACE-I/ARB + NSAID + diuretic → acute renal failure - Contraindicated: Pregnancy, prior angioedema, K⁺ >6.0 mEq/L
Tier 3: Finerenone (Non-Steroidal Mineralocorticoid Receptor Antagonist)
Recommendation: For CKD/T2D, finerenone is appropriate when eGFR is ≥25, potassium permits initiation, and albuminuria persists despite a maximally tolerated ACE inhibitor or ARB. The CKD/T2D indication should not be generalized to any albuminuric CKD; separate HF indications require their own phenotype and label assessment.
Key Evidence: - FIDELIO-DKD trial [3]: Finerenone 10 mg daily (titrate to 20 mg) in CKD + T2D - Primary outcome: 18% RRR in composite of ≥40% GFR decline, ESRD, or renal death - Cardiovascular outcome: 14% RRR
- FIGARO-DKD trial: Finerenone in earlier-stage CKD + T2D
- Consistent benefit across CKD stages G2–G4
Mechanism: Selective MRA (non-steroidal; hyperkalemia remains a clinically important risk) → anti-inflammatory, reduces fibrosis.
Dosing for CKD/T2D: The US label uses 10 mg daily at eGFR 25–<60 and 20 mg daily at eGFR ≥60; initiation is not recommended below 25. Do not initiate when potassium >5.0 mEq/L. Adjust by potassium, eGFR, and the product-specific algorithm.
Monitoring: Check potassium/eGFR at baseline and potassium about 4 weeks after starting or changing the dose; continue periodic monitoring, commonly every 4 months when stable in the KDIGO pathway. Hold finerenone if potassium >5.5 and consider restart when ≤5.0 according to the label. US prescribing information.
Side Effects: Hyperkalemia (more common if eGFR <30; incidence 10–15%), volume depletion, hypotension.
Tier 4: GLP-1 Receptor Agonists (If Diabetes + Obesity)
Recommendation: For T2D patients with CKD who require glucose control and have weight loss indication.
Evidence: In FLOW, semaglutide reduced the primary composite kidney/CV-death outcome in patients with type 2 diabetes and CKD [4]. This trial does not establish a fixed additive benefit from combining every kidney-protective drug class.
Advantage: Weight loss (unlike other antihyperglycemics), reduced cardiovascular events.
Monitor: Pancreatitis risk (low but real), retinopathy changes if diabetic.
Part 3: Blood Pressure Management in CKD
Target Blood Pressure
KDIGO target: For many adults with hypertension and nondialysis CKD, target systolic BP <120 mmHg when tolerated using standardized office measurement. This is not a universal home-BP target. Individualize for orthostasis, frailty, limited life expectancy, and treatment harms; use home/ambulatory measurements to complement office assessment.
Evidence: SPRINT tested intensive versus standard systolic BP targets in selected high-risk adults without diabetes. The primary benefit was a cardiovascular composite; it was not a 25% reduction in ESRD/death. Apply standardized measurement and consider tolerance, AKI, and electrolyte risks. SPRINT primary report.
Home Blood Pressure Monitoring
Preferred over office BP (office readings overestimate; home BP more predictive of progression).
Protocol: - Measure in morning (before medications) and evening - Record 3 readings, separated by 1–2 minutes, on 3+ days/week - Use validated automated device (avoid aneroid manometers) - Target: Use the clinician-agreed home target; do not directly transfer the standardized-office <120 target
Antihypertensive Strategy
First-line (for CKD with albuminuria): 1. ACE-I or ARB (proteinuria reduction) 2. Add SGLT2i (cardiac + renal benefit) 3. Add finerenone if persistent albuminuria/progression
Add second agent if BP target not met: - Calcium channel blocker (amlodipine, diltiazem): reduces proteinuria, no adverse metabolic effects - Thiazide-type diuretic (chlorthalidone, hydrochlorothiazide): caution in K⁺ disturbances
Avoid (or use with extreme caution): - Direct vasodilators (hydralazine) as monotherapy: reflex tachycardia, hypertensive tolerance - Alpha-blockers: no renal protection; increased HF risk
Part 4: Metabolic Complications of CKD
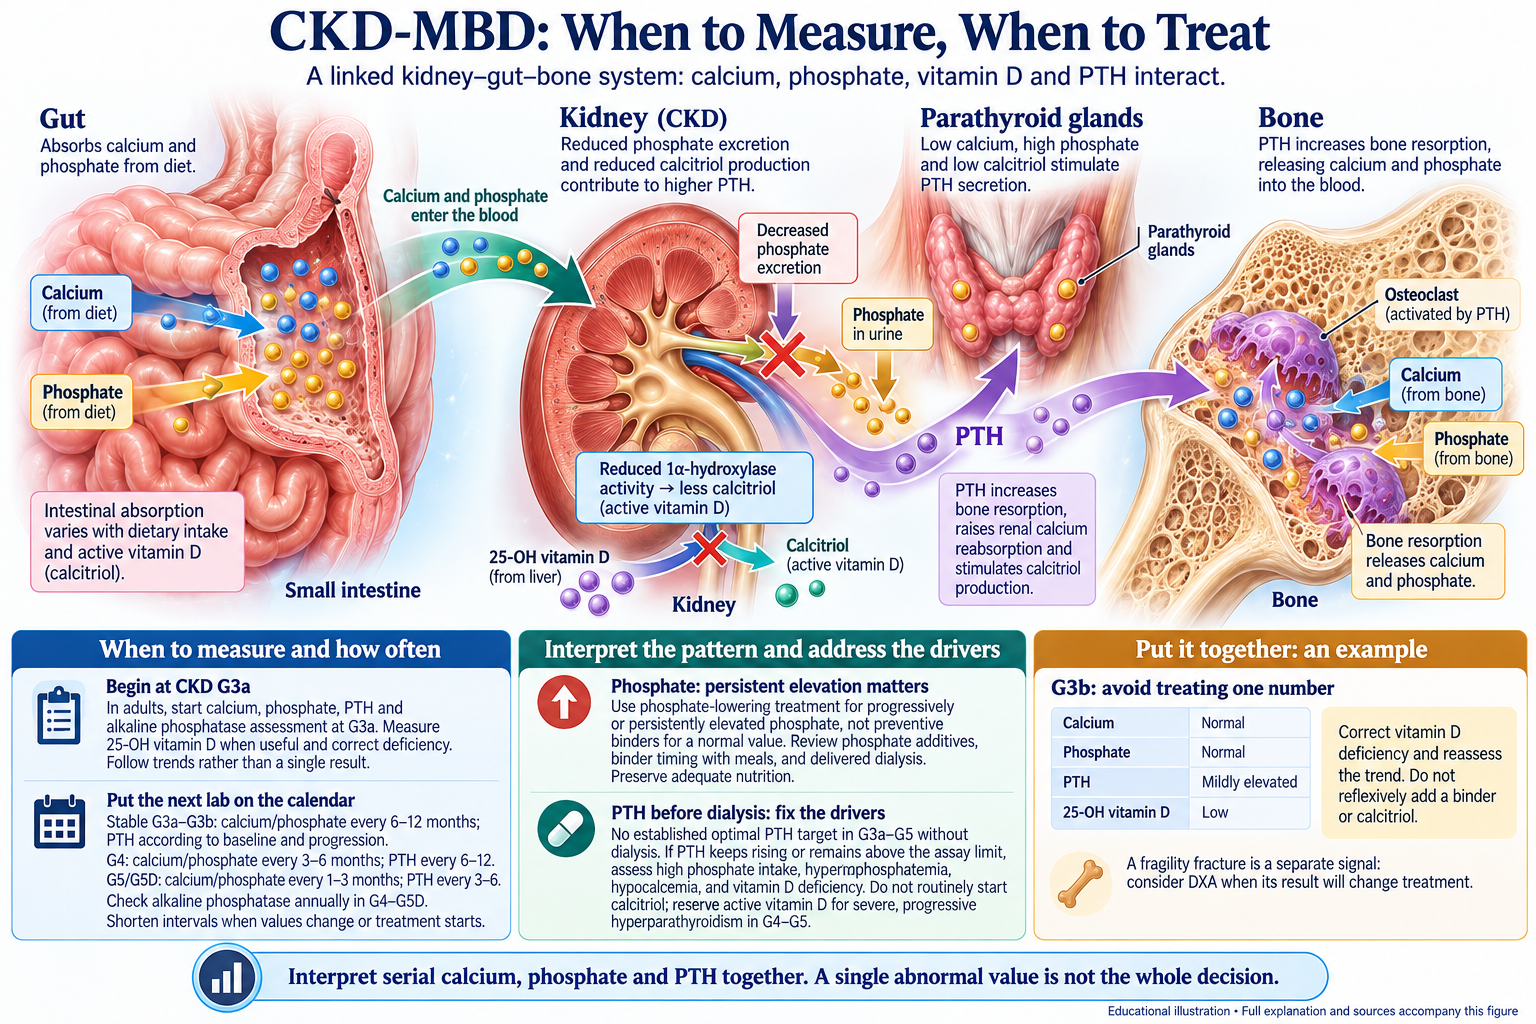
Chronic Kidney Disease–Mineral Bone Disorder (CKD-MBD)
Assess calcium, phosphate and PTH trends together, with CKD stage and treatment history. There is no single PTH target for all nondialysis CKD. Address persistently elevated phosphate with dietary counseling and, when indicated, phosphate binders such as sevelamer, lanthanum or calcium-based agents. Patiromer is a potassium binder, not a phosphate binder. Avoid routine active vitamin D solely for modest PTH elevation in nondialysis CKD; specialist management depends on severity and trends. KDIGO 2017 CKD-MBD guideline.
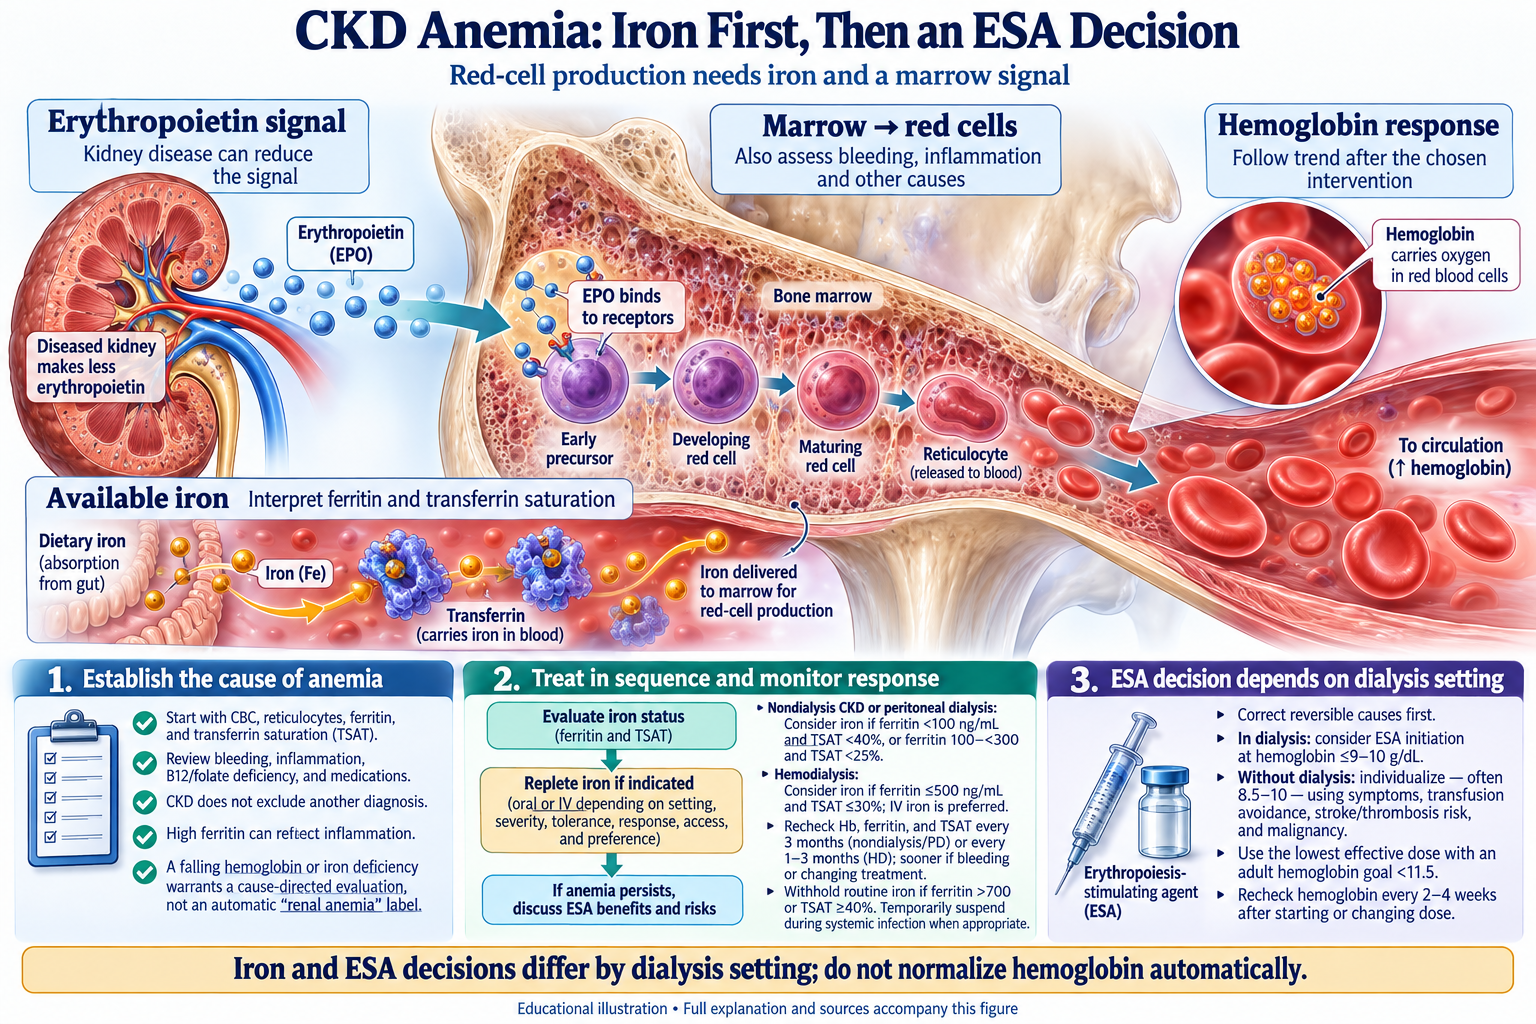
Anemia in CKD
Etiology: Erythropoietin (EPO) deficiency (85%) + chronic inflammation + reduced RBC lifespan.
Hemoglobin Target: For adults treated with an ESA, KDIGO 2026 recommends a target below 11.5 g/dL. Initiation and the working range are individualized; nondialysis CKD does not have a universal Hb <10 initiation rule. Final KDIGO 2026 anemia guideline.
Treatment Pathway: Evaluate iron status, B12/folate deficiency, bleeding, hemolysis, inflammation, and other causes before attributing anemia to CKD. For nondialysis CKD/PD, KDIGO 2026 suggests iron initiation with ferritin <100 ng/mL and TSAT <40%, or ferritin 100–<300 and TSAT <25%; for HD, ferritin ≤500 and TSAT ≤30%. Routine iron is generally withheld if ferritin >700 or TSAT ≥40%, and suspended during systemic infection. Oral or IV iron in nondialysis CKD is chosen by severity, response, tolerance, access, and preference—not eGFR alone; consider switching after an inadequate 1–3-month oral trial. Ferritin 600/TSAT18% does not automatically mandate IV iron in nondialysis CKD. ESA initiation weighs symptoms, transfusion risk, and treatment harms; use local labeling for ESA/HIF-PHI eligibility rather than treating the classes as interchangeable.
Metabolic Acidosis
Mechanisms: Reduced ammonia excretion, impaired H⁺ secretion, accumulation of organic acids.
Assessment: Serum bicarbonate is a chemistry measurement, not a blood pH. Confirm persistent metabolic acidosis and its cause before treatment [5].
Management: Individualize dietary and pharmacologic measures for clinically important acidosis. Monitor bicarbonate, blood pressure, potassium and fluid status during alkali treatment. Patiromer treats hyperkalemia; it is not an alkali replacement [5].
Evidence limit: Alkali treatment decisions should address the severity of acidosis and patient risks; a fixed 30% reduction in CKD progression is not established for all patients.
Part 5: CKD Progression Prevention Checklist
| Intervention | Target/Frequency | Evidence |
|---|---|---|
| SGLT2i | Use guideline eligibility, product label, and patient tolerance | DAPA-CKD primary composite: HR 0.61, 39% relative reduction |
| ACE-I/ARB | Initiate if albuminuria; max tolerated dose | Proteinuria reduction |
| Finerenone | CKD/T2D with eligible eGFR, potassium, and persistent albuminuria despite tolerated RAAS blockade | FIDELIO: 18% relative reduction in its kidney composite |
| SBP <120 mmHg when tolerated | Standardized office measurement; home readings complement care | KDIGO; selected-population SPRINT evidence |
| Statins | Initiate regardless of LDL (CKD is ASCVD equivalent) | 20–30% CV risk reduction |
| UACR | Repeat annually (or 6 months if proteinuria) | Track progression |
| eGFR | Repeat annually (or 3–6 months if G4–G5) | Assess slope |
| Hemoglobin | ESA-treated adult target <11.5; monitor according to stage, treatment changes, and response | Avoid overcorrection; individualize initiation |
| Bone markers | PTH, Ca, PO₄, 25-OH Vit D every 6–12 months (G3) | Prevent CKD-MBD |
| Nephrology referral | At G4 or rapidly declining GFR | Prepare for RRT |
| Flu/pneumococcal vaccine | Annual (CKD = immunocompromised) | Infection prevention |
Part 6: Dialysis Preparation (Pre-CKD 5 Pathway)
Timing of Referral to Nephrology
KDIGO Recommendations: - G4 (eGFR 15–29): Refer for CKD management intensification, education, vascular access planning - G5 (eGFR <15): Prepare for renal replacement therapy (RRT) choice and timing
Modality Selection (Patient Education Timing: G3b–G4)
| Modality | Frequency | Vascular Access | Pros | Cons |
|---|---|---|---|---|
| Hemodialysis (HD) | 3×/week, 4–5 hrs | AVF (preferred), AVG, CVC | Efficient toxin removal; less dietary restriction | Cardiovascular stress; catheter-related infections; time-dependent |
| Peritoneal Dialysis (PD) | Daily (4–6 exchanges/day) | Peritoneal catheter | Home-based; continuous; cardiovascular advantages | Peritonitis risk; weight gain; declining residual function over time |
| Twice-weekly HD | 2×/week, 4–5 hrs (with RKF) | AVF, AVG | For patients with significant residual kidney function | Limited solute clearance; requires good residual function |
| Nocturnal HD | 3–6×/week, 6–8 hrs | AVF, AVG | Better solute/fluid removal; improved quality of life | Limited availability; cost |
Vascular Access Planning (G4 Stage)
Timing: Initiate access planning when eGFR ~20 mL/min/1.73 m² to allow maturation.
Preferred Hierarchy: 1. Arteriovenous fistula (AVF): Autologous vein-to-artery; lowest infection/stenosis risk; 6–12 weeks maturation - Forearm (cephalic-radial preferred) or upper arm (brachial-axillary) 2. Arteriovenous graft (AVG): Synthetic prosthetic; shorter maturation (2–4 weeks); higher complication rate 3. Central venous catheter (CVC): Temporary access only; highest infection/thrombosis risk; should not be chronic access
Nephrologist’s Role: Refer to vascular surgeon for fistula evaluation; optimize BP, avoid BP draws/IV lines in non-fistula arm.
Advance Care Planning (G4–G5)
- Discuss RRT options (HD vs PD vs conservative care)
- Address goals of care, quality-of-life expectations, family preferences
- Document wishes if progression to G5 and RRT initiation needed
- Palliative care consultation if considering conservative (non-dialytic) management
Part 7: Special Populations
CKD + Heart Failure
Unique Challenge: Diuretics reduce BP/perfusion → risk of AKI progression; RAAS blockade may worsen hyperkalemia.
Strategy: Use SGLT2 therapy when the HF/CKD indication and product label fit; outcome benefits differ by trial and phenotype. Treat congestion with an appropriate diuretic and reassess perfusion, kidney function, and electrolytes. For HFrEF, spironolactone/eplerenone have established indication-specific evidence; do not automatically substitute finerenone because CKD is present. Finerenone requires its own CKD/T2D or eligible HF indication, potassium monitoring, and avoidance of unnecessary overlapping MRA therapy.
CKD + Diabetes
Layer kidney-protective therapies when the patient meets each treatment indication and can tolerate monitoring. Do not assume that individual trial effect sizes can be added together [5].
Goals: - Tight glycemic control (HbA₁c 7–8%); avoid hypoglycemia (↑ CV risk in CKD) - Initiate SGLT2i immediately at DM diagnosis if eGFR ≥20 - Add finerenone if albuminuria persists on ACE-I/ARB + SGLT2i - GLP-1 RA for additional glycemic and cardiometabolic benefit
CKD + Obesity
Advantage: SGLT2i provide weight loss (2–3 kg over 6 months); GLP-1 RA provide greater weight loss (4–8 kg).
Recommendation: Prefer these agents in obese CKD patients; defer to these drugs as primary weight-loss therapy.
Warning Flags
Warning 1: Hyperkalemia in Advanced CKD
RAAS blockers and finerenone can increase potassium; SGLT2 inhibitors are not potassium-sparing drugs and should not be grouped with them mechanistically. Advanced CKD, interacting medicines, and acute illness increase monitoring needs. Assess each treatment’s eligibility and potassium response.
Management: Use drug-specific monitoring and hold/restart rules; do not wait for potassium >6.0 before applying the finerenone label threshold. Review supplements, potassium salt substitutes, constipation, acidosis, and interacting medicines. Potassium binders may help preserve indicated therapy in selected patients; dietary advice should address actual sources and nutritional needs rather than a blanket plant-food ban.
Warning 2: Acute Decline in GFR on ACE-I/ARB
30% SCr rise acceptable after initiation (due to hemodynamic changes). However, >30% rise or rise >0.5 mg/dL warrants reassessment: - Rule out AKI (dehydration, infections, NSAIDs) - Check renal artery stenosis if sudden decline - Consider dose reduction if marked hyperkalemia
Warning 3: Volume Overload in Dialysis Preparation
Paradoxically, CKD G4 can present with volume expansion (inability to excrete Na + H₂O) while still maintaining systolic hypertension. This requires: - ACE-I/ARB + loop diuretics (to reduce volume + BP) - Sodium restriction (<2000 mg/day) - Fluid restriction if SIADH or severe hyponatremia
References
Kidney Disease: Improving Global Outcomes (KDIGO) CKD Work Group. KDIGO 2024 Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease. Kidney Int. 2024;105(4S):S117. PubMed
[2] Heerspink HJL, Stefansson BV, Chertow GM, et al. Dapagliflozin in patients with chronic kidney disease. N Engl J Med. 2020;383:1436–1446. PubMed
[3] Bakris GL, Agarwal R, Chan JC, et al. Effect of finerenone on chronic kidney disease outcomes in type 2 diabetes. N Engl J Med. 2020;383:2219–2229. PubMed
[4] Perkovic V, Tuttle KR, Rossing P, et al. Effects of Semaglutide on Chronic Kidney Disease in Patients with Type 2 Diabetes. N Engl J Med. 2024. PubMed PMID 38785209
Kidney Disease: Improving Global Outcomes (KDIGO) CKD Work Group. KDIGO 2024 Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease. Kidney Int. 2024;105(4S):S117. PubMed
Last updated: 2026-02-28 Board-review quality curriculum for nephrology education.
Also on this topic
The same subject at other levels of depth.
- Lecture: Comprehensive CKD Management 2025