Diabetic Kidney Disease: Comprehensive Management Overview
Visual reference
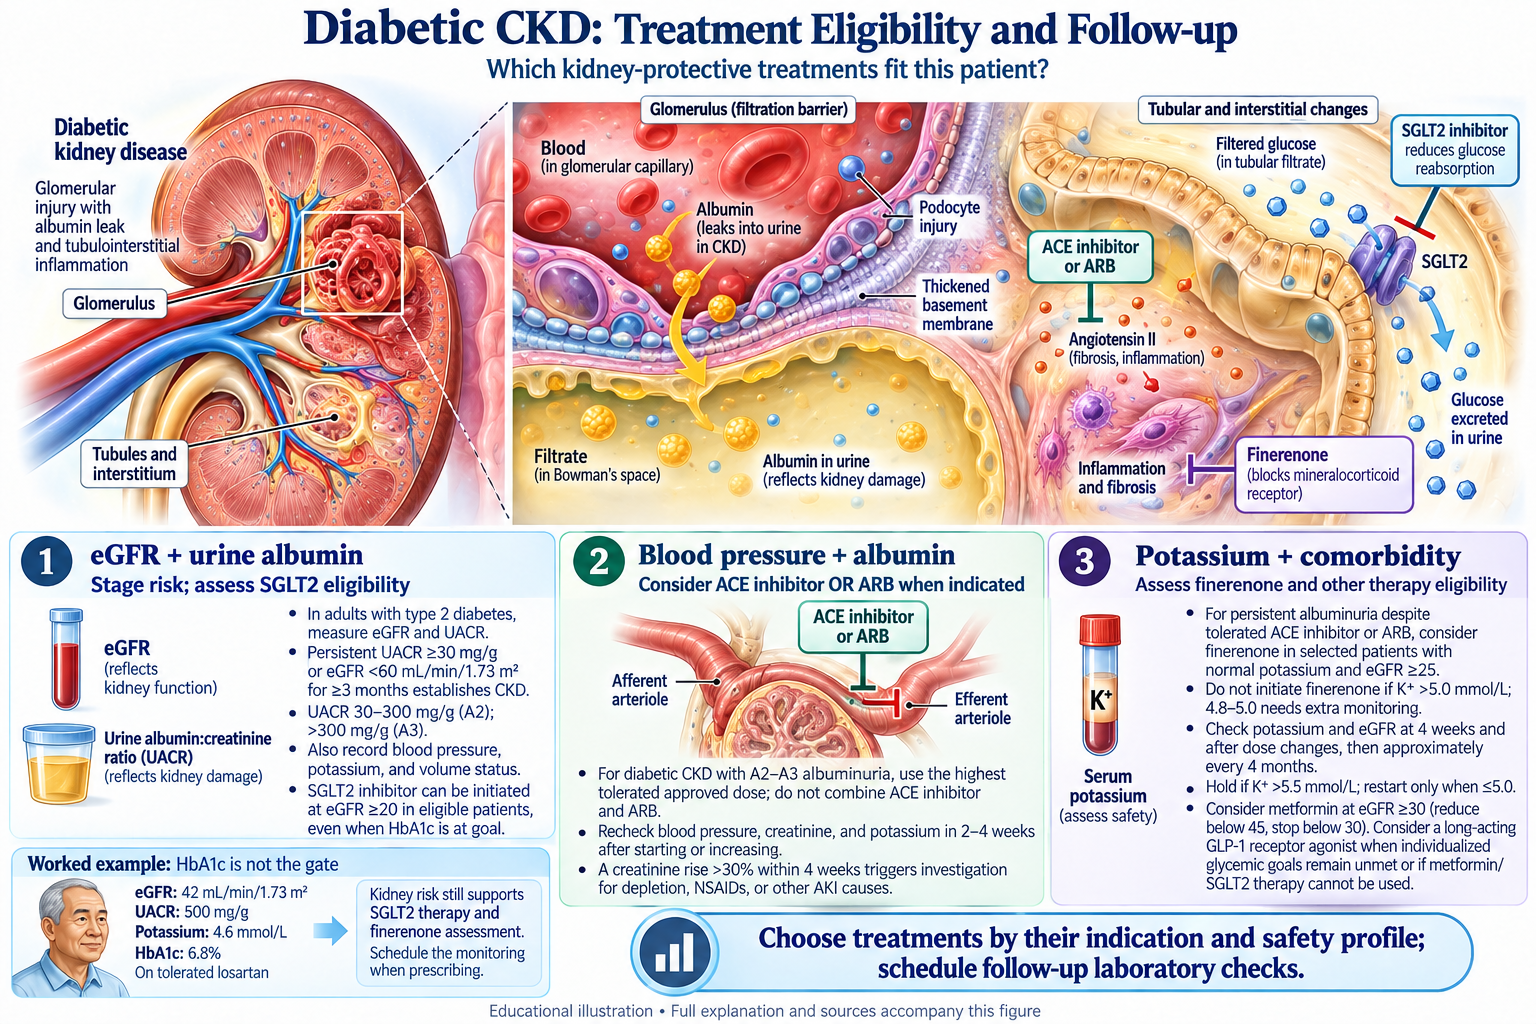
Browse the visual reference library · Download lesson Markdown
Learning Objectives
By the end of this handout, students will be able to: 1. Understand the pathophysiology and clinical manifestations of diabetic kidney disease (DKD) 2. Compare the efficacy of RAAS inhibitors, SGLT2 inhibitors, finerenone, and GLP-1 receptor agonists 3. Apply evidence-based sequencing of medications for DKD management 4. Identify appropriate candidates for each drug class and manage side effects 5. Calculate number needed to treat (NNT) and communicate outcomes to patients
Epidemiology & Pathophysiology
DKD Burden
- Leading cause of chronic kidney disease globally (affects ~40% of diabetic patients)
- 537 million individuals with diabetes worldwide
- Mortality: 30-40% 5-year mortality rate (cardiovascular disease #1 cause)
Mechanisms of Kidney Injury
- Glomerular hyperfiltration → intraglomerular pressure elevation
- Inflammation → cytokine activation, immune cell infiltration
- Fibrosis → TGF-β activation, myofibroblast proliferation
- Tubular dysfunction → impaired sodium/glucose reabsorption
- Metabolic dysfunction → mitochondrial injury, oxidative stress
Key Point: DKD is multifactorial; single-agent therapy insufficient for optimal outcomes.
Four Pillars of DKD Therapy
Pillar 1: RAAS Inhibition (ACE-I/ARBs)
Comparative Efficacy Table
| Parameter | ACE Inhibitors | ARBs | Clinical Significance |
|---|---|---|---|
| Kidney failure prevention | 39% reduction (RR 0.61) | 18% reduction (RR 0.82) | ACE-I superior |
| All-cause mortality | 22% reduction* | No benefit | ACE-I advantage |
| Doubling SCr prevention | 42% reduction | 21% reduction | ACE-I better |
| Albuminuria reduction | 25-35% | 25-35% | Similar |
| Hyperkalemia risk | 3.4% absolute ↑ | 3.9% absolute ↑ | Similar |
| Cough incidence | 10-15% | <1% | ARB better tolerated |
| NNT for kidney failure prevention | 67 | — | Modest benefit |
*Only at maximally tolerated doses
Key Insights
- Both are foundational, but ACE-I shows slight edge in mortality when dosed optimally
- Direct comparisons show minimal difference between ACE-I and ARBs
- Uptitration critical: Full-dose therapy required; many patients undertreated
- Implementation gap: Only 17% of eligible CKD patients initiated RAAS blockade within 1 year of diagnosis
Pillar 2: SGLT2 Inhibitors — Paradigm Shift
Major Trials Summary
| Trial | n | Population | Primary Outcome RRR | NNT | Key Secondary |
|---|---|---|---|---|---|
| CREDENCE (Canagliflozin) | 4,401 | T2DM + CKD stages 2-3 | 30% kidney/CV composite | 23 | 32% ESKD reduction; 31% CV death/HHF |
| DAPA-CKD (Dapagliflozin) | 4,304 | CKD ± T2DM | 39% kidney/CV composite | 19 | 46% eGFR ≥50% decline; 31% mortality |
| EMPA-KIDNEY (Empagliflozin) | 6,609 | CKD ± T2DM | 28% kidney/CV composite | 26 | 29% progression; 14% hospitalization |
Meta-Analysis: 13 Trials, 90,413 Participants
- 37% reduction in kidney disease progression (HR 0.63, 95% CI 0.58-0.69)
- Benefits across all: CKD stages, albuminuria levels, diabetic + non-diabetic disease
- Rapid onset: Benefit curves separate within 3-6 months of treatment initiation
- Albuminuria reduction: 30-40%
Mechanisms of Renoprotection
- Reduction in intraglomerular pressure via tubuloglomerular feedback restoration
- Decreased tubular workload and oxygen consumption
- Metabolic reprogramming favoring ketone utilization
- Anti-inflammatory and anti-fibrotic effects
- Direct natriuretic and blood pressure effects
Clinical Implementation
- Initiate regardless of glycemic control (not just for diabetics)
- Start early: Benefit appears within 3-6 months
- In T2D with CKD, initiate an SGLT2 inhibitor with proven benefit at eGFR ≥20; once started, continuing below 20 can be reasonable if tolerated until kidney replacement therapy is initiated.
- Expected eGFR dip: 3-5% decline in first weeks (benign hemodynamic change)
- Side effect: Genital infections (educate on hygiene; consider prophylaxis if recurrent)
Pillar 3: Non-Steroidal MRA (Finerenone)
Trial Results (FIDELITY Pooled Analysis)
| Outcome | FIDELIO-DKD | FIGARO-DKD | FIDELITY Pooled |
|---|---|---|---|
| Population | Advanced CKD (eGFR 44) | Earlier CKD (eGFR 68) | Combined |
| Kidney outcomes reduction | 18% (HR 0.82) | 13% (HR 0.87) | 23% (HR 0.77) |
| CV outcomes reduction | 14% (HR 0.86) | 13% (HR 0.87) | 14% (HR 0.86) |
| Kidney failure reduction | 13% | Limited | 20% |
| Albuminuria reduction | 31% | 32% | 32% |
| NNT (kidney failure) | — | — | 48 |
| Hyperkalemia ≥5.5 mmol/L | 15.8% vs 7.8% | 10.8% vs 5.3% | 14% vs 6.9% |
Unique Advantages Over Spironolactone
- More balanced tissue distribution (kidney-selective)
- Greater MR selectivity (fewer off-target effects)
- Lower hyperkalemia risk vs steroidal MRAs
- Anti-inflammatory and anti-fibrotic beyond hemodynamics
Critical Combination Data
- Benefits preserved with SGLT2 inhibitors: Interaction p=0.63 (non-significant)
- Safe combination: No excess hyperkalemia beyond expected from each agent
- Supports use of both agents as complementary therapies
Pillar 4: GLP-1 Receptor Agonists — Emerging Fourth Pillar
FLOW Trial: Semaglutide in DKD
| Outcome | Semaglutide | Placebo | HR | ARR | NNT |
|---|---|---|---|---|---|
| Primary composite (kidney failure, ≥50% eGFR ↓, kidney/CV death) | 18.7% | 23.2% | 0.76 | 4.5% | 22 |
| Kidney-specific composite | 15.2% | 18.7% | 0.79 | 3.5% | 29 |
| CV death | 5.2% | 7.0% | 0.71 | 1.8% | 56 |
| MACE (major adverse CV) | 11.8% | 14.0% | 0.82 | 2.2% | 45 |
| All-cause mortality | 9.0% | 11.0% | 0.80 | 2.0% | 50 |
| eGFR slope benefit | — | — | — | +1.16 mL/min/year | — |
| UACR reduction | — | — | — | 32% greater | — |
Trial Design (FLOW)
- 3,533 T2DM patients with CKD (eGFR 25-75)
- Albuminuria requirements stratified by eGFR
- Trial stopped early due to efficacy
- Benefit consistent across all CKD stages
Mechanisms of Kidney Protection
- Direct natriuretic effects (NHE3 inhibition)
- Anti-inflammatory actions
- Improved glycemic control (without hypoglycemia risk)
- Weight loss (mean 5.4 kg)
- Blood pressure reduction
- Direct anti-fibrotic effects
Clinical Implementation Notes
- Preserved benefit with SGLT2i: No interaction (p=0.755)
- Side effects: GI (nausea) common but manageable; no increase in serious AEs
- Slow titration: Improves GI tolerance
- Cost: Highest of four pillars (~$800-1000/month)
Biomarkers & Monitoring
Albuminuria: The Therapeutic Target
Why albuminuria matters: - Unlike heart failure (natriuretic peptide resistance), albuminuria remains modifiable throughout DKD - 30% albuminuria reduction associated with ~23% reduction in kidney failure risk - Target: <30 mg/g (or 50-70% reduction from baseline)
Expected Albuminuria Reductions by Agent
- ACE-I/ARB: 25-35%
- SGLT2i: 30-40%
- Finerenone: 30-35%
- GLP-1 RA: 30-40%
- Combination: Can achieve >50-60% reduction
eGFR Initial “Dip” — Expected & Benign
| Agent | Initial Decline | Mechanism |
|---|---|---|
| ACE-I/ARB | 5-10% | Efferent vasodilation → pressure drop |
| SGLT2i | 3-5% | Tubuloglomerular feedback restoration |
| Finerenone | 2-3% | Afferent vasodilation |
Key Point: This dip reflects beneficial hemodynamic changes. Do NOT discontinue therapy. Long-term eGFR slopes improve dramatically with all agents.
Monitoring Schedule
- New initiation: Labs at 2 weeks (K⁺, Cr, BP)
- Established therapy: Q3-6 months (K⁺, Cr, eGFR slope)
- Albuminuria: Annually
- HbA1c: Q3-6 months (if on GLP-1 RA)
Optimal DKD Management: Sequencing & Targets
Step 1: Foundation Therapy (Initiate Weeks 0-4)
├─ ACE inhibitor OR ARB (maximal tolerated dose)
│   └─ lisinopril/enalapril: target 20-40 mg/day
│   └─ losartan/valsartan: target 80-160 mg/day
│   └─ Monitor: K⁺, Cr at 2 weeks
│
└─ Add SGLT2 inhibitor (regardless of glycemia)
    └─ empagliflozin 10 mg OR dapagliflozin 10 mg daily
    └─ canagliflozin 100 mg daily
    └─ Educate: Genital hygiene, sick-day management, volume status
Target: Completed within 3 months of DKD diagnosis
Step 2: Risk Stratification (Weeks 12-16)
Finerenone in CKD with T2D: Consider persistent albuminuria despite tolerated ACEi/ARB with eGFR ≥25 and suitable potassium. Do not initiate if K⁺ >5.0 mmol/L; K⁺ 4.8–5.0 calls for added monitoring. Start 10 mg if eGFR 25–<60 or 20 mg if ≥60 for this indication. Check potassium/eGFR at 4 weeks and after dose changes, then about every 4 months; withhold if K⁺ >5.5 and consider restarting at 10 mg only when ≤5.0. Use the current product label and clinical context.
If HbA1c >7% or high cardiovascular risk: - Add GLP-1 RA (semaglutide 0.25 mg → titrate to 1.0 mg weekly) - Slower titration improves GI tolerance - Recheck labs at 4 weeks
Target: Complete assessment by 6 months
Step 3: Optimization (Months 6-12)
- Titrate all agents to maximally tolerated doses
- Monitor potassium closely (especially if on both RAAS blocker + finerenone)
- Track eGFR slope (should improve/stabilize)
- Reinforce adherence; address cost barriers
- Target: All eligible therapies at goal doses by 12 months
Stage-Specific Approaches
Early DKD (eGFR >60, UACR 30-300 mg/g)
Priority: Primary prevention - SGLT2i critical (regardless of HbA1c) - GLP-1 RA for additional glycemic control + CV benefit - ACE-I/ARB if hypertensive or albuminuria present
Moderate DKD (eGFR 30-60, UACR >30 mg/g)
Progression risk: Select each protective therapy by indication and tolerability; all four classes are not obligatory for every patient. Use the BP goal and measurement method from the chosen guideline without converting standardized SBP <120 into a presumed routine-office value. Continue tolerated SGLT2 therapy below the initiation threshold when appropriate, with reassessment during illness.
Advanced DKD (eGFR <30)
Priority: Prepare for renal replacement therapy while slowing progression - Continue ACE-I/ARB (careful monitoring) - SGLT2i shown beneficial down to eGFR 20; continue - Limited data for finerenone + GLP-1 RA at this stage - Assess readiness for dialysis/transplant - Involve nephrology specialists
Safety Monitoring & Side Effects
ACE-I/ARB Safety
| Concern | Management |
|---|---|
| Hyperkalemia | Accept ≤30% Cr rise; K⁺ <5.5 = continue; dietary K⁺ counseling |
| Acute kidney injury | Expected 5-10% eGFR dip; monitor 2 weeks; discontinue if decline >30% |
| Angioedema (ACE-I) | Switch to ARB if occurs |
SGLT2 Inhibitor Safety
| Concern | Management |
|---|---|
| Genital infections | Hygiene education (wipe front-to-back); prophylactic fluconazole if recurrent |
| Volume depletion | Counsel on adequate hydration; hold before major surgery |
| Euglycemic DKA (rare) | Educate on sick-day rules; hold during acute illness |
Finerenone Safety
| Concern | Management |
|---|---|
| Hyperkalemia | Start 10 mg if eGFR <60; recheck K⁺ at 1 month; hold if ≥5.5; retry after correction |
| Hypotension | Monitor BP; reduce if SBP <120 persistently |
GLP-1 RA Safety
| Concern | Management |
|---|---|
| GI symptoms (nausea) | Slow titration; small frequent meals; antiemetic if needed |
| Injection site reactions | Rotate injection sites; reassure usually self-limited |
| Pancreatitis (very rare) | Educate on warning signs; D/C if suspected |
The Implementation Gap: Why Therapies Underused
| Therapy | Eligible | Actually Receiving | Gap | Barriers |
|---|---|---|---|---|
| ACE-I/ARB | 90% | 40-70% | 20-50% | Hyperkalemia fears, creatinine rise concerns, lack of uptitration |
| SGLT2i | 80% | 10-30% | 50-70% | Cost, safety concerns, “diabetes drug” perception |
| Finerenone | 60% | <5% | >90% | New therapy, hyperkalemia monitoring, cost |
| GLP-1 RA | 70% | 5-15% | 55-65% | Injectable route, GI side effects, cost/access |
Clinical Pearl: Implementation of existing therapies prevents more kidney failure cases than discovery of new drugs.
Cost-Effectiveness & Patient Communication
Cost Per Quality-Adjusted Life Year (QALY)
- ACE-I: Dominant (cheapest + most effective)
- SGLT2i: $30-50K/QALY
- Finerenone: $40-60K/QALY
- GLP-1 RA: $50-80K/QALY
- Combination therapy: Cost-effective by standard US thresholds (<$100K/QALY)
Key Messages for Patients
- “DKD is serious but treatable.” Modern medications can slow/stop progression.
- “Multiple medications work better.” Like managing hypertension, combination therapy provides better results.
- “Starting early matters.” Benefits appear within months, compound over years.
- “Expect lab dips initially.” Kidney numbers may drop slightly—this is beneficial long-term.
- “Regular monitoring keeps you safe.” Blood tests ensure medications work without harm.
- “Cost assistance exists.” Patient assistance programs available for all drug classes.
Practice Questions
Question 1: A 62-year-old with T2DM, eGFR 48, UACR 150 mg/g, and hypertension is started on lisinopril. Two weeks later: K⁺ 5.3, Cr increased from 1.5 to 1.8 mg/dL (27% rise). What is the most appropriate action?
- Discontinue lisinopril immediately; switch to nifedipine
- Continue lisinopril; this is expected; recheck labs in 4 weeks
- Reduce lisinopril dose by half
- Assess potassium severity, ECG/symptoms, reversible causes and medication exposure; use the local acute pathway if severe, or a suitable chronic potassium-lowering strategy with follow-up when appropriate
Answer: B — A 27% creatinine rise is within acceptable parameters (up to 30%). This reflects hemodynamic benefit, not true kidney injury. Continue therapy, recheck labs, and plan to add SGLT2i next.
Question 2: Your T2DM patient is on lisinopril 40 mg, empagliflozin 10 mg, and finerenone 20 mg, but UACR is still 120 mg/g after 6 months. HbA1c is 8.2%. What is the next step?
- Increase finerenone to maximum dose
- Add GLP-1 RA (semaglutide) for additional albuminuria reduction
- Switch empagliflozin to dapagliflozin (different SGLT2i)
- Consider kidney biopsy to reassess diagnosis
Answer: B — GLP-1 RA provides additional 30-40% albuminuria reduction and improves glycemia. Also, elevated HbA1c (8.2%) suggests benefit from GLP-1 agent.
Question 3: A 71-year-old with T2DM, CKD stage 3b, and mild albuminuria wants to avoid “too many pills.” Which single agent provides the most evidence-based kidney protection in early DKD?
- Increase lisinopril dose
- Start SGLT2 inhibitor
- Add finerenone
- Start GLP-1 receptor agonist
Answer: B — SGLT2i demonstrates 37% kidney protection across all CKD stages, benefits both diabetic and non-diabetic disease, and has the largest clinical trial base. If forced to choose one agent beyond RAAS blockade, SGLT2i is the highest priority.
Summary: The Four Pillars At-A-Glance
| Pillar | Mechanism | Kidney Failure RRR | NNT | Cost/Month | Uptake |
|---|---|---|---|---|---|
| RAAS-I | Hemodynamic (efferent dilation) | 20-40% | 67 | $5-20 | 40-70% |
| SGLT2i | Hemodynamic + metabolic | 30-40% | 26 | $400-500 | 10-30% |
| Finerenone | Aldosterone + inflammation | 20-25% | 48 | $400-500 | <5% |
| GLP-1 RA | Metabolic + hemodynamic | 20-30% | 22 | $800-1000 | 5-15% |
Bottom Line: Combination therapy targeting multiple mechanisms provides 50-60% reduction in kidney failure risk compared to no treatment. Optimal care requires overcoming implementation barriers and patient education.
See Also
Clinical Content (01-Clinical-Medicine/Nephrology)
- CKD Hub - Full Clinical Reference
- Essential Renal Laboratory Tests
Atomic Notes (ZK)
- RAAS System and Blood Pressure Regulation
Butler-COM Resources
- Butler COM - Nephrology Deep Dive
Additional Resources
- Full Comprehensive Management Report
- KDIGO 2022 Diabetes Management in CKD Guideline
- FLOW Trial: GLP-1 Receptor Agonists in CKD
This handout emphasizes rapid, early, multi-targeted therapy as the modern standard for DKD management. The evidence base supports combination therapy with sequential addition of agents rather than traditional monotherapy approaches.
Also on this topic
The same subject at other levels of depth.
- Clinical Mastery deep dive: Diabetic Kidney Disease Treatment