Urinalysis Master Diagnostic Algorithm
Visual reference
Browse the visual reference library · Download lesson Markdown
Introduction: The Underutilized Diagnostic Tool
Urinalysis remains one of the most powerful diagnostic tools in clinical medicine, yet is often ordered but not carefully interpreted. A methodical, stepwise approach to urinalysis—dipstick interpretation followed by microscopic analysis—reveals specific pathophysiologic processes occurring within the kidneys and urinary tract. This guide teaches pattern recognition for urinalysis as a diagnostic window into renal disease [1].
Urinalysis is not a screening test—it is a targeted diagnostic tool. The findings must be integrated with BMP, renal function, imaging, and serologic markers to construct a differential diagnosis.
Part 1: Dipstick Analysis
The Seven Key Dipstick Parameters
1. pH (4.5–8.0 normal)
| pH | Causes | Clinical Significance |
|---|---|---|
| Acidic (< 5.5) | Meat-based diet, metabolic acidosis, diarrhea | Favors uric acid stone formation |
| Neutral (6.5–7.0) | Mixed diet, normal | Normal range |
| Alkaline (> 7.5) | Vegetarian diet, UTI (urease-producing organisms), alkali therapy, respiratory alkalosis | Favors phosphate/calcium stone formation (triple phosphate) |
Clinical Pearl: Urine pH interpretation requires timing—pH changes rapidly if specimen sits at room temperature (bacteria consume acids, pH rises).
2. Specific Gravity: Interpret with the Collection Context
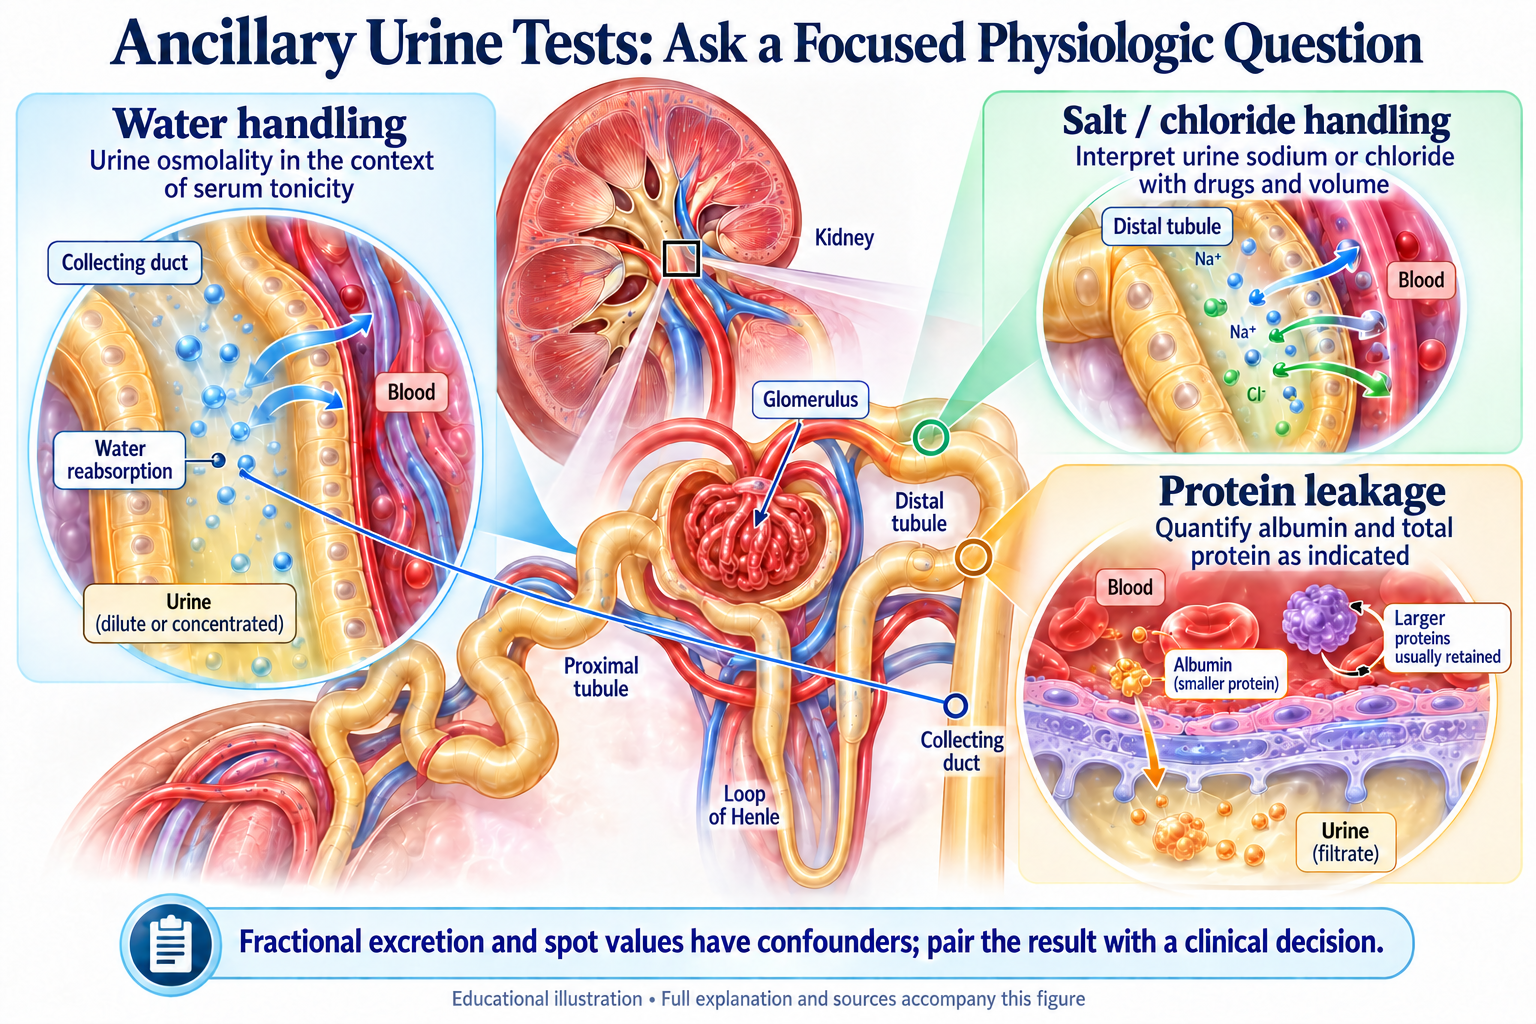
Specific gravity estimates urine concentration. A single result does not diagnose dehydration, SIADH, tubular injury, or normal kidney function. Compare it with fluid intake, urine output, serum sodium, medications, and prior results.
| Finding | Useful next step |
|---|---|
| Very dilute urine | If polyuria is present, quantify urine volume and measure serum sodium and urine osmolality before assigning a cause. |
| Repeated values near 1.010 | Consider impaired concentrating ability only in the clinical context; a single value is insufficient. |
| High specific gravity | Assess fluid balance and check for glucose, protein, or recent contrast that may affect the measurement. |
Clinical pearl: Specific gravity and osmolality are different measurements. Protein or radiographic contrast can disproportionately raise specific gravity, depending on the measurement method. Use measured urine osmolality when evaluating water balance or unexplained discordant results.
3. Protein: Quantify a Positive Dipstick
Dipstick grades reflect protein concentration in the sample, predominantly albumin. They cannot be converted directly into milligrams per day. Concentrated urine can exaggerate a grade; dilute urine and nonalbumin proteins can produce misleadingly low results.
| Dipstick result | Interpretation and action |
|---|---|
| Negative | Below the strip's detection threshold; does not exclude CKD, moderately increased albuminuria, or light-chain proteinuria. |
| Trace to 1+ | Confirm with a quantitative ratio when clinically indicated; repeat a first-morning sample to assess persistence. |
| 2+ to 4+ | Quantify promptly and assess eGFR, sediment, serum albumin, edema, and systemic features. The grade alone does not establish nephrotic-range proteinuria. |
- Urine albumin-to-creatinine ratio (ACR): preferred initial adult CKD albumin assessment. A1 <30, A2 30–300, A3 >300 mg/g. Confirm persistence and interpret with eGFR.
- Urine protein-to-creatinine ratio (PCR/UPCR): measures total protein. It is not interchangeable with ACR. Unexpectedly high PCR with low ACR raises concern for nonalbumin protein.
- Calculation: ratio in mg/g = (urine albumin or protein in mg/dL ÷ urine creatinine in mg/dL) × 1,000. Example: protein 60 and creatinine 100 mg/dL gives PCR 600 mg/g.
- Adult nephrotic-range proteinuria: approximately PCR >3,500 mg/g or protein excretion >3.5 g/day. Assess hypoalbuminemia and edema to establish the clinical syndrome.
- Timed collection: useful when spot ratios are discordant or a precise estimate changes management; collection errors remain possible.
See KDIGO 2024 CKD guidance for confirmation and albuminuria assessment and the 2022 urinalysis review for dipstick limitations.
4. Blood on Dipstick (Negative–3+)
| Finding | Interpretation | Differential |
|---|---|---|
| Blood + RBCs on microscopy | True hematuria | Glomerular (casts, proteinuria), IgAN, ANCA, post-infectious, trauma, stones, malignancy |
| Blood + NO RBCs on microscopy | Hemoglobinuria (free Hb) | Intravascular hemolysis (malaria, PNH, severe burns) |
| Blood + NO RBCs + dark urine | Myoglobinuria | Rhabdomyolysis, severe myositis |
| Blood + lots of RBCs + casts | Glomerulonephritis | PSGN, IgAN, lupus, ANCA-associated |
The dipstick is exquisitely sensitive for blood (detects heme-containing compounds) but not specific (can detect Hb, myoglobin). Always confirm with microscopy. If blood 3+ but no RBCs on microscopy → think hemolysis or rhabdo.
5. Leukocyte Esterase (Negative or Positive)
| Result | Interpretation | Significance |
|---|---|---|
| Positive | WBCs present (from neutrophils) | UTI, pyelonephritis, acute interstitial nephritis, contamination |
| Negative | No WBCs or very few | A negative screen lowers suspicion for pyuria but does not exclude UTI or AIN; use symptoms, microscopy, culture when indicated, and the kidney-function trend |
Limitations: False negatives if immunosuppressed (unable to mount WBC response); false positives from contamination.
6. Nitrites (Negative or Positive)
| Result | Interpretation |
|---|---|
| Positive | Gram-negative bacteria (E. coli, Klebsiella, Proteus); highly specific for UTI |
| Negative | Gram-positive bacteria, anaerobes, Pseudomonas (all nitrite-negative); does NOT rule out UTI |
Pearl: Positive leukocyte esterase + positive nitrites = high likelihood of bacterial UTI (~95%). Negative nitrites does NOT exclude UTI.
7. Glucose (Dipstick: Negative–4+)
| Finding | Threshold | Significance |
|---|---|---|
| Negative | < 5 mg/dL | Normal (renal threshold ~180 mg/dL plasma) |
| Positive (any grade) | > 5 mg/dL | Plasma glucose > renal threshold (160–180) OR abnormal proximal tubular reabsorption (Fanconi, SGLT2i) |
Additional Dipstick Parameters
| Parameter | Normal | Pathologic | Interpretation |
|---|---|---|---|
| Ketones | Negative | Positive | DKA, starvation ketosis, high-fat diet |
| Bilirubin | Negative | Positive | Bilirubinuria (conjugated bilirubin in urine); suggests liver disease/biliary obstruction |
| Urobilinogen | Trace–0.1 mg/dL | Elevated | Hemolysis, liver disease; absent in biliary obstruction |
Part 2: Microscopy Interpretation
Specimen Preparation and Quality
- Fresh urine only (< 2 hours old ideally)
- Centrifuged: 5 mL at 1,500 rpm × 5 min
- Low power (LPF, 10×): 10–15 fields for casts, crystals, large structures
- High power (HPF, 40×): 5–10 fields for cells, bacteria, small crystals
Casts: The “Renal Cell Express”
Golden Rule: Finding ANY casts in urine = casts came from kidneys (not contamination)
Cast Types and Pathophysiology
| Cast Type | Composition | Clinical Significance | Associated Findings |
|---|---|---|---|
| Hyaline | Tamm-Horsfall (uromodulin) only | Normal if < 2–3/LPF; increased in dehydration, fever, exercise, acidosis | Often asymptomatic |
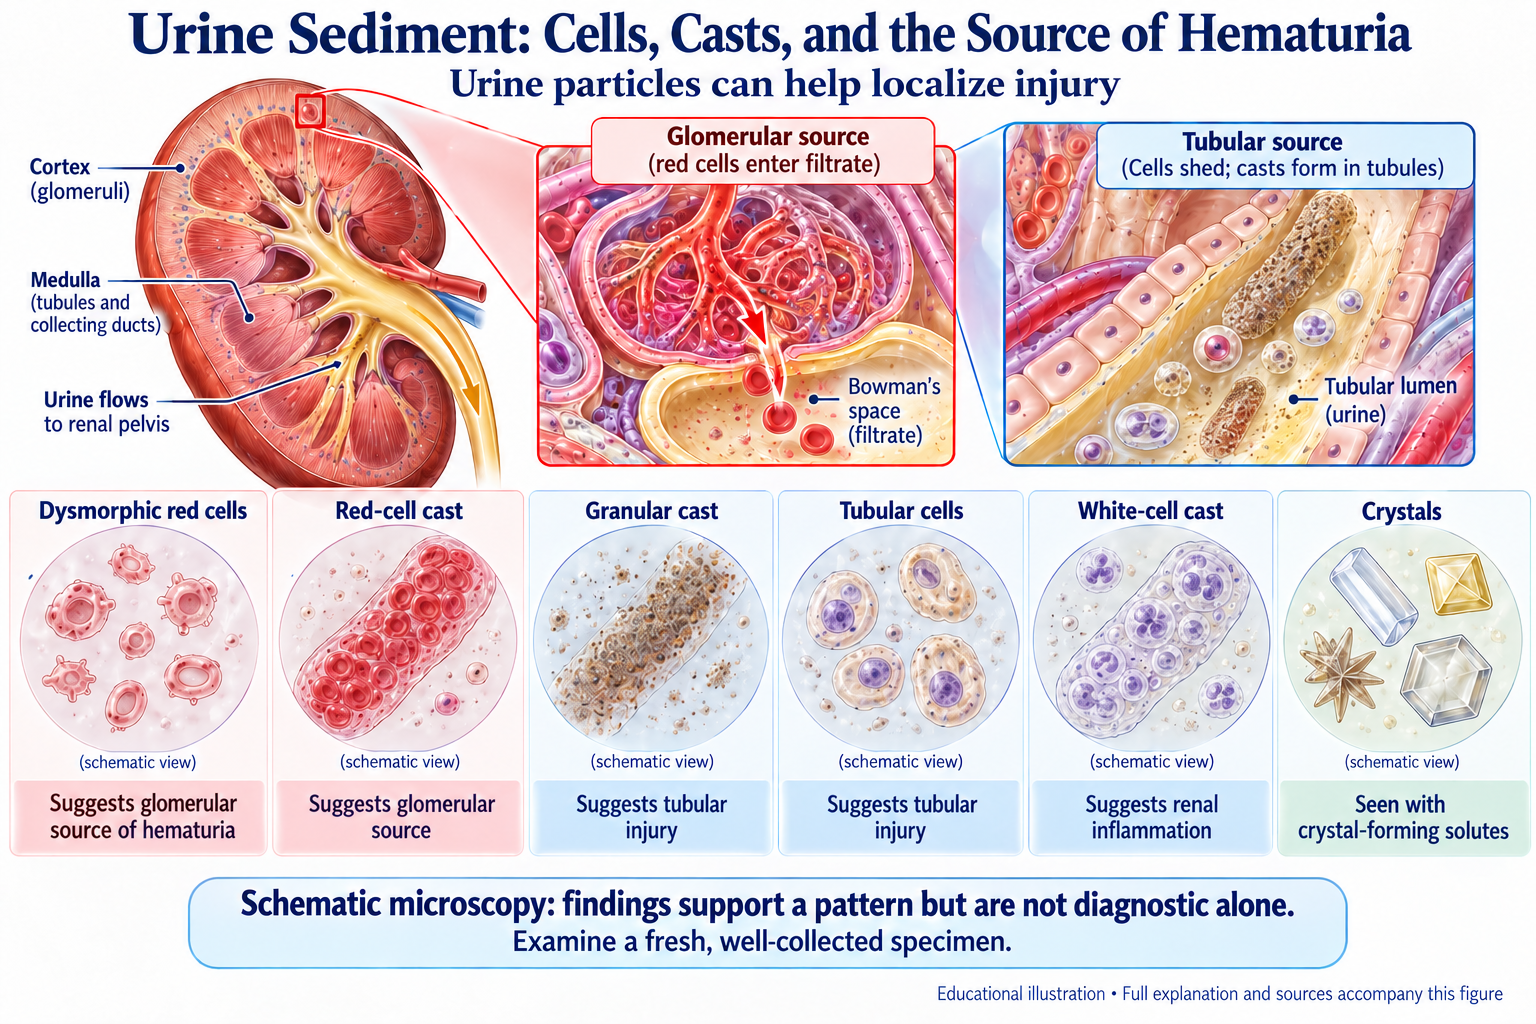
| RBC | RBCs trapped in matrix | ALWAYS pathologic; glomerulonephritis | Hematuria, proteinuria, dysmorphic RBCs, acanthocytes |
| WBC | WBCs in matrix | Pyelonephritis, acute interstitial nephritis, lupus | Pyuria, bacteriuria, systemic symptoms |
| Muddy Brown/Granular | Cellular debris, degenerated organelles | Acute tubular injury; muddy-brown casts strongly support this pattern | Acute rise in Cr, FeNa > 2%, muddy casts |
| Waxy/Broad | Uromodulin + proteinaceous material | Chronic kidney disease; indicates slowed urine flow/long tubular transit | Chronic Cr elevation, narrow casts also present |
| Fatty | Lipids, oval fat bodies (lipid-laden epithelial cells) | Nephrotic syndrome | Heavy proteinuria, hyperlipidemia, lipiduria |
| Crystalline | Specific crystal types (see table below) | Stone-forming tendency; Fanconi; toxic medication (sulfadiazine, ampicillin) | Acidic/alkaline pH, relevant medication history |
Cells and Cellular Elements
| Element | Normal | Pathologic | Interpretation |
|---|---|---|---|
| RBCs | 0–3/HPF | > 3/HPF = hematuria | Glomerular if dysmorphic/acanthocytes; non-glomerular if isomorphic |
| WBCs | 0–5/HPF (female); 0–2/HPF (male) | > 5/HPF = pyuria | UTI, pyelonephritis, AIN, lupus |
| Epithelial cells (renal tubular) | 0–1/HPF | > 2–3/HPF | Tubular injury (ATN, drug toxicity, reflux) |
| Epithelial cells (squamous) | Common (contamination) | Should be ignored if > 5–10/HPF | Vaginal/skin contamination; invalidates specimen |
| Bacteria | Absent | Present | UTI if symptomatic + nitrites/LE positive |
| Yeast | Absent | Rare | Vaginal candidiasis (female) or contamination |
| Trichomonads | Absent | Rare | Trichomoniasis (sexually transmitted) |
Dysmorphic RBCs (irregular shape, membrane protrusions) indicate glomerular origin; isomorphic RBCs (uniform, regular shapes) indicate non-glomerular hematuria (stones, tumors, trauma).
Crystals: Identifying Stone-Forming Tendency and Toxicity
| Crystal Type | pH | Associated Condition | Clinical Pearl |
|---|---|---|---|
| Calcium oxalate | Acidic | Hyperoxaluria, ethylene glycol toxicity | Envelope-shaped (diagnostic); elevated in ethylene glycol poisoning |
| Calcium phosphate/apatite | Alkaline | Normal variant, stone former | Appear as amorphous granules |
| Uric acid | Acidic | Gout, tumor lysis, dehydration | Rhomboid or needle-shaped; increase in acidosis |
| Struvite (magnesium ammonium phosphate) | Alkaline | UTI with urease producers (Proteus); chronic struvite stones | “Coffin-lid” shaped; always indicates infection |
| Cystine | Acidic | Cystinuria (inherited amino-acid transport disorder); cystine stones | Pathognomonic hexagonal shape; strongly suggests cystinuria |
| Sulfonamide/Sulfadiazine | Variable | Drug-induced nephropathy (TMP-SMX, sulfadiazine) | Needle-shaped; associated with fever, rash (AIN) |
| Bilirubin | Any | Hemolysis, liver disease | Rare; biliary obstruction prevents bilirubin excretion |
| Myoglobin/Hemoglobin | Any | Rhabdomyolysis, hemolysis | Dark (tea-colored) urine; associated with hypokalemia |
Bacteria and Organisms
| Organism | Morphology | Associated Condition |
|---|---|---|
| Bacteria (rods) | Gram-negative coccobacilli | E. coli, Klebsiella, Proteus (UTI) |
| Cocci | Clusters or pairs | Staphylococcus, Streptococcus |
| Trichomonads | Motile, flagellate | Trichomoniasis |
| Yeast | Budding forms | Candidiasis (especially with glycosuria) |
| Sperm | Motile (fresh specimen) | Semen contamination |
Part 3: Systematic Diagnostic Algorithm
The Five-Question Diagnostic Cascade
URINALYSIS INTERPRETATION FLOWCHART
│
├─ Question 1: Is there HEMATURIA (RBCs > 3/HPF)?
│  ├─ YES → Is there PROTEINURIA and CASTS?
│  │   ├─ YES → GLOMERULONEPHRITIS (See Differential Table)
│  │   │   └─ Pattern: Dysmorphic RBCs, RBC casts, proteinuria
│  │   │       Differential: IgAN, post-infectious GN, lupus, ANCA
│  │   │
│  │   └─ NO → NON-GLOMERULAR HEMATURIA
│  │       └─ Pattern: Isomorphic RBCs, NO casts, no proteinuria
│  │           Differential: Stones, malignancy, trauma, benign hematuria
│  │
│  └─ NO
│
├─ Question 2: Is there PROTEINURIA (dipstick positive)?
│  ├─ Nephrotic range (> 3.5 g/24h)
│  │   ├─ Pattern: Heavy proteinuria, oval fat bodies, fatty casts, hypoalbuminemia
│  │   │   Differential: Minimal change, FSGS, membranous, diabetic
│  │   │
│  └─ Non-nephrotic (< 3.5 g/24h) with/without RBCs
│      └─ Differential: IgAN, secondary GN, CKD, hypertensive
│
├─ Question 3: Is there PYURIA (WBCs > 5/HPF)?
│  ├─ + Leukocyte esterase + Nitrites → BACTERIAL UTI
│  ├─ + Leukocyte esterase – Nitrites → Viral UTI or Sterile Pyuria
│  │   └─ Sterile pyuria differential: Tuberculosis, AIN, glomerulonephritis
│  │
│  └─ – Leukocyte esterase → UTI/AIN not excluded; assess symptoms and microscopy
│
├─ Question 4: Are there CASTS?
│  ├─ RBC or WBC casts → INTRINSIC RENAL DISEASE
│  ├─ Muddy brown casts → ACUTE TUBULAR NECROSIS (ATN)
│  ├─ Waxy/broad casts → CHRONIC KIDNEY DISEASE
│  └─ Hyaline casts alone → Usually benign (if < 2/LPF)
│
└─ Question 5: Are there CRYSTALS or UNUSUAL ELEMENTS?
   ├─ Calcium oxalate → Stone former, ethylene glycol toxicity
   ├─ Cystine → Cystinosis (rare)
   ├─ Sulfonamide → Drug-induced AIN (TMP-SMX, sulfadiazine)
   └─ Myoglobin + dark urine → Rhabdomyolysis
Diagnostic Patterns by Clinical Scenario
Pattern 1: Acute Glomerulonephritis (AGN)
| Finding | Significance |
|---|---|
| RBC casts | Strongly suggests glomerular bleeding; not perfectly specific |
| Dysmorphic RBCs | Indicates glomerular damage |
| Proteinuria | Often 2–3+ (can be nephrotic; 5–10 g/day) |
| RBC count | Moderate to numerous |
| WBC casts or RBC casts | Variable |
| Hyaline casts | Often present |
Associated BMP findings: ↑ Cr, ↓ GFR, ↑ K (if severe oliguria), hypervolemia
Differential by serologies/clinical context: - Post-infectious GN: Young, recent infection (throat, skin), complement low - IgA nephropathy: Recurrent hematuria, IgA dominant on biopsy - ANCA-associated: Systemic symptoms, ANCA positive - Lupus: Systemic symptoms, ANA/anti-dsDNA positive
Pattern 2: Nephrotic Syndrome
| Finding | Significance |
|---|---|
| Heavy proteinuria | Confirm quantitatively: adult PCR approximately >3,500 mg/g or protein >3.5 g/day; a dipstick grade alone is insufficient |
| Oval fat bodies | Lipid-laden cells support lipiduria; interpret with quantified proteinuria |
| Fatty casts | Lipid-containing casts |
| No RBC casts | RBC casts suggest a nephritic component; their absence does not exclude glomerulonephritis |
| Hyaline casts | Often numerous |
| Minimal hematuria | < 5 RBCs/HPF (absent or trace blood) |
Associated findings: Hypoalbuminemia, hyperlipidemia, edema, heavy proteinuria on quantification
Differential: - Minimal change disease: Young, sudden onset, excellent prognosis - Focal segmental glomerulosclerosis (FSGS): Partially responsive to steroids; worse prognosis - Membranous nephropathy: Older, anti-PLA2R antibodies, insidious onset - Diabetic nephropathy: Long DM history, concurrent diabetic retinopathy, proteinuria without RBCs
Pattern 3: Acute Tubular Necrosis (ATN)
| Finding | Significance |
|---|---|
| Muddy brown/dark granular casts | Strongly supports acute tubular injury |
| Renal tubular epithelial (RTE) cells | From desquamated tubules |
| RTE cell casts | Desquamated cells in casts |
| Coarse granular casts | Debris from necrotic tubules |
| Minimal or absent RBCs | Unlike glomerular disease |
| Minimal proteinuria | < 1+ dipstick (< 500 mg/day) |
| High urine osmolality | Often > 400 (kidney trying to concentrate) |
Associated findings: Acute rise in Cr, oliguria, FeNa > 2%, “dirty” urine appearance
Causes: Ischemia (shock, sepsis), nephrotoxins (aminoglycosides, contrast, NSAIDs with volume depletion), rhabdomyolysis
Pattern 4: Pyelonephritis
| Finding | Significance |
|---|---|
| Pyuria | WBCs > 5/HPF, often numerous |
| WBC casts | Supports inflammation within the kidney; also occurs in AIN and some glomerular diseases |
| Bacteria | Rods (gram-negative) most common |
| Nitrites | Positive if gram-negative organism |
| Leukocyte esterase | Positive |
| Proteinuria | Usually trace–1+ (< 500 mg/day) |
| Hematuria | Trace to 1+ (microscopic) |
Associated findings: Fever, flank pain, CVA tenderness, elevated WBC, elevated CRP/ESR
Pattern 5: Acute Interstitial Nephritis (AIN)
| Finding | Significance |
|---|---|
| Sterile pyuria | WBCs without bacteria; LE positive, nitrites negative |
| WBC casts | If present, confirms renal involvement |
| RTE cells | Tubular epithelial shedding |
| Eosinophiluria | (Special stain: Hansel stain); suggests drug-induced |
| Proteinuria | Usually mild (trace–1+); nephrotic is unusual |
| Minimal hematuria | May be absent or trace |
| Normal or mildly elevated casts | Hyaline predominant |
Associated findings: Acute Cr rise (often > 50% increase), fever, rash (if drug), recent NSAID/antibiotic use
Causes: NSAIDs, β-lactams (PCN, cephalosporins), diuretics, PTIs (omeprazole), anticonvulsants
Pattern 6: Chronic Kidney Disease (CKD)
| Finding | Significance |
|---|---|
| Waxy/broad casts | Indicate slowed urine flow; advanced CKD |
| Granular casts | Fine or coarse; reflect chronic tubular atrophy |
| Mild proteinuria | Usually < 1+ (< 1 g/day), unless secondary cause |
| Minimal hematuria | Absent or trace; may be present in FSGS/IgAN |
| Minimal or absent RBC casts | Unlike active glomerulonephritis |
| Hypocellular sediment | Few cells overall |
Associated findings: Chronic Cr elevation, small kidneys on imaging, anemia (CKD-related)
Urine Electrolytes and Functional Indices
Urine Sodium (UNa) and Chloride (UCl)
| Finding | Interpretation | Clinical Significance |
|---|---|---|
| UNa < 10–20 mEq/L | Sodium avid | Pre-renal azotemia, hepatic encephalopathy, heart failure |
| UNa > 40 mEq/L | Sodium wasting | Intrinsic renal disease, diuretic use, advanced CKD |
| UCl < 20 mEq/L | Supports chloride-responsive alkalosis | Vomiting, NG suction (volume depletion) |
| UCl ≥ 20 mEq/L | Suggests chloride-resistant alkalosis or renal chloride loss | Mineralocorticoid excess, active diuretics, Bartter/Gitelman syndromes |
Interpret in context: In confirmed metabolic alkalosis, urine chloride below 20 mEq/L supports a chloride-responsive pattern; 20 mEq/L or above directs attention to renal chloride loss or a chloride-resistant pattern. This is a practical classification threshold, not an absolute diagnostic or treatment rule. Active or recent diuretics can raise urine chloride despite volume and chloride depletion; interpret sampling time, blood pressure, volume status, potassium, and treatment history, and repeat when needed. Urine electrolyte cutoffs are not diagnostic in stage 4–5 CKD. Give saline only when volume assessment supports it; a low result alone does not justify fluid in a congested patient. Sources: Core Curriculum 2022; Cervantes et al., 2022; Merck Manual: metabolic alkalosis.
Fractional Excretion of Sodium (FeNa)
$$FeNa = \frac{(UNa × Plasma Cr)}{(Plasma Na × Urine Cr)} × 100$$
| FeNa | Interpretation | AKI Type |
|---|---|---|
| < 1% | Sodium avid; intact tubular function | Pre-renal azotemia (volume depletion, shock, heart failure) |
| > 2% | Sodium wasting; tubular dysfunction | Intrinsic renal disease (ATN, GN, AIN, contrast nephropathy) |
| 1–2% | Gray zone; clinical judgment required | Early ATN or severe pre-renal |
FeNa < 1% in oliguria strongly suggests pre-renal; FeNa > 2% suggests intrinsic disease. However, FeNa can be falsely low in heart failure/cirrhosis and falsely high in elderly/CKD. Clinical context is paramount.
Urine Osmolality (Uosm)
| Uosm | Interpretation | Significance |
|---|---|---|
| > 500 mOsm/kg | Concentrated urine | Intact renal concentrating ability; pre-renal pattern |
| 250–500 mOsm/kg | Moderately concentrated | Intermediate; assess clinical context |
| < 300 mOsm/kg | Dilute urine | Loss of concentrating ability; intrinsic disease, DI, overhydration |
Urine Anion Gap (UAG) [2]
UAG = (UNa + UK) − UCl
| UAG | Interpretation | Differential |
|---|---|---|
| Negative (< 0) | GI bicarbonate loss | Diarrhea (especially small bowel) → appropriate renal acidification |
| Positive (> 0) | Renal tubular dysfunction | RTA (Type 1, 2, 4); reduced GFR; kidney cannot acidify urine |
Clinical use: Differentiates causes of non-gap metabolic acidosis
Board-Level Clinical Vignettes
Vignette 1: Hematuria with Casts
A 24-year-old male college athlete presents with dark urine for 2 days, beginning 2 weeks after streptococcal pharyngitis. Dipstick: 3+ blood, 2+ protein. Microscopy: Numerous dysmorphic RBCs, RBC casts, WBC casts, no bacteria.
Diagnosis: Post-infectious glomerulonephritis (PSGN)
Key findings: RBC casts (strongly suggest glomerular bleeding) + dysmorphic RBCs + proteinuria + recent infection
Next steps: Serologies (ASO titer, strep Ag), complement levels (C3 often low), renal ultrasound, possibly biopsy if atypical presentation
Prognosis: Excellent in children/young adults; most recover spontaneously; dialysis for refractory life-threatening fluid, electrolyte, or acid–base complications, not oliguria alone
Vignette 2: Heavy Proteinuria with Oval Fat Bodies
A 38-year-old woman with 2-week history of leg swelling and dark urine. Dipstick: 4+ protein. Microscopy: Numerous oval fat bodies, fatty casts, rare RBCs (< 1/HPF), no casts except fatty.
Diagnosis: Nephrotic syndrome
Likely etiology: Membranous nephropathy, minimal change disease, FSGS, diabetic kidney disease, and systemic causes. Distinguish these using history, serology, and appropriate biopsy; do not infer the diagnosis from race.
Supporting findings to order: - Serum albumin (expect < 3.5 g/dL) - Lipid panel (expect elevated cholesterol/triglycerides) - 24-hour urine protein (should be > 3.5 g) - Renal ultrasound (normal size does not exclude CKD; use prior eGFR, albuminuria, and chronicity) - Serologies: ANA, anti-PLA2R (membranous marker), hepatitis B/C, malignancy screening
Next: Kidney biopsy to establish diagnosis and prognosis
Vignette 3: Muddy Brown Casts in Oliguria
A 52-year-old male post-major surgery (day 1 post-op) with oliguria (urine output 200 mL/12h). Dipstick: Trace protein, trace blood. Microscopy: Numerous muddy brown granular casts, RTE cells, minimal RBCs, no bacteria.
Diagnosis: Acute tubular necrosis (ATN) — ischemic type
Mechanism: Perioperative hypotension + major surgical stress → ischemia to renal tubules
Evaluate with: Creatinine and urine-output trends, urine microscopy, hemodynamics, medication review, and assessment for obstruction. FeNa and urine osmolality may support the differential but do not confirm or exclude tubular injury.
Management: Assess perfusion and congestion first. Give isotonic crystalloid for documented hypovolemia with reassessment; avoid automatic fluid loading in oliguric or congested patients. Review nephrotoxins and medication dosing. Monitor potassium, acid–base status, urine output, and weight. Seek urgent nephrology support for refractory hyperkalemia, pulmonary edema, or severe acidosis. Recovery time varies; follow trends rather than promising recovery within a fixed number of days.
Reassess: Persistent or worsening AKI requires review for ongoing hemodynamic injury, obstruction, infection, medication effects, and alternative diagnoses; cast persistence alone does not establish prognosis.
Vignette 4: Sterile Pyuria Post-Antibiotic
A 68-year-old female post-TMP-SMX for UTI (started 2 weeks ago) presents with fever, rash, acute Cr rise from 1.0 to 2.1. Dipstick: 1+ protein, trace blood, LE positive, nitrites negative. Microscopy: WBCs 15/HPF (no bacteria), occasional RTE cells, hyaline casts, no RBC casts.
Diagnosis: Acute interstitial nephritis (AIN) — drug-induced (TMP-SMX)
Classic triad: Fever + rash + acute kidney injury post-drug exposure
Evaluate further: Review the medication timeline, creatinine trend, microscopy, and alternative causes. Urine eosinophils perform poorly and do not confirm or exclude AIN; absent RBC casts do not exclude GN. Ultrasound helps assess obstruction. Nephrology may recommend biopsy when diagnostic uncertainty affects treatment.
Management: 1. Immediately stop TMP-SMX (causative agent) 2. Supportive care, hydration 3. Corticosteroids if severe (prednisone 1 mg/kg/day × 3 days, taper over 2–4 weeks); benefit greatest if started early 4. Monitor Cr daily; most improve within 5–7 days after drug discontinuation 5. Avoid NSAIDs, ACE-I (further stress kidney)
Vignette 5: Cystine Crystals in Asymptomatic Adolescent
A 16-year-old male routine physical. Dipstick: Negative. Microscopy: Several pathognomonic hexagonal cystine crystals, otherwise negative findings.
Diagnosis: Cystinosis — autosomal recessive disorder of cystine transport
Significance: Cystine crystals = diagnostic for cystinosis; patient likely has progressive renal disease ahead
Next steps: 1. Check plasma cystine (elevated confirms cystinosis) 2. Slit-lamp examination for corneal cystine deposition 3. Referral to genetics and nephrology 4. Consider cysteamine therapy (chelating agent) to reduce intracellular cystine 5. Monitor for other manifestations: growth retardation, photophobia, hypothyroidism, ESRD by adolescence/early adulthood
Integration with BMP and Renal Function
Complete Picture: Urinalysis + BMP + Renal Function
| Clinical Scenario | UA Pattern | BMP Pattern | GFR/Cr | Diagnosis |
|---|---|---|---|---|
| Acute GN | RBC casts, dysmorphic RBCs, 2+ protein | Normal K initially; ↑ Cr if severe | Acute ↓ GFR | Post-infectious or primary GN |
| Nephrotic syndrome | Heavy proteinuria, oval fat bodies | ↓ Albumin, ↓ Ca, ↑ lipids | Normal–mildly ↓ | FSGS, membranous, minimal change |
| ATN (ischemic) | Muddy brown casts, RTE cells, trace protein | ↑ K, ↑ PO4, ↑ BUN/Cr ratio | Rapidly ↑ (doubling) | Post-shock, post-op, sepsis |
| Pre-renal azotemia | Concentrated urine, hyaline casts | Normal electrolytes, ↑ BUN/Cr ratio | Mildly ↑ | Volume depletion, heart failure, sepsis |
| AIN | Sterile pyuria, WBC casts, ±eosinophils | Normal electrolytes | Acute ↑ | Recent drug exposure |
| Chronic GN/CKD | Waxy casts, mild proteinuria | Chronic ↑ K, ↑ PO4, ↑ PTH (if severe) | Chronically ↓ | IgAN, FSGS, hypertensive, diabetic |
References
[1] Simerville JA, Maxted WC, Pahira JJ. “Urinalysis: a comprehensive review.” American Family Physician. 2005 Mar 15;71(6):1153-62. PubMed
[2] Fogazzi GB, Makarova E, Rampani L, et al. “Urinary microscopy as seen by nephrologists.” Clinical Chemistry and Laboratory Medicine. 1998 Dec;36(12):975-978. doi: 10.1515/cclm.1998.172 PubMed
[3] Perazella MA. “The diagnostic utility of urinary sediment examination in acute kidney injury: a brief review.” Clinical Journal of the American Society of Nephrology. 2008 Nov;3(6):1615-1619. doi: 10.2215/CJN.04640808 PubMed
[4] Berend K, de Vries AP, Gans RO. “Physiological approach to assessment of acid-base disturbances.” New England Journal of Medicine. 2014 Sep 4;371(10):932-943. doi: 10.1056/NEJMra1003327 PubMed