Visual reference
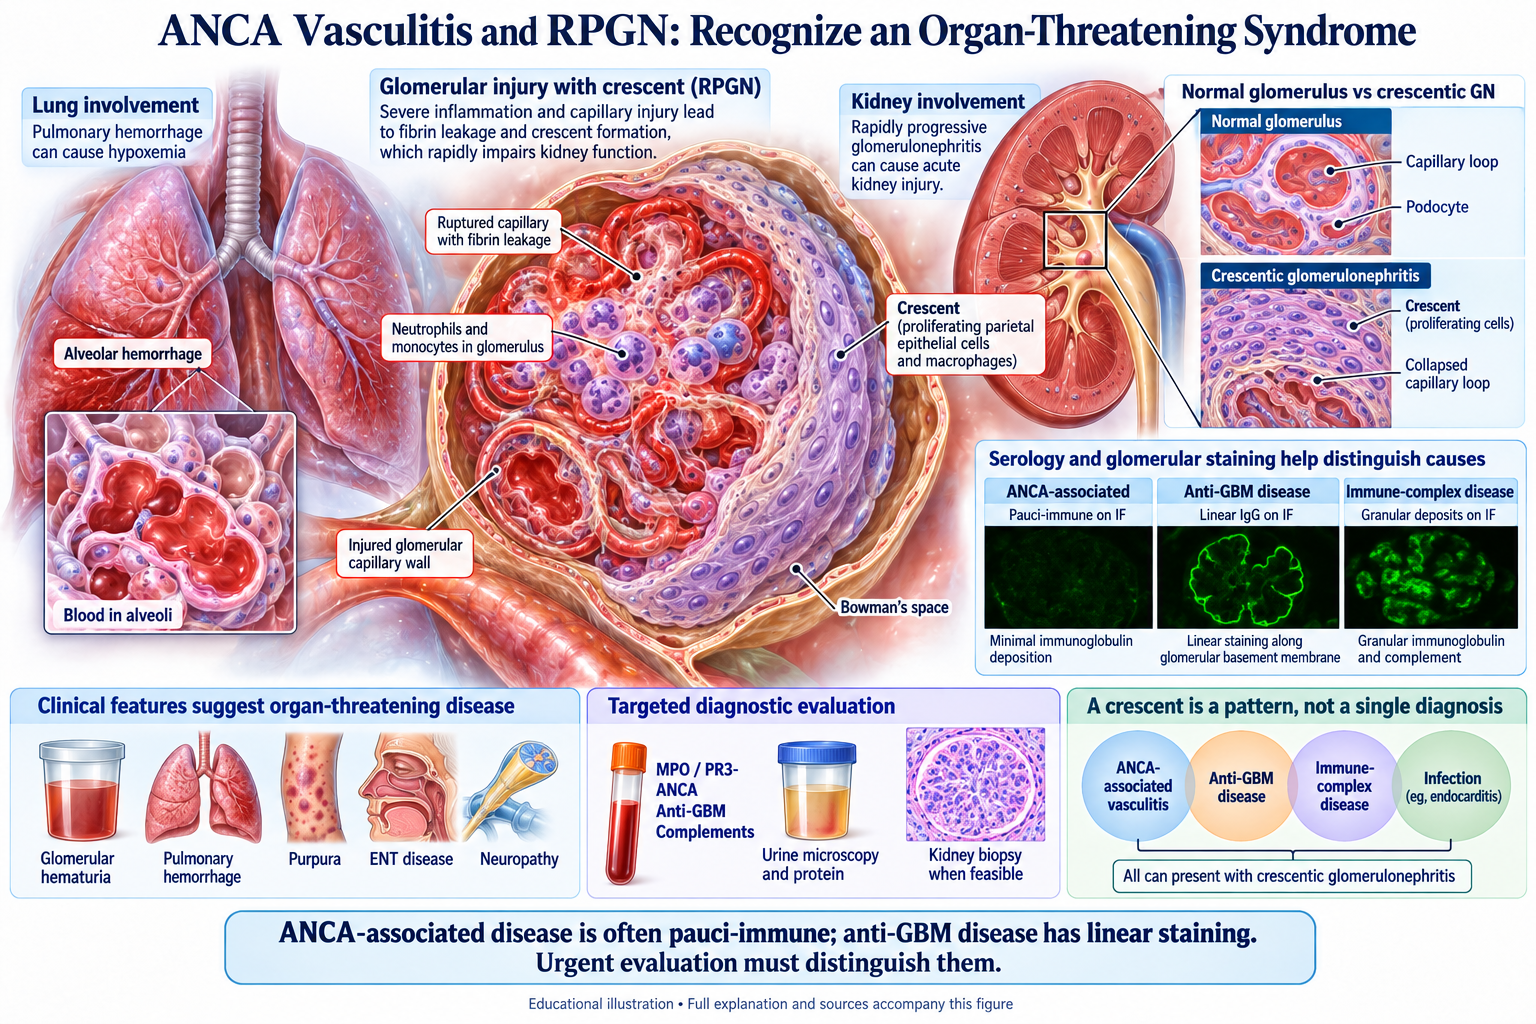
Browse the visual reference library · Download lesson Markdown
Classification: Three Phenotypes
ANCA-associated vasculitis (AAV) accounts for ~50% of pulmonary-renal syndrome cases. Three clinically and serologically distinct entities:
| Phenotype | ANCA Type | Associated Antigen | Prevalence | Key Features |
|---|---|---|---|---|
| GPA (Granulomatosis with Polyangiitis, formerly Wegener granulomatosis) | c-ANCA | Proteinase-3 (PR3) | 40-50% of AAV | Upper resp tract granulomas, pulmonary nodules, necrotizing GN |
| MPA (Microscopic Polyangiitis) | p-ANCA | Myeloperoxidase (MPO) | 40-50% of AAV | Pulmonary-renal syndrome, minimal extrapulmonary involvement, necrotizing GN |
| EGPA (Eosinophilic Granulomatosis with Polyangiitis, formerly Churg-Strauss) | p-ANCA (50%) | MPO or ANCA-negative | 10-15% of AAV | Asthma, eosinophilia, cardiac/GI involvement, later-onset vasculitis |
Serology-pathology mismatch: Don’t diagnose by serology alone. Biopsy remains gold standard. ~10% of confirmed AAV are ANCA-negative (especially EGPA).
Epidemiology & Presentation
Age & Demographics
- Peak incidence: 50-70 years old
- GPA: Slightly younger, more common in Whites
- MPA: Slightly older, no racial predominance
- EGPA: Most common in 40-50 year-olds
ANCA-Associated Vasculitis Clinical Spectrum
GPA (Granulomatosis with Polyangiitis) - Upper respiratory tract (90%): Sinusitis, nasal granulomas, saddle nose deformity - Lungs (85%): Nodules (often cavitary), infiltrates, hemoptysis - Kidneys (80%): RPGN, hematuria, RBC casts - Other: Eyes (scleritis), skin (palpable purpura), joints (arthritis), CNS (rare)
MPA (Microscopic Polyangiitis) - NO upper respiratory involvement (distinguishes from GPA) - Lungs (85%): Pulmonary hemorrhage (hemoptysis, pulmonary edema) - Kidneys (100%): RPGN (diagnostic hallmark) - Skin (40%): Palpable purpura, necrotizing vasculitis - GI (20%): Abdominal pain, bleeding - Systemic: Constitutional symptoms (fever, weight loss, arthralgia)
EGPA (Eosinophilic Granulomatosis with Polyangiitis) - Prodrome: Asthma (>90%), usually 5-10 years before vasculitis - Eosinophilia: Marked peripheral eosinophilia (>1.5 × 10⁹/L) diagnostic - Cardiac (50%): Myocarditis, pericarditis, heart failure - GI (60%): Abdominal pain, ischemia, perforation - Neuropathy (70%): Mononeuritis multiplex, distal symmetric polyneuropathy - Kidneys (40%): RPGN, but less severe than GPA/MPA; glomerulonephritis more pauci-immune
Pathophysiology: ANCA-Mediated Vascular Injury
The Four-Hit Model
Hit 1: Abnormal Neutrophil Priming - Genetic susceptibility genes (HLA-DPA1, HLA-DPB1, PR3, PRTN3 loci) - Environmental triggers (infections, drugs like hydralazine, propylthiouracil) - Neutrophils primed to express ANCA antigens on surface
Hit 2: ANCA Autoantibody Production - B cells produce anti-PR3 (c-ANCA, GPA) or anti-MPO (p-ANCA, MPA) - IgG1/IgG3 subclasses activate complement - Serum ANCA titer correlates with disease activity (especially PR3)
Hit 3: Neutrophil Activation & Degranulation - ANCA IgG crosslinks surface PR3/MPO → neutrophil activation - Fc receptor engagement amplifies activation - Neutrophil extracellular traps (NETs) release enzymes, exacerbating inflammation
Hit 4: Vascular Injury - Necrotizing vasculitis of small arteries, capillaries, venules - Direct endothelial injury from serine proteases (PR3, NE) - Complement activation (C5a, MAC), monocyte recruitment - Glomerular crescent formation if renal involvement
Diagnosis: Biopsy + ANCA Testing
ANCA Serology
c-ANCA (Cytoplasmic Pattern)
- Antigen: Proteinase-3 (PR3)
- Association: GPA (>90%), rarely MPA
- Method: Indirect immunofluorescence (staining pattern) + ELISA (antigen confirmation)
- Specificity: 95-99% if positive
- Sensitivity: 90% in generalized GPA; <50% in localized disease (confined to upper resp)
p-ANCA (Perinuclear Pattern)
- Antigen: Myeloperoxidase (MPO)
- Association: MPA (90%), EGPA (50%), vasculitis-associated GN
- Specificity: 95-99% if positive
- Sensitivity: 80% in MPA, 50% in EGPA
ANCA-Negative AAV
- ~10% of confirmed AAV cases (especially EGPA)
- Diagnosis: Clinical features + compatible pathology on biopsy
- Don’t exclude AAV if high suspicion and negative ANCA
Drug-induced ANCA vasculitis: Hydralazine, propylthiouracil (PTU), sulfasalazine, minocycline → MPO-ANCA vasculitis (typically p-ANCA). Discontinue drug; vasculitis usually resolves without immunosuppression over weeks-months.
Kidney Biopsy (Gold Standard for Renal Involvement)
Light Microscopy: - Segmental fibrinoid necrosis (crescent formation) - Necrosis of capillary wall without immune complex deposition - Crescent types: Cellular (early, reversible), fibrocellular (intermediate), fibrous (end-stage, irreversible) - Pauci-immune pattern (minimal immune complex)
Immunofluorescence: - Pauci-immune (minimal IgG, IgM, IgA, C3) - Hallmark of ANCA-GN - C3 may be present if secondary complement activation - Full-house IF rules OUT AAV, suggests lupus instead
Electron Microscopy: - Minimal electron-dense deposits (pauci-immune) - Rarefaction of capillary wall, fibrin material
Other Diagnostic Clues
| Test | Findings | Significance |
|---|---|---|
| CBC | Anemia (chronic disease), elevated WBC if active | Non-specific |
| CMP | Elevated Cr, AKI pattern | GN activity |
| UA | Hematuria, RBC casts, proteinuria | GN activity |
| Chest X-ray | Pulmonary nodules (GPA), infiltrates (MPA/EGPA), eosinophilic infiltrates (EGPA) | Often diagnostic for GPA |
| ESR/CRP | Markedly elevated | Indicates inflammation; high ESR predicts relapse |
| Complement | Normal (hallmark) | Helps distinguish from lupus (low complement) |
| Cryoglobulins | Negative | Distinguishes from mixed cryoglobulinemia |
ANCA-Associated GN Classification (Pathologic Findings)
| Class | % Glomeruli Sclerosed | % Glomeruli with Crescents | Prognosis | Treatment |
|---|---|---|---|---|
| Focal | <50% | <50% | Best | Standard induction |
| Crescentic | <50% | 50-75% | Intermediate | Aggressive induction |
| Sclerotic | >50% | Variable | Worst | Supportive care, no reversal expected |
Sclerotic ANCA-GN: If >80% of glomeruli sclerosed at biopsy, prognosis for renal recovery poor. Immunosuppression unlikely to help; focus on preventing further deterioration.
Treatment Algorithm
Remission Induction (3-6 Months)
Goal: Achieve complete remission (Cr stable, UA normalized, ANCA becoming negative or titer declining, no systemic symptoms).
Standard Induction: Rituximab Preferred (RAVE Trial)
RAVE Trial (2010): Rituximab non-inferior to cyclophosphamide for remission induction (64% vs. 53% at 6 months) and superior in relapsing disease (67% vs. 42%); adverse-event rates did not differ between arms, so rituximab is preferred chiefly to avoid cyclophosphamide gonadal and bladder toxicity [1]
Rituximab-based induction: - Rituximab: 1000 mg IV × 2 infusions 2 weeks apart (or 375 mg/m² weekly × 4 weeks) - Corticosteroids: IV methylprednisolone 1000 mg × 3 days (or 500-750 mg/day × 3 days), then prednisone 1 mg/kg daily (max 80 mg) taper over 3-6 months to 5-10 mg/day - Induction duration: 3-6 months to remission
Advantages: - Non-inferior to cyclophosphamide for remission induction (64% vs. 53% at 6 months in RAVE) [1] - Less infertility risk (especially in women) — avoids cyclophosphamide gonadal toxicity - Avoids cumulative cyclophosphamide dose limits and bladder toxicity (RAVE found no difference in overall adverse-event rates) [1] - Can repeat doses if relapse
Monitoring: - Monthly: CBC (CD19 cells should become undetectable), ANCA titer, Cr, UA - Assess for sterile pyuria, infections
Alternative Induction: Cyclophosphamide (If Rituximab Contraindicated)
NIH vs Euro-Lupus Dosing: - NIH: 500-1000 mg/m² IV monthly × 3-6 months - Euro-Lupus: 500 mg fixed dose IV monthly × 6 months (equivalent efficacy, lower cumulative toxicity)
Corticosteroids: Same as rituximab regimen above
Monitoring: Monthly CBC, Cr, UA; mesna prophylaxis (0.6 mg per mg CYC) for hemorrhagic cystitis
Complementary Therapy
Avacopan: Historical ADVOCATE Evidence Retracted
Historical study: ADVOCATE (2021) compared the C5a receptor inhibitor avacopan with a prednisone taper on background rituximab or cyclophosphamide [2]. The article was retracted in June 2026.
Evidence interpretation: Its originally reported remission, steroid-sparing, and comparative-safety findings must not be taught as established benefits. Use current regulatory advice and independently supported treatment options when planning induction therapy.
Current decision: Retraction of this article does not establish lack of benefit or resolve evidence from other studies. Avacopan use requires reassessment of independent evidence and current prescribing, regulatory, and guideline information. Read the retraction notice.
Remission Maintenance (≥18-24 Months)
Goal: Maintain remission on minimal immunosuppression to prevent relapse (50% risk without maintenance) while minimizing long-term toxicity.
Rituximab-Based Maintenance
- Fixed-schedule rituximab: 500 mg IV every 6 months (MAINRITSAN trials)
- Alternative: Rituximab doses based on B-cell recovery (CD19 reappearance)
- Duration: Minimum 18-24 months; some trials used ≥3 years
- Prednisone: Taper to 5-7.5 mg daily (continue indefinitely at low dose)
Azathioprine-Based Maintenance (Older Standard)
- Azathioprine: 1.5-2.5 mg/kg daily
- Prednisone: 5-10 mg daily
- Duration: ≥18-24 months (≥2 years preferred)
- Disadvantage: Higher relapse rates than rituximab
- Use if: Rituximab contraindicated or cost prohibitive
Maintenance Without Rituximab Infusions
- If CYC used for induction, switch to azathioprine or MMF for maintenance
Special Scenarios
ANCA-GN with Pulmonary Hemorrhage
- Immediate life threat: Hemoptysis + hypoxia
- Management:
- Urgent immunosuppression (induction as above)
- Consider plasma exchange (debate persists, but some benefit if Hb <7 or O₂ requirement high)
- High-dose IV methylprednisolone 1000 mg × 3-7 days
- Intubation if severe respiratory failure
- PEXIVAS Trial (2020): Plasma exchange vs. no plasma exchange on background immunosuppression — no significant difference in the primary outcome of death or ESKD (28.4% vs. 31.0%; HR 0.86, 95% CI 0.65–1.13), and results were similar across subgroups, so PEXIVAS does not support a benefit in fulminant presentations. The same trial found reduced-dose glucocorticoids non-inferior to standard-dose with fewer serious infections [3]
ANCA-Negative Pauci-Immune RPGN
- ~10% of pauci-immune RPGN are ANCA-negative
- Diagnosis: Clinical features + biopsy findings (pauci-immune crescents)
- Treatment: Same as ANCA+ RPGN
- Prognosis: Variable; some respond well, others more aggressive
Localized GPA (Upper Respiratory Only)
- No systemic/renal involvement at diagnosis
- ANCA: Often negative or low-titer c-ANCA
- Management: Observation or low-dose rituximab (rituximab 375 mg/m² × 4 weeks)
- Close follow-up: Monitor for systemic progression (monthly UA, Cr, ANCA)
- Risk of progression: 50% progress to generalized disease if untreated
Relapsing ANCA Vasculitis
- 40-50% relapse rate during or after maintenance therapy
- Predictors of relapse: PR3-ANCA (higher risk), persistent ANCA seropositivity, male sex
- Management:
- If on maintenance rituximab: Increase frequency (q 4 months vs. q 6 months)
- If on azathioprine: Switch to rituximab maintenance
- Assess adherence to medications
- Exclude infection, drug-induced vasculitis
Clinical Pearls & Pitfalls
ANCA-negative pauci-immune RPGN: Don’t miss these! 10-15% of confirmed AAV are ANCA-negative. Biopsy is diagnostic. Clinical features + pauci-immune crescents sufficient for diagnosis and treatment initiation.
PR3-ANCA vs. MPO-ANCA relapse risk: PR3-ANCA (GPA) patients have ~50% relapse risk; MPO-ANCA (MPA) have ~30% relapse risk. Higher relapse risk in PR3 justifies longer maintenance (2-3 years vs. 18 months).
Monitoring ANCA titers: Persistently positive or rising ANCA during remission predicts imminent relapse. However, negative ANCA doesn’t exclude relapse (15% of relapses are ANCA-negative). Monitor clinical features more than serology.
EGPA cardiac involvement: Myocarditis with reduced EF is ominous sign in EGPA. Requires intensive induction (CYC often preferred over rituximab if severe cardiac disease). Echocardiography baseline screening recommended.
Infection risk with rituximab induction: Opportunistic infections (PCP, CMV, listeria) can occur during B-cell depletion. Screen for TB; consider PCP prophylaxis (TMP-SMX) if CD4 <500. Monitor for symptoms closely.
Landmark Trials
[1] RAVE Trial (2010): Rituximab vs. cyclophosphamide for ANCA-associated vasculitis induction. NEJM. 2010;363(3):221–232. PMID: 20647199
[2] [RETRACTED — historical citation] Jayne DRW, Merkel PA, Schall TJ, Bekker P; ADVOCATE Study Group. Avacopan for the Treatment of ANCA-Associated Vasculitis. N Engl J Med. 2021;384:599–609. PMID 33596356. Retracted 29 June 2026: Rubin EJ, retraction notice; PMID 42377355.
[3] PEXIVAS Trial (2020): Plasma exchange and two glucocorticoid dosing regimens in severe ANCA-associated vasculitis (eGFR <50 mL/min/1.73 m² or diffuse pulmonary hemorrhage). NEJM. 2020;382(7):622–631. PMID: 32053298