Visual reference
Browse the visual reference library · Download lesson Markdown
Learning objectives
Explain why ammonia accumulates, recognize a neurological emergency, and compare rapid clearance with sustained control. Distinguish acute liver failure from chronic cirrhosis and explain why a single ammonia value is not a universal dialysis trigger.
Connect the physiology to the presentation
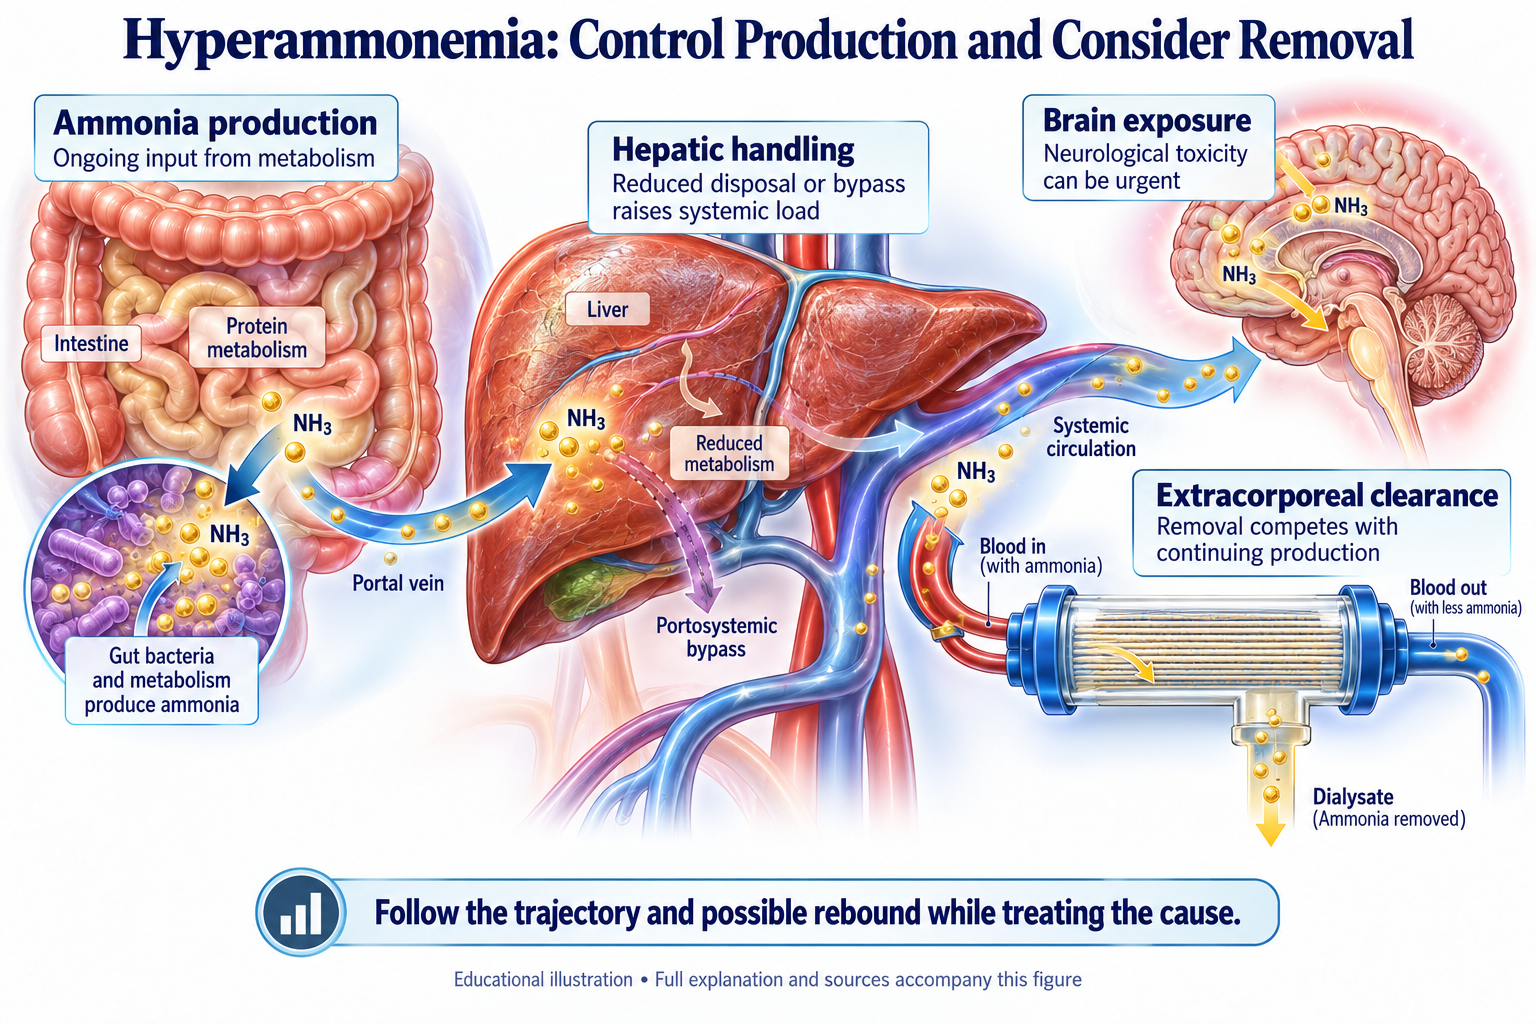
Ammonia is produced during nitrogen metabolism. The liver normally converts much of it to urea. Liver failure and portosystemic shunting can impair this handling. Ammonia reaching the brain promotes glutamine accumulation in astrocytes and contributes to swelling and altered neurotransmission. The severity and cause of illness matter alongside the measured concentration [1,4].
Look for altered behavior, confusion, reduced consciousness, seizures, or concern for cerebral edema. Evaluate other causes of altered mental status at the same time, including infection, hypoglycemia, medication effects, and intracranial disease. A patient can need urgent ammonia removal despite a normal creatinine [1].
First identify the clinical context
- Acute liver failure: encephalopathy and cerebral-edema risk require early critical-care and hepatology involvement, including transplant-center assessment when indicated.
- Chronic cirrhosis: manage precipitating factors and hepatic encephalopathy with the hepatology team. Isolated elevation of ammonia does not automatically create the same dialysis indication as acute liver failure.
- Nonhepatic causes: consider drugs, metabolic disease, or other cause-specific diagnoses. Neonatal and pediatric metabolic emergencies require their own specialist pathways.
Check sample handling, laboratory reference intervals, and units. Interpret serial results with the examination rather than applying an isolated cutoff across these different conditions [1,4].
Recognize when to escalate
Severe or rising ammonia with deteriorating consciousness, seizures, or suspected cerebral edema warrants urgent assessment by critical care, nephrology, and the relevant cause-specific team. Stabilization and cause-directed treatment proceed together. Do not wait for a universal threshold or for kidney failure to develop [1,4].
No single initiation value has been established for all adult causes of hyperammonemia. A concentration quoted in a liver-failure cohort is not a validated treatment threshold for every patient with cirrhosis. Treatment decisions incorporate trajectory, neurological status, hemodynamics, and available expertise [1,4].
Compare dialysis modalities
| Approach | Reason to consider it | What to watch |
|---|---|---|
| Intermittent hemodialysis | Rapid ammonia removal when tolerated | Hemodynamic or osmotic changes and rebound after stopping |
| Continuous kidney replacement therapy | Sustained removal; often favored with instability or cerebral-edema risk in acute liver failure | Delivered clearance, circuit downtime, electrolyte losses |
| Sequential or prolonged treatment | May combine initial removal with continued control | Individual specialist prescription; no universally superior sequence |
Ammonia is a small dialyzable solute, but clearance depends on the delivered prescription and ongoing production. A membrane name or high prescribed dose does not establish better survival. Continued production and redistribution can cause rebound after intermittent treatment [1,4,5].
Read the evidence accurately
- Cardoso et al.: a multicenter acute-liver-failure registry analysis associated CRRT with lower ammonia and better 21-day transplant-free survival. Association does not establish a causal survival benefit or one mandatory initiation threshold [2].
- Warrillow et al.: a retrospective single-center study described correction of hyperammonemia during early CRRT. It was not a randomized test of optimal timing, dose, or duration [3].
- Slack et al.: physiologic measurements show that hemofiltration removes ammonia. Solute clearance is a different outcome from neurological recovery or survival [5].
Use these data to understand treatment rationale and uncertainty. They do not support promises of a fixed mortality reduction or a universal dose for all patients.
Monitor the patient and the delivered treatment
Track neurological examination, serial ammonia, hemodynamics, fluid balance, electrolytes, and actual treatment delivery. Phosphate loss and medication clearance deserve attention during continuous therapy. Coordinate dose changes and treatment cessation with the team, and continue surveillance for rebound [4].
Dialysis supports ammonia removal. It does not replace treatment of the underlying disease, metabolic therapy when appropriate, or liver-transplant evaluation.
Apply the framework: a synthetic teaching case
An adult with acute liver failure becomes progressively less responsive as ammonia rises, despite initially preserved kidney function. The immediate concern is neurological deterioration and possible cerebral edema, not whether creatinine has crossed an AKI threshold.
Discuss the next steps
Escalate immediately to critical care, hepatology, and nephrology. Reassess airway and neurological status, verify the result and units, evaluate other reversible causes, and arrange cause-directed treatment and transplant-center input. The team weighs urgent extracorporeal removal, modality, stability, and cerebral-edema risk. Monitor response and rebound rather than treating the first numerical improvement as definitive recovery [1,4].
Self-check: Why might continuous control be valuable even if intermittent HD offers faster instantaneous clearance? Explain ongoing production, rebound, and tolerance. Why should an ammonia value from a stable patient with cirrhosis be interpreted differently? Explain the differing clinical context.
References
- Gupta S, Fenves AZ, Hootkins R. The Role of RRT in Hyperammonemic Patients. Clin J Am Soc Nephrol. 2016. PubMed PMID 27197910
- Cardoso FS, Gottfried M, Tujios S, et al. Continuous renal replacement therapy is associated with reduced serum ammonia levels and mortality in acute liver failure. Hepatology. 2018. PubMed PMID 28859230
- Warrillow S, Fisher C, Bellomo R. Correction and Control of Hyperammonemia in Acute Liver Failure: The Impact of Continuous Renal Replacement Timing, Intensity, and Duration. Crit Care Med. 2020. PubMed PMID 31939790
- Paine C, Pichler R. How We Treat Hyperammonemia in Acute Liver Failure. Clin J Am Soc Nephrol. 2024. PubMed PMID 37847521
- Slack AJ, Auzinger G, Willars C, et al. Ammonia clearance with haemofiltration in adults with liver disease. Liver Int. 2014. PubMed PMID 23786538