Hepatorenal Syndrome: A Student Handout for PA/Medical Students
Visual reference
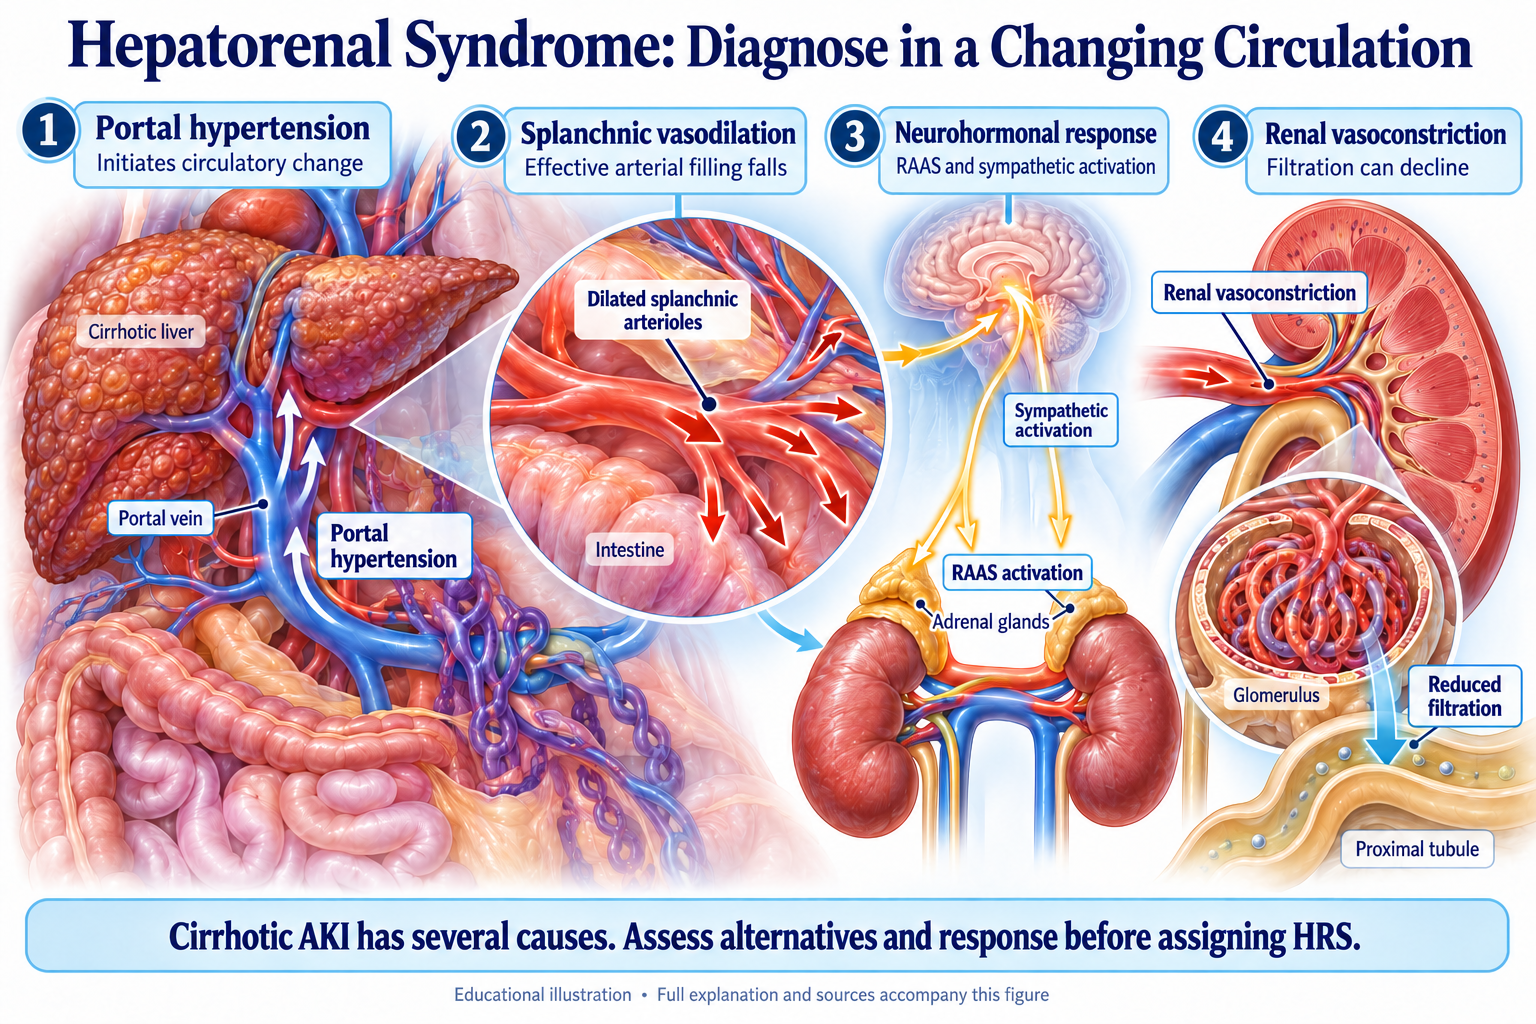
Browse the visual reference library · Download lesson Markdown
Learning Objectives
By the end of this session, you should be able to: 1. Define hepatorenal syndrome and its updated classification (HRS-AKI vs. HRS-non-AKI) 2. Explain the hemodynamic and inflammatory mechanisms linking portal hypertension to kidney dysfunction 3. Recognize HRS-AKI using current diagnostic criteria (without arbitrary creatinine thresholds) 4. Differentiate HRS from acute tubular necrosis (ATN) and other causes of AKI in cirrhotic patients 5. Discuss the role of vasoconstrictors (terlipressin + albumin) as first-line therapy 6. Interpret when dialysis is indicated and understand its limitations in HRS 7. Manage complications of dialysis in portal hypertensive patients (intradialytic hypotension, bleeding risk)
What Is Hepatorenal Syndrome?
HRS-AKI is a circulatory phenotype of AKI in cirrhosis with ascites. Renal vasoconstriction and systemic inflammation contribute; tubular injury, proteinuria, or pre-existing CKD can coexist. ADQI–ICA 2024 consensus.
Key Point
Assess alternative and coexisting causes of AKI promptly. HRS-AKI requires no stronger alternative explanation as the primary cause, but tubular injury or CKD may coexist; do not delay assessment by requiring every other kidney process to be absent.
Why This Matters for You
- HRS-AKI occurs in decompensated cirrhosis, with risk influenced by ascites, infection, circulatory dysfunction, and baseline kidney disease.
- HRS-AKI has high short-term mortality; prognosis depends on illness severity, response, and transplant eligibility.
- Early recognition and pharmacological intervention can save lives
- You will encounter HRS in ICU, hospital medicine, and nephrology rotation settings
- Understanding HRS is essential for managing complex patients with simultaneous liver and kidney failure
The Pathophysiology: How Portal Hypertension Breaks the Kidneys
Step 1: Portal Hypertension Creates Splanchnic Vasodilation
- Increased pressure in the portal system triggers vasodilation in the splanchnic vascular bed
- This occurs via endothelial nitric oxide (NO) activation and other vasodilatory factors
- Result: Blood pools in the splanchnic circulation → “effective hypovolemia” despite total body fluid overload
Step 2: The Body Tries to Compensate (But It Backfires)
To maintain blood pressure, your body activates: - RAAS (renin-angiotensin-aldosterone system) - Sympathetic nervous system - Vasopressin (antidiuretic hormone)
These normally help restore blood pressure by causing vasoconstriction. But in HRS, this compensation goes too far.
Step 3: Intense Renal Vasoconstriction Develops
- The renal arteries constrict severely
- Glomerular filtration rate (GFR) plummets
- Kidney function fails — structural injury may coexist
- This is why we call it “functional” kidney failure
Step 4: Inflammation Worsens It
Recent research shows that systemic inflammation in acute-on-chronic liver failure also contributes: - Dysregulated immune response → inflammatory cytokine release - Bacterial translocation from the gut - Epithelial dysfunction and vascular injury
Pathophysiology Summary
| Stage | What Happens | Result |
|---|---|---|
| Portal HTN | Splanchnic vasodilation | “Effective hypovolemia” |
| Compensation | RAAS + SNS activation | Renal vasoconstriction |
| Renal Failure | Intense vasoconstriction | GFR drops, serum creatinine rises |
| Inflammation | Cytokine cascade | Endothelial injury, worsens outcome |
Updated Classification: HRS-AKI and HRS-non-AKI
The International Club of Ascites (ICA) revised HRS nomenclature in 2021-2023. The old “Type 1” and “Type 2” terminology is outdated. Here’s the new framework:
HRS-AKI (Hepatorenal Syndrome-Acute Kidney Injury)
- Rapidly progressive kidney dysfunction
- AKI: serum creatinine increases ≥0.3 mg/dL within 48 hours, or ≥50% within 7 days, and/or urine output is ≤0.5 mL/kg/h for at least 6 hours.
- Prognosis is poor without reversal of the precipitating illness or definitive liver treatment; no single survival interval applies to all patients.
- Clinical urgency: Promptly assess for HRS-AKI and treat once diagnosed; verify oxygenation, ischemic risks, and volume status before vasoconstrictor therapy.
HRS-non-AKI (HRS-NAKI)
- Slower, progressive kidney dysfunction
- Includes both HRS-acute kidney disease (AKD) and HRS-chronic kidney disease (CKD)
- Develops over weeks to months
- Lower immediate mortality but requires management to prevent progression
Why the Change Matters
The new criteria eliminate the need for absolute creatinine thresholds, which is crucial because: - Many cirrhotic patients are malnourished (sarcopenia) → baseline creatinine is artificially low - A patient with baseline Cr 0.6 who rises to 1.0 has real kidney dysfunction but the old criteria might miss this - Dynamic creatinine changes catch more patients earlier
Diagnostic Approach
Clinical Suspicion
Use the ADQI–ICA 2024 framework: Cirrhosis with ascites; dynamic AKI by creatinine and/or urine output; no improvement within 24 hours after adequate resuscitation when indicated; and no stronger alternative explanation as the primary cause. Assess volume first—routine 48-hour albumin is not a prerequisite.
Essential Workup to Rule Out Other Causes
Assess these competing or coexisting causes and identify the primary driver of AKI:
| Alternative Diagnosis | How to Distinguish |
|---|---|
| Prerenal AKI | Assess losses, perfusion and response to indicated resuscitation; BUN:Cr and urine sodium are not definitive classifiers in cirrhosis. |
| ATN | Granular casts and tubular epithelial cells support tubular injury; low urine sodium/FeNa can still occur in cirrhosis and do not exclude injury. |
| Drug-induced (aminoglycosides, NSAIDs, ACE-I) | Review drug exposure and mechanism; CK/pigment evaluation when rhabdomyolysis is plausible. Urine eosinophils do not diagnose drug injury or rhabdomyolysis |
| Glomerulonephritis | Hematuria, RBC casts, proteinuria; elevated creatinine in context |
| Hepatic cirrhosis with structural kidney disease | Biopsy shows intrinsic GN; different clinical context |
Key Diagnostic Clue: The Urine Sodium
In HRS, the kidneys are avidly reabsorbing sodium due to RAAS activation: - Urine sodium typically <10 mEq/L (very low) - Fractional excretion of sodium (FENa) <0.1% (very low)
Low urine sodium or FeNa may occur across AKI phenotypes in cirrhosis. Urine indices cannot independently separate HRS from tubular injury; integrate sediment, exposures, perfusion, and response.
Clinical Features at Presentation
Symptoms
- Fatigue, weakness (from uremia)
- Nausea, anorexia
- Encephalopathy (confusion, asterixis) — from ammonia + uremia
- Abdominal distention (ascites)
- Dyspnea (from fluid overload, hepatopulmonary syndrome)
Physical Examination
- Stigmata of cirrhosis: Spider telangiectasias, palmar erythema, jaundice, caput medusae
- Signs of portal hypertension: Ascites, splenomegaly, dilated veins
- Volume status: Ascites can coexist with low effective arterial volume; distinguish true depletion from congestion before giving fluid.
- Encephalopathy: Altered mental status, tremor, asterixis
Laboratory Findings
| Test | Typical Finding | Interpretation |
|---|---|---|
| Serum Creatinine | Rising (50%+ increase) | Evidence of AKI |
| BUN | Elevated | Nonspecific; integrate dynamic creatinine and urine-output criteria |
| Urinalysis | Minimal proteinuria; no casts | A bland sample may fit HRS; structural disease can coexist |
| Urine Na+ | <10 mEq/L (very low) | Intact tubular reabsorption |
| FENa | <0.1% | Low FeNa is a contextual clue; it does not exclude structural injury |
| Albumin | Low (<2.5 g/dL) | Hepatic synthetic dysfunction |
| INR/PT | Prolonged | Liver failure |
| Bilirubin | Elevated | Liver failure |
| Platelets | Low (<100) | Bone marrow suppression, splenic sequestration |
Management: The Stepwise Approach
Step 1: Promptly Assess Alternatives and Volume Response
- Correct documented hypovolemia with reassessment; avoid automatic albumin/fluid loading when euvolemic or congested.
- Stop nephrotoxic drugs (NSAIDs, ACE inhibitors, aminoglycosides)
- Assess for active infection (SBP, UTI, pneumonia) and treat
- Correct electrolyte abnormalities
Step 2: First-Line Pharmacological Therapy
Terlipressin + Albumin is the gold standard for HRS-AKI.
Terlipressin
- Mechanism: Vasopressin-receptor agonism, especially splanchnic vasoconstriction, can improve effective arterial volume and renal perfusion.
- US dosing: Start terlipressin 0.85 mg IV every 6 hours on days 1–3; reassess on day 4 and adjust or stop using the product-label creatinine algorithm. Check the formulation:0.85 mg terlipressin corresponds to 1 mg terlipressin acetate.
- Regulatory history: Initial US approval was in 2022 for adults with HRS and rapid reduction in kidney function.
- Duration: Follow response and safety stop criteria. US labeling continues until 24 hours after two consecutive creatinine values≤1.5 mg/dL at least 2 hours apart, or a maximum 14 days; lack of response or toxicity can require earlier discontinuation.
- Major safety risks: Serious or fatal respiratory failure and ischemia. Assess oxygenation/volume before treatment, monitor continuously, and do not initiate with hypoxia or worsening respiratory symptoms; stop if SpO₂ falls below 90%. Ongoing coronary, peripheral or mesenteric ischemia is a contraindication.
Albumin
- Albumin: Individualize to resuscitation need and daily volume assessment; do not automatically load a congested patient. During vasoconstrictor treatment,20–40 g/day of concentrated albumin is commonly used with adjustment/withholding for overload or pulmonary edema.
- Mechanism: Expands effective intravascular volume, improves renal perfusion pressure
- Rationale: Albumin + vasoconstrictor is superior to either agent alone
Combination Therapy Outcomes
Terlipressin plus albumin improved verified HRS reversal in CONFIRM, but that does not establish a survival benefit. Respiratory harm must be weighed against kidney response; liver transplant assessment remains essential. CONFIRM.
Step 3: When to Add Dialysis
Kidney replacement therapy is based on refractory hyperkalemia, severe acidemia, pulmonary edema, uremic complications, and the overall trajectory. Lack of terlipressin response after a fixed number of days or the presence of tubular injury alone is not an automatic dialysis indication. Discuss potential bridging to transplant, reversibility, burden, and patient goals.
Step 4: Managing Dialysis Complications in Portal Hypertension
Portal hypertensive patients are at high risk for problems during dialysis:
Intradialytic Hypotension (IDH)
- Definition: Systolic BP drop ≥20 mmHg OR MAP drop ≥10 mmHg requiring intervention
- Incidence in CKD: 10-12%
- Incidence in cirrhotic patients: Much higher (splanchnic pooling, autonomic dysfunction)
Prevention strategies: - Smaller fluid removal per session (ultra-gradual dry-weight achievement) - Minimal anticoagulation or regional anticoagulation (citrate) — reduce bleeding risk - Cool dialysate (35-36°C) to improve hemodynamic stability - Avoid large meals before dialysis - Monitor continuously; be ready to adjust ultrafiltration rate mid-session
Variceal Bleeding Risk
- Problem: Dialysis causes hemodynamic fluctuations → risk of variceal rupture
- Contributing factors: Required anticoagulation, rebound hypertension post-dialysis
- Management:
- Variceal prevention is individualized by hepatology. In ascites with persistently low BP or HRS-AKI, nonselective beta-blockers may need reduction/temporary discontinuation; do not add them automatically during unstable HRS.
- Careful anticoagulation protocol (minimal heparin, or none)
- Endoscopic variceal ligation if varices present
- Close monitoring for signs of bleeding
Key Clinical Pearls
Creatinine is a poor marker in cirrhosis — muscle wasting means baseline is falsely low. Trust the change in creatinine, not the absolute value.
HRS-AKI has high mortality. Level of care and prognosis depend on hemodynamic/respiratory instability, liver disease severity and organ support needs; the syndrome does not by itself assign a fixed 1-year mortality or require ICU care in every case.
Terlipressin requires a safety screen — US approval was in 2022. Start an eligible HRS-AKI treatment plan promptly after diagnosis, while monitoring oxygenation, ischemia and congestion.
Dialysis is rarely “curative” for HRS — it’s a bridge therapy. A low recovery rate reported in a maintenance-dialysis cohort is not an individual acute-HRS prediction. Assess reversibility and transplant candidacy rather than applying that percentage to every patient.
Infection is a major trigger — Many HRS cases are precipitated by spontaneous bacterial peritonitis (SBP), UTI, or pneumonia. Always look for and treat infections aggressively.
During HRS therapy: Albumin accompanies vasoactive treatment when appropriate, but dose is adjusted to volume status and withheld with fluid overload or pulmonary edema; monitor oxygenation and perfusion.
Choose kidney support deliberately. Hemodynamic instability can favor continuous therapy when available; modality, ultrafiltration and anticoagulation require an individualized plan. Peritoneal dialysis is not an automatic substitute in acute HRS.
Early recognition saves lives — The new diagnostic criteria (dynamic Cr changes) catch patients earlier than the old “Type 1/Type 2” system. Don’t wait for creatinine to reach 2.0+.
Practice Questions
Question 1: Case Presentation
A 58-year-old man with biopsy-proven cirrhosis (Child-Pugh C) from alcoholic liver disease presents to the hospital with fever (38.5°C). His last creatinine 3 months ago was 0.7 mg/dL. Today it is 1.4 mg/dL. Urine output is 300 mL in the past 24 hours. Urine sodium is 8 mEq/L. Urinalysis shows no proteinuria or casts.
Which of the following is the best next step in management?
A. Start hemodialysis immediately B. Assess volume and infection; resuscitate only when indicated and evaluate for HRS-specific treatment C. Start furosemide to increase urine output D. Order a kidney biopsy to assess for glomerulonephritis
Answer: B, with a volume-guided assessment. Evaluate/treat infection and other AKI causes promptly. Reassess response to fluids only when resuscitation is indicated. Low urine sodium and absent casts do not establish HRS or exclude other lesions. Once HRS-AKI is diagnosed, coordinate vasoconstrictor/albumin treatment with repeated oxygenation and congestion checks.
Question 2: Mechanism Question
A cirrhotic patient develops HRS-AKI despite normal or low-normal systemic blood pressure. This paradoxical finding is best explained by:
A. Acute tubular necrosis from ischemia B. Splanchnic vasodilation causing “effective hypovolemia” triggering RAAS and intense renal vasoconstriction C. Direct toxic effect of ammonia on renal tubules D. Glomerulonephritis secondary to immune complex deposition
Answer: B. Splanchnic vasodilation and renal vasoconstriction can reduce filtration despite an apparently acceptable systemic BP. This mechanism can coexist with tubular or other structural injury; absent casts cannot prove a purely functional disorder.
Question 3: Drug Therapy Question
A 65-year-old woman with cirrhosis and HRS-AKI is receiving US-label terlipressin 0.85 mg IV every 6 hours. After 3 days, creatinine improves from 2.8 to 1.9 mg/dL without respiratory or ischemic complications. The team considers stopping solely because the creatinine is improving.
Is this appropriate?
A. Yes, discontinue terlipressin immediately since creatinine is improving B. No, reassess on day 4 and continue or adjust according to creatinine response and safety criteria C. Yes, switch to a beta-blocker for long-term renal protection D. No, the patient needs dialysis because creatinine is still >1.5
Answer: B. The creatinine reduction is greater than 30%; the US day 4 algorithm therefore continues 0.85 mg every 6 hours if treatment remains appropriate. Do not use a fixed 5–7-day rule. Apply the label response endpoint and maximum 14-day limit, and stop earlier for toxicity or other specified stopping criteria. Current label.
Summary Table: HRS at a Glance
| Concept | Key Point |
|---|---|
| Pathophysiology | Portal HTN → splanchnic vasodilation → “effective hypovolemia” → RAAS activation → renal vasoconstriction |
| Classification | HRS-AKI (rapidly progressive) vs. HRS-non-AKI (slower); no more “Type 1/Type 2” |
| Diagnosis | ADQI–ICA 2024 criteria: cirrhosis with ascites, dynamic AKI, no improvement within 24 hours after indicated resuscitation, and no stronger alternative primary cause; do not diagnose from FeNa alone |
| Prognosis | High mortality; prognosis depends on liver disease severity, kidney trajectory, treatment response, and transplant eligibility |
| First-line Rx | Terlipressin plus individualized albumin when eligible; monitor respiratory and ischemic risks |
| Dialysis Role | Bridging therapy, not primary treatment; used for refractory cases or complications |
| Dialysis Risks | Hemodynamic intolerance and bleeding risk require individualized ultrafiltration, monitoring and anticoagulation; no universal incidence applies |
| Prognosis with Tx | Terlipressin can improve HRS reversal but has important respiratory/ischemic risks; maintenance-dialysis recovery percentages do not predict every acute case |
See Also
Clinical Content (01-Clinical-Medicine/Nephrology & Hepatology)
- Hepatorenal Disease Hub
- Essential Renal Laboratory Tests
Butler-COM Resources
- Butler COM - Nephrology Deep Dive
References & Further Reading
- Tiwari N, Wong F. Hepatorenal syndrome: Updates. Clin Liver Dis (Hoboken). 2023;22(2):32-36. PubMed
- Kiani C, Zori AG. Recent advances in pathophysiology, diagnosis and management of hepatorenal syndrome: A review. World J Hepatol. 2023;15(6):741-754. PubMed
- Loftus M, Brown RS, El-Farra NS, et al. Improving the Management of Hepatorenal Syndrome-Acute Kidney Injury Using an Updated Guidance and a New Treatment Paradigm. Gastroenterol Hepatol (N Y). 2023;19(9):527-536. PubMed
- McAllister S, Lai JC, Copeland TP, et al. Renal Recovery and Mortality Risk among Patients with Hepatorenal Syndrome Receiving Chronic Maintenance Dialysis. Kidney360. 2021;2(5):819-827. PubMed
- Nadim MK, Kellum JA, Forni L, et al. Acute kidney injury in patients with cirrhosis: Acute Disease Quality Initiative (ADQI) and International Club of Ascites (ICA) joint multidisciplinary consensus meeting. J Hepatol. 2024;81(1):163-183. PubMed
- Kaplan DE, Ripoll C, Thiele M, et al. AASLD Practice Guidance on risk stratification and management of portal hypertension and varices in cirrhosis. Hepatology. 2024;79(5):1180-1211. PubMed
Created for PA/Medical Student Education in Nephrology. Last updated February 2026.