Drug Dosing in CKD Quick Reference
Visual reference
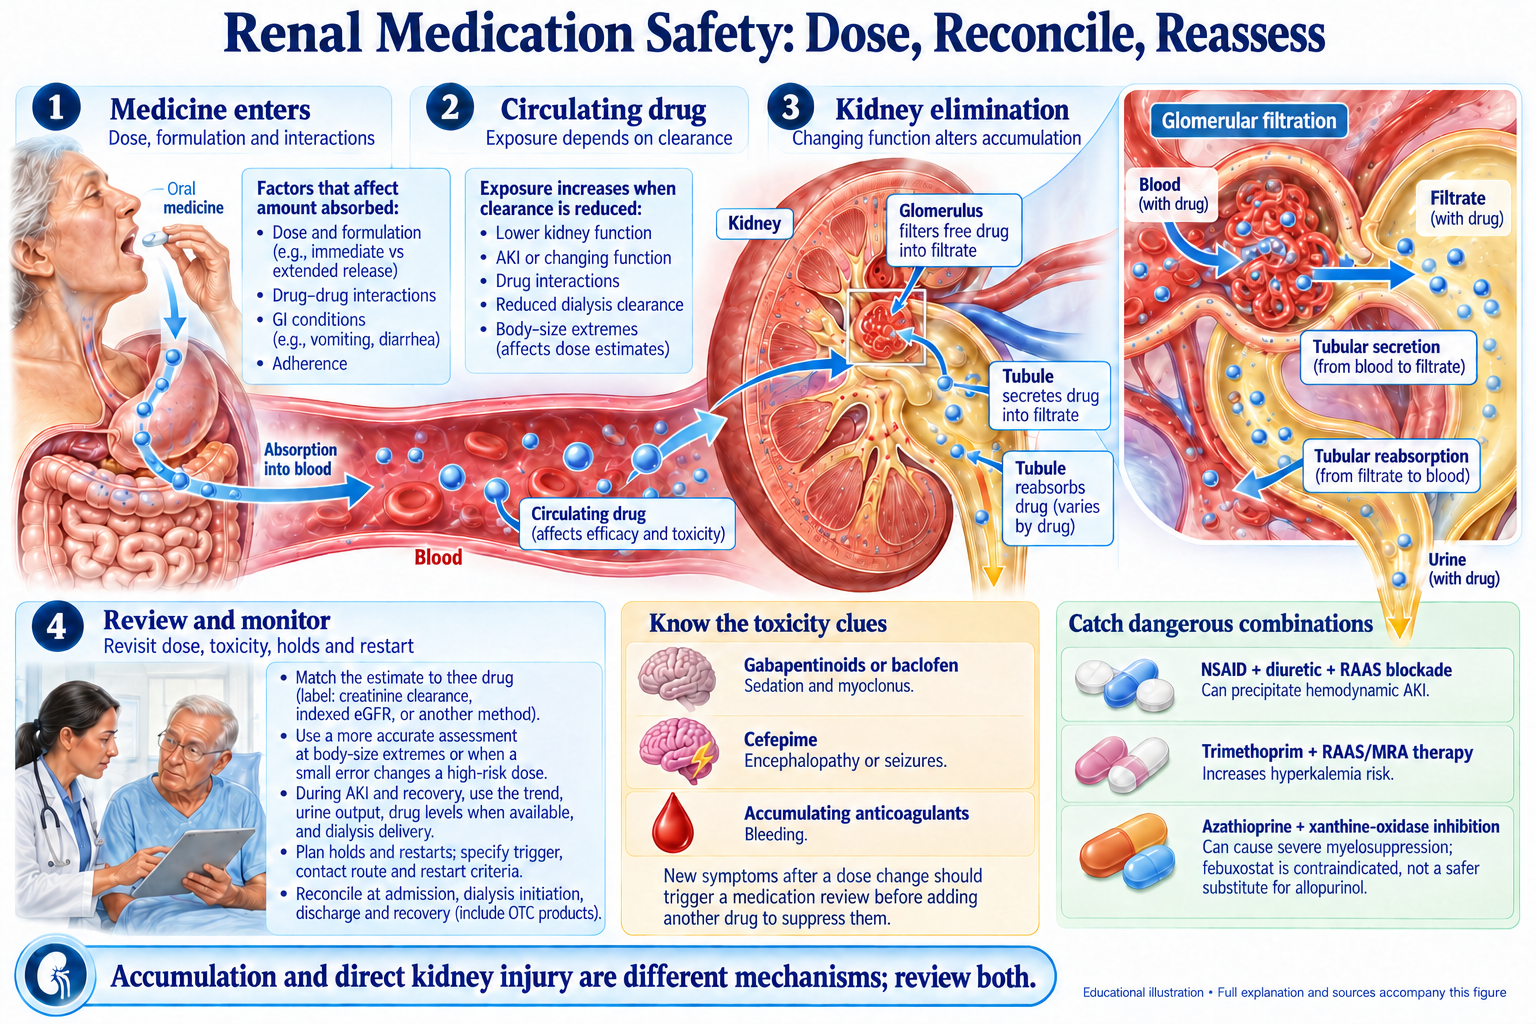
Browse the visual reference library · Download lesson Markdown
Overview
Drug dosing in chronic kidney disease requires systematic assessment of renal function (eGFR-based or creatinine clearance), understanding of drug metabolism/elimination, and knowledge of dialyzability [1]. This guide provides practical quick-reference tables for common medications requiring adjustment in CKD, organized by drug class and GFR stage. Principles, contraindications, and special considerations for dialysis dosing are included.
Key Clinical Pearl
“Estimated GFR-based dosing is standard for most drugs; however, actual creatinine clearance (CG equation or measured) may be more accurate for certain drugs (e.g., aminoglycosides, vancomycin). Always verify actual dose in individual patients; extrapolation from tables is a starting point, not absolute.”
Part 1: Principles of Drug Dosing in CKD
GFR Estimation Methods
Recommended by KDIGO for drug dosing:
MDRD Study Equation (4-variable): eGFR = 175 × (SCr)−1.154 × (Age)−0.203 × 0.742 (if female) × 1.212 (if Black)
- Kidney function for dosing: Use an appropriate contemporary race-free eGFR equation in adults and follow the equation/units used in the medication’s prescribing information. Near dose thresholds or when creatinine is unreliable, consider creatinine–cystatinC eGFR or measured clearance. Do not apply a race multiplier. 2021 CKD-EPI equations.
Cockcroft-Gault (Creatinine clearance estimation): $$\text{CCr (mL/min)} = \frac{(140-\text{Age}) \times \text{Weight (kg)} \times 0.85 \text{ (if female)}}{72 \times \text{SCr (mg/dL)}}$$
Choice of equation: Use a current race-free eGFR equation for kidney assessment and follow the kidney-function measure specified by the drug label or validated dosing protocol. Cockcroft–Gault estimates creatinine clearance; it does not measure actual clearance. Consider body size, non-steady-state creatinine, and drug-level monitoring, especially for aminoglycosides and vancomycin.
Dosing Adjustment Approaches
Two main strategies:
- Dose reduction: Decrease individual dose; maintain normal dosing interval
- Preferred for drugs with therapeutic index requiring steady levels
- Examples: Antimicrobials, cardiac glycosides
- Interval prolongation: Maintain normal dose; increase interval between doses
- Preferred for drugs where peak serum level important (beta-lactams, fluoroquinolones)
- Examples: Antibiotics
- Combination: Reduce both dose and interval (for severe renal failure)
Part 2: Antibiotics (GFR-Based Adjustment)
Beta-Lactams (Penicillins, Cephalosporins, Carbapenems)
| Agent | Normal Dose | eGFR >50 | eGFR 30–50 | eGFR 10–30 | eGFR <10 | Dialyzed |
|---|---|---|---|---|---|---|
| Penicillin G | 2–4 million units IV Q4-6h | No change | 2M Q6–8h | 2M Q8–12h | 1–2M Q12h | Yes (15–50%) |
| Ampicillin | 500 mg IV Q6h | No change | 500 mg Q6h | 250–500 mg Q6–12h | 250–500 mg Q12h | Yes |
| Ceftriaxone | 1–2 g IV Q12h | No change | No change | 1 g Q12–24h | 0.5–1 g Q24h | Minimal |
| Cefazolin | 1 g IV Q8h | No change | 0.5–1 g Q12h | 0.5 g Q12–24h | 0.25–0.5 g Q24h | Yes |
| Cefepime | 1 g IV Q12h | No change | 1 g Q12h | 0.5 g Q12–24h | 0.5 g Q24h | Yes |
| Meropenem | 0.5–1 g IV Q8h | No change | 0.5–1 g Q8–12h | 0.5 g Q12h | 0.25–0.5 g Q12h | Yes |
| Amoxicillin | 500 mg PO Q8h | No change | 250–500 mg Q8h | 250–500 mg Q12h | 250–500 mg Q24h | Yes |
Aminoglycosides (Nephrotoxic; Use with Caution)
Principle: Accumulates in renal cortex; dose-dependent nephrotoxicity. Use extended-interval dosing (more effective, less toxic).
| Agent | Extended-Interval Dose | Dosing Interval by eGFR |
|---|---|---|
| Gentamicin | 5–7 mg/kg IV | eGFR >50: Q24h; >20: Q36–48h; <20: Q48–72h or avoid |
| Tobramycin | 5–7 mg/kg IV | Same as gentamicin |
| Amikacin | 15 mg/kg IV | eGFR >50: Q24h; >20: Q36–48h; <20: Avoid or prolonged interval |
Monitoring: Serum levels required; trough <1 mg/L (gentamicin/tobramycin), <5 mg/L (amikacin); peak 15–30 mg/L (tobramycin).
Contraindication: eGFR <20 mL/min (alternative antibiotics preferred).
Vancomycin (Glycopeptide Antibiotic)
Principle: Kidney function, actual body weight, infection and measured concentrations guide an individualized regimen. Static eGFR tables are inadequate during changing kidney function.
Serious MRSA infection: The 2020 consensus guideline recommends AUC-guided monitoring, targeting AUC/MIC 400–600 when MIC is assumed to be 1 mg/L. Trough-only targeting of 15–20 μg/mL is no longer recommended for this indication because of nephrotoxicity concerns [2].
Timing: Assess target exposure early, ideally within 24–48 hours, using a validated pharmacy protocol. Do not automatically extrapolate the serious-MRSA target to every organism or infection.
Hemodialysis: Modern high-flux dialysis can remove vancomycin. Coordinate dosing, dialysis timing and concentration sampling with the local dialysis/pharmacy protocol.
Fluoroquinolones
| Agent | Normal Dose | eGFR 30–50 | eGFR <30 | Dialyzed |
|---|---|---|---|---|
| Ciprofloxacin | 500–750 mg PO/IV Q12h | 250–500 mg Q12–24h | 250 mg Q24h | Yes (minimal) |
| Levofloxacin | 500–750 mg daily | 250 mg daily or Q48h | 250 mg Q48h | Minimal |
| Moxifloxacin | 400 mg daily | No change | No change (but caution) | Minimal |
Note: Fluoroquinolones generally safe in renal failure; dose reduction for quinolone accumulation and CNS toxicity risk.
Macrolides
| Agent | Normal Dose | eGFR <30 | Note |
|---|---|---|---|
| Azithromycin | 500 mg PO daily | No change needed | Hepatic metabolism; minimal renal involvement |
| Clarithromycin | 500 mg PO Q12h | 250 mg PO Q12h | Renal elimination; dose reduce to avoid toxicity |
| Erythromycin | 500 mg PO Q6–8h | 250 mg Q6–8h | Hepatic; not eliminated by kidneys; caution with QT prolongation |
Part 3: Anticoagulants and Antiplatelet Drugs
Direct Oral Anticoagulants (DOACs)
Principle: Renal clearance varies by agent; eGFR thresholds critical for dose selection.
| Agent | Type | Dosing by eGFR | Contraindication |
|---|---|---|---|
| Apixaban | Fxa inhibitor | eGFR ≥30: 5 mg BID; eGFR 15–29: 5 mg BID (caution); <15: Avoid | eGFR <15 (ESRD) |
| Rivaroxaban | Fxa inhibitor | eGFR ≥30: 20 mg daily; eGFR 15–29: 15 mg daily; <15: Avoid | eGFR <15 (ESRD) |
| Dabigatran | Direct thrombin inhibitor | eGFR ≥30: 150 mg BID; eGFR <30: REDUCE or avoid | eGFR <15 (ESRD); significant renal clearance (~80%) |
| Edoxaban | Fxa inhibitor | eGFR ≥50: 60 mg daily; eGFR 30–50: 30 mg daily; <30: Caution | eGFR <15 (no data) |
Key point: DOACs removed by dialysis; redose AFTER dialysis session if timing convenient.
Warfarin
No renal adjustment needed (hepatic metabolism). However, CKD patients have enhanced INR sensitivity; monitor INR closely.
Antiplatelet Drugs
| Agent | eGFR <30 | Notes |
|---|---|---|
| Aspirin | No dosage change | Standard dosing; may accumulate metabolites |
| Clopidogrel (Plavix) | No dosage change | Standard dosing; metabolized hepatically |
| Prasugrel | Caution | Increased bleeding risk in CKD; use lower loading/maintenance dose if eGFR <30 |
| Ticagrelor | Caution | Monitor for bradycardia, blocks adenosine uptake; dosing unchanged but increased AE risk |
Part 4: Antihypertensives and Cardiac Drugs
ACE Inhibitors and Angiotensin Receptor Blockers
No dosage adjustment based on eGFR; however, monitor SCr and K carefully.
Caution thresholds: - Hold if Cr rise >30% from baseline within 4 weeks of initiation - Hold if K >6.0 mEq/L (hyperkalemia)
Beta-Blockers
| Agent | eGFR <30 | Normal Dose | Adjusted Dose |
|---|---|---|---|
| Metoprolol | Safe | 25–50 mg BID | 25 mg daily (start low) |
| Atenolol | Caution | 25–50 mg daily | 12.5–25 mg daily |
| Propranolol | Safe | 10–20 mg Q6–8h | No change (hepatic) |
| Carvedilol | Safe | 3.125–25 mg BID | No change (hepatic) |
Monitoring: Heart rate, blood pressure, fatigue, bradycardia in advanced CKD.
Calcium Channel Blockers
No significant renal adjustment (hepatically metabolized).
| Agent | eGFR <30 | Normal Dose | Note |
|---|---|---|---|
| Amlodipine | Safe | 2.5–10 mg daily | Hepatic metabolism; no dose change |
| Diltiazem | Safe | 120–240 mg daily | Hepatic; no change needed |
| Verapamil | Safe | 120–240 mg daily | Hepatic; caution with constipation in CKD |
Diuretics
| Agent | eGFR <30 | Dosing Adjustment |
|---|---|---|
| Furosemide | Decreased efficacy | Higher doses needed; eGFR <30 may need 40–80 mg BID to TID |
| Hydrochlorothiazide | Reduced efficacy | May add loop diuretic if eGFR <30 |
| Spironolactone | CAUTION | Higher hyperkalemia risk; eGFR <30 generally avoid; if use, monitor K closely Q2–4 weeks |
| Potassium-sparing (amiloride, triamterene) | AVOID | High hyperkalemia risk; contraindicated eGFR <30 |
Digoxin (Cardiac Glycoside)
Principle: Entirely renally eliminated; significant accumulation risk.
Dosing: - eGFR >50: 0.25–0.5 mg daily - eGFR 30–50: 0.25 mg daily or Q48h - eGFR 10–30: 0.125 mg daily or Q48h - eGFR <10: 0.125 mg Q48–72h or avoid
Monitoring: Serum digoxin level (target 0.5–1.5 ng/mL); toxicity more common in CKD due to hypokalemia and hypermagnesemia interactions.
Part 5: Antidiabetic Medications
Metformin
CONTRAINDICATION: eGFR <30 mL/min/1.73 m²
Rationale: Lactic acidosis risk from accumulation.
Dosing: - eGFR ≥60: Standard dosing (500–1000 mg BID–TID) - eGFR 45–60: Use standard dosing; monitor closely - eGFR 30–45: Reduce to 500 mg BID; caution - eGFR <30: CONTRAINDICATED; discontinue
Hold metformin in acute situations: Surgery, acute illness, contrast administration.
Sulfonylureas (Glyburide, Glipizide, Glimepiride)
Significant renal clearance; hypoglycemia risk in CKD.
| Agent | eGFR <30 | Normal Dose | Adjusted Dose |
|---|---|---|---|
| Glyburide | Caution | 5–10 mg daily–BID | Avoid; use alternatives |
| Glipizide | Safer | 5–10 mg daily–BID | 2.5–5 mg daily (metabolized hepatically) |
| Glimepiride | Caution | 1–4 mg daily | 0.5–1 mg daily; increase gradually |
Monitoring: Glucose monitoring; risk of hypoglycemia increases as eGFR declines.
GLP-1 Receptor Agonists
Generally safe; some dosing considerations:
| Agent | eGFR <30 | Normal Dose | Adjusted Dose |
|---|---|---|---|
| Liraglutide | Safe | 1.8 mg daily SQ | No change |
| Semaglutide | Safe | 1 mg weekly SQ | No change |
| Dulaglutide | Safe | 0.75–1.5 mg weekly SQ | No change |
| Exenatide | Caution | 10 μg BID or 2 mg weekly | eGFR <30: avoid immediate-release; use extended-release carefully |
SGLT2 Inhibitors
Safe in CKD; continue even as eGFR declines (per KDIGO 2024).
| Agent | eGFR <45 | eGFR <20 | Note |
|---|---|---|---|
| Dapagliflozin | 10 mg daily | Continue if eGFR ≥20 | No change; approved for eGFR ≥20 |
| Empagliflozin | 10 mg daily | Continue if eGFR ≥20 | No change; beneficial even at G5 |
| Canagliflozin | 100 mg daily | Caution; limit to 100 mg if eGFR <30 | No change but limit max dose |
DPP-4 Inhibitors
Generally safe; some renal clearance.
| Agent | eGFR <30 | Normal Dose | Adjusted Dose |
|---|---|---|---|
| Sitagliptin | Reduce dose | 100 mg daily | 50 mg daily (eGFR 30–50); 25 mg daily (eGFR <30) |
| Saxagliptin | Reduce dose | 5 mg daily | 2.5 mg daily if eGFR <50 |
| Linagliptin | Safe | 5 mg daily | No change (hepatic metabolism) |
| Alogliptin | Reduce dose | 25 mg daily | 12.5–25 mg daily if eGFR <30 |
Part 6: Analgesics and NSAIDs (CONTRAINDICATED in CKD)
NSAIDs (Nonsteroidal Anti-Inflammatory Drugs)
GENERAL CONTRAINDICATION: eGFR <60 mL/min/1.73 m² (especially <30)
Mechanism: Inhibit prostaglandin-mediated renal vasodilation; cause acute kidney injury; increase cardiovascular risk.
Absolute avoidance: eGFR <30, acute decompensation, polyuric renal disease, volume depletion.
Caution if used in eGFR 30–60: Shorter duration (<7 days preferred); adequate hydration; avoid in acute illness.
Safer alternatives: - Acetaminophen: Up to 3 g/day (eGFR >30) - Tramadol: 50–100 mg Q4–6h (reduce to 50–100 mg Q12h if eGFR <30) - Opioids: Morphine, hydromorphone (see below)
Opioid Analgesics (Dose by Renal Function)
| Agent | Normal Dose | eGFR 30–50 | eGFR <30 | Avoidance |
|---|---|---|---|---|
| Morphine | 10–30 mg PO Q4–6h | 50% dose reduction | 50% dose reduction + longer interval | Metabolite accumulation |
| Hydromorphone | 2–4 mg PO Q4–6h | 50% reduction | 50% reduction | M6G metabolite toxic |
| Codeine | 15–60 mg Q4–6h | Reduce 25–50% | Avoid (codeine-6-glucuronide accumulation) | Neurotoxicity risk |
| Tramadol | 50–100 mg Q4–6h | 50–100 mg Q12h | 50–100 mg Q24h or avoid | Seizure risk; accumulation |
| Fentanyl | Variable (patch, lozenge) | Safe (hepatic) | Safe (hepatic) | No renal adjustment |
| Oxycodone | 5–10 mg Q4–6h | 50% reduction | 50% reduction + longer interval | Noroxycodone accumulation |
Key principle: Opioid metabolites accumulate in renal failure; use long-acting opioids (fentanyl) or non-accumulating agents (hydromorphone with caution).
Part 7: Drugs to AVOID or Use with EXTREME CAUTION in CKD
Absolute Contraindications
| Drug | Reason | Threshold |
|---|---|---|
| Metformin | Lactic acidosis | eGFR <30 |
| NSAIDs | Acute kidney injury; GI bleed risk | eGFR <60 (avoid); <30 contraindicated |
| ACE-I/ARB in acute setting | Can precipitate acute renal failure | Use only if chronic HTN indication; monitor Cr closely |
| Potassium-sparing diuretics | Hyperkalemia | eGFR <30 |
| Lithium | Accumulates; neurotoxicity; kidney damage | eGFR <60 (avoid most); requires therapeutic drug monitoring |
| Gadolinium (contrast agent) | Nephrogenic systemic fibrosis (NSF) | eGFR <30 (use only if essential; avoid gadolinium-based) |
| Iodinated contrast agents | Contrast-induced nephropathy (CIN) | eGFR <30 (use iso/low-osmolar; hydrate; hold metformin) |
Relative Contraindications (Use with Caution)
| Drug | Reason | Adjustment |
|---|---|---|
| Aminoglycosides | Nephrotoxicity; ototoxicity | eGFR <20: avoid or extended-interval dosing |
| Vancomycin | Accumulation | Individualize dose; use indication-appropriate drug-level monitoring |
| NSAIDs (if eGFR 30–60) | Renal injury risk | Use lowest dose, shortest duration; ensure hydration |
| Codeine | Metabolite accumulation | Reduce dose or avoid eGFR <30 |
| Thiazolidinediones (pioglitazone) | Fluid retention; heart failure exacerbation | Use cautiously in advanced CKD; monitor for edema |
| Finasteride, dutasteride | Renal clearance; accumulation risk | eGFR <30: consider dose reduction |
Part 8: Dialysis-Specific Dosing
Hemodialysis (HD)
Principles: - Removed by HD: Small water-soluble molecules (urea, creatinine, small MW drugs) - NOT removed: Protein-bound drugs, large molecules, highly lipophilic agents - Timing: Dose AFTER HD if drug significantly removed
Peritoneal Dialysis (PD)
Generally: Less drug clearance than HD; similar dosing principles as nondialyzed CKD patients.
Specific Drug Adjustments for Dialysis
| Drug | HD Removal | Dosing Strategy | Timing |
|---|---|---|---|
| Gentamicin | Significant (70–90%) | Extended-interval dosing; usual dose Q36–48h | Dose after HD |
| Vancomycin | Minimal (<10%) | 10–15 mg/kg per HD session (NOT post-HD redose; allow level to drop 10–15 μg/mL/day) | Dose after HD or per serum level |
| Penicillins/cephalosporins | Significant | Standard dosing; Q8–12h dosing in nondialyzed; Q12–24h in HD | Dose after HD |
| Warfarin | Minimal | No change; monitor INR | Standard |
| DOAC | Variable (apixaban 25%, dabigatran 80%) | Standard dosing; redose after HD if timing convenient | Post-HD redose |
| Digoxin | Minimal | No change; maintain low level (avoid toxicity) | Standard |
| Metoprolol | Minimal | 25–50 mg post-HD | Post-HD |
| Acetaminophen | Significant | Standard dosing | Standard |
Part 9: Special Considerations
Contrast-Induced Nephropathy (CIN) Prevention
Risk factors: - eGFR <30 mL/min/1.73 m² - Diabetes - Volume depletion - Repeated contrast exposure
Contrast-associated AKI prevention: Assess kidney function, clinical indication, and volume status. IV isotonic saline prophylaxis is considered for patients with AKI or eGFR below 30 mL/min/1.73 m² who are not on maintenance dialysis, unless contraindicated; tailor the regimen to heart failure and fluid-overload risk. Avoid unnecessary nephrotoxins. Metformin management depends on kidney function, AKI, and the contrast procedure; it is not itself a nephrotoxin. N-acetylcysteine is not recommended for prophylaxis. Follow-up creatinine testing is individualized to risk. See the ACR–NKF consensus and PRESERVE trial.
Drug-Drug Interactions in CKD
Common problematic interactions:
| Combination | Problem | Management |
|---|---|---|
| ACE-I/ARB + NSAID + diuretic | “Triple whammy” → acute renal failure | Avoid; use SGLT2i instead of NSAID |
| ACE-I/ARB + potassium-sparing diuretic | Hyperkalemia | Monitor K; reduce diuretic dose |
| Digoxin + diuretics (loop, thiazide) | Hypokalemia → digoxin toxicity | Ensure K >3.5 mEq/L; add K-sparing diuretic |
| NSAIDs + ACE-I/ARB | Acute renal failure | Avoid; separate if possible; monitor Cr |
| Metformin + iodinated contrast | Lactic acidosis (contrast-induced AKI) | Hold metformin; restart 48 hours post-contrast if Cr normal |
Part 10: Key Warnings
Warning 1: Metformin Accumulation Lactic Acidosis
Metformin is cleared renally; at eGFR <30, accumulation increases lactate production and acidosis risk. Absolute contraindication: eGFR <30. Hold in acute illness, dehydration, sepsis, or before contrast administration.
Warning 2: NSAIDs Cause “Silent” Renal Failure
NSAIDs rarely cause obvious symptoms; patient may not realize declining renal function. Especially dangerous in elderly, diabetic, or volume-depleted patients. Educate patients to avoid OTC NSAIDs; recommend acetaminophen or tramadol.
Warning 3: Opioid Metabolite Neurotoxicity
Morphine-6-glucuronide, codeine-6-glucuronide, and other opioid metabolites accumulate in renal failure and cause sedation, confusion, myoclonus, and seizures. Prefer fentanyl (hepatically metabolized) or non-accumulating opioids in advanced CKD.
Warning 4: Hyperkalemia from Drug Combinations
ACE-I/ARB + SGLT2i + NSAIDs + potassium-sparing diuretics = dangerous hyperkalemia (K >6.0 mEq/L with arrythmias). Monitor K closely; educate on low-K diet; remove one agent if K trending up.
Warning 5: Vancomycin Dosing by Level, Not By eGFR
Vancomycin requires individualized therapeutic drug monitoring. For serious MRSA infection use the AUC-guided approach above. Dialysis patients need a regimen and sampling schedule matched to the dialysis modality and local pharmacy protocol.
References
Matzke GR, Aronoff GR, Atkinson AJ, et al. Drug dosing consideration in patients with acute and chronic kidney disease-a clinical update from Kidney Disease: Improving Global Outcomes (KDIGO). Kidney Int. 2011;80(11):1122. PubMed
[2] Rybak MJ, Le J, Lodise TP, et al. Therapeutic monitoring of vancomycin for serious methicillin-resistant Staphylococcus aureus infections: A revised consensus guideline and review by the American Society of Health-System Pharmacists, the Infectious Diseases Society of America, the Pediatric Infectious Diseases Society, and the Society of Infectious Diseases Pharmacists. Am J Health Syst Pharm. 2020. PubMed PMID 32191793
Ashley C, Dunleavy A. The Renal Drug Handbook. 5th ed. CRC Press; 2019. Publisher.
[4] Perazella MA, Rosner MH. Drug-Induced Acute Kidney Injury. Clin J Am Soc Nephrol. 2022. PubMed PMID 35273009
[5] Levey AS, Stevens LA, Schmid CH, et al. A new equation to estimate glomerular filtration rate. Ann Intern Med. 2009;150:604–612. PubMed
Last updated: 2026-02-28 Board-review quality curriculum for nephrology education.