Visual reference
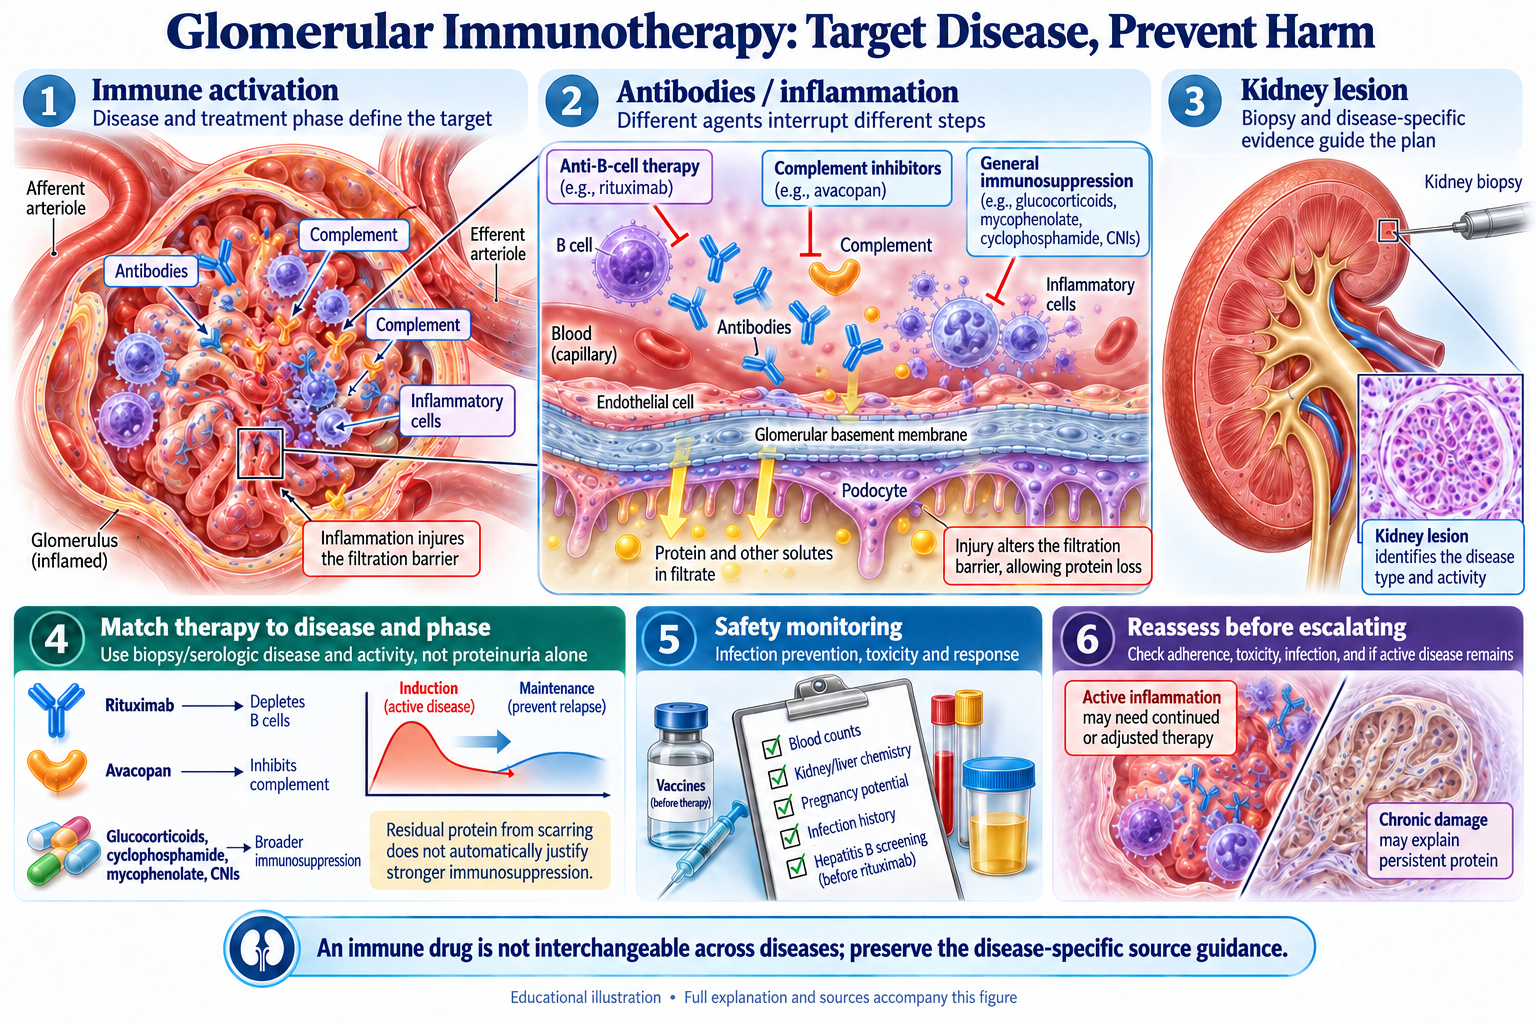
Browse the visual reference library · Download lesson Markdown
Start with the disease and treatment goal
Immunosuppression is selected for a defined kidney disease and disease phase. Induction controls active inflammation; maintenance reduces relapse after response. Biopsy findings, disease severity, chronic damage, prior treatment, infection risk, fertility, pregnancy plans, and patient priorities influence the regimen. A positive serology or isolated complement abnormality is not a universal indication for a particular drug [1–3].
For students, the essential task is to connect mechanism, indication, monitoring, and toxicity. Exact doses and combinations require the disease-specific guideline, current product information, and specialist supervision.
Glucocorticoids: effective but costly exposure
Glucocorticoids broadly suppress inflammation. They often form part of induction treatment, but the dose and taper differ across diseases and clinical severity. Monitor infection, glucose, blood pressure, mood, sleep, bone health, and cumulative exposure. A severe presentation does not make an arbitrary pulse dose or a prolonged high-dose course universally correct [1–3].
In severe ANCA-associated vasculitis, PEXIVAS supported a reduced oral glucocorticoid regimen for its studied outcomes, with fewer serious infections in the first year. Its findings do not mean that every patient can omit initial glucocorticoids or that plasma exchange has no role in any selected circumstance [6].
Cyclophosphamide: induction with toxicity planning
Cyclophosphamide is an alkylating immunosuppressant used in selected severe glomerular diseases. Toxicities include marrow suppression, infection, gonadal injury, and bladder toxicity. Assess blood counts, kidney function, cumulative exposure, fertility preservation, and protocol-specific preventive measures [1–3].
Euro-Lupus is a low-dose intravenous cyclophosphamide strategy studied in lupus nephritis. It must not be conflated with higher-dose monthly protocols or with the ALMS mycophenolate trials. Regimen choice depends on the clinical setting and the evidence for that population [2,7,8].
Mycophenolate: formulation and tolerance matter
Mycophenolic acid inhibits inosine monophosphate dehydrogenase and reduces lymphocyte proliferation. Mycophenolate mofetil and enteric-coated mycophenolate sodium are different formulations; they are not interchangeable milligram for milligram. Monitor blood counts, gastrointestinal symptoms, infections, and reproductive safety. These agents can cause embryo-fetal harm [1,2].
Severe diarrhea requires evaluation for infection, medication toxicity, dehydration, and other causes. Specialist-directed dose or formulation changes may be appropriate. Enteric-coated mycophenolate sodium is an oral formulation; it should not be described as an intravenous treatment for gastrointestinal intolerance. Do not assume that absence of fever excludes infection.
ALMS studied mycophenolate versus cyclophosphamide for lupus induction and mycophenolate versus azathioprine for maintenance. Results must be assigned to the correct phase of treatment; they do not establish mycophenolate as preferred maintenance for every glomerular disease [8,9].
B-cell therapy and maintenance
Rituximab depletes CD20-positive B cells and has established roles in ANCA-associated vasculitis and selected other glomerular diseases. Before treatment, assess hepatitis B status and infection risk, update appropriate vaccinations when feasible, and review immunoglobulins and prior infections. Monitor infusion reactions, infections, and hypogammaglobulinemia [1,3].
RAVE compared rituximab with a cyclophosphamide-based regimen for ANCA vasculitis induction; MAINRITSAN compared rituximab with azathioprine for maintenance. An induction result and a maintenance result answer different questions [4,5]. Azathioprine remains an option in selected maintenance settings, with blood-count and liver monitoring and attention to drug interactions.
Calcineurin inhibitors and targeted additions
Tacrolimus, cyclosporine, and voclosporin act through calcineurin inhibition. Clinical roles vary by disease. Monitor kidney function, blood pressure, potassium, and drug interactions; therapeutic drug monitoring applies where specified. A fall in proteinuria does not eliminate the need to monitor toxicity and sustained kidney response [1,2].
For active proliferative lupus nephritis, current guidance includes glucocorticoids with mycophenolic acid analogs or low-dose intravenous cyclophosphamide, with selected combination approaches involving belimumab or a calcineurin inhibitor. Choice depends on kidney function, disease features, and patient circumstances. Hydroxychloroquine and supportive kidney care also have important roles when appropriate [2].
Complement drugs are not interchangeable
Eculizumab inhibits C5 and has evidence in complement-mediated atypical hemolytic-uremic syndrome. It is not a routine substitute for ANCA-vasculitis induction solely because complement staining is present. Terminal complement inhibition carries serious meningococcal infection risk; vaccination, additional preventive measures, and urgent infection assessment follow current prescribing guidance [10].
Avacopan is a C5a-receptor antagonist (Tavneos), not a factor D inhibitor and not Fabhalta. The ADVOCATE publication is now retracted and its reported efficacy should not support current treatment claims [11,12]. On April 27, 2026, FDA proposed withdrawal of Tavneos approval; a proposal is distinct from a completed withdrawal. Consult the current FDA status notice and specialist guidance. Historical recommendations based on ADVOCATE need reassessment. Other avacopan evidence must be assessed separately.
Build a safety plan before the first dose
- Confirm the diagnosis, treatment phase, baseline blood counts, kidney and liver function, and relevant infection screening.
- Discuss pregnancy prevention, fertility, vaccinations, adherence, and access to treatment.
- Plan infection prophylaxis where indicated, including Pneumocystis prevention for appropriate regimens.
- Specify monitoring and escalation for fever, dyspnea, severe diarrhea, cytopenias, or worsening organ function.
- Distinguish disease activity from infection and drug toxicity before escalating immunosuppression.
Supportive treatment—blood pressure and proteinuria management, thrombosis assessment where appropriate, and avoidance of nephrotoxins—continues alongside disease-directed therapy [1–3].
Case discussion: identify the problem before changing therapy
Synthetic teaching case: A patient receiving mycophenolate for lupus nephritis develops persistent diarrhea and weight loss. The next step is a clinical reassessment for medication toxicity, infection, volume depletion, and other causes. It is not an automatic switch to “IV mycophenolate sodium” or empirical addition of another immunosuppressant.
Questions for discussion
Which monitoring results and exposure history would you obtain? How would you assess infection and dehydration? Which disease-response measures determine whether the problem is intolerance or treatment failure? Explain how a specialist might alter dose, formulation, or regimen while preserving disease control.
Selected evidence
- KDIGO Glomerular Diseases Work Group. KDIGO 2021 Clinical Practice Guideline for the Management of Glomerular Diseases. PubMed 34556256
- KDIGO Lupus Nephritis Work Group. KDIGO 2024 Clinical Practice Guideline for the management of Lupus Nephritis. PubMed 38182286
- KDIGO ANCA Vasculitis Work Group. KDIGO 2024 Clinical Practice Guideline for ANCA-Associated Vasculitis. PubMed 38388102
- Stone JH, et al. Rituximab versus cyclophosphamide for ANCA-associated vasculitis. 2010. PubMed 20647199
- Guillevin L, et al. Rituximab versus azathioprine for maintenance in ANCA-associated vasculitis. 2014. PubMed 25372085
- Walsh M, et al. Plasma Exchange and Glucocorticoids in Severe ANCA-Associated Vasculitis. 2020. PubMed 32053298
- Houssiau FA, et al. Immunosuppressive therapy in lupus nephritis: the Euro-Lupus Nephritis Trial. 2002. PubMed 12209517
- Appel GB, et al. Mycophenolate mofetil versus cyclophosphamide for induction treatment of lupus nephritis. 2009. PubMed 19369404
- Dooley MA, et al. Mycophenolate versus azathioprine as maintenance therapy for lupus nephritis. 2011. PubMed 22087680
- Legendre CM, et al. Terminal complement inhibitor eculizumab in atypical hemolytic-uremic syndrome. 2013. PubMed 23738544
- RETRACTED — historical reference only. Jayne DRW, et al. Avacopan for the Treatment of ANCA-Associated Vasculitis. 2021. PubMed 33596356
- Retraction notice for the ADVOCATE publication. 2026. PubMed 42377355