Nephrolithiasis: Pathophysiology, Diagnosis, and Medical Management
Visual reference
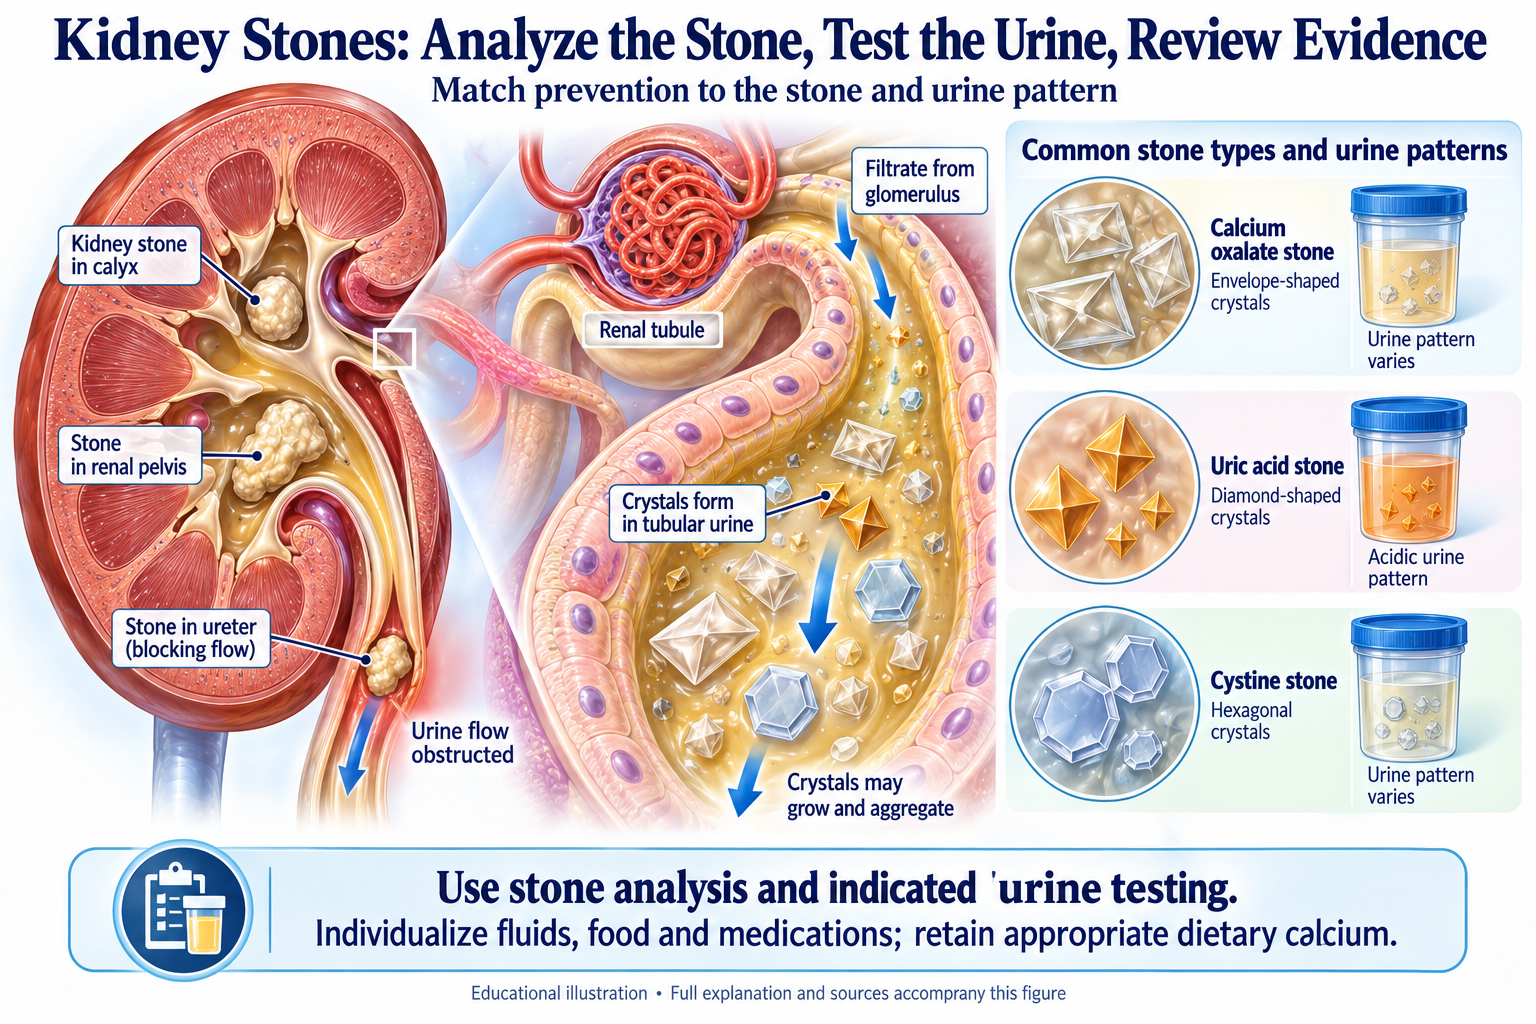
Browse the visual reference library · Download lesson Markdown
Learning Objectives
By the end of this session, students will be able to: - Identify stone types based on composition and clinical presentation - Understand pathophysiology of stone formation (supersaturation, inhibitors, promoters) - Diagnose nephrolithiasis using clinical history, imaging, and urinalysis - Manage acute stone episodes and provide appropriate analgesia - Apply medical therapy tailored to stone type and metabolic abnormalities - Implement dietary modifications and prevention strategies - Interpret 24-hour urine studies and guide metabolic stone evaluation - Recognize indications for surgical intervention (ESWL, ureteroscopy, PCNL)
I. Stone Types and Composition
Epidemiology and Prevalence
- Lifetime prevalence: 12% of men, 5% of women
- Peak incidence: 4th–5th decade; higher in males 3:1
- Recurrence rate: 50% within 5–10 years if untreated; 10–15% with prevention
Stone Type Distribution in USA
| Stone Type | Frequency | Radiopacity | pH Range | Peak Age |
|---|---|---|---|---|
| Calcium oxalate monohydrate | 35% | Very radiopaque | Acidic (5.0–6.5) | 40s–50s |
| Calcium oxalate dihydrate | 25% | Very radiopaque | Acidic (5.0–6.5) | 40s–50s |
| Calcium phosphate (apatite) | 10–15% | Radiopaque | Alkaline (>7.0) | 40s–50s |
| Struvite (magnesium ammonium phosphate) | 10–15% | Radiopaque | Alkaline (>7.0) | Females, post-infection |
| Uric acid | 5–10% | Radiolucent | Acidic (<5.5) | 50s–60s |
| Cystine | 1–2% | Radiopaque | Acidic–neutral (5.5–7.5) | Early adulthood (genetic) |
| Other (xanthine, ammonium urate) | <1% | Radiolucent–lucent | Variable | Rare |
Calcium Oxalate Stones (60% of all stones)
Subtypes: - Monohydrate (COM): Dumbbell-shaped, harder, more aggressive clinically - Dihydrate (COD): Envelope-shaped, less damaging, often asymptomatic
Associated conditions: - Hypercalciuria (high urine calcium >250 mg/day) - Hyperoxaluria (high urine oxalate >40 mg/day) - Hypocitraturia (low urine citrate <320 mg/day) - Dehydration and low urine volume - Obesity - High animal protein diet (↑ uric acid and oxalate)
Calcium Phosphate Stones (10–15%)
Subtypes: - Apatite (most common): Whitish, forms in alkaline urine - Brushite (calcium hydrogen phosphate): Rare, more soluble
Associated conditions: - Primary hyperparathyroidism (most important association—check PTH and serum Ca) - Renal tubular acidosis (Type 1, distal RTA) — alkaline urine + hypocitraturia - Medullary sponge kidney (ductal dilatation) - Sarcoidosis and granulomatous diseases (↑ calcitriol production) - Hyperthyroidism - Vitamin D intoxication
Clinical pearl: Any patient with calcium phosphate stones should be screened for primary hyperparathyroidism and RTA.
Struvite Stones (Infection Stones, 10–15%)
Composition: Magnesium ammonium phosphate hexahydrate (MgNH₄PO₄·6H₂O)
Pathophysiology: - Caused by urease-producing bacteria: Proteus mirabilis (most common), Klebsiella, Morganella, Pseudomonas - Bacteria produce urease enzyme → breaks down urea → ↑ ammonia → ↑ pH (>7.5–8.0) - Alkaline urine precipitates magnesium ammonium phosphate - Forms rapidly, often as “staghorn calculi” filling entire renal pelvis/calyces
Demographics: - More common in women (UTI frequency + catheterization) - Associated with chronic indwelling catheters, neurogenic bladder, frequent UTIs
Clinical significance: - Highly symptomatic; large size at diagnosis - Recurrent infections common - High surgical morbidity if nephrectomy needed
Treatment: Require antibiotics + stone removal (often surgical); medical management alone insufficient
Uric Acid Stones (5–10%)
Pathophysiology: - Uric acid poorly soluble in acidic urine (pKa 5.75) - Acidic urine (pH <5.5) favors crystallization - Most uric acid stones are radiolucent (not visible on plain X-ray)
Risk factors: - Gout (30% of gout patients get uric acid stones) - High purine diet (red meat, organ meats, shellfish, high-fructose drinks) - Dehydration - Diarrhea (↓ urinary pH from bicarbonate loss) - Malignancy with high cell turnover (leukemia, lymphoma) → ↑ uric acid - Thiazides can raise serum urate; persistently low urine pH is central to uric-acid stone risk
Unique feature: Uric acid stones are radiolucent but can appear as filling defects on CT or ultrasound.
Cystine Stones (1–2%, Genetic)
Pathophysiology: - Genetic disorder: Cystinuria — autosomal recessive - Defect in dibasic amino acid transporter (SLC3A1 or SLC7A9 genes) - ↓ Renal reabsorption of cystine, lysine, arginine, ornithine - Cystine poorly soluble; crystallizes at physiologic pH (6.5–7.0) - Requires urine cystine >400 mg/day to form stones
Diagnosis: - Elevated 24-hour urine cystine (>250 mg = abnormal) - Positive cyanide-nitroprusside test (qualitative urine cystine) - Genetic testing if confirmed - Family screening important (10–20% of siblings affected)
Clinical presentation: - Early age of onset (teens–30s) — red flag for cystinuria - Multiple recurrent stones - Large staghorn calculi common - Family history of stones in young patients
II. Pathophysiology of Stone Formation
The Three-Component Model of Lithogenesis
1. Supersaturation
Stone formation requires urine to become supersaturated with stone-forming substances.
Mechanism: - Solubility product (Ksp) is exceeded when [ion concentration] > Ksp - Example: For calcium oxalate, [Ca²⁺] × [Ox²⁻] > Ksp - Urine pH, temperature, ionic strength, and presence of inhibitors/promoters all affect solubility
Promoters of Supersaturation: - High sodium intake (↑ urinary Na → ↑ Ca reabsorption inhibition → ↑ urine Ca) - High animal protein (↑ uric acid, oxalate, acid load) - Dehydration (low urine volume concentrates solutes) - High fructose intake (↑ oxalate, ↑ uric acid) - Excessive ascorbic acid supplementation (↑ oxalate)
Inhibitors of Supersaturation (Protective): - Citrate: Forms soluble complexes with Ca²⁺; key inhibitor; excreted in urine - Magnesium: Forms soluble complex with oxalate - Pyrophosphate: Inhibits nucleation and crystal growth - Proteins: Nephrocalcin, Tamm-Horsfall protein inhibit crystallization - High urine volume: Dilutes solutes, ↓ saturation
2. Crystal Nucleation and Growth
Once supersaturation occurs, crystals form and grow.
Nucleation (Initial crystal formation): - Heterogeneous nucleation: Crystals form on existing matrix (Tamm-Horsfall protein, cellular debris) - Homogeneous nucleation: Spontaneous crystal formation in supersaturated urine (rare)
Growth factors: - Prolonged stasis of urine (low flow, obstruction) - Presence of biofilm or cellular matrix - Inadequate inhibitor concentration
3. Aggregation and Stone Maturation
Crystals clump together forming clinically significant stones.
Factors promoting aggregation: - Low urine volume - Prolonged urine contact time in renal pelvis/calyces - Presence of organic matrix (bacterial biofilm, cellular material) - Imbalance of inhibitors and promoters
III. Clinical Presentation and Diagnosis
Classic Presentation: Renal Colic
Symptoms: - Sudden-onset severe flank pain (8–10/10 severity) - Pain radiates from flank to groin (testis/labia in women) - Associated nausea and vomiting (visceral pain → vagal stimulation) - Hematuria (gross or microscopic) - Dysuria if stone in distal ureter near bladder - Frequency and urgency if stone low in ureter - Patient often restless (unlike peritonitis where still)
Timeline: - Pain can last minutes to hours - Episodes separated by pain-free intervals (stone movement) - Mild variants may present as chronic flank ache (asymptomatic/indolent stones)
Atypical Presentations
- Silent stones: Found incidentally on imaging for other reasons (10–15%)
- Chronic pyelonephritis: Recurrent infection if stone obstructing
- Acute kidney injury: Large stone with complete obstruction to solitary kidney
- Fever: If infected obstructed system (pyonephrosis) — surgical emergency
Physical Examination Findings
- Costovertebral angle (CVA) tenderness — non-specific; also present in pyelonephritis
- Hematuria — microscopic in 85%, gross in 10%
- Vital signs may show tachycardia, mild hypertension from pain
- Abdomen: Non-specific; may have abdominal guarding if severe pain
- No fever (unless infected; fever = pyonephrosis until proven otherwise)
Diagnostic Imaging
Non-Contrast CT Scan (CT KUB) — GOLD STANDARD
- Sensitivity: 97–99%
- Specificity: 96–98%
- Advantages:
- No contrast needed (better in renal failure)
- Detects all stone types (including radiolucent uric acid/cystine stones)
- Shows stone size, location, degree of obstruction
- Identifies complications (perinephric stranding, abscess)
- Alternate diagnosis if not stone (AAA, MI, etc.)
- Disadvantages:
- Radiation exposure varies by scanner and protocol; use an appropriate low-dose stone protocol when suitable rather than quoting 100 mSv as a routine CT-KUB dose.
- Cost
- Not ideal for monitoring asymptomatic stones or pregnancy
Ultrasound
- Sensitivity: 90–95% for stones >4 mm
- Specificity: 98–99%
- Advantages:
- No radiation
- Real-time, portable
- Good for pregnancy
- Detects hydronephrosis (obstruction)
- Can assess for AAA if presented
- Disadvantages:
- Operator-dependent
- Misses distal ureteral stones
- Limited in obese patients
Plain Abdominal X-Ray (KUB)
- Sensitivity: 50–80% (only radiopaque stones visible)
- Not useful for diagnosis (misses 20–50% of stones)
- Use: Follow-up imaging in known stone-formers; assess stone progression
Intravenous Pyelography (IVP)
- Largely replaced by CT
- Still used in some settings where CT unavailable
- Requires contrast; risk in renal insufficiency
Laboratory Findings
Urinalysis: - Hematuria: Present in 85% (microscopic), 10% (gross) - Crystals: May see oxalate, uric acid, or cystine crystals (not diagnostic) - Pyuria: Present if concurrent infection - Proteinuria: Usually absent unless concomitant kidney disease - Glucose, ketones: Absent (helps rule out DKA)
Serum Studies (initial workup): - Creatinine: Assess renal function; baseline for contrast toxicity risk - Calcium, phosphate: Screen for hyperparathyroidism - Uric acid: Elevated in gout, malignancy; risk for uric acid stones - Magnesium: Low magnesium associated with CaOx stones - BUN: Assess hydration
Urine Culture: - Obtain if fever, pyuria, or recurrent UTIs (rule out infection stone) - Essential before instrumentation if febrile
IV. Medical Management by Stone Type
Acute Stone Episode Management
Pain Control (First Priority):
| Agent | Dose | Route | Onset | Notes |
|---|---|---|---|---|
| NSAIDs | Indomethacin 50 mg q6h or Ketorolac 30–60 mg | PO/IV/IM | 30–60 min | Preferred; inhibits prostaglandins; reduces pain + ureteral spasm |
| Opioids | Morphine 4–10 mg q4–6h; Hydromorphone 2–4 mg | IV/IM/PO | 15–30 min | Backup if NSAID contraindicated; risk of constipation |
| Acetaminophen | 650–1000 mg q6h | PO | 30–60 min | Weaker; adjunct to NSAIDs |
| Antispasmodics | Dicyclomine 10–20 mg q4–6h | PO | 1–2 hours | Reduces ureteral spasm; adjunct |
| Antiemetics | Ondansetron 4–8 mg q8h or metoclopramide 10 mg | IV/PO | 15–30 min | Essential for nausea from visceral pain |
Acute stone episode: Correct hypovolemia and treat pain/nausea; forced hydration does not establish stone passage and can worsen pain or overload. Fever, sepsis, anuria, or threatened kidney function with obstruction requires urgent assessment and possible drainage. Long-term prevention usually aims for urine volume at least 2.5 L/day when clinically appropriate.
Medical expulsive therapy: An alpha blocker may be offered off label for suitable distal ureteral stones 5–10 mm when observation is safe; discuss hypotension and follow-up. Benefit is less certain for smaller stones. Do not present nifedipine as an equally supported routine alternative, and stop observation if infection, uncontrolled pain or kidney-function deterioration develops.
Monitoring: - Pain control; expect improvement within 24–48 hours - Urine output and hydration status - Renal function (creatinine) - Follow-up imaging in 2–4 weeks to confirm passage
Medical Management by Stone Type
Calcium Oxalate Stones
Management goals: - ↓ Urine calcium (hypercalciuria) - ↓ Urine oxalate (hyperoxaluria) - ↑ Urine citrate (hypocitraturia) - ↑ Urine volume (dilute urine)
Dietary prevention: Aim for urine volume at least 2.5 L/day when clinically appropriate, reduce excessive sodium, maintain normal dietary calcium (usually 1000–1200 mg/day) with meals and moderate excess animal protein. Target oxalate advice to stone composition and urine findings; do not prescribe blanket calcium restriction or magnesium supplements to all stone formers.
Pharmacologic therapy (if dietary modification insufficient after 3–6 months):
| Drug | Dose | Mechanism | Use Case |
|---|---|---|---|
| Thiazide diuretic (HCTZ) | 25 mg daily | ↓ urine Ca | Hypercalciuria (urine Ca >250 mg/day) |
| Potassium citrate | 20 mEq BID–TID | ↑ urine citrate; alkalinize urine | Hypocitraturia (<320 mg/day) + CaOx |
| Allopurinol | 100–300 mg daily | ↓ uric acid production | If uric acid >800 mg/day (↓ CaOx) |
| Vitamin B6 (pyridoxine) | 25–100 mg daily | ↓ oxalate synthesis | Hyperoxaluria or genetic predisposition |
| Magnesium supplementation | Individualized for a defined indication | Recurrence benefit uncertain | Avoid routine stone-only use; assess kidney function and toxicity risk |
Specific Workup: - 24-hour urine: Calcium, oxalate, citrate, magnesium, volume, uric acid - Serum: Calcium, phosphate, PTH (rule out hyperparathyroidism) - Urine pH: If <5.5, more likely CaOx; may add potassium citrate
Calcium Phosphate Stones
Management goals: - ↓ Urine phosphate and calcium - ↓ Urine pH (acidify urine) - Screen for and treat underlying cause (hyperparathyroidism, RTA, sarcoidosis)
Workup (ESSENTIAL): - Serum: PTH and serum calcium (hyperparathyroidism in 50% of apatite stones) - Serum and urine electrolytes, bicarbonate - 24-hour urine: Calcium, phosphate, citrate, pH - Screen for RTA: Urine anion gap (GAP = [Na+K-Cl]; <0 suggests dRTA), urine pH >5.5 in setting of acidemia
Treatment of hyperparathyroidism: - Surgical parathyroidectomy if symptomatic (elevated Ca, osteoporosis) — reduces the hyperparathyroid driver; stone recurrence can still occur and needs follow-up - Medical management alone (thiazide, cinacalcet) less effective for stone prevention
Calcium-phosphate stone prevention: Evaluate hyperparathyroidism, distal RTA, urine pH and calcium/citrate excretion. Acetazolamide alkalinizes urine and can promote calcium-phosphate stones; it is not routine prevention. Use normal dietary calcium, sodium reduction and individualized fluid intake. Consider a thiazide for persistent hypercalciuria after discussing benefits, adverse effects and uncertain recurrence benefit; potassium citrate may be appropriate for selected hypocitraturia/RTA but requires monitoring urine pH and calcium-phosphate supersaturation.
Struvite (Infection) Stones
Key principle: Medical therapy alone CANNOT dissolve struvite stones. Surgery required.
Infection/struvite stones: Obtain urine cultures and coordinate urologic source control; infected obstruction requires urgent drainage and antibiotics. Culture-directed antibiotics complement stone clearance. Do not use acetazolamide as urine-acidification therapy. A urease inhibitor may be considered by a specialist when surgical options are exhausted or unsuitable, balancing substantial adverse effects.
Surgical management (definitive): - Percutaneous nephrolithotomy (PCNL): For large staghorn calculi - Partial nephrectomy: If renal function already compromised and stone burden large - Complete nephrectomy: If recurrent infections, non-functioning kidney, patient unable to tolerate repeat surgery
Prevention of recurrence: - Treat underlying UTI/neurogenic bladder aggressively - Consider prophylactic antibiotics if recurrent infections - Regular imaging to monitor for recurrence
Uric Acid Stones
Uric acid management: Low urine pH is the central modifiable driver. Alkalinization is the primary dissolution/prevention strategy, with the pH target and monitoring individualized to the treatment goal and calcium-phosphate risk; add urate-lowering therapy for a relevant indication.
Unique feature: Uric acid stones can partially or completely dissolve with medical therapy (unlike CaOx/struvite).
Uric acid prevention: Aim for at least 2.5 L/day urine when appropriate, moderate purine-rich animal foods and excess fructose, and use monitored alkali treatment. Review potassium/kidney function before choosing potassium citrate.
Pharmacologic therapy:
| Drug | Dose | Mechanism | Notes |
|---|---|---|---|
| Potassium citrate | 20 mEq BID–TID | Alkalinize urine | First-line; target pH 6.0–6.5 |
| Sodium bicarbonate | 500–1000 mg TID | Alkalinize urine | Alternative if K+ restricted |
| Allopurinol | 100–300 mg daily | ↓ xanthine oxidase; ↓ uric acid | If uric acid >800 mg/day or gout |
| Febuxostat | 40–80 mg daily | Xanthine oxidase inhibitor | Alternative to allopurinol; less renal dosing |
| Rasburicase | 0.2 mg/kg IV | Uricase; converts uric acid → allantoin | Acute tumor lysis syndrome only; very expensive |
Monitoring: - 24-hour urine pH (target 6.0–6.5) - Serum uric acid (if on allopurinol; target <6 mg/dL) - Repeat imaging at 6–12 weeks to assess stone dissolution
Cystine Stones
Management goals: - ↑ Urine volume (massive; target 3–4 L/day or higher) - ↑ Urine pH (>7.0 increases cystine solubility) - ↓ Urine cystine concentration (<250 mg/day)
Dietary modifications: 1. Fluid intake: 3–4 L/day minimum (most important intervention) - Split intake: 1 L before bed + nocturia to maintain high nighttime urine volume - This alone may prevent stone formation 2. Sodium restriction: <2.3 g/day (↑ Na → ↑ cystine reabsorption) 3. Protein restriction: 0.8–1.0 g/kg/day (reduces urine cystine) 4. Potassium citrate: Alkalinize urine to pH >7.0 (but careful not to precipitate calcium phosphate)
Pharmacologic therapy (if dietary changes insufficient):
| Drug | Dose | Mechanism | Notes |
|---|---|---|---|
| Potassium citrate | 20 mEq BID–TID | ↑ pH to 7.0–7.5 | Mandatory; forms soluble calcium cystinate complex |
| D-Penicillamine | 250–500 mg BID | Chelates cystine → form soluble disulfide | Second-line; significant side effects (rash, taste, proteinuria) |
| Tiopronin | 100–300 mg TID | Similar to penicillamine; fewer side effects | Preferred over penicillamine; still significant SE profile |
| Alpha-lipoic acid | 300–600 mg daily | May reduce cystine; investigational | Limited evidence; some benefit reported |
Monitoring: - 24-hour urine cystine (target <250 mg/day) - Urine pH (target 7.0–7.5) - Serum electrolytes (hypokalemia risk from citrate) - Renal function (monitor for proteinuria from chelators)
V. Dietary Modifications Summary
Universal Recommendations (All Stone Types)
| Recommendation | Rationale |
|---|---|
| Increase fluid intake to achieve at least 2.5 L/day urine when clinically appropriate | ↓ supersaturation; dilutes solutes |
| Restrict sodium to <2.3 g/day | ↓ urine Ca; improves citrate retention |
| Moderate protein: 0.8–1.0 g/kg/day | ↓ uric acid, oxalate, acid load |
| Maintain calcium intake: 1000–1200 mg/day | ↓ intestinal oxalate absorption |
| Increase magnesium intake | Forms soluble complexes with oxalate |
| Limit high-purine foods | ↓ uric acid (if uric acid stones) |
| Avoid high-fructose drinks | ↓ uric acid, oxalate |
Stone-Specific Dietary Recommendations
| Stone Type | Add | Avoid |
|---|---|---|
| CaOx | Magnesium, potassium citrate | Spinach, nuts, chocolate, tea |
| CaPO₄ | Normal dietary calcium; sodium reduction; urine-guided citrate/thiazide assessment | Excess sodium; unmonitored urine alkalinization |
| Uric acid | Potassium citrate, water | Purines, fructose |
| Cystine | Massive water intake (3–4 L/day urine), potassium citrate | Sodium, high protein |
| Struvite | Adequate fluid; infection control and complete stone clearance when feasible | Persistent urease-producing infection; dietary acidification alone is not treatment |
VI. Surgical Management Indications and Options
Indications for Intervention (Non-Medical Management)
Emergent: - Infected obstructed kidney (pyonephrosis) with sepsis → ureteral stent/nephrostomy + antibiotics, then definitive treatment - Complete bilateral obstruction with AKI - Obstruction of solitary kidney with AKI
Urgent (within 1–2 weeks): - Persistent pain despite optimal medical therapy - Fever/infection - Complete obstruction with nausea/vomiting preventing hydration
Stone location and size affect passage; distal stones generally pass more readily than proximal stones of comparable size.
Surgical Options by Stone Location and Size
Shock Wave Lithotripsy (ESWL)
Mechanism: Externally applied shock waves fragment stone via energy transmission through tissues.
Advantages: - Non-invasive, outpatient - Can treat multiple stones - No instrumentation of urinary tract
Disadvantages: - Lower success rate (70–80%) vs. ureteroscopy (>90%) - Requires stone visualization (need radiopaque stone or CT guidance) - Residual fragments common; may require second procedure - Contraindicated in pregnancy - Risk of renal injury (minor, usually)
Best use: Proximal ureteral stones 10–20 mm, or as first-line if patient desires non-invasive approach
Ureteroscopy (URS)
Mechanism: Endoscopic visualization of ureter; stone fragmented (laser, pneumatic) or removed directly.
Advantages: - High success rate (>95% for stones <15 mm) - Can treat distal ureteral stones (where ESWL difficult) - Minimal residual fragments - Real-time visualization - Lower re-treatment rate than ESWL
Disadvantages: - Requires instrumentation (risk of ureteral perforation, stricture, infection) - Anesthesia required - Not ideal for very large stones (>20 mm) - Operative time longer than ESWL
Best use: Distal ureteral stones, recurrent stones, large stones unsuitable for ESWL, pregnancy
Percutaneous Nephrolithotomy (PCNL)
Mechanism: Percutaneous puncture of kidney; nephroscope inserted; stone fragmented (ultrasonic, laser) or removed.
Advantages: - Highest success rate (95–98%) for any stone - Can treat very large (>2 cm) and staghorn stones - Can obtain stone fragments for analysis - Best for complex stone burden
Disadvantages: - Invasive; requires percutaneous renal access - Highest bleeding risk (~15% transfusion in unselected patients) - Significant morbidity (fever, infection, sepsis 3–8%) - Highest cost - Requires anesthesia and skilled percutaneous access
Best use: Large (>2 cm) stones, staghorn calculi, PCNL failure, struvite stones, pediatric stones
Prone PCNL vs. Supine PCNL
- Prone: Traditional; easier anatomic access; risk of aspiration under anesthesia
- Supine: Newer; less risk of aspiration; may allow combined cystoscopy/ESWL; slightly limited access
Mini-PCNL or Ultra-Mini-PCNL
- Smaller bore access (20–24 Fr vs. 28–30 Fr for standard)
- Lower bleeding risk; higher re-treatment rate; emerging technique
Robotic-Assisted Pyelolithotomy
- Open surgical approach (planned intra-renal stone extraction)
- Rarely indicated; reserved for complex cases or failed endoscopic approach
Success Rates and Complications by Procedure
| Procedure | Success Rate (Stone-Free) | Perforation Risk | Bleeding Risk | Infection Risk | Cost |
|---|---|---|---|---|---|
| ESWL | 70–85% | Minimal | Minimal | Low | Low |
| URS | 90–98% | 1–2% (ureteral) | Minimal | Low–moderate | Moderate |
| PCNL | 95–98% | 1–3% (collecting system) | 15% (transfusion) | 3–8% | High |
VII. 24-Hour Urine Interpretation and Metabolic Workup
When to Order 24-Hour Urine
Metabolic testing: Offer additional testing to recurrent or high-risk stone formers and interested first-time stone formers. Consider composition, age of onset, family history, CKD, associated disease and recurrence burden rather than an automatic age-below-50 rule.
Timing: Collect after acute stone episode resolves (3–4 weeks later); patient on normal diet/hydration.
Standard 24-Hour Urine Parameters
A 24-hour urine assessment includes volume, creatinine (collection adequacy), calcium, oxalate, citrate, uric acid, sodium, potassium and pH; add other analytes such as cystine when indicated. Interpret the whole profile, diet and collection quality rather than isolated universal cutoffs. Aim for at least 2.5 L/day urine for most stone formers when clinically appropriate; cystinuria often requires a higher target.
Interpretation Patterns by Stone Type
Calcium Oxalate Stone Pattern
- ↑ Calcium (>250 mg/day)
- ↑ Oxalate (>40 mg/day)
- ↓ Citrate (<320 mg/day) — common finding
- ↓ Magnesium (<100 mg/day) — common finding
- ↓ Volume (<2 L/day) — nearly always present
- pH: Acidic (5.5–6.5)
Intervention: ↑ Volume, ↓ Na, ↓ protein, ↓ oxalate intake, do not prescribe magnesium routinely; consider potassium citrate and/or thiazide selectively
Uric Acid Stone Pattern
- ↑ Uric acid (>800 mg/day, often >1000)
- ↓ pH (<5.5) — KEY finding
- ↓ Citrate (often <300 mg/day)
- ↓ Volume often present
- Normal Ca, P, Mg
Intervention: Alkalinize urine (potassium citrate), allopurinol if uric acid >900 mg/day, purine-restrict diet
Cystine Stone Pattern
- ↑ Cystine (>250 mg/day; diagnostic if >400)
- Positive cyanide-nitroprusside test on random urine
- ↓ Volume critical finding
- ↓ pH often <6.0
- Family history often positive
Intervention: Massive volume (3–4 L/day), sodium restriction, potassium citrate, consider D-penicillamine or tiopronin
Hyperparathyroidism Pattern (Apatite/Calcium Phosphate Stones)
- ↑↑ Calcium (often >300 mg/day)
- ↑ Phosphate
- ↓ Citrate
- Elevated serum PTH and serum calcium
- pH: Alkaline (>7.0)
- Note: May form apatite concurrently with CaOx
Intervention: Check serum PTH, consider parathyroidectomy if surgical candidate; thiazide if not surgical
VIII. Prevention and Long-Term Management
Lifestyle Modifications for Stone Prevention
Tier 1 (Universal, for all patients): 1. Increase hydration (target at least 2.5 L/day urine output when clinically appropriate; split throughout day) 2. Reduce sodium (<2.3 g/day) 3. Moderate protein (0.8–1.0 g/kg) 4. Maintain calcium intake (1000–1200 mg/day; don’t restrict) 5. Increase vegetables and whole grains
Tier 2 (Based on stone type/metabolic abnormalities): 1. Restrict oxalate (if hyperoxaluria) 2. Restrict purines (if uric acid stones) 3. Assess magnesium only for a defined indication; do not routinely supplement every CaOx stone former 4. Alkali supplementation (if uric acid or cystine stones)
Tier 3 (Pharmacologic, if dietary modifications insufficient): - See Section IV (Medical Management) for specific agents
Monitoring Strategy
After first stone (no known risk factors): - Repeat imaging at 6–12 months - Annual follow-up
After recurrent stones or high-risk metabolic profile: - Repeat 24-hour urine at 6 weeks after implementing interventions - Adjust therapy based on results - Repeat annually if ongoing risk
High-risk patients (cystine, young age, multiple recurrences): - 24-hour urine every 6–12 months - Imaging every 6–12 months - More aggressive pharmacologic intervention
Practice Questions
A 45-year-old man with a history of one prior kidney stone presents with severe left flank pain radiating to the groin. Non-contrast CT shows a 5 mm stone in the left proximal ureter with mild hydronephrosis. No fever. Labs show normal creatinine and urinalysis shows microscopic hematuria. Urine culture is negative. What is the best initial management?
- Immediate ureteroscopy for stone removal
- IV fluids, NSAIDs, antiemetics, and observation for stone passage
- Shock wave lithotripsy
- Empiric antibiotics
Answer: B. A 5 mm proximal ureteral stone has a 50–70% chance of spontaneous passage with conservative management. First-line treatment is hydration, analgesia (NSAIDs preferred), and antiemetics. If pain is controlled and no fever/infection, observe. Add expulsive therapy (tamsulosin) if desired. Consider ureteroscopy if pain not controlled, fever develops, or stone fails to pass after 4–6 weeks. ESWL or URS would be reserved for larger stones (>6–8 mm) or failed passage.
A 38-year-old woman has a 1 cm calcium oxalate stone. Her urine calcium is 320 mg/day (elevated), oxalate 65 mg/day (elevated), citrate 250 mg/day (low), volume 0.8 L/day (low), and magnesium 80 mg/day (low). Serum calcium and PTH are normal. Which initial intervention is most important?
- Start thiazide diuretic
- Increase fluid intake to achieve at least 2.5 L/day urine when clinically appropriate
- Start allopurinol
- Restrict dietary calcium
Answer: B. Urine volume 0.8 L/day is an important modifiable risk; aim for at least 2.5 L/day when clinically appropriate. This patient also has hyperoxaluria, hypocitraturia and urine calcium 320 mg/day, which is elevated rather than normal. Maintain normal dietary calcium with meals, reduce excessive sodium and targeted oxalate intake, and individualize citrate/thiazide treatment from repeated urine studies and current evidence.
A 32-year-old man presents with his third kidney stone in 2 years. Basic metabolic panel shows serum calcium 10.2 mg/dL (normal), PTH 85 pg/mL (normal 15–65). 24-hour urine shows: Uric acid 950 mg/day (elevated), Oxalate 35 mg/day (normal), Citrate 280 mg/day (low), pH 5.2 (acidic), Volume 1.5 L/day. What is the stone type likely to form, and what is first-line therapy?
- Calcium oxalate; start potassium citrate
- Uric acid is likely; use monitored urine alkalinization and assess the indication for additional urate-lowering therapy
- Calcium phosphate; start thiazide
- Struvite; start prophylactic antibiotics
Answer: B. The acidic urine and hyperuricosuria make uric acid stones a strong possibility; confirm composition when a stone is available. Use monitored urine alkalinization as the central treatment, assess potassium and kidney function, and add urate-lowering therapy when hyperuricosuria/gout warrants it. Evaluate the mildly raised PTH with calcium rather than ignoring it; do not infer the cause of hyperuricosuria from this profile alone.
Clinical Pearls Summary
- CT KUB is the gold standard for diagnosis (97–99% sensitivity); detects all stone types including radiolucent ones
- Calcium restriction is harmful in stone-formers (↑ oxalate absorption); maintain 1000–1200 mg/day
- Uric acid stones may dissolve through appropriately monitored urine alkalinization. Add allopurinol for a relevant hyperuricosuria/gout indication; it is not the principal dissolution treatment.
- Offer metabolic testing to recurrent or high-risk stone formers and interested first-time stone formers; age below 50 alone is not a universal testing mandate.
- Medical management fails in struvite stones; surgery mandatory; antibiotics alone won’t cure
- Cystine stones require aggressive hydration (3–4 L/day urine output); fluids > medications
- Asymptomatic stones <4 mm pass spontaneously 90% of the time; observation reasonable
- Stone-free rates: ESWL 70–85%, URS >90%, PCNL >95%
- Low urine volume is a modifiable risk: aim for at least 2.5 L/day urine for most stone formers when clinically appropriate, with a higher individualized target for cystinuria.
References
- Khan SR, Pearle MS, Robertson WG, et al. Kidney stones. Nat Rev Dis Primers. 2016;2:16008. PubMed
- Sakhaee K. Epidemiology and clinical pathophysiology of uric acid kidney stones. J Nephrol. 2014;27(3):241-245. PubMed
- Fink HA, Wilt TJ, Eidman KE, et al. Medical management to prevent recurrent nephrolithiasis in adults: a systematic review for an American College of Physicians Clinical Guideline. Ann Intern Med. 2013;158(7):535-543. PubMed
- Ramello A, Vitale C, Marangella M. Epidemiology of nephrolithiasis. J Nephrol. 2000;13 Suppl 3:S45. PubMed
- Brisbane W, Bailey MR, Sorensen MD. An overview of kidney stone imaging techniques. Nat Rev Urol. 2016;13(11):654-662. PubMed
- Pearle MS, Goldfarb DS, Assimos DG, et al. Medical management of kidney stones: AUA guideline. J Urol. 2014;192(2):316-324. PubMed
- Matlaga BR, American Board of Urology. Contemporary surgical management of upper urinary tract calculi. J Urol. 2009;181(5):2152-2156. PubMed
- Curhan GC. Epidemiology of stone disease. Urol Clin North Am. 2007;34(3):287-293. PubMed
- Kidney Disease: Improving Global Outcomes (KDIGO) CKD Work Group. KDIGO 2024 Clinical Practice Guideline for the Evaluation and Management of Chronic Kidney Disease. Kidney Int. 2024;105(4S):S117. PubMed
- Borghi L, Schianchi T, Meschi T, et al. Comparison of two diets for the prevention of recurrent stones in idiopathic hypercalciuria. N Engl J Med. 2002;346(2):77-84. PubMed
Created for PA and medical student education. Consult clinical guidelines and supervising physicians for patient care decisions.