Visual summary
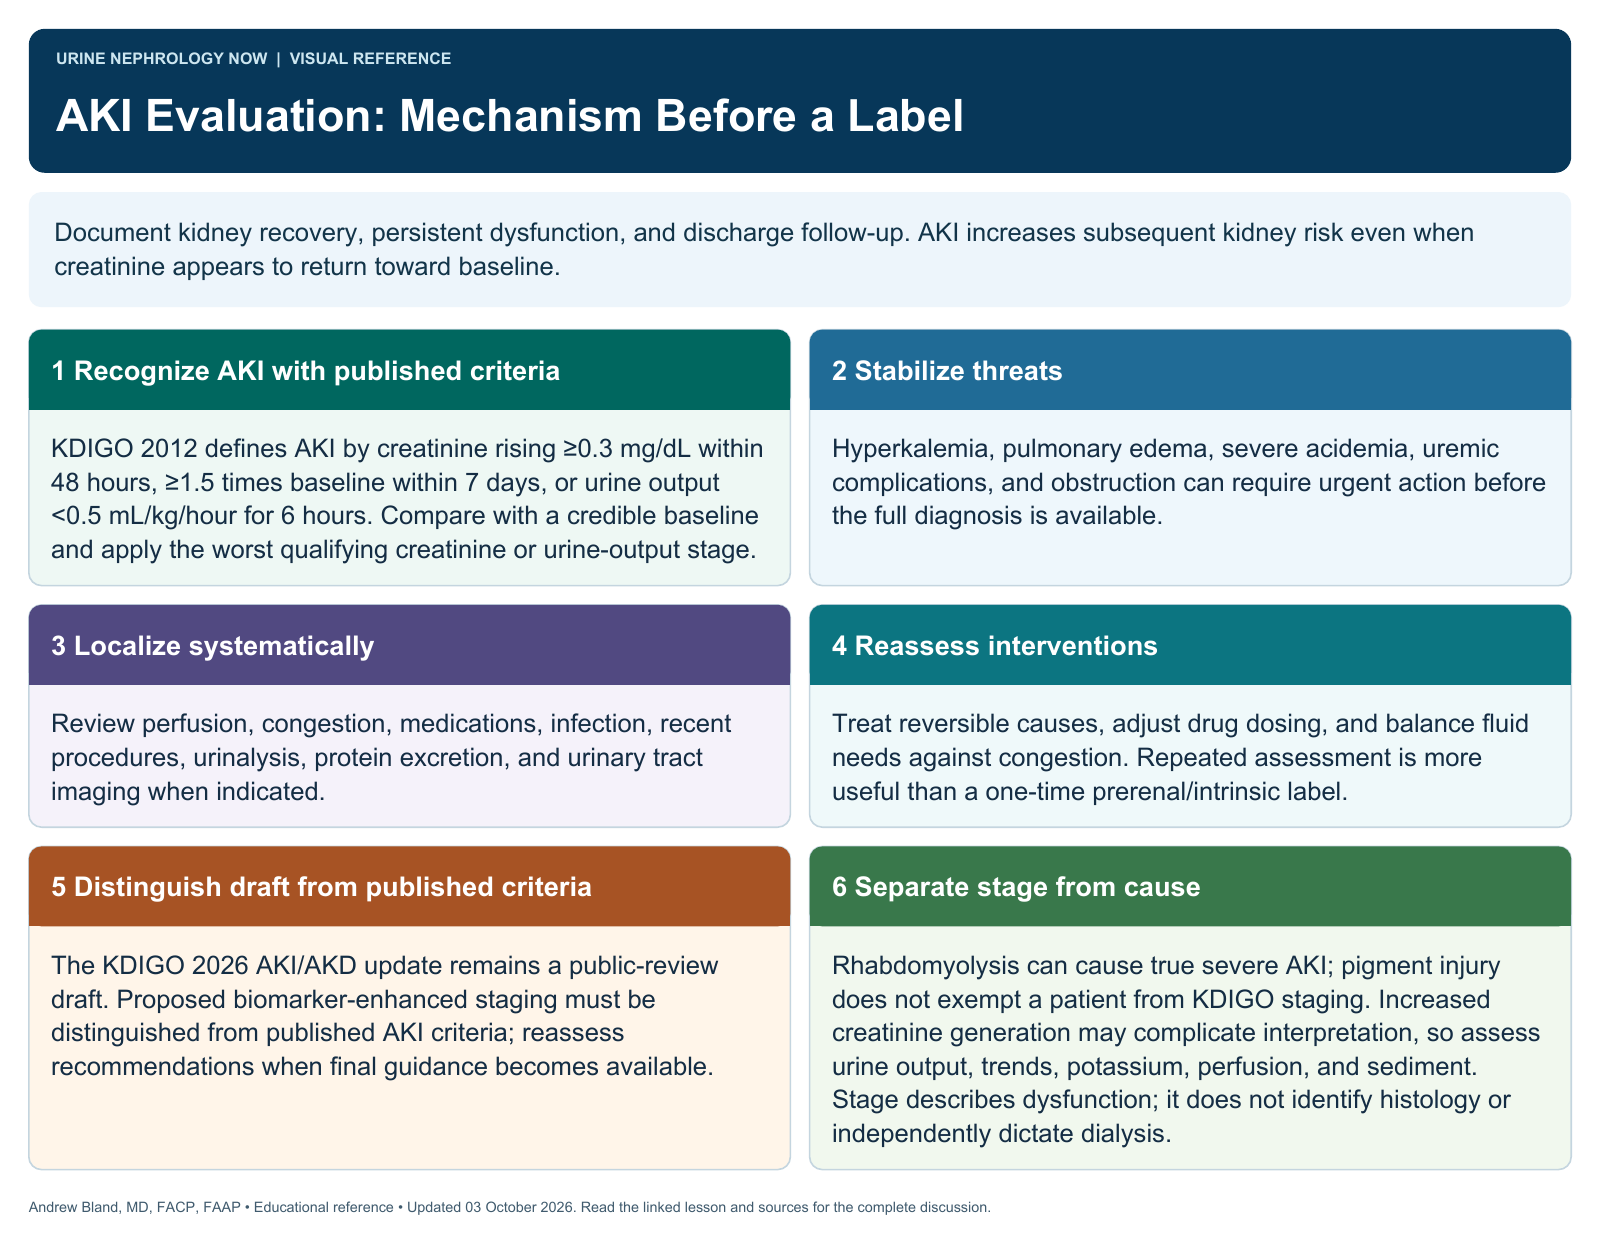
Document kidney recovery, persistent dysfunction, and discharge follow-up. AKI increases subsequent kidney risk even when creatinine appears to return toward baseline.
Text version
Recognize AKI with published criteria
KDIGO 2012 defines AKI by creatinine rising ≥0.3 mg/dL within 48 hours, ≥1.5 times baseline within 7 days, or urine output <0.5 mL/kg/hour for 6 hours. Compare with a credible baseline and apply the worst qualifying creatinine or urine-output stage.
Stabilize threats
Hyperkalemia, pulmonary edema, severe acidemia, uremic complications, and obstruction can require urgent action before the full diagnosis is available.
Localize systematically
Review perfusion, congestion, medications, infection, recent procedures, urinalysis, protein excretion, and urinary tract imaging when indicated.
Reassess interventions
Treat reversible causes, adjust drug dosing, and balance fluid needs against congestion. Repeated assessment is more useful than a one-time prerenal/intrinsic label.
Distinguish draft from published criteria
The KDIGO 2026 AKI/AKD update remains a public-review draft. Proposed biomarker-enhanced staging must be distinguished from published AKI criteria; reassess recommendations when final guidance becomes available.
Separate stage from cause
Rhabdomyolysis can cause true severe AKI; pigment injury does not exempt a patient from KDIGO staging. Increased creatinine generation may complicate interpretation, so assess urine output, trends, potassium, perfusion, and sediment. Stage describes dysfunction; it does not identify histology or independently dictate dialysis.