Visual summary
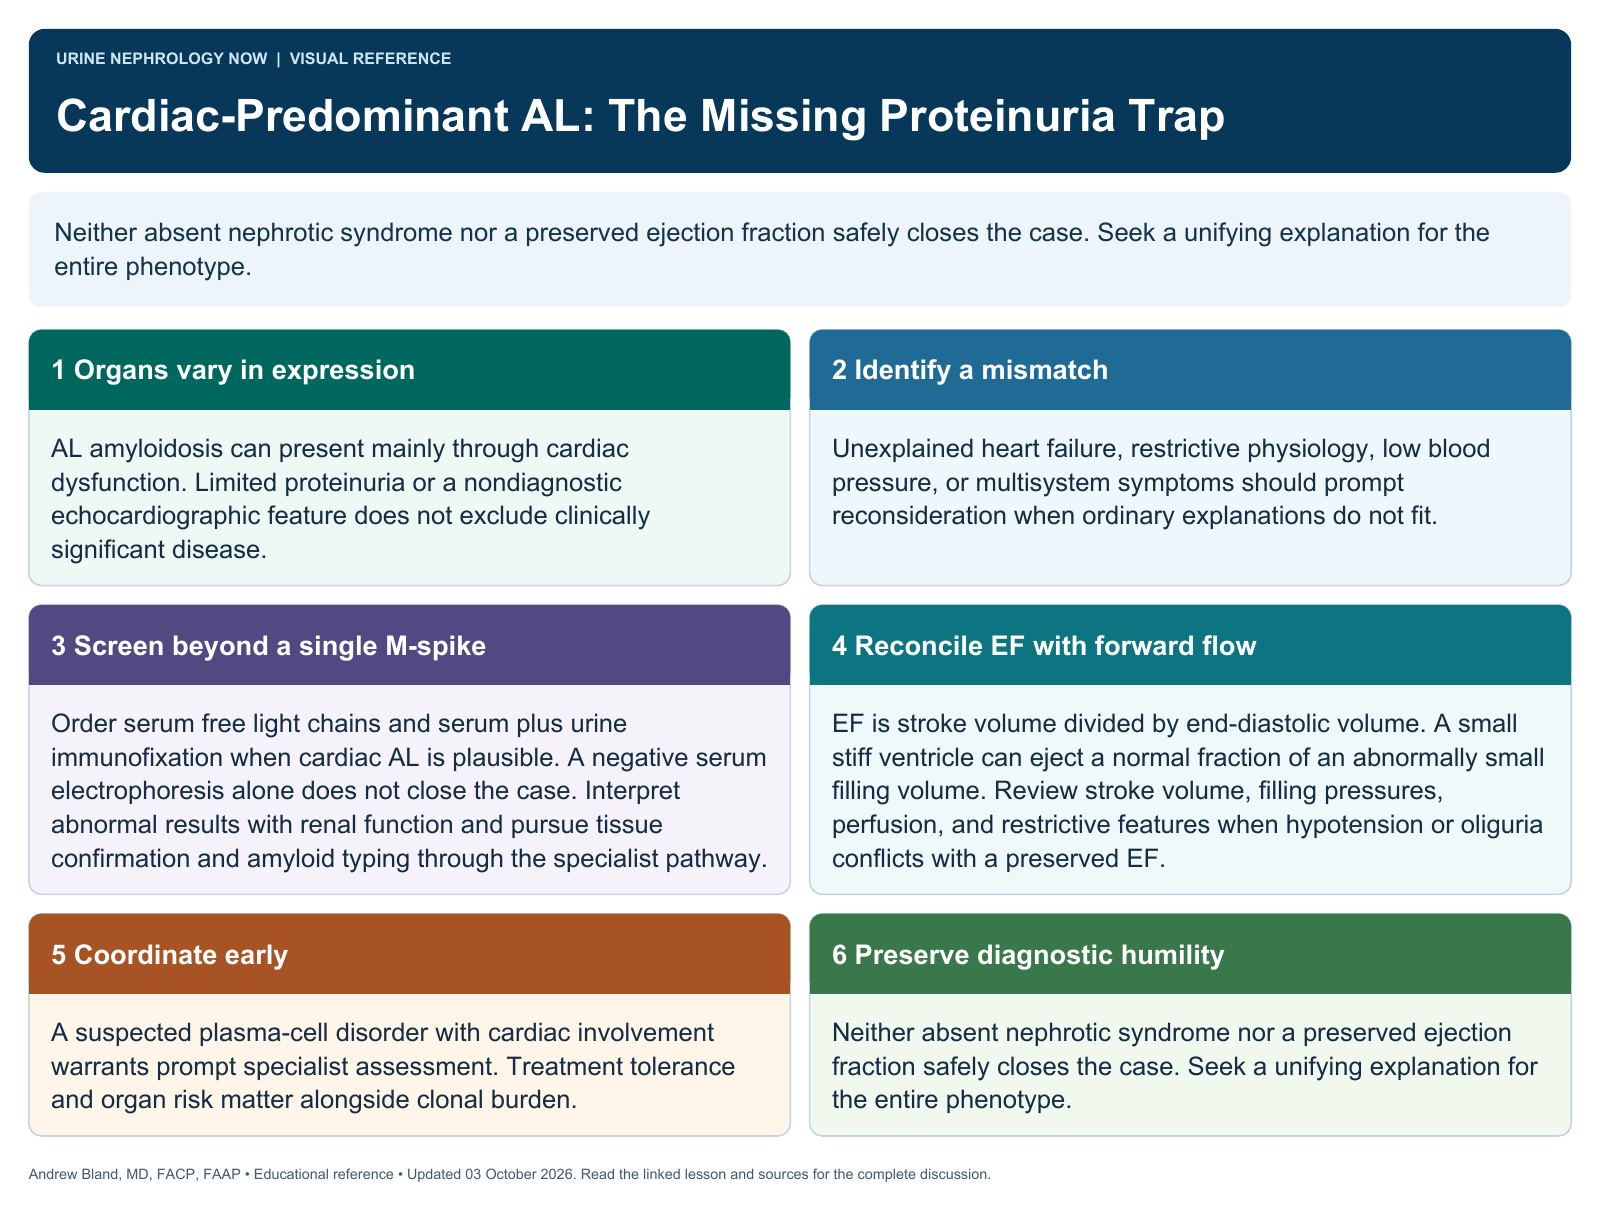
Neither absent nephrotic syndrome nor a preserved ejection fraction safely closes the case. Seek a unifying explanation for the entire phenotype.
Text version
Organs vary in expression
AL amyloidosis can present mainly through cardiac dysfunction. Limited proteinuria or a nondiagnostic echocardiographic feature does not exclude clinically significant disease.
Identify a mismatch
Unexplained heart failure, restrictive physiology, low blood pressure, or multisystem symptoms should prompt reconsideration when ordinary explanations do not fit.
Combine evidence streams
Assess monoclonal studies, light chains, cardiac imaging, biomarkers, and tissue findings. Each test answers a different part of the diagnostic question.
Avoid echo-only diagnosis
Wall thickness, strain patterns, and ejection fraction can be misleading or nonspecific. Interpret imaging with hemodynamics and laboratory evidence.
Coordinate early
A suspected plasma-cell disorder with cardiac involvement warrants prompt specialist assessment. Treatment tolerance and organ risk matter alongside clonal burden.
Preserve diagnostic humility
Neither absent nephrotic syndrome nor a preserved ejection fraction safely closes the case. Seek a unifying explanation for the entire phenotype.
Continue learning
This graphic summarizes a topic. The full educational pages provide the broader discussion and references.