Visual summary
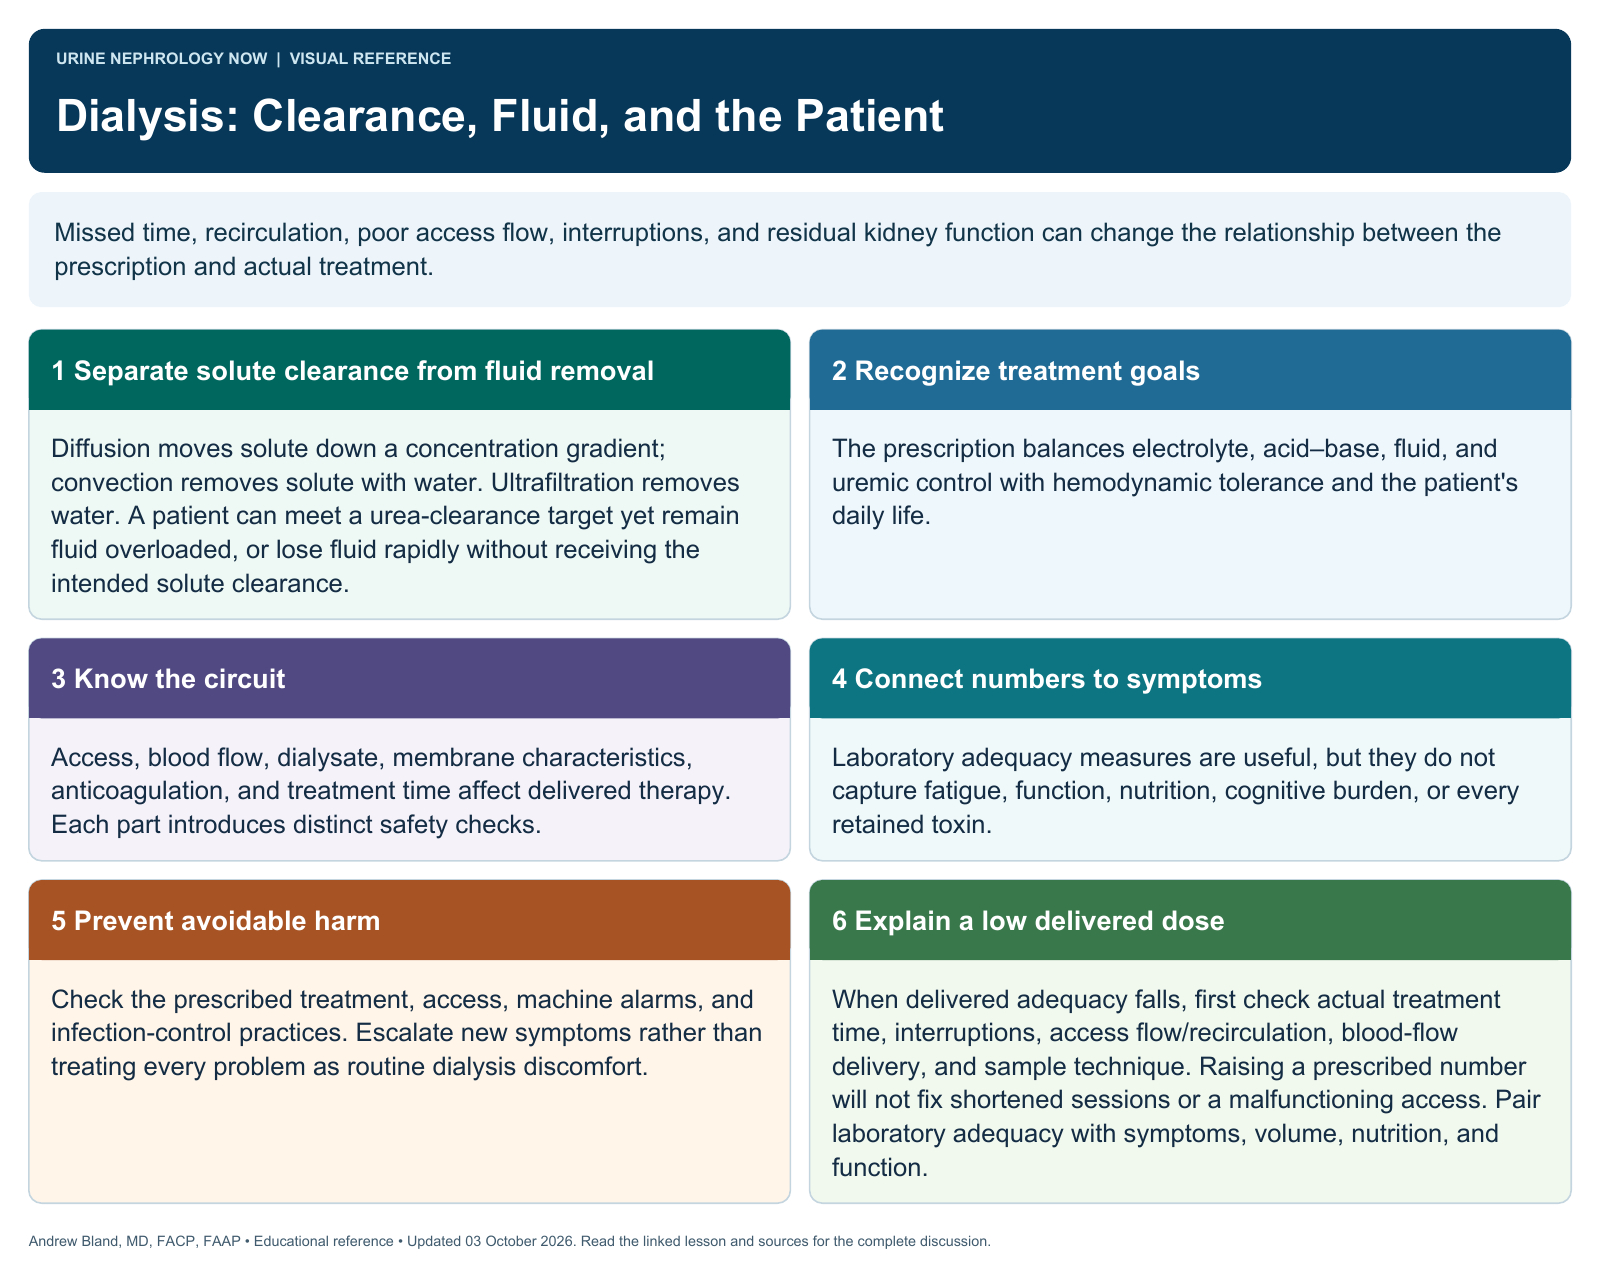
Missed time, recirculation, poor access flow, interruptions, and residual kidney function can change the relationship between the prescription and actual treatment.
Text version
Separate solute clearance from fluid removal
Diffusion moves solute down a concentration gradient; convection removes solute with water. Ultrafiltration removes water. A patient can meet a urea-clearance target yet remain fluid overloaded, or lose fluid rapidly without receiving the intended solute clearance.
Recognize treatment goals
The prescription balances electrolyte, acid–base, fluid, and uremic control with hemodynamic tolerance and the patient's daily life.
Know the circuit
Access, blood flow, dialysate, membrane characteristics, anticoagulation, and treatment time affect delivered therapy. Each part introduces distinct safety checks.
Connect numbers to symptoms
Laboratory adequacy measures are useful, but they do not capture fatigue, function, nutrition, cognitive burden, or every retained toxin.
Prevent avoidable harm
Check the prescribed treatment, access, machine alarms, and infection-control practices. Escalate new symptoms rather than treating every problem as routine dialysis discomfort.
Explain a low delivered dose
When delivered adequacy falls, first check actual treatment time, interruptions, access flow/recirculation, blood-flow delivery, and sample technique. Raising a prescribed number will not fix shortened sessions or a malfunctioning access. Pair laboratory adequacy with symptoms, volume, nutrition, and function.