Visual summary
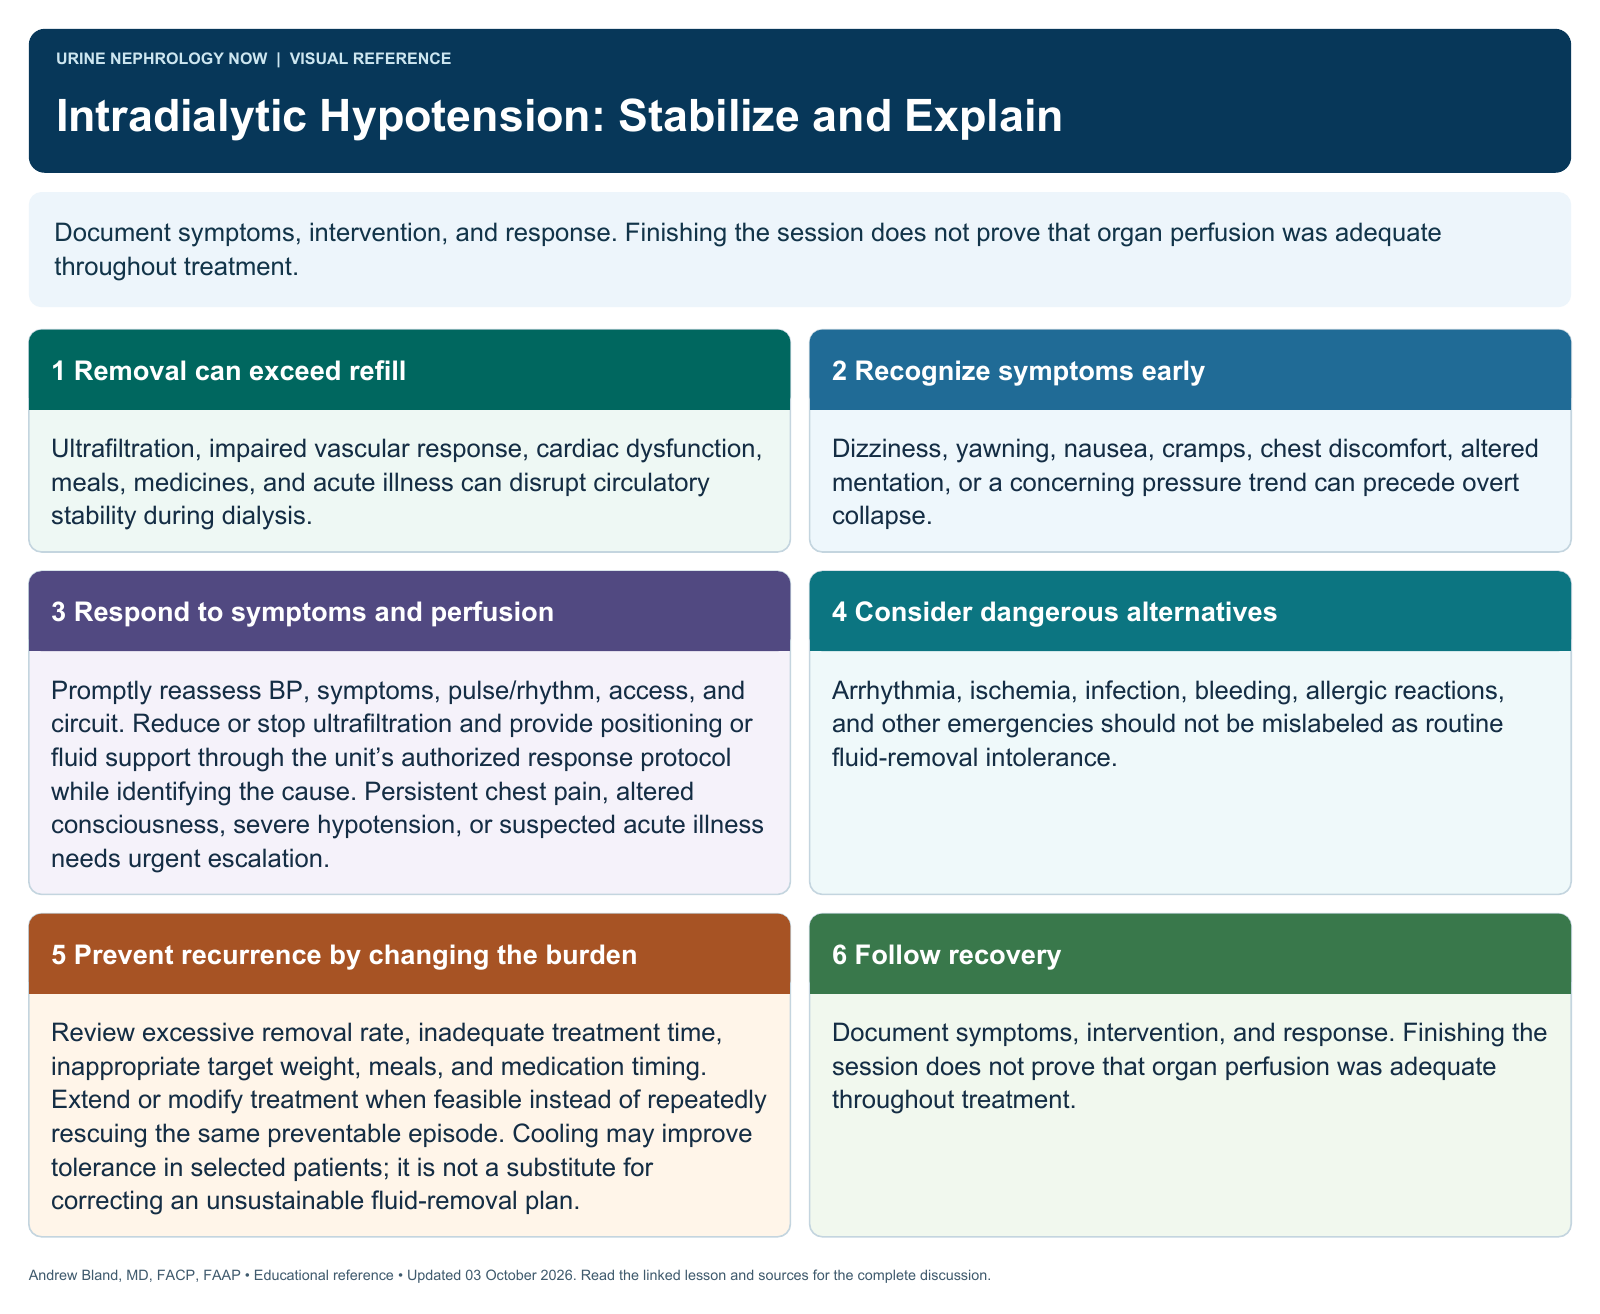
Document symptoms, intervention, and response. Finishing the session does not prove that organ perfusion was adequate throughout treatment.
Text version
Removal can exceed refill
Ultrafiltration, impaired vascular response, cardiac dysfunction, meals, medicines, and acute illness can disrupt circulatory stability during dialysis.
Recognize symptoms early
Dizziness, yawning, nausea, cramps, chest discomfort, altered mentation, or a concerning pressure trend can precede overt collapse.
Respond to symptoms and perfusion
Promptly reassess BP, symptoms, pulse/rhythm, access, and circuit. Reduce or stop ultrafiltration and provide positioning or fluid support through the unit’s authorized response protocol while identifying the cause. Persistent chest pain, altered consciousness, severe hypotension, or suspected acute illness needs urgent escalation.
Consider dangerous alternatives
Arrhythmia, ischemia, infection, bleeding, allergic reactions, and other emergencies should not be mislabeled as routine fluid-removal intolerance.
Prevent recurrence by changing the burden
Review excessive removal rate, inadequate treatment time, inappropriate target weight, meals, and medication timing. Extend or modify treatment when feasible instead of repeatedly rescuing the same preventable episode. Cooling may improve tolerance in selected patients; it is not a substitute for correcting an unsustainable fluid-removal plan.
Follow recovery
Document symptoms, intervention, and response. Finishing the session does not prove that organ perfusion was adequate throughout treatment.