Visual summary
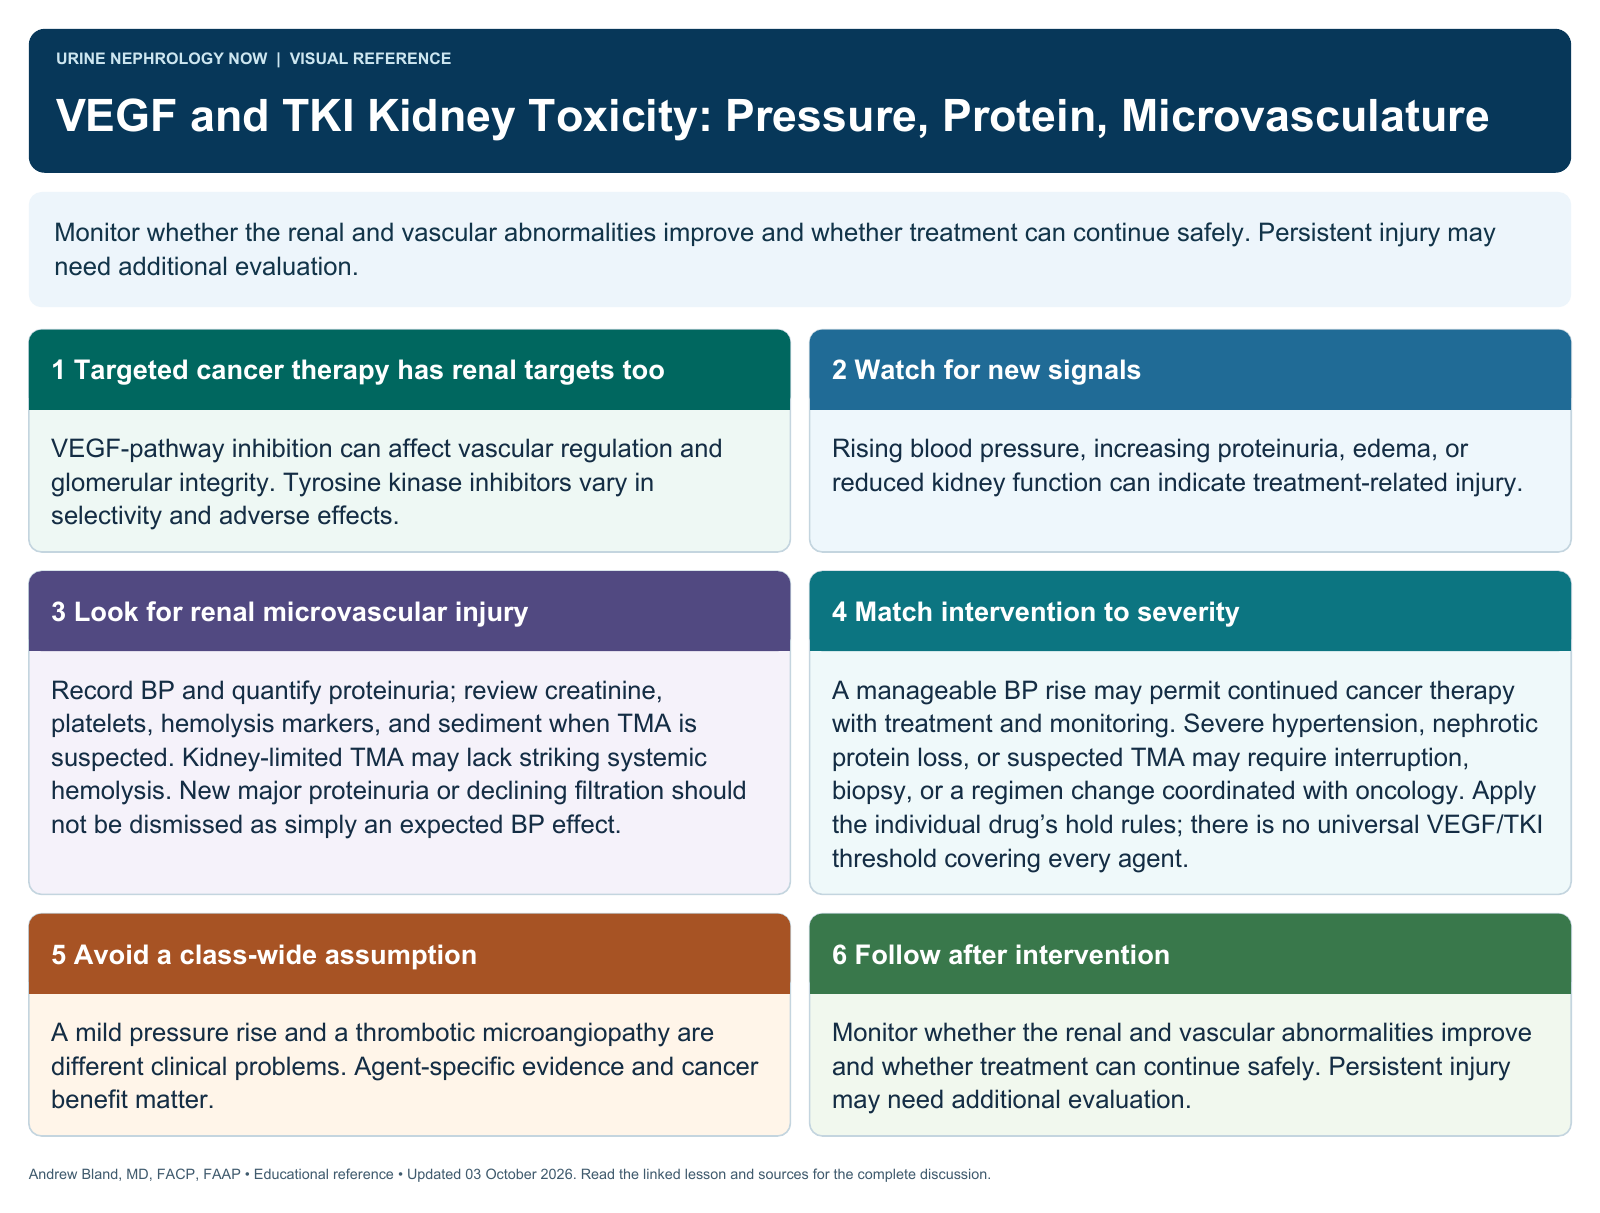
Monitor whether the renal and vascular abnormalities improve and whether treatment can continue safely. Persistent injury may need additional evaluation.
Text version
Targeted cancer therapy has renal targets too
VEGF-pathway inhibition can affect vascular regulation and glomerular integrity. Tyrosine kinase inhibitors vary in selectivity and adverse effects.
Watch for new signals
Rising blood pressure, increasing proteinuria, edema, or reduced kidney function can indicate treatment-related injury.
Look for renal microvascular injury
Record BP and quantify proteinuria; review creatinine, platelets, hemolysis markers, and sediment when TMA is suspected. Kidney-limited TMA may lack striking systemic hemolysis. New major proteinuria or declining filtration should not be dismissed as simply an expected BP effect.
Match intervention to severity
A manageable BP rise may permit continued cancer therapy with treatment and monitoring. Severe hypertension, nephrotic protein loss, or suspected TMA may require interruption, biopsy, or a regimen change coordinated with oncology. Apply the individual drug’s hold rules; there is no universal VEGF/TKI threshold covering every agent.
Avoid a class-wide assumption
A mild pressure rise and a thrombotic microangiopathy are different clinical problems. Agent-specific evidence and cancer benefit matter.
Follow after intervention
Monitor whether the renal and vascular abnormalities improve and whether treatment can continue safely. Persistent injury may need additional evaluation.