Visual summary
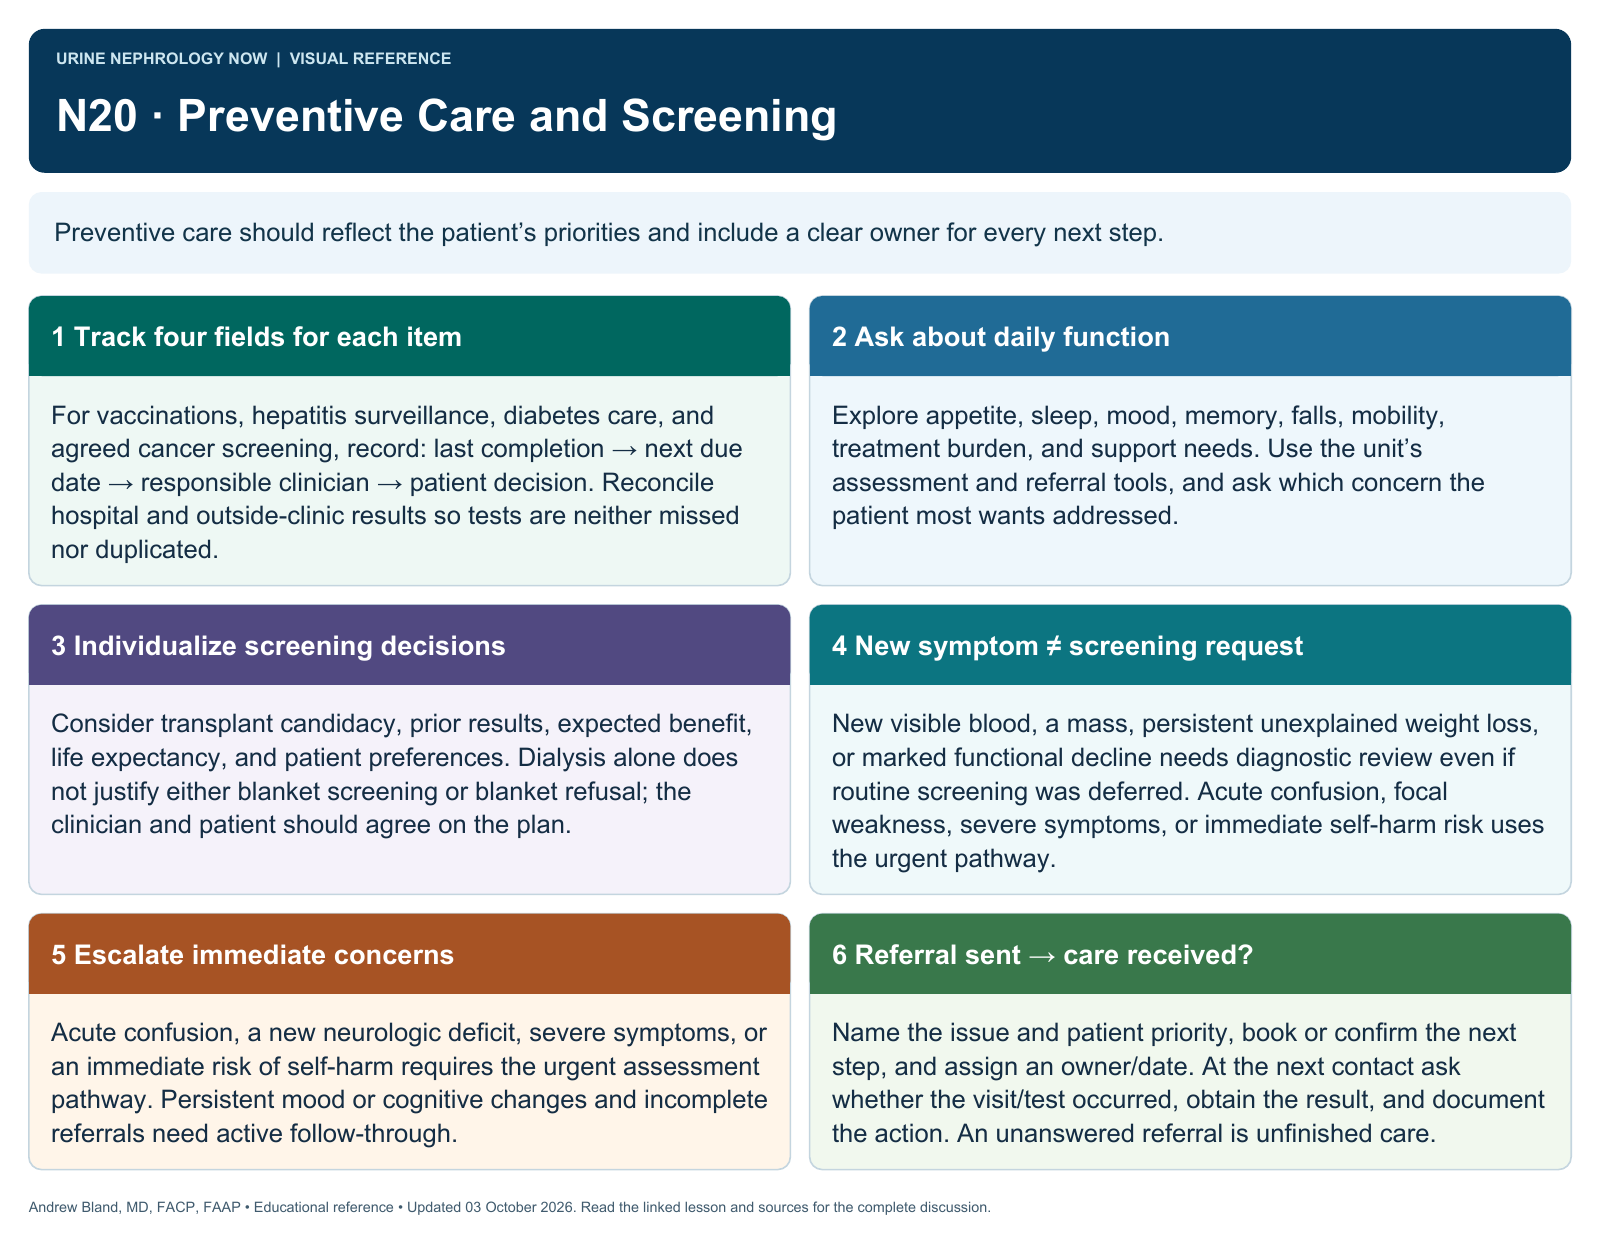
Preventive care should reflect the patient’s priorities and include a clear owner for every next step.
Text version
Track four fields for each item
For vaccinations, hepatitis surveillance, diabetes care, and agreed cancer screening, record: last completion → next due date → responsible clinician → patient decision. Reconcile hospital and outside-clinic results so tests are neither missed nor duplicated.
Ask about daily function
Explore appetite, sleep, mood, memory, falls, mobility, treatment burden, and support needs. Use the unit’s assessment and referral tools, and ask which concern the patient most wants addressed.
Individualize screening decisions
Consider transplant candidacy, prior results, expected benefit, life expectancy, and patient preferences. Dialysis alone does not justify either blanket screening or blanket refusal; the clinician and patient should agree on the plan.
New symptom ≠ screening request
New visible blood, a mass, persistent unexplained weight loss, or marked functional decline needs diagnostic review even if routine screening was deferred. Acute confusion, focal weakness, severe symptoms, or immediate self-harm risk uses the urgent pathway.
Escalate immediate concerns
Acute confusion, a new neurologic deficit, severe symptoms, or an immediate risk of self-harm requires the urgent assessment pathway. Persistent mood or cognitive changes and incomplete referrals need active follow-through.
Referral sent → care received?
Name the issue and patient priority, book or confirm the next step, and assign an owner/date. At the next contact ask whether the visit/test occurred, obtain the result, and document the action. An unanswered referral is unfinished care.