Visual summary
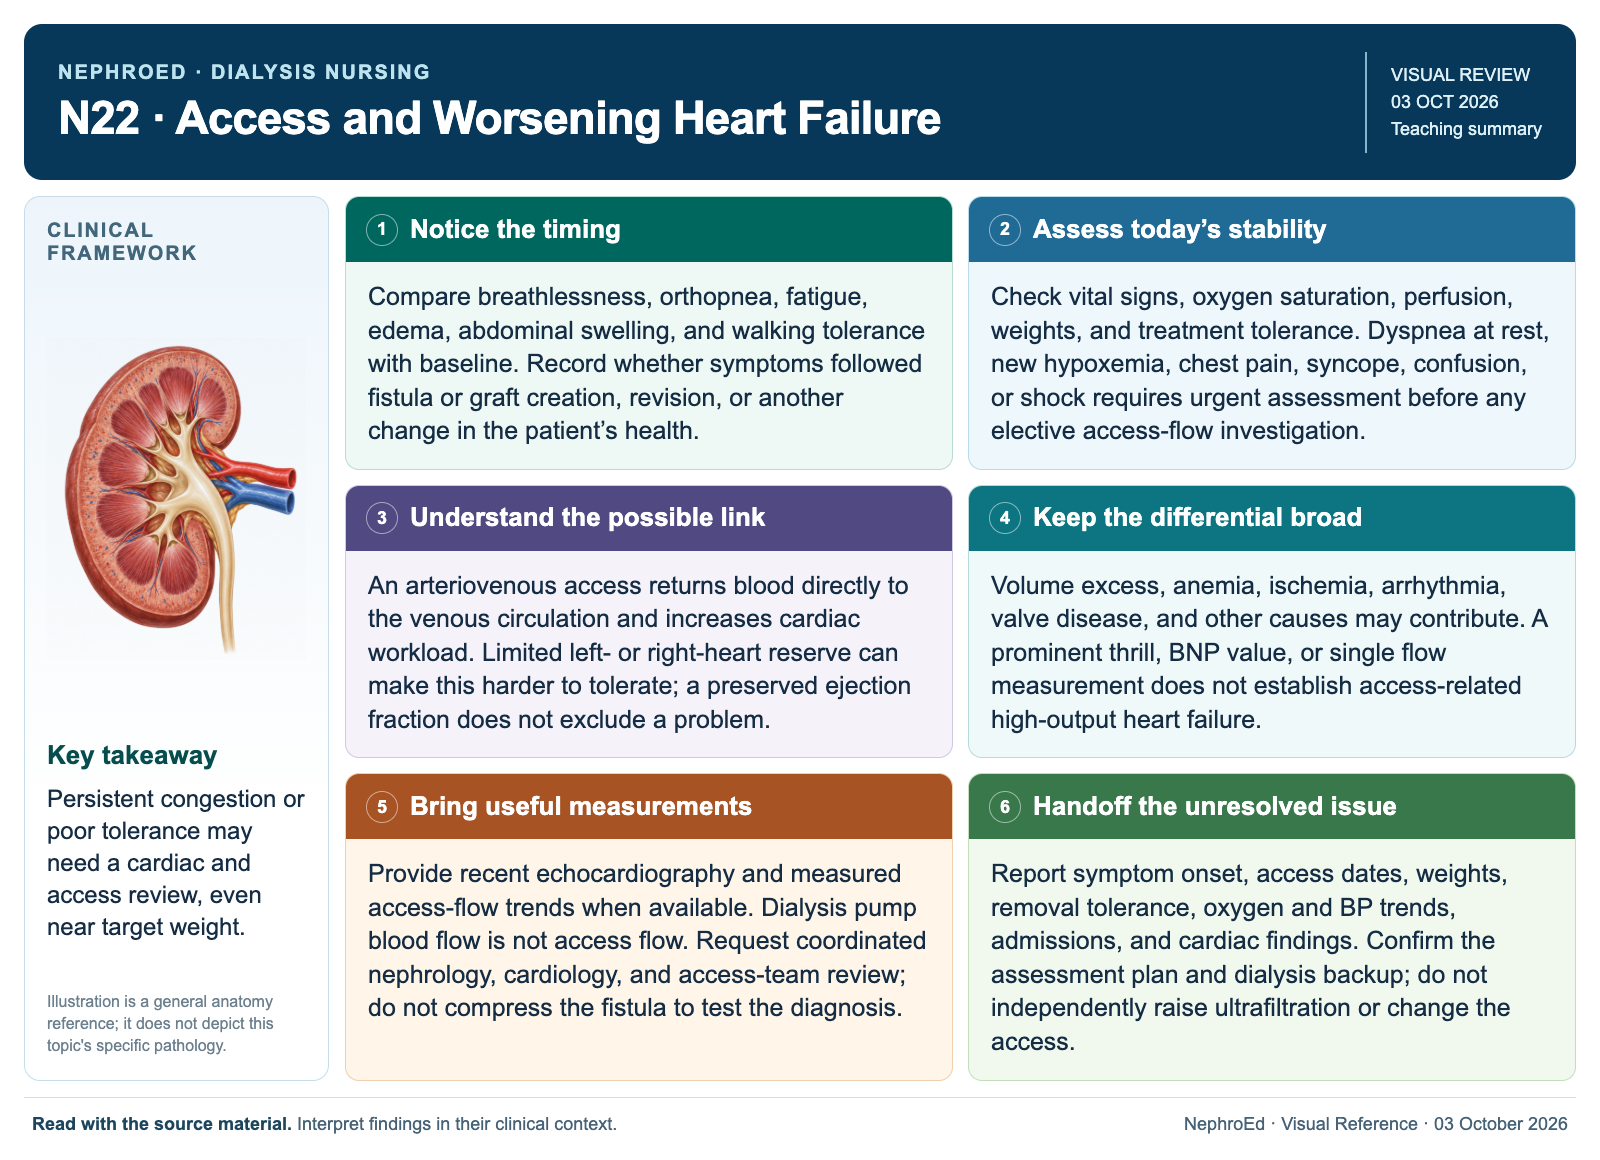
Persistent congestion or poor tolerance may need a cardiac and access review, even near target weight.
Text version
Notice the timing
Compare breathlessness, orthopnea, fatigue, edema, abdominal swelling, and walking tolerance with baseline. Record whether symptoms followed fistula or graft creation, revision, or another change in the patient’s health.
Assess today’s stability
Check vital signs, oxygen saturation, perfusion, weights, and treatment tolerance. Dyspnea at rest, new hypoxemia, chest pain, syncope, confusion, or shock requires urgent assessment before any elective access-flow investigation.
Understand the possible link
An arteriovenous access returns blood directly to the venous circulation and increases cardiac workload. Limited left- or right-heart reserve can make this harder to tolerate; a preserved ejection fraction does not exclude a problem.
Keep the differential broad
Volume excess, anemia, ischemia, arrhythmia, valve disease, and other causes may contribute. A prominent thrill, BNP value, or single flow measurement does not establish access-related high-output heart failure.
Bring useful measurements
Provide recent echocardiography and measured access-flow trends when available. Dialysis pump blood flow is not access flow. Request coordinated nephrology, cardiology, and access-team review; do not compress the fistula to test the diagnosis.
Handoff the unresolved issue
Report symptom onset, access dates, weights, removal tolerance, oxygen and BP trends, admissions, and cardiac findings. Confirm the assessment plan and dialysis backup; do not independently raise ultrafiltration or change the access.
Continue learning
This graphic summarizes a topic. The full educational pages provide the broader discussion and references.