Visual summary
Follow the patient, electrolytes, and kidney trajectory; CK helps identify muscle injury but does not by itself dictate treatment.
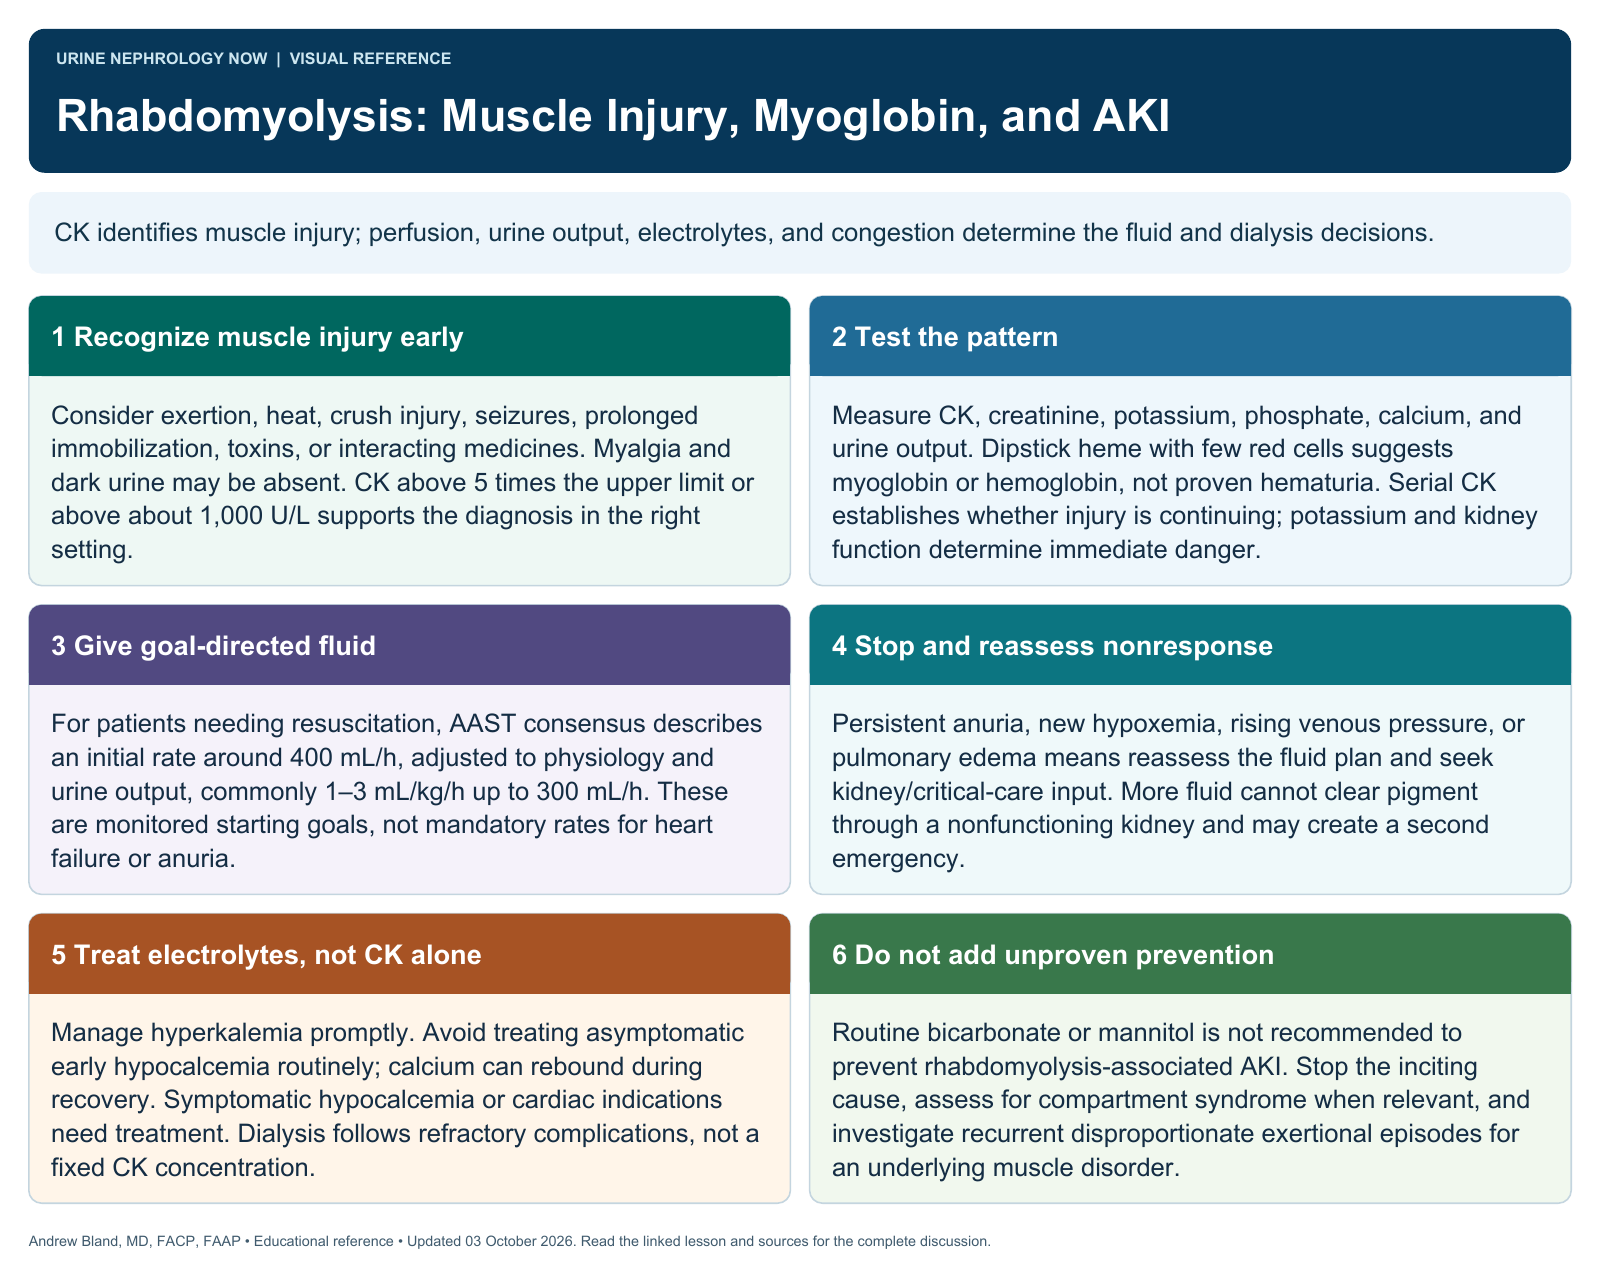
Text version
Muscle contents enter circulation
Muscle injury releases creatine kinase, myoglobin, potassium, and phosphate. Kidney injury can reflect pigment toxicity, tubular obstruction, reduced perfusion, and additional clinical insults; CK is a marker rather than the toxin.
Recognize beyond the triad
Myalgia, weakness, and dark urine are helpful when present but are not required. Ask about exertion, immobilization, seizures, medications, toxins, heat exposure, and trauma; look for compartment syndrome when clinically relevant.
Evaluate severity
Follow CK trend, creatinine, potassium, calcium, phosphate, and urine output. A heme-positive dipstick with few red cells suggests pigment, but is not specific. Risk assessment should incorporate physiology and laboratory trends.
Treat the cause and circulation
Stop the inciting exposure and provide appropriate fluid resuscitation when depleted. Reassess congestion and urine output frequently. Treat dangerous electrolyte abnormalities promptly and use dialysis for established indications.
Applied case: exertional injury
Case 10 links intense exercise with muscle injury and evolving renal risk. The teaching sequence is recognition, electrolyte surveillance, individualized hydration, and a gradual return to activity after clinical recovery.
Expect changing recovery needs
Electrolytes can change during recovery, including calcium rebound. A single CK cutoff does not determine dialysis need. Routine bicarbonate or mannitol should not be presented as established prevention for every patient.
Continue learning
This graphic summarizes a topic. The full educational pages provide the broader discussion and references.