Visual summary
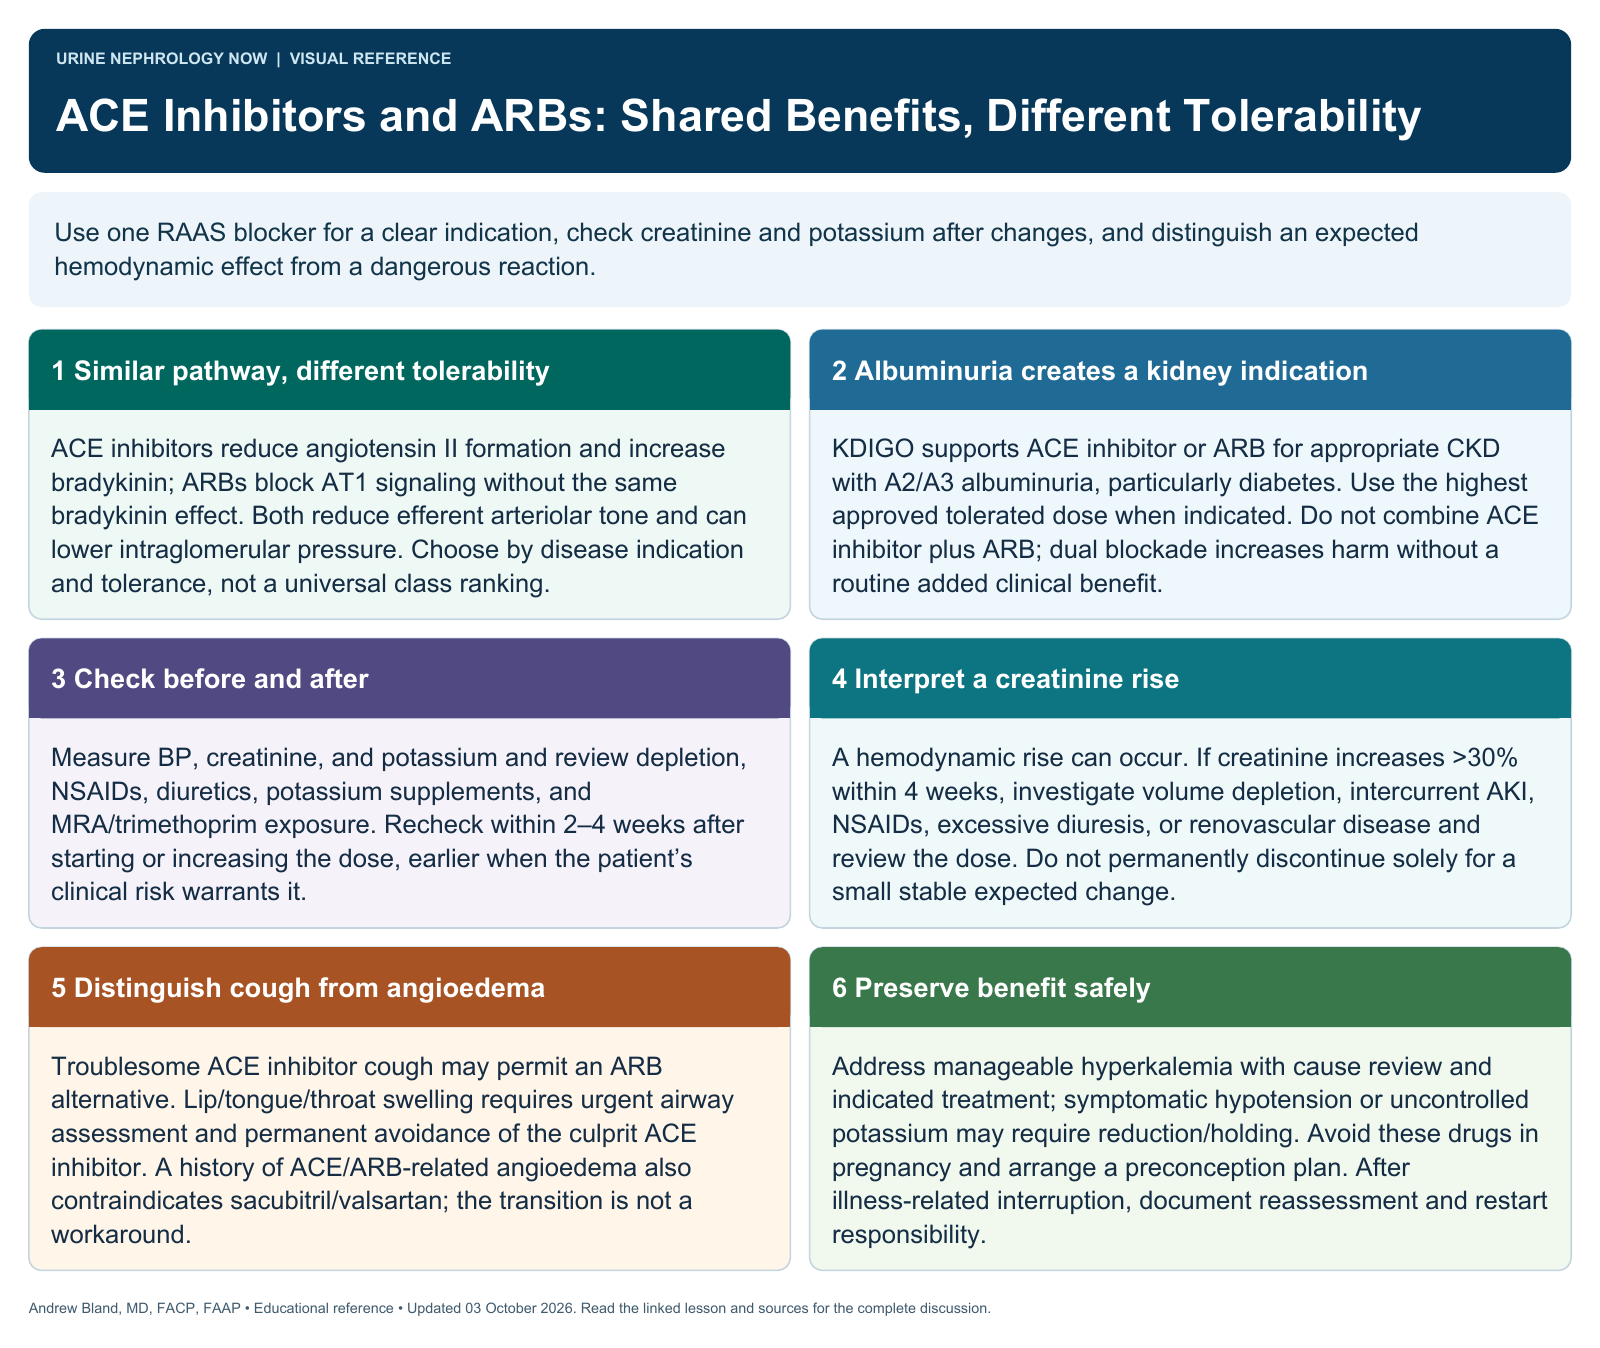
Use one RAAS blocker for a clear indication, check creatinine and potassium after changes, and distinguish an expected hemodynamic effect from a dangerous reaction.
Text version
Similar pathway, different tolerability
ACE inhibitors reduce angiotensin II formation and increase bradykinin; ARBs block AT1 signaling without the same bradykinin effect. Both reduce efferent arteriolar tone and can lower intraglomerular pressure. Choose by disease indication and tolerance, not a universal class ranking.
Albuminuria creates a kidney indication
KDIGO supports ACE inhibitor or ARB for appropriate CKD with A2/A3 albuminuria, particularly diabetes. Use the highest approved tolerated dose when indicated. Do not combine ACE inhibitor plus ARB; dual blockade increases harm without a routine added clinical benefit.
Check before and after
Measure BP, creatinine, and potassium and review depletion, NSAIDs, diuretics, potassium supplements, and MRA/trimethoprim exposure. Recheck within 2–4 weeks after starting or increasing the dose, earlier when the patient’s clinical risk warrants it.
Interpret a creatinine rise
A hemodynamic rise can occur. If creatinine increases >30% within 4 weeks, investigate volume depletion, intercurrent AKI, NSAIDs, excessive diuresis, or renovascular disease and review the dose. Do not permanently discontinue solely for a small stable expected change.
Distinguish cough from angioedema
Troublesome ACE inhibitor cough may permit an ARB alternative. Lip/tongue/throat swelling requires urgent airway assessment and permanent avoidance of the culprit ACE inhibitor. A history of ACE/ARB-related angioedema also contraindicates sacubitril/valsartan; the transition is not a workaround.
Preserve benefit safely
Address manageable hyperkalemia with cause review and indicated treatment; symptomatic hypotension or uncontrolled potassium may require reduction/holding. Avoid these drugs in pregnancy and arrange a preconception plan. After illness-related interruption, document reassessment and restart responsibility.