Visual summary
The useful question is how this drug and its interactions affect this patient, not whether its marketing category sounds safer.
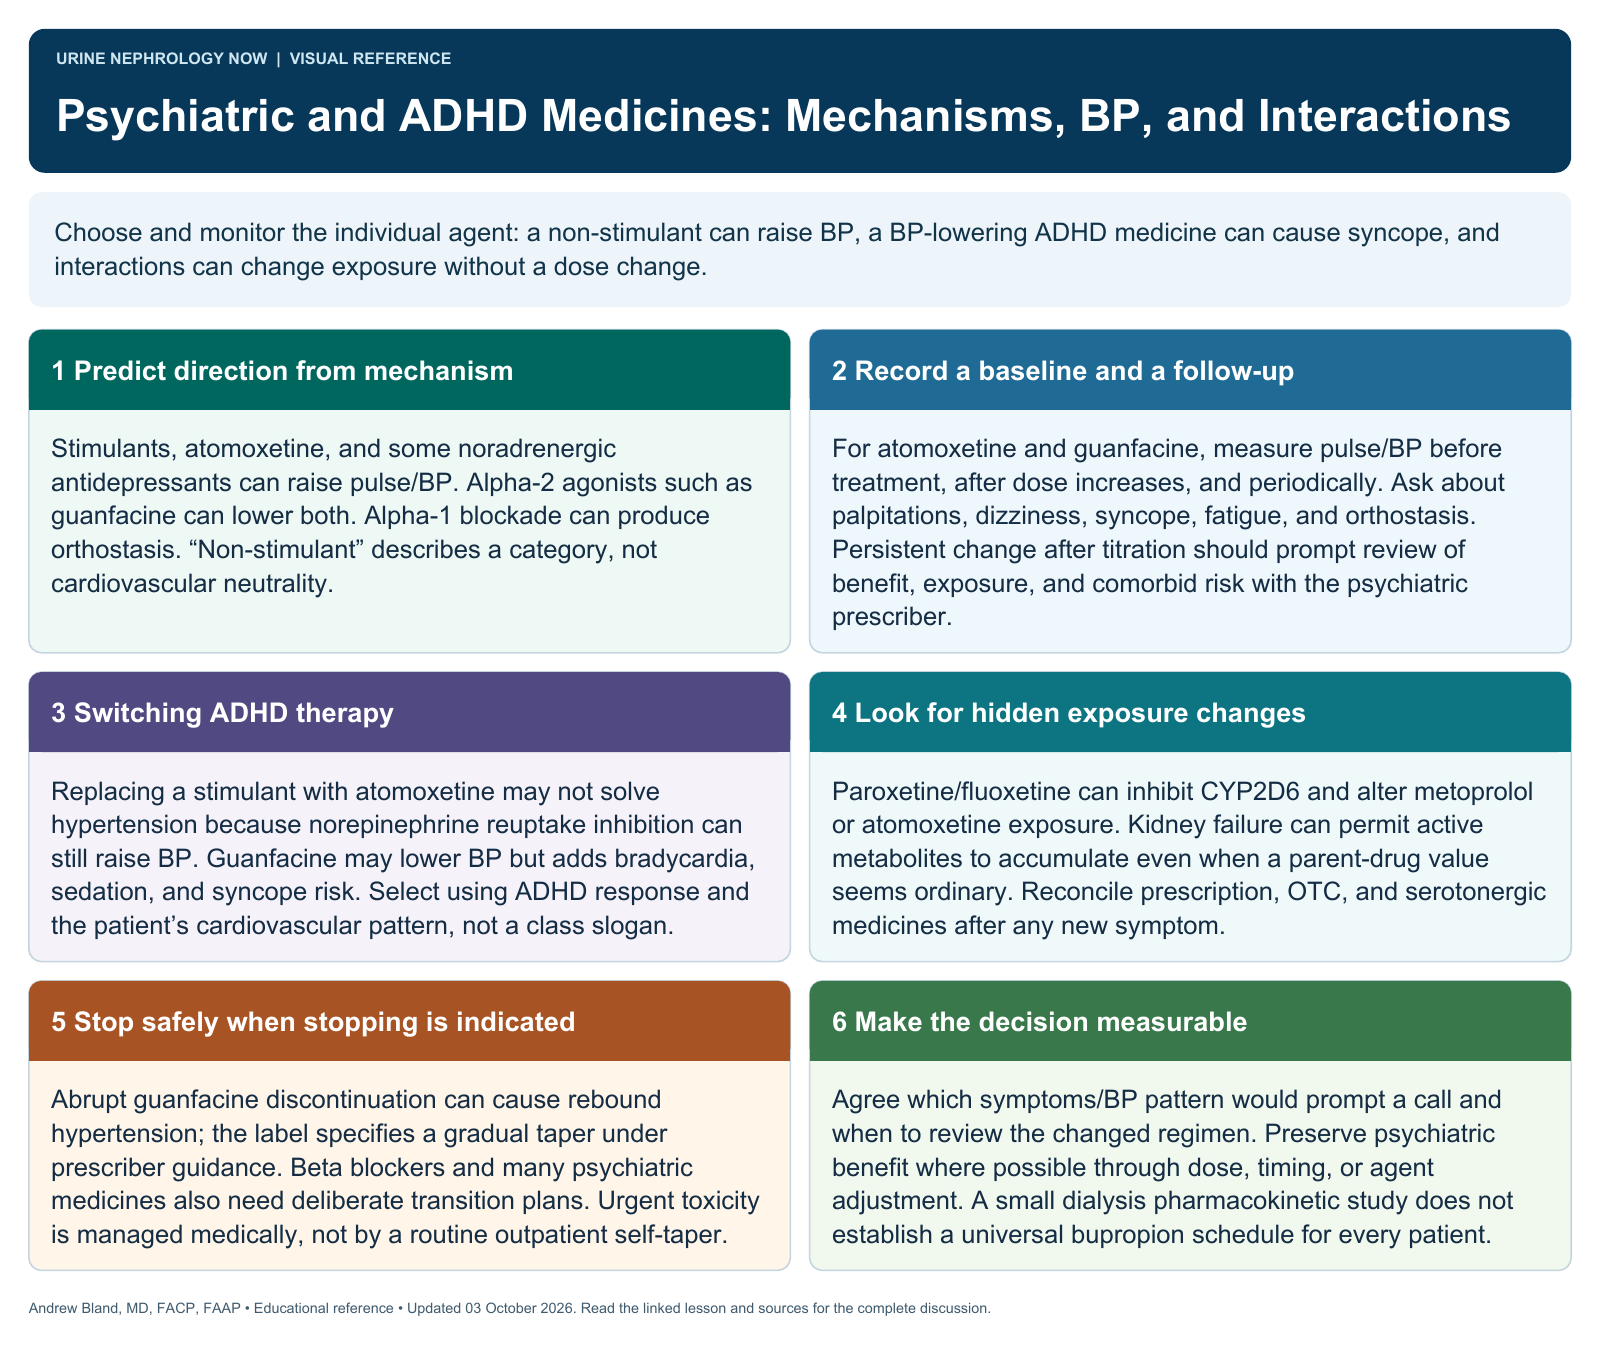
Text version
Mechanism helps predict direction
Noradrenergic effects can raise heart rate or pressure, central alpha-2 agonism can lower them, and alpha-1 blockade can promote orthostasis. Individual drugs, doses, interactions, and patient physiology create exceptions to simple class rules.
Recognize more than hypertension
Monitor palpitations, dizziness, syncope, orthostasis, sedation, and changes after a new drug or dose. Psychiatric benefit and cardiovascular tolerability both matter; the label “non-stimulant” does not guarantee a neutral BP effect.
Review the complete regimen
Check CYP-mediated interactions, serotonergic combinations, other antihypertensives, kidney function, and active metabolites. A new psychotropic may alter exposure to an established cardiovascular drug even when that drug’s dose has not changed.
Coordinate treatment choices
Choose therapy with the mental-health prescriber using symptom control, previous response, BP pattern, comorbidity, and the current product guidance. Avoid replacing an effective treatment based solely on a drug-category label or average trial effect.
Applied reasoning: an ADHD switch
The ADHD medication scenario compares a stimulant with atomoxetine and considers guanfacine. Atomoxetine can increase hemodynamic measures, while guanfacine can cause hypotension or bradycardia; both require patient-specific monitoring.
Avoid absolute safety claims
SSRIs are not free of interactions or all cardiovascular effects, and a small pharmacokinetic study does not establish universal dialysis dosing. Verify renal guidance and arrange monitoring instead of declaring one class safe for every hypertensive patient.
Self-check: Explain how a new psychiatric medication can change the effect of an unchanged cardiovascular prescription through an interaction.
Continue learning
This graphic summarizes a topic. The full educational pages provide the broader discussion and references.