Visual summary
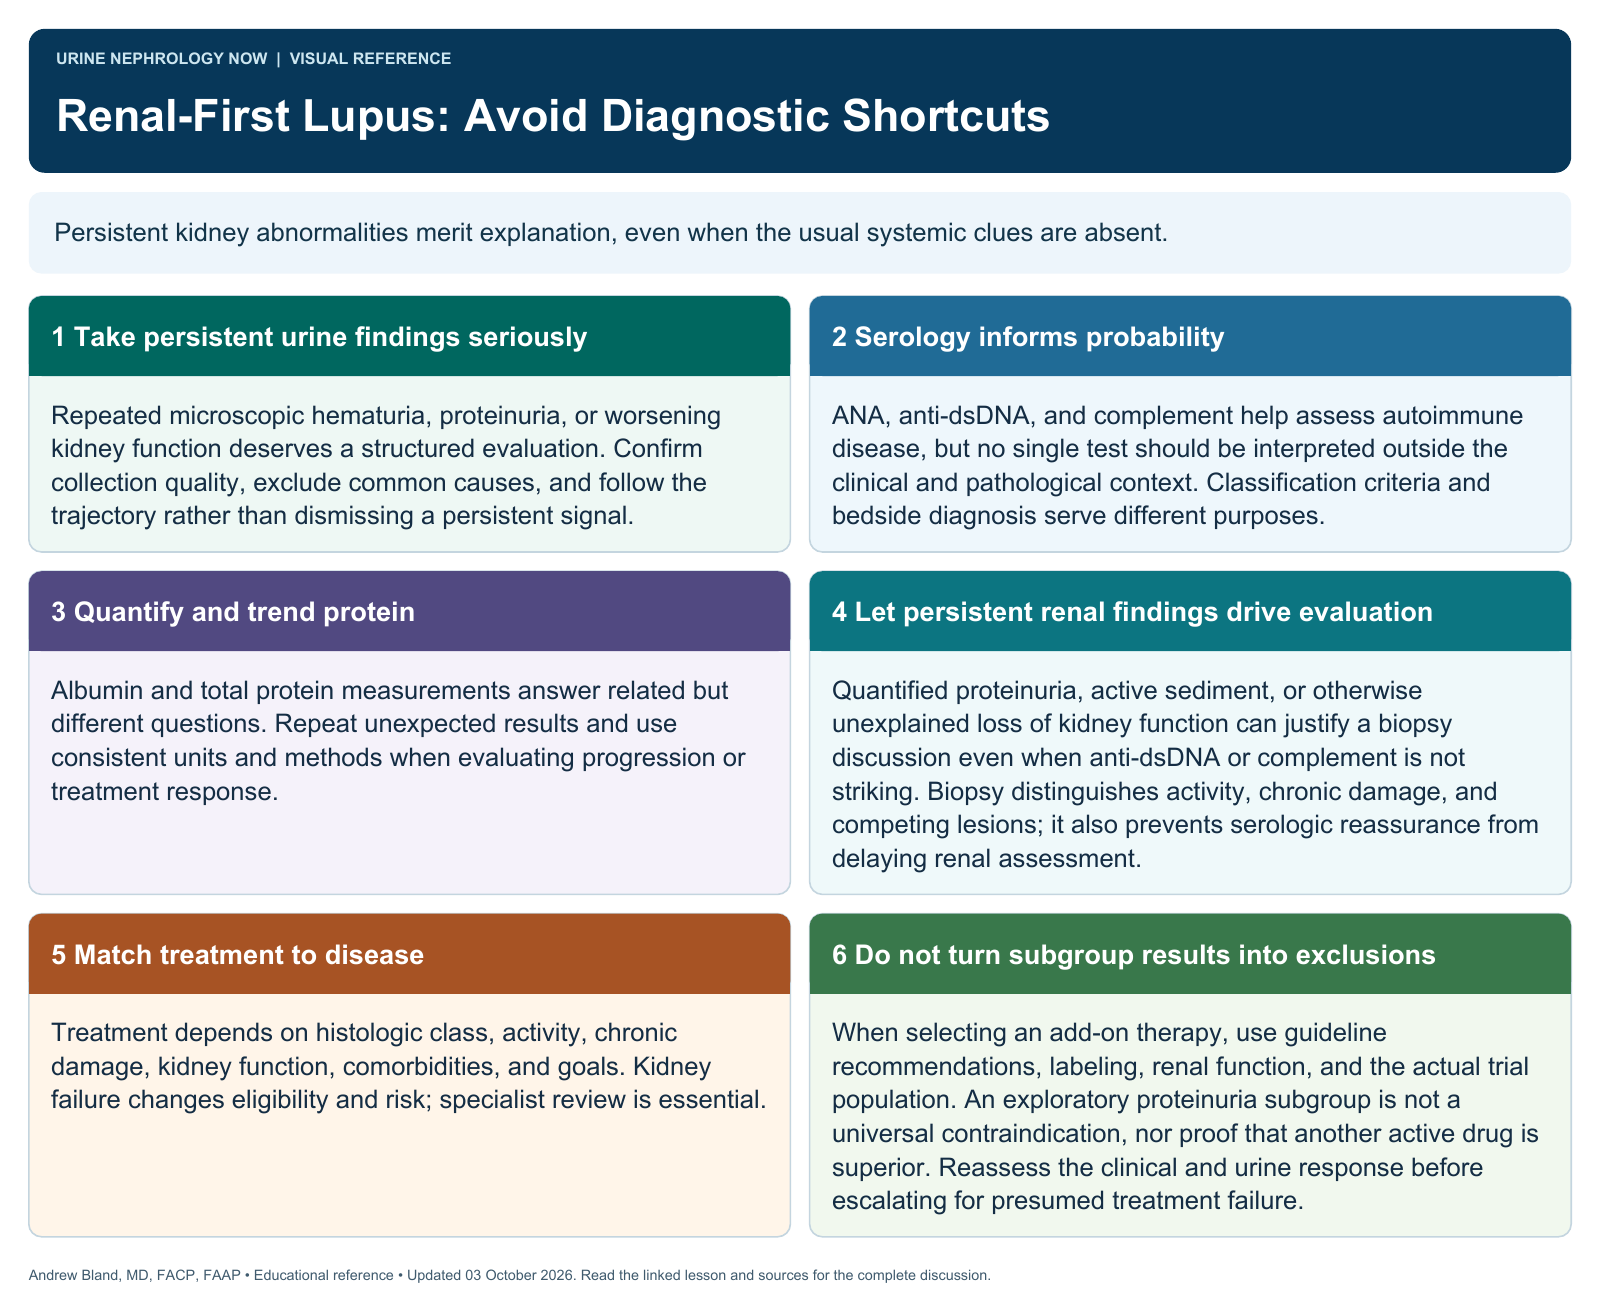
Persistent kidney abnormalities merit explanation, even when the usual systemic clues are absent.
Text version
Take persistent urine findings seriously
Repeated microscopic hematuria, proteinuria, or worsening kidney function deserves a structured evaluation. Confirm collection quality, exclude common causes, and follow the trajectory rather than dismissing a persistent signal.
Serology informs probability
ANA, anti-dsDNA, and complement help assess autoimmune disease, but no single test should be interpreted outside the clinical and pathological context. Classification criteria and bedside diagnosis serve different purposes.
Quantify and trend protein
Albumin and total protein measurements answer related but different questions. Repeat unexpected results and use consistent units and methods when evaluating progression or treatment response.
Use biopsy when indicated
Biopsy can reveal disease severity and activity that routine symptoms or laboratory patterns do not show. Interpret light microscopy, immunofluorescence, and electron microscopy with the clinical presentation.
Match treatment to disease
Treatment depends on histologic class, activity, chronic damage, kidney function, comorbidities, and goals. Kidney failure changes eligibility and risk; specialist review is essential.
Separate evidence levels
Guideline recommendations, trial results, and exploratory subgroup analyses should be labeled distinctly. A subgroup finding cannot automatically dictate an individual regimen, especially outside the trial population.
Continue learning
This graphic summarizes a topic. The full educational pages provide the broader discussion and references.